Category: Autism Challenges

  • What Does an Autism Face Look Like? Understanding Facial Features and Autism

    What Does an Autism Face Look Like? Understanding Facial Features and Autism

    What if there really are subtle facial differences associated with autism? A 2019 study published in Autism Research found that autistic children showed significantly greater facial asymmetry than both typically developing children and their non-autistic siblings. 

    The study examined 84 autistic children, 110 typically developing children and 49 siblings of autistic children using three-dimensional facial imaging. It also found that greater lateral facial asymmetry in autistic children was associated with greater severity of repetitive and restrictive behaviours.

    So, while research is beginning to uncover interesting links between facial characteristics and autism, much more remains to be understood before concluding that appearance alone is diagnostic. Let’s take a closer look at what the research says about the autism face, the facial features being studied, and what they actually mean.

    What Does an Autism Face Look Like?

    Illustration of two boys showing that autistic people have the same range of facial appearances as everyone else

    The simplest answer is that no distinctive autism face exists.

    Autistic people have the same enormous range of facial appearances as everyone else. Some may have round faces; others may have long or narrow faces. Some may have closely set eyes, while others may have widely spaced eyes. Facial symmetry, nose shape, jawline, forehead, lips, skin tone, and other physical characteristics vary naturally from person to person.

    So, if you are searching for an autism face because you want to know whether a child “looks autistic”, facial appearance cannot provide that answer.

    The confusion often comes from grouping two different things: facial structure and facial behaviour.

    Facial structure refers to physical characteristics such as the shape and proportions of the face. Facial behaviour refers to things such as eye contact, facial expressions, and how someone responds to another person’s expression.

    Autism can involve differences in social communication, including how some people use eye contact, gestures, and facial expressions. These are behavioural and communication characteristics. They should not be confused with a particular physical appearance.

    Is There Really an Autism Face?

    Illustrated boy with a question mark, explaining that autism face is an online phrase, not a clinical term

    The phrase autism face is popular online, but it is not a clinical term.

    Researchers have investigated whether autistic people may show subtle differences in facial morphology. Facial morphology refers to the study of facial shape, proportions, and structure. Some research has reported differences between groups of autistic and non-autistic participants.

    However, it is important to distinguish between a research finding and a diagnostic feature.

    If a study finds that a particular facial measurement occurs more often in one group, that does not mean everyone in that group has the feature. It also does not mean that someone with that feature belongs to that group.

    More recent research continues to investigate the subject, but it has not established a universal facial pattern that can be used to identify autism.

    Autism Face vs Normal Face: Is There a Difference?

    Autism face vs normal face: illustration explaining that facial structure varies naturally and cannot diagnose autism

    No scientifically meaningful autism face vs normal face comparison exists.

    The word “normal” can make this question particularly misleading. Human faces naturally differ in thousands of ways, and no single facial template represents a normal person.

    More importantly, autism is a neurodevelopmental condition. Diagnostic features relate primarily to social communication and interaction, along with associated developmental characteristics.

    Facial structure is not a diagnostic criterion.

    This means that putting an autistic person’s photograph next to a non-autistic person’s photograph cannot provide a reliable way of identifying autism.

    Even when researchers find measurable differences between groups, substantial overlap remains. A statistical difference between two groups does not automatically create a visible boundary between them.

    Think about height. If one population has a different average height from another, you could not determine a person’s population simply by looking at them. Facial measurements work similarly. Group-level patterns do not become individual diagnostic tests.

    Do Autistic People Have Different Eyes?

    Illustrated eyes showing that no eye shape, colour or spacing indicates autism, though eye contact may differ

    The eyes are probably the most discussed part of the autistic face. However, no specific eye shape indicates autism.

    Researchers have studied gaze behaviour more extensively. Some autistic people may use eye contact differently from non-autistic people. They may look at eyes less often, find prolonged eye contact uncomfortable, or focus on other areas of a person’s face.

    But these patterns vary considerably. Some autistic people make frequent eye contact. Some may make eye contact in familiar situations but not in stressful or unfamiliar ones. Others may consciously learn social expectations around eye contact.

    NIMH lists inconsistent eye contact among possible social communication characteristics of autism, but also emphasises that not every autistic person displays every characteristic.

    This is why “autistic eyes” should not be treated as a medical category.

    Eye colour, eye shape, eyelid shape or the physical spacing of the eyes cannot establish whether someone is autistic.

    Can Facial Expressions Be Different in Autism?

    Illustration of a boy with raised hands explaining how some autistic people use or read facial expressions differently

    Yes, facial expressions can sometimes be different in autistic people, but this is not the same thing as having a different face. Some autistic children may use fewer facial expressions or express emotions in ways that others find less predictable. Others may have highly expressive faces.

    Some people may also find it difficult to interpret subtle changes in another person’s facial expression. The NHS notes that autistic children may use fewer facial expressions and may respond differently to other people’s facial expressions or feelings.

    However, this does not mean that autistic people lack emotions or cannot understand other people’s feelings. Facial expression is only one way humans communicate emotion. Tone of voice, body language, gestures, words, and context all contribute to communication.

    Is There a Mild Autism Face?

    Illustrated boy explaining there is no recognised mild autism face and features cannot show support needs

    There is no recognised mild autism face.

    The phrase “mild autism” is commonly used in everyday conversation, but facial appearance cannot tell you how much support an autistic person needs. Autism is a spectrum, and people can have very different profiles of strengths, difficulties and support requirements. Someone may communicate verbally but struggle considerably with sensory processing, social interaction or daily living. Another person may have significant communication difficulties but strong abilities in another area.

    Therefore, there is no facial shortcut for determining whether autism is “mild”.

    The term can also create an inaccurate assumption that autism is always easy to recognise when support needs are lower.

    They are not.

    A person may appear confident, talkative or socially capable while experiencing substantial internal difficulties. Some autistic people also consciously or unconsciously mask autistic characteristics, making them less obvious to other people. The NHS notes that masking can make autism less noticeable and can be exhausting and stressful.

    Is There a Severe Autism Face?

    Illustration explaining there is no severe autism face and appearance cannot indicate a person’s support needs

    There is no medically recognised severe autism face either.

    A person’s facial appearance cannot tell you whether they have high support needs.

    This is particularly important because the language of “mild” and “severe” can oversimplify autism. Support needs may vary across communication, learning, sensory processing, behaviour, independence and daily living.

    No facial feature can tell a parent whether a child has low or high support needs.

    The right question is not “What does severe autism look like?” It is “What support does this individual need?”

    What Should Parents Look For Instead of Autism Face Features?

    Illustrated family with puzzle pieces: parents can observe social, sensory and behavioural signs, not facial features

    If you are concerned that your child may be autistic, developmental behaviour is much more informative than facial appearance.

    Look at patterns over time rather than focusing on one characteristic.

    Social communication

    Possible differences can include:

    • not consistently responding to their name
    • limited use of gestures such as pointing or waving towards something
    • difficulty sharing attention or enjoyment
    • difficulty with back-and-forth interaction
    • unusual or delayed development of spoken language
    • difficulty understanding social cues
    • differences in eye contact or facial expression

    Repetitive behaviour and interests

    Some children may:

    • repeat words or phrases
    • repeat movements such as rocking or hand-flapping
    • become distressed by changes in routines
    • develop unusually intense interests
    • play with objects in repetitive ways
    • focus strongly on particular parts of objects

    Sensory differences

    Autistic children may also experience sensory input differently. They may be unusually sensitive or under-responsive to sounds, lights, textures, smells, movement, temperature, or other sensations.

    No single characteristic proves that a child is autistic. The pattern, developmental history, and effect on everyday life matter

    Can a Doctor Diagnose Autism by Looking at the Face?

    Illustrated doctor explaining autism assessment considers development, behaviour and communication, not facial appearance

    No. A clinician may observe a child’s face, eye contact, and facial expressions during an assessment, but they do not diagnose autism based on facial appearance. A proper autism assessment considers development, behaviour, communication, and social interaction.

    Can a Photograph Show Autism?
    Family photo illustration explaining a photograph alone cannot provide enough information to diagnose autism

    A photograph cannot provide enough information to diagnose autism. A photograph captures a single moment. Autism assessment requires information about how a person communicates, behaves, and interacts across situations and over time.

    Even a video provides only part of the picture.

    A child might make excellent eye contact in a familiar environment but behave differently in an unfamiliar clinical setting. Another child may appear socially confident during a short interaction while experiencing significant challenges elsewhere.

    Can Artificial Intelligence Recognise an Autism Face?

    Illustration of a boy and an AI icon explaining AI facial analysis is not a clinically validated autism diagnostic tool

    Artificial intelligence is increasingly being studied in autism research, including research involving facial images and facial measurements.

    That does not mean AI can currently diagnose autism simply by analysing someone’s face.

    Researchers usually train and test models using particular datasets. Sample size, demographic characteristics, image quality, age, ethnicity, camera conditions, and the characteristics of the people included in the dataset can affect their results.

    A model that identifies statistical patterns in a research dataset is not automatically a clinically validated diagnostic tool.

    Five Important Facts to Remember About Autism and Facial Features

    Five facts about autism and facial features: there is no universal autism face and appearance cannot diagnose autism

    If you have come across conflicting information online, these five points can help separate evidence from misconception:

    1. There is no universal autism face.

    Autistic people have diverse facial appearances.

    2. Facial morphology research is real, but it is still research.

    Studies have identified possible group-level differences, but these are not diagnostic criteria.

    3. Facial behaviour is different from facial structure.

    Eye contact, facial expressions, and gaze patterns may differ in some autistic people.

    4. A photograph cannot diagnose autism.

    A diagnosis requires developmental and behavioural information.

    5. Support needs cannot be judged from appearance.

    There is no mild autism face or severe autism face. The required support therefore does not depend on a person’s facial features.

    What Parents Should Do If They Are Concerned?

    Illustrated worried parents, with advice to record communication, behaviour and sensory examples for an autism assessment

    If you are wondering whether your child’s development may indicate autism, start with what you have observed rather than what your child looks like.

    Write down specific examples. For instance, instead of saying “my child seems autistic”, note that your child rarely responds to their name, does not point to share interest, repeats particular phrases, becomes extremely distressed by changes to routine, or has significant sensory reactions.

    Specific observations give professionals much more useful information.

    You can also speak with your child’s paediatrician, developmental specialist, psychologist, or another appropriately qualified professional who can advise whether an autism assessment is warranted.

    How India Autism Center (IAC) Helps Families Understand Autism

    India Autism Centre logo with text on how IAC helps families understand autism communication, development and support

    At India Autism Center, understanding autism goes beyond trying to identify an autism face or a set of facial characteristics. While research continues to explore possible differences in facial appearance and expression, autism assessment focuses on a person’s communication, social interaction, behaviour, development, and individual support needs. 

    For families, reliable information can help separate genuine research findings from misleading online claims about autism face features. India Autism Center provides resources on autism screening, assessment, early intervention and therapies, helping families understand what to look for and when to seek professional guidance. 

    This informed approach keeps the focus on the individual, not appearance.

    Conclusion
    Illustrated family with puzzle pieces and a brain icon: autism is about unique neurodevelopment, not appearance

    An autism face is not defined by one particular shape, expression, or set of facial features. Although research has identified interesting associations between facial asymmetry and autism, appearance alone cannot explain an individual’s developmental profile. 

    What matters is understanding how a person communicates, interacts, behaves, and experiences the world. If you notice developmental differences, look beyond facial features associated with autism and seek a professional assessment for meaningful clarity. 

    Ultimately, autism is about a person’s unique neurodevelopment, not simply what they look like.

    Frequently Asked Questions

    Can facial asymmetry be an autism face feature?

    Research has reported greater facial asymmetry in some autistic children, but it is not a diagnostic feature. Facial asymmetry also occurs naturally in people without autism.

    Is there a specific autism face shape in children?

    No. No single face shape is associated with autism. Facial structure varies considerably among autistic children, just as it does among other children.

    Can widely spaced eyes be an autism face feature?

    No evidence shows that widely spaced eyes can identify autism. Researchers can study individual facial measurements scientifically, but they cannot use them as a diagnostic checklist.

    Are autistic children’s facial features different from other children?

    Some research has identified statistical differences in particular facial measurements between groups, but no universal facial appearance distinguishes autistic children from other children.

    Can facial expressions be different in autistic children?

    Yes, some autistic children may use or interpret facial expressions differently. However, facial expression varies considerably between individuals and should be considered alongside other characteristics rather than viewed as an autism marker.


  • Hyperactive Autism – Symptoms, Causes, and How It Differs From ADHD

    Hyperactive Autism – Symptoms, Causes, and How It Differs From ADHD

    A child who is constantly moving, struggles to sit still, or acts impulsively may be described as having “hyperactive autism”. However, hyperactive autism is not a separate type or diagnosis of autism. 

    Hyperactivity can occur in autistic people for several reasons, including sensory needs, anxiety, communication difficulties, or co-occurring Attention Deficit Hyperactivity Disorder, ADHD. 

    In one study of 3,319 children with autism aged 6 to 17, 45.3% had a reported diagnosis of or treatment for ADHD, highlighting how commonly the two conditions can overlap. 

    Understanding why a person is hyperactive is therefore more useful than simply trying to stop the behaviour.

    What Is Hyperactive Autism?

    What is meant by hyperactive autism, explaining that hyperactivity may occur alongside autism for different reasons.

    Hyperactive autism is a term commonly used to describe an autistic person who displays high levels of movement, restlessness, impulsivity or difficulty staying focused. 

    However, it is important to note that hyperactive autism is not a clinical diagnosis.

    Autism is characterised by differences when it comes to social communication and interaction, along with restricted or repetitive patterns of behaviour, interests or even activities. Hyperactivity is not a core diagnostic feature of autism.

    However, an autistic person may be highly active or restless. The behaviour can have different causes depending on the individual. For example, movement may provide sensory input, while running away from an activity may indicate anxiety, confusion or sensory overload. In other cases, the person may have co-occurring ADHD.

    This distinction matters because the same outward behaviour can have very different underlying causes.

    Instead of asking only, “How can I stop my child from moving so much?”, it is more useful to ask:

    • When does the behaviour occur?
    • What happens immediately before it?
    • Does it happen at home, school and other settings?
    • Is the person trying to communicate a need?
    • Could sensory overload, anxiety, pain or poor sleep be involved?
    • Could ADHD or another co-occurring condition be contributing?

    Symptoms of Hyperactivity in Autism

    Symptoms of hyperactivity in autism including constant movement, impulsivity, pacing and increased activity when overwhelmed.

    There is no official symptom checklist for hyperactive autism because it is not a recognised diagnostic category. However, families and teachers may notice certain behaviours in an autistic person who experiences significant hyperactivity.

    These can include:

    • Constant fidgeting or movement
    • Frequent running, jumping, climbing or pacing
    • Difficulty remaining seated
    • Moving quickly from one activity to another
    • Acting before thinking
    • Interrupting or struggling to wait
    • Difficulty slowing down during transitions
    • Increased activity when anxious or overwhelmed
    • Repeatedly seeking movement or particular sensory experiences
    • Difficulty concentrating on activities that are not highly engaging

    Not every instance of movement should be treated as a problem.

    For some autistic people, repetitive movements or stimming can help regulate sensory input or emotions. If the movement is safe and does not interfere with participation, it may not need to be stopped.

    Instead, focus on whether the behaviour causes distress, creates safety concerns or prevents the person from participating in everyday activities.

    What Causes Hyperactivity in Autism?

    Causes of hyperactivity in autism including co-occurring ADHD, sensory differences, communication difficulties and sleep issues.

    There is no single cause of hyperactivity in autism. Several factors may contribute, and more than one may be present at the same time.

    Co-occurring ADHD

    ADHD is one of the most important conditions to consider when an autistic person shows persistent hyperactivity, impulsivity or inattention.

    Autism and ADHD are separate neurodevelopmental conditions, but they can occur together. NICE recommends considering ADHD as a possible coexisting condition when assessing autistic children and young people.

    When both conditions are present, difficulties with attention, impulse control and activity levels may be more pronounced.

    Sensory differences

    Autistic people can experience sensory input differently. Sounds, lights, textures, crowds or movement may feel overwhelming, while some people actively seek particular sensory experiences.

    A child who repeatedly jumps, spins or runs may therefore be seeking movement or trying to regulate their sensory state rather than simply being unable to behave calmly.

    Understanding sensory processing can help parents and professionals identify what is driving the behaviour.
    Communication difficulties

    Hyperactivity can sometimes respond to an unmet communication need.

    For example, a child who cannot easily say that a classroom is too noisy may leave the room, pace or become increasingly restless. Similarly, frustration with a difficult task may appear as constant movement rather than verbal refusal.

    Improving communication can therefore be an important part of supporting behaviour.

    Anxiety and changes in routine

    Unfamiliar situations, unexpected changes and socially demanding environments can increase anxiety in some autistic people. This may appear as pacing, constant movement, escape behaviours or difficulty settling.

    NICE recommends considering changes to routine, lack of predictability and environmental factors when identifying triggers for challenging behaviour. 

    Sleep and physical discomfort

    Poor sleep can affect daytime attention, regulation and behaviour. Physical discomfort can also result in noticeable behavioural changes.

    If hyperactivity suddenly increases, parents should not automatically assume that the autism has become “worse”. Sleep difficulties, pain, gastrointestinal problems, anxiety, medication effects or environmental changes may need to be considered.

    Hyperactive Autism vs ADHD: What Is the Difference?

    Hyperactive autism vs ADHD illustration explaining key differences between autism-related hyperactivity and ADHD symptoms.

    One of the biggest challenges for parents is distinguishing hyperactivity associated with autism from ADHD.

    The two can look similar, but their defining features are different.

    FeatureHyperactivity associated with autismADHD
    Diagnostic statusNot a separate diagnosisRecognised neurodevelopmental condition
    Social communication differencesMay be present because of autismNot a core diagnostic feature
    Repetitive behavioursMay occur as part of autismNot a defining feature
    HyperactivityCan occur for several reasonsOne of the core symptom domains
    ImpulsivityMay occur, particularly with ADHDCore symptom domain
    Sensory differencesOften relevant in autismNot a defining diagnostic feature
    Need for predictabilityCommonly important in autismNot a core feature
    Co-occurrenceCan occur with ADHDCan occur with autism

    ADHD diagnosis involves looking at persistent symptoms of inattention and/or hyperactivity-impulsivity that cause meaningful impairment.

    This is why a child who is extremely active at home should not automatically be assumed to have ADHD. Equally, persistent hyperactivity should not automatically be attributed to autism.

    Can Autism and ADHD Occur Together?

    Can autism and ADHD occur together? Illustration explaining co-occurring autism and ADHD and related support needs.

    Yes. An individual can meet the core diagnostic criteria for both autism and ADHD.

    This is clinically important because treating only one set of difficulties may leave other needs unaddressed. A child may need support for autistic communication and sensory differences while also requiring ADHD-specific strategies for attention and impulse control.

    How to Reduce Hyperactivity in Autism?

    How to reduce hyperactivity in autism using behaviour support, routines, movement, sensory adjustments and communication strategies.

    Parents looking to reduce hyperactivity in autism should first identify what triggers or maintains the behaviour.

    No universal strategy exists because the right approach depends on the underlying cause.

    Identify patterns and triggers

    A simple behaviour diary can help identify whether hyperactivity occurs around particular situations.

    Record:

    • What happened immediately beforehand
    • What the person did
    • What happened afterwards
    • Time of day
    • Sleep and energy levels
    • Environment and sensory demands
    • Communication or task demands

    Patterns may reveal that the behaviour occurs mainly during transitions, in noisy environments, during difficult tasks or during periods of fatigue.

    Create predictable routines

    Visual schedules, clear instructions and warnings can make transitions easier for autistic children.

    Rather than abruptly ending a preferred activity, a parent might provide a visual or verbal warning and explain what will happen next.

    Provide appropriate movement

    If movement helps with regulation, planned opportunities for physical activity may be useful.

    Movement breaks, outdoor play and age-appropriate physical activities can provide an appropriate outlet without treating movement itself as misbehaviour.

    Reduce sensory overload

    If noise, lighting, crowds or other sensory experiences trigger hyperactivity, environmental changes may help.

    Depending on the person, this could mean using a quieter area, reducing unnecessary background noise or allowing breaks from overwhelming environments.

    An occupational therapist can help assess functional and sensory needs where appropriate.

    Support communication

    If hyperactivity is linked to frustration, communication support may reduce the need for behaviour to communicate a message.

    Speech and language professionals can support communication according to the person’s abilities and needs.

    Autism Hyperactivity Support

    Autism hyperactivity support including behavioural interventions, occupational therapy, speech therapy and educational adjustments.

    There is no single autism hyperactivity support suitable for everyone.

    It is best to identify and address factors that may trigger or maintain challenging behaviour before moving to other interventions. If no underlying physical, mental health, behavioural, or environmental factor is identified, a psychosocial intervention informed by a functional assessment may be considered.

    Depending on the individual’s needs, support may involve:

    • Behavioural or psychosocial intervention
    • Occupational therapy
    • Speech and language therapy
    • Educational adjustments
    • Parent-mediated strategies
    • Support for anxiety or sleep difficulties
    • Assessment and treatment for ADHD where appropriate

    Medication is not used to make an autistic person quieter or easier to manage. If medication is considered, it should be based on an identified clinical need and monitored by an appropriately qualified professional.

    Controlling Hyperactivity in Autism at Home and School

    Controlling hyperactivity in autism at home and school through consistent routines and supportive environments.

    Controlling hyperactivity in autism works best when parents, teachers and professionals understand the behaviour and respond consistently.

    A child may behave differently at home and school because the two environments place different sensory, communication and social demands on them. Useful strategies can include clear instructions, visual supports, predictable routines, manageable task lengths and appropriate movement breaks.

    The objective should not be to eliminate every movement. If a child safely fidgets, rocks or moves while remaining engaged, there may be no reason to stop them.

    On the other hand, if a child repeatedly leaves a classroom because of sensory overload, simply telling them to remain seated is unlikely to address the underlying difficulty.

    The goal is meaningful participation, safety and quality of life.

    When Should Parents Seek Professional Help?

    When parents should seek professional help for autism-related hyperactivity, especially when behaviour affects safety or daily life.

    Professional assessment may be appropriate when hyperactivity:

    • Interferes significantly with learning or daily life
    • Creates safety concerns
    • Occurs consistently across different settings
    • Is accompanied by significant impulsivity or inattention
    • Appears suddenly or becomes substantially worse
    • Occurs alongside major sleep difficulties
    • Causes significant distress
    • Makes communication or participation difficult

    A professional assessment can also help to determine whether the behaviour relates primarily to autism, ADHD, sensory needs, anxiety, communication difficulties, sleep or another physical or developmental issue.

    How India Autism Center Can Help

    India Autism Centre support for individuals with autism and hyperactivity through personalised assessment and behavioural support.

    India Autism Center takes an individualised approach to understanding autism and associated behavioural concerns. Rather than viewing hyperactivity as a behaviour that needs to be stopped, the focus can be on understanding what the behaviour may be communicating and what factors may be contributing to it. 

    Families can benefit from support that considers the individual’s autism assessment, communication profile, sensory processing, developmental needs and possible co-occurring conditions such as ADHD. 

    Where appropriate, areas such as early intervention, occupational therapy, speech and language therapy and parent support can form part of a broader support plan. The emphasis is on helping autistic individuals develop practical skills while supporting their wellbeing, participation and independence.

    Conclusion

    Conclusion on hyperactive autism, highlighting the importance of understanding causes and providing individualised support.

    Hyperactive autism is not a separate autism diagnosis. Hyperactivity in an autistic person can arise from sensory differences, communication difficulties, anxiety, environmental demands, sleep problems or co-occurring ADHD. 

    Understanding the reason behind the behaviour is therefore more important than simply trying to suppress it. A comprehensive assessment can help identify underlying factors and determine whether additional conditions, such as ADHD, are present. 

    With individualised support, environmental adaptations and appropriate professional intervention, families can develop practical ways to support attention, regulation, communication and everyday participation.

    Frequently Asked Questions

    1. Is hyperactive autism a type of autism?

    No. Hyperactive autism is not a recognised clinical subtype of autism. It is an informal term used to describe autistic people who display significant hyperactivity or restlessness.

    1. Can an autistic child also have ADHD?

    Yes. Autism and ADHD can occur together. A professional assessment can determine whether the child meets criteria for both conditions.

    1. How can I tell if hyperactivity is caused by autism or ADHD?

    You can’t reliably determine the cause from hyperactivity alone. Professionals consider the child’s developmental history, attention, impulsivity, social communication, repetitive behaviours, sensory needs and symptoms across different settings.

    1. How can I reduce hyperactivity in autism?

    Start by identifying triggers. Predictable routines, movement opportunities, communication support and adjustments to overwhelming sensory environments may help, depending on the individual’s needs.

    1. Does sensory overload cause hyperactivity in autism?

    Sensory overload can contribute to increased movement or escape behaviour in some autistic people. Understanding the individual’s sensory needs can help identify appropriate environmental adjustments.

    1. Does hyperactivity mean autism is severe?

    No. Hyperactivity does not determine autism severity. Autistic people have different strengths, support needs and developmental profiles.

  • What Is Infantile Autism? Meaning, Definition, Early Signs, Causes and Diagnosis

    What Is Infantile Autism? Meaning, Definition, Early Signs, Causes and Diagnosis

    Autism is increasingly identified in early childhood, but the term infantile autism can be confusing because it is an older diagnostic term rather than a separate condition recognised today. The CDC states that about 1 in 31 children aged eight were identified with autism in its 2022 surveillance data, while NIMH notes that autism symptoms generally emerge during the first two years of life. Research has also identified developmental differences associated with autism as early as infancy.

    Understanding what infantile autism means can help parents recognise developmental differences without jumping to conclusions.

    What Is Infantile Autism?

    The term infantile autism historically referred to a form of autism that became apparent during infancy or early childhood. Psychiatrist Leo Kanner was particularly associated with it. He described a group of children in 1943 with distinctive differences in social interaction, communication, and behaviour.
    Today, the definition of infantile autism is understood differently because autism is no longer divided into the same diagnostic categories used historically. Modern diagnostic systems use the broader term autism spectrum disorder (ASD) or autism. The term “infantile autism” may still appear in older medical literature, educational material, or conversations with parents. Still, it generally refers to autism in which characteristics become apparent very early in development.
    NIMH describes autism as a neurological and developmental disorder affecting how people interact, communicate, learn, and behave. Symptoms generally appear during the first two years of life, although the age at which characteristics become noticeable and the way they present can differ considerably between children.

    This distinction matters. A baby or toddler does not need to display every characteristic associated with historical descriptions of infantile autism to be autistic. Autism is a spectrum, and children can have very different developmental profiles.

    In practical terms, when parents search for infantile autism meaning, they are often trying to answer a more immediate question: Could the developmental differences I am noticing in my baby or toddler be signs of autism?

    You can’t determine the answer from one behaviour or one milestone. Autism identification involves looking at a broader pattern of development, including social communication, interaction, play, behaviour and sensory responses.

    Is Infantile Autism Still a Diagnosis?

    No. Infantile autism is not generally used as a separate diagnosis in current diagnostic practice.

    The DSM-5 (Diagnostic and Statistical Manual) consolidated previously separate autism-related diagnoses into autism spectrum disorder. The spectrum approach recognises that autism can involve different combinations and degrees of support needs rather than fitting neatly into distinct subtypes.

    Therefore, early infantile autism is best understood as a historical or descriptive term for autism characteristics that become evident during infancy or very early childhood.

    This does not mean the developmental differences are less significant. In fact, early detection can be valuable because it allows families and professionals to understand a child’s developmental profile and provide appropriate support.

    It is also important not to interpret “infantile” as meaning that autism only occurs in babies. Autism is a lifelong neurodevelopmental condition. Some children show noticeable characteristics during the first year or two, while others become more clearly identifiable later.

    What Are the Early Signs of Infantile Autism?

    No single behaviour confirms autism in an infant. Many behaviours associated with autism can also occur in children who are developing typically, particularly when they occur occasionally rather than as part of a persistent pattern.

    What matters is the overall developmental picture.

    Possible early characteristics may involve social attention, communication, gestures, play and responses to sensory experiences.

    1. Differences in social communication

    Some infants who receive an autism diagnosis later may show differences in how they engage socially. These can include:

    • Limited or inconsistent eye contact
    • Less frequent social smiling
    • Reduced interest in faces or people
    • Limited sharing of attention or enjoyment
    • Reduced response to social interaction
    • Less use of gestures to communicate
    • Limited response to their name as they grow older

    Importantly, eye contact alone is not a diagnostic test for autism. A child may make limited eye contact for many reasons, and autistic children can also make eye contact.

    The relevant question is whether there is a broader and persistent pattern of differences in social communication.

    2. Differences in early communication

    Communication does not begin with spoken words. Babies communicate through facial expressions, sounds, gestures, eye gaze, body movements and shared attention.

    A child may warrant developmental assessment if there are concerns about:

    • Babbling or vocal development
    • Gestures such as pointing or waving
    • Imitating sounds or actions
    • Sharing attention with caregivers
    • Understanding or responding to simple communication
    • Development or loss of early language skills

    Speech delay can occur in autism, but speech delay by itself does not mean that a child is autistic. Children can have isolated language delays, hearing difficulties, developmental language disorder, and other developmental differences.

    This is why distinguishing speech delay vs autism requires a broader assessment rather than relying on the presence or absence of speech.

    3. Differences in play and interaction

    As children move towards toddlerhood, differences in play may become easier to recognise.

    A child may:

    • Show limited interest in interactive games
    • Prefer repetitive ways of playing
    • Focus intensely on particular parts of toys
    • Repeat the same actions for extended periods
    • Have difficulty with flexible or pretend play
    • Show limited interest in sharing toys or activities with others

    Again, repetitive play does not automatically indicate autism. Young children naturally repeat actions as they learn. Concern increases when repetitive behaviours occur alongside persistent social communication differences or restricted patterns of behaviour.

    4. Sensory differences

    Some autistic children experience sensory input differently. They may be unusually sensitive or less responsive to sounds, textures, movement, lights, smells or other sensations.

    For example, a toddler might become extremely distressed by a particular sound or strongly resist certain textures.

    Sensory differences are recognised as part of autism’s diagnostic characteristics. Still, they are not exclusive to autism. Sensory challenges can occur in children with other developmental or medical conditions and in children without a developmental diagnosis.

    When Can Early Infantile Autism Be Detected?

    One of the most important points for parents is that autism can sometimes be identified surprisingly early, but early signs are not always obvious.

    NIMH reports research showing that developmental differences associated with autism can be observed in some infants before their first birthday. However, this research should not be interpreted as meaning that a parent can diagnose autism by observing eye contact in a young baby.

    Infant development is highly variable. Some early differences become clearer with age, while some children initially appear to develop typically and later show a noticeable change in social communication or behaviour.

    NIMH states that autism can usually be reliably diagnosed by age two when an appropriate evaluation is available. However, diagnosis may occur earlier or much later, depending on the child and circumstances.

    This is one reason developmental monitoring matters.

    What Are the Causes of Infantile Autism?

    Parents searching for infantile autism causes are often looking for one identifiable reason. Current science does not support that explanation.

    Autism does not have one single cause. Research indicates that genetic factors and aspects of the prenatal and early developmental environment can influence the likelihood of autism. These factors can interact in different and complex ways and affect brain development.

    Genetic factors

    Genetics plays a substantial role in autism.

    Researchers have identified numerous genetic variations associated with autism, but there is no single “autism gene” responsible for all cases. Some genetic conditions, including Fragile X syndrome and Down syndrome, are associated with a higher likelihood of autism. Having a sibling with autism is also associated with an increased likelihood.

    Importantly, having a genetic factor associated with autism does not mean that a child will necessarily be autistic.

    The genetic architecture of autism is complex. Different combinations of inherited genetic variation and, in some cases, newly occurring genetic changes may contribute to differences in neurodevelopment.

    Prenatal and developmental factors

    Research has also identified several factors associated with increased likelihood of autism. These include certain pregnancy and birth-related factors, although an association does not mean that the factor directly causes autism.

    NIMH identifies factors such as having older parents and very low birth weight among factors associated with increased likelihood.

    Researchers continue to investigate how genetic susceptibility interacts with biological and environmental influences during brain development.

    It is therefore more accurate to talk about risk factors for autism than to suggest a simple list of causes.

    What does not cause autism?

    what does not cause autism

    Several persistent myths about autism can create unnecessary guilt and confusion for parents.

    Vaccines do not cause autism. Extensive research has found no credible evidence establishing a causal relationship between vaccination and autism.

    Autism is also not caused by poor parenting, a lack of affection, a child’s personality, or a failure by parents to provide enough social interaction.

    Parents should not blame themselves for their child’s neurodevelopmental differences.

    What about autism screening?

    about autism screening

    Screening and diagnosis are not the same thing.

    A screening tool estimates whether a child may have characteristics associated with autism and whether further assessment may be appropriate. It does not establish a diagnosis.

    For toddlers, validated screening instruments can help identify children who may benefit from a comprehensive evaluation.

    Parents should also remember that they can discuss developmental concerns with a professional even when a child is younger than the usual screening age.

    If a child shows developmental regression, particularly a loss of language or social skills, discuss it promptly with a healthcare professional. NICE recommends referral to an autism team for children younger than three when there is regression in language or social skills.

    Does Infantile Autism Mean a Child Will Have Severe Autism?

    No. The age at which autism characteristics become noticeable does not determine the eventual level of support a person will require.

    Autism is a spectrum, and support needs can vary significantly. Some children have substantial support needs across communication, learning and daily living. Others have relatively greater independence but may still need targeted support for social communication, sensory processing, emotional regulation, education or employment.

    The term early infantile autism therefore should not be used to predict a child’s future abilities.

    Assess a child’s developmental profile individually and revisit it as they grow.

    What Should Parents Do If They Notice Early Signs?

    The most useful response to developmental concerns is not panic and not prolonged waiting. It is assessment.

    If you notice persistent differences in communication, social interaction, play, or behaviour, start by discussing them with a qualified healthcare or developmental professional.

    Parents can make the assessment more useful by keeping a simple record of developmental observations. Videos of everyday behaviours can sometimes help professionals understand what parents have noticed, although they should not replace an in-person assessment.

    It is also helpful to record:

    • When a developmental concern was first noticed
    • Skills the child has gained
    • Skills that appear delayed
    • Any skills that have been lost
    • How the child communicates needs
    • Responses to their name and social interaction
    • Repetitive behaviours or unusual sensory responses
    • Concerns raised by childcare or other caregivers

    Most importantly, do not wait for every possible sign to appear before seeking professional advice.

    How India Autism Center Can Help Families Understand Autism

    At India Autism Center, we do not focus on assigning a diagnostic label. Understanding autism means understanding the child behind the diagnosis, including their communication style, strengths, developmental needs, sensory profile and ability to participate in everyday life. Early identification can help families make informed decisions about assessment, early intervention and education without relying on myths or unsupported claims. Through evidence-informed resources, multidisciplinary perspectives and family-centred support, IAC aims to help parents navigate autism with greater clarity.

    Conclusion

    The term infantile autism has historical roots, but modern professionals generally use autism spectrum disorder to describe the condition. Its characteristics can emerge during infancy or the toddler years, particularly through differences in social communication, language, play, repetitive behaviour and sensory processing. No single cause or diagnostic test exists. If developmental concerns persist, professional assessment is more useful than waiting for symptoms to become more pronounced. Early identification can help families access appropriate support sooner while allowing the child’s individual strengths and needs to guide intervention.

    Frequently Asked Questions

    Is infantile autism the same as autism spectrum disorder?

    The terms are related, but infantile autism is an older diagnostic term. Modern diagnosis generally uses autism spectrum disorder, which reflects the broad variation in autistic characteristics and support needs.

    What are the early signs of infantile autism?

    Possible signs include limited social engagement, differences in eye contact, reduced response to social interaction, delayed gestures or communication, repetitive behaviours and sensory differences.

    Does delayed speech mean a child has infantile autism?

    No. Speech delay can occur for many reasons. Autism is associated with broader patterns involving social communication and restricted or repetitive behaviours.

    Can early intervention cure autism?

    No. Autism is a lifelong neurodevelopmental condition. Early intervention aims to support communication, learning, independence, participation and quality of life.

    Can a child outgrow infantile autism?

    Autism is a lifelong neurodevelopmental condition. However, skills, communication abilities, independence and support needs can change significantly over time.

  • Regressive Autism: Causes, Signs, Diagnosis and What Families Need to Know

    Regressive Autism: Causes, Signs, Diagnosis and What Families Need to Know

    Watching a child lose skills they had already developed can be confusing and emotionally overwhelming for any parent. A toddler who once spoke simple words, responded to their name, or enjoyed social interaction may gradually stop doing so, raising questions about their development. 

    This pattern, known as regressive autism, is a recognised presentation of autism spectrum disorder (ASD). Research suggests that one-third of children diagnosed with autism spectrum disorder experience some form of developmental regression, most commonly during the preschool years. 

    Hence, understanding the signs of autism regression, when it typically occurs, and the support available can help families seek timely intervention and improve long-term developmental outcomes.

    What Is Regressive Autism?

    What is regressive autism and how previously developed skills may be lost in children

    Regressive autism refers to a pattern of autism spectrum disorder (ASD) in which a child appears to develop typically during infancy before losing previously acquired skills. This loss may involve speech, communication, social interaction, play, or everyday abilities that had already been learned.

    Unlike children who show signs of autism from infancy, children with regressive autism often meet developmental milestones initially. Parents may notice that their child has started using words, responding to their name, making eye contact, or engaging in pretend play before these abilities gradually or suddenly disappear.

    Although regressive autism is recognised as a developmental pattern within ASD, it is not considered a separate diagnosis. Instead, it describes how autism presents in certain individuals.

    What Is Autism Regression?

    Autism regression explained as loss of speech, social, play or daily living skills

    Autism regression describes the loss of developmental skills after a period of seemingly typical progress. The changes may happen over several weeks or months rather than overnight.

    Regression may affect one or several areas of development, including:

    • Spoken language
    • Social communication
    • Eye contact
    • Gestures such as pointing or waving
    • Play skills
    • Adaptive daily living skills
    • Emotional responsiveness

    Some children lose only a few words, while others experience more noticeable declines across multiple developmental domains.

    When Does Autism Regression Happen?

    When autism regression happens after a child has developed early communication and social skills

    One of the most common questions parents ask is, “When does autism regression happen?“

    For most children, regression occurs between 15 and 30 months, with many cases becoming noticeable around 18 to 24 months.

    During this period, parents may observe that a child who previously:

    • Used several meaningful words
    • Enjoyed interactive games
    • Smiled socially
    • Responded consistently to their name
    • Imitated actions
    • begins to lose these abilities.

    The timing often coincides with rapid brain development, which may explain why developmental differences become more apparent during toddlerhood.

    It is important to remember that not every child experiences regression in the same way. Some children show gradual changes over several months, while others experience more noticeable losses within a shorter period.

    Understanding Developmental Regression in Autism

    Developmental regression in autism involving loss of previously acquired communication and social skills

    The term developmental regression in autism refers specifically to the loss of developmental milestones after they have already been achieved.

    Regression may involve:

    Communication

    Children may stop using words they had previously learned or become less interested in communicating with others.

    Social Interaction

    Parents may notice reduced eye contact, fewer smiles, limited interest in family members, or withdrawal from social activities.

    Play Skills

    Pretend play may disappear, and children may instead engage in repetitive behaviours or focus intensely on specific objects.

    Daily Living Skills

    Some children experience difficulties with self-feeding, dressing, or toilet training after previously making progress.

    Not every developmental delay represents regression. Some children acquire skills more slowly, whereas regression involves an actual loss of abilities that were consistently demonstrated before.

    What Are the Common Signs of Regressive Autism?

    common signs of regressive autism

    Recognising the early signs allows families to seek professional assessment without unnecessary delay. Here are the common signs that may occur:

    Loss of Speech: One of the earliest indicators is losing words that were previously used meaningfully. A child who regularly said “mummy” or “ball” may gradually stop speaking altogether.

    Reduced Social Engagement: Children may become less interested in interacting with parents or siblings and may stop responding consistently to their name.

    Limited Eye Contact: Parents often notice that eye contact becomes less frequent than before.

    Changes in Play: Interactive games may be replaced by repetitive activities such as spinning objects, lining up toys, or repeatedly opening and closing doors.

    Increased Repetitive Behaviours: Children may begin displaying repetitive hand movements, rocking, spinning, or strong preferences for routines.

    Sensory Differences: Some children become unusually sensitive to sounds, textures, lights, or certain foods during or after regression.

    A qualified developmental paediatrician or multidisciplinary autism assessment team should always evaluate these changes.

    Does Speech Regression Always Mean Autism?

    speech regression

    This is a common concern, but the answer is no; regression does not always mean autism. Although speech regression is an important warning sign, it does not automatically indicate autism.

    Speech loss may also occur due to:

    • Hearing impairment
    • Childhood apraxia of speech
    • Certain neurological conditions
    • Epilepsy-related disorders such as Landau-Kleffner syndrome
    • Severe emotional stress or trauma (less commonly)

    However, when speech regression occurs alongside reduced social interaction, repetitive behaviours, and communication difficulties, clinicians may investigate autism spectrum disorder.

    Because many conditions can cause developmental changes, children experiencing regression require comprehensive developmental assessment rather than assumptions based on a single symptom.

    Why Does Regressive Autism Occur?

    why regressive autism occur

    Researchers have not identified one single cause of regressive autism, but evidence suggests multiple biological factors contribute. There are several possibilities, such as:

    Genetic Factors

    Autism tends to have one of the strongest genetic components among neurodevelopmental conditions. Hundreds of genes have been linked with ASD, although no single gene explains regression.

    Brain Development

    Studies using neuroimaging suggest that differences in early brain connectivity may influence how communication and social skills develop.

    Immune and Neurological Factors

    Researchers continue investigating how immune system activity and early neurological development may contribute to autism regression, although no definitive explanation has been established.

    Importantly, extensive scientific evidence confirms that vaccinations do not cause autism or autism regression. Numerous large-scale international studies have consistently disproved this claim.

    Risk Factors Associated with Autism Regression

    regressive autism risk factors

    While regression cannot currently be predicted with certainty, several factors may increase the likelihood of developmental concerns. Some common risks include:

    • Family history of autism
    • Certain genetic syndromes
    • Neurodevelopmental differences
    • Male sex, although girls can also experience regression
    • Older parental age, which is associated with a modest increase in autism risk overall

    Having one or more risk factors does not mean a child will develop autism. Likewise, many autistic children have no identifiable risk factors.

    Autism Regression in Adults

    Adults regressive autism

    Although autism regression is most commonly associated with early childhood, some autistic adults may also experience a decline in certain abilities. However, autism regression in adults is different from the developmental regression seen in young children.

    Adults do not lose autism-related skills because autism is “returning.” Instead, periods of prolonged stress, anxiety, burnout, illness, sensory overload, or significant life changes can temporarily affect their ability to communicate, socialise, regulate emotions, or manage daily tasks. 

    This phenomenon is often referred to as autistic burnout rather than developmental regression.

    An autistic adult experiencing burnout may:

    • Find conversations more difficult than usual.
    • Become increasingly sensitive to noise, light, or crowded environments.
    • Struggle with executive functioning tasks such as planning, organising, or decision-making.
    • Feel exhausted after routine social interactions.
    • Need additional time to recover from everyday activities.

    Recent research published in Autism highlights autistic burnout as a distinct experience that requires recognition and appropriate support. 

    While some skills may temporarily decline, they often improve when stressors are addressed, routines are adjusted, and suitable accommodations are provided.

    How Is Regressive Autism Diagnosed?

    diagnosis of regressive autism

    There are no specific medical tests which can help diagnose regressive autism. Instead, diagnosis involves a comprehensive assessment of the child’s developmental history, current behaviour, and communication abilities.

    Healthcare professionals may include:

    • Developmental paediatricians
    • Child psychologists
    • Child psychiatrists
    • Speech and language therapists
    • Occupational therapists
    • Neurologists, when necessary

    The assessment usually includes:

    Developmental History

    Parents are asked detailed questions about early milestones, language development, social interaction, and when changes first became noticeable.

    Behavioural Observation

    Clinicians observe how the child communicates, plays, responds to social situations, and manages sensory experiences.

    Standardised Assessment Tools

    Evidence-based tools including the Autism Diagnostic Observation Schedule (ADOS-2) and the Autism Diagnostic Interview-Revised (ADI-R) may be used alongside clinical judgement.

    Medical Evaluation

    Where appropriate, hearing assessments, genetic testing, neurological examinations, or metabolic investigations may be recommended to rule out other conditions that can cause developmental regression.

    Receiving an early diagnosis enables families to access interventions during a period of rapid brain development, when children are often most responsive to support.

    Can Regressive Autism Be Reversed?

    scientific evidence indicates that autism itself cannot be reversed or cured

    One of the questions parents ask most frequently is, “Can regressive autism be reversed?“

    Current scientific evidence indicates that autism itself cannot be reversed or cured. Autism is a lifelong neurodevelopmental condition rather than an illness.

    However, this does not mean that children cannot make significant progress.

    With early diagnosis, evidence-based therapies, supportive educational environments, and family involvement, many children with regressive autism develop stronger communication, social interaction, adaptive skills, and independence over time.

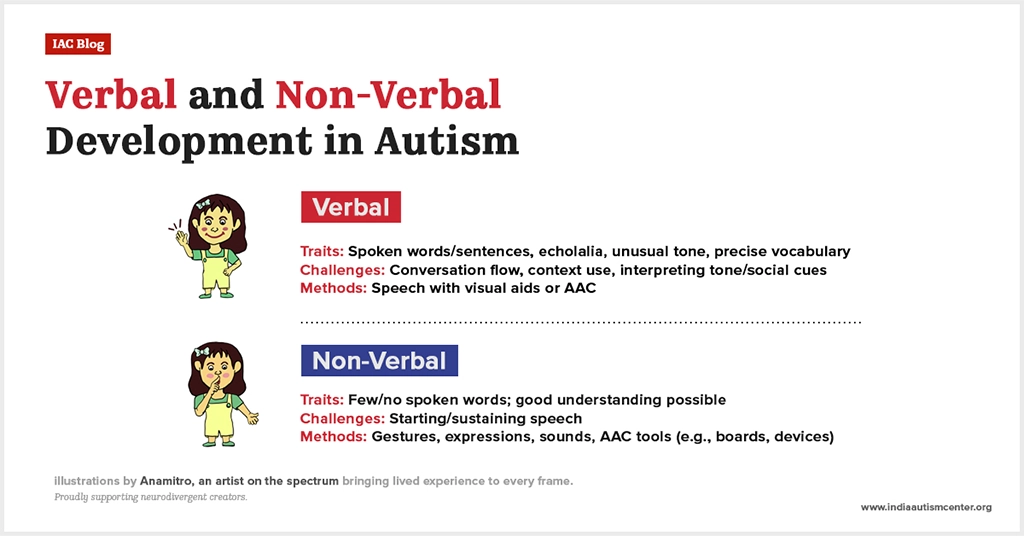
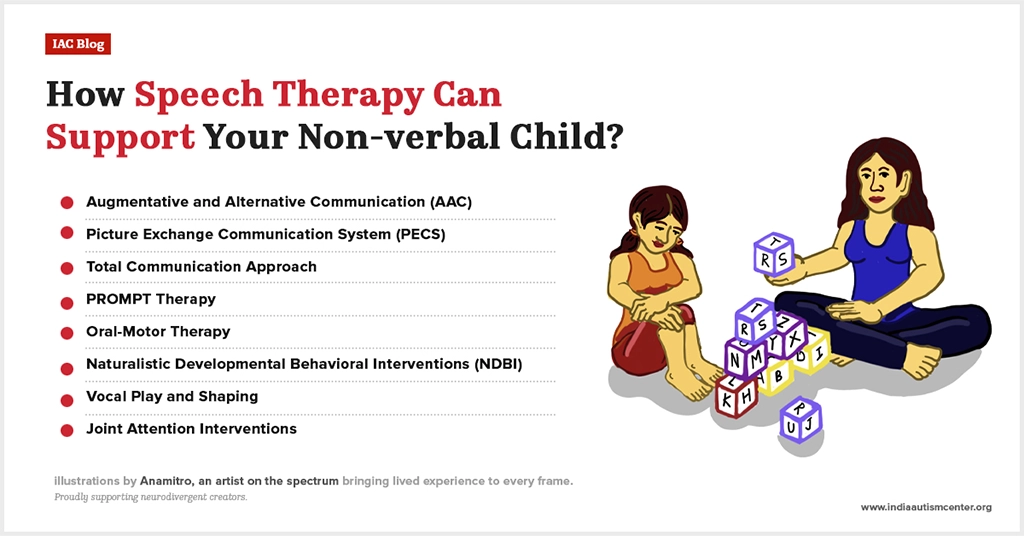
    Some children regain speech or social abilities that appeared to have been lost, while others develop alternative ways of communicating through gestures, visual supports, or augmentative and alternative communication (AAC).

    Rather than focusing on “reversing” autism, healthcare professionals emphasise helping every child reach their individual potential while respecting their unique strengths and needs.

    Support for Regressive Autism

    regressive autism support

    There is no single treatment that works for every autistic child. Instead, early intervention plans should be individualised based on the child’s developmental profile, strengths, challenges, and family priorities.

    Common evidence-based interventions include:

    Speech and Language Therapy

    Speech therapy supports communication through spoken language, gestures, visual communication systems, or AAC where appropriate.

    Occupational Therapy

    Occupational therapy helps children to develop fine motor skills, sensory regulation, self-care abilities, and independence in daily activities.

    Behavioural and Developmental Interventions

    Approaches such as Naturalistic Developmental Behavioural Interventions (NDBIs), parent-mediated programmes, and other evidence-based developmental behavioural therapies can improve communication, learning, and social participation.

    Educational Support

    Inclusive educational settings, structured teaching strategies, and reasonable adjustments help children participate more effectively in school.

    Family Training

    Parents play a significant role in reinforcing communication, play, and social learning during everyday routines. Guidance from experienced professionals helps families build confidence and consistency at home.

    Treatment goals should focus on improving quality of life, communication, independence, emotional well-being, and meaningful participation rather than attempting to change a child’s identity.

    Supporting a Child Through Autism Regression

    learning that a child is experiencing autism and regression can feel overwhelming

    Learning that a child is experiencing autism and regression can feel overwhelming. However, there are several steps families can take.

    Parents and caregivers need to:

    • Seek professional assessment as soon as developmental concerns arise.
    • Keep a record of developmental changes and new behaviours.
    • Celebrate small milestones rather than comparing progress with other children.
    • Maintain predictable routines that help reduce anxiety.
    • Encourage communication in all forms, including gestures, pictures, signs, or AAC.
    • Work closely with therapists and educators to maintain consistency across home and school.

    Equally important is supporting parents themselves. Caring for a child with additional developmental needs can be emotionally demanding, and access to counselling, parent support groups, and community resources can make a meaningful difference.

    How Does India Autism Center Support Children and Families?

    At India Autism Center, families receive guidance from experienced professionals

    Understanding regressive autism is only the first step. Accessing timely, evidence-based support is equally important for helping children develop communication, independence, and confidence. 

    At India Autism Center, families receive guidance from experienced professionals who recognise that every autistic individual has unique strengths, interests, and support needs. Through multidisciplinary assessments, therapeutic interventions, parent training, educational guidance, and community-based programmes, the centre promotes a holistic approach to lifelong development. 

    By empowering both autistic individuals and their families, India Autism Center helps create opportunities for meaningful participation, inclusion, and improved quality of life at every stage of the journey.

    Conclusion

    regressive autism summary

    Regressive autism can be an unexpected and emotional experience for families, but recognising the early signs allows children to access the support they need as early as possible. While autism regression may involve the loss of previously acquired skills, it does not define a child’s future. 

    Early assessment, evidence-based interventions, family involvement, and ongoing professional support can help children continue to learn, communicate, and thrive. With greater awareness and informed care, families can move forward with confidence, knowing that every child has the potential to grow in their own unique way.

    Frequently Asked Questions

    What is the difference between regressive autism and classic autism?

    Regressive autism refers to a pattern where a child loses previously acquired skills, such as speech or social interaction, after a period of typical development. In contrast, children with classic autism usually show developmental differences from infancy without a noticeable loss of skills.

    Does every child with autism experience developmental regression?

    No. Research suggests that only about 25% to 30% of autistic children experience developmental regression, while many others show signs of autism from early infancy without losing previously acquired skills.

    Can a child regain skills after autism regression?

    Yes. Many children regain some or all lost skills through early diagnosis, evidence-based therapies, consistent support, and family involvement. Progress varies from one child to another.

    Why do some children suddenly lose skills after developing normally?

    Researchers believe autism regression results from complex genetic and neurological factors affecting early brain development. The exact cause remains under investigation, and there is no evidence that parenting or vaccines cause regression.

    Can autism regression happen after the age of three?

    Although regression most often occurs before three years of age, some children may experience later developmental changes. A healthcare professional should always assess any noticeable loss of previously acquired skills.

  • Early Intervention for Autism: The Parent Guide That Can Change Outcomes

    Early Intervention for Autism: The Parent Guide That Can Change Outcomes

    Imagine giving your child the right support before challenges begin to build. That’s the power of early intervention for autism spectrum disorder (ASD).

    In this guide, you’ll learn why early intervention for autism isn’t just beneficial, but essential.

    We’ll also walk you through how to recognize early signs, what early autism intervention actually involves, and the steps you can take to improve long-term outcomes.

    So, let’s begin.

    What Is Early Intervention For Autism?

    Early intervention for autism spectrum disorder means providing targeted therapies and support to young children, ideally before they turn 3 years old. In many cases, it starts as early as 18 months.

    At this age, the brain develops rapidly. It remains highly plastic and especially receptive to learning, change, and growth. 

    Early autism intervention during this window reduces developmental delays, strengthens key life skills, and improves long-term outcomes.

    It typically addresses areas such as:

    • Communication and speech
    • Social interaction and play
    • Emotional regulation
    • Sensory integration
    • Gross motor skills (like walking, running, jumping)
    • Fine motor tasks (like feeding, writing, buttoning)
    • Daily self-care routines and more

    So, early intervention is highly effective in shaping a child’s developmental trajectory. As Raksheet Jain, Co-Founder of Aignosis, shared on the IAC podcast,

    This raises the question.

    When Should You Consider Early Intervention?

    When Should You Consider Early Intervention

    Recognizing early signs of autism is often the first step toward timely support. 

    These are the signs that often appear in the first three years. And spotting them opens the door to early support.

    The most common signs include:

    • No babbling, waving, or pointing by 12 months
    • Not responding to their name despite normal hearing
    • Minimal eye contact or shared expressions
    • Few or no spoken words by 16–18 months
    • Limited interest in social play or imitation
    • Strong, unusual reactions to sensory input (noise, light, textures)
    • Repetitive movements like hand-flapping or spinning
    • Rigid routines or distress over small changes

    Understanding these early signs is only part of the journey. The next and most impactful step is knowing why early intervention is important for autism.

    Benefits of Early Intervention In Autism

    Benefits of Early Intervention In Autism

    Without early intervention, progress often slows. 

    But with it? The difference can be dramatic.

    So, how does early intervention help autism? Let’s find out.

    Improved Expressive and Receptive Communication

    Early intervention for autism spectrum disorder is just about helping children talk. It nurtures both expressive and receptive communication. 

    This helps children move from single words or gestures to full thoughts, shared intent, and emotional clarity.

    With consistent therapy and parent-guided strategies, children begin to connect language with interaction.

    Enhanced Social Interaction and Reciprocal Engagement

    Through guided play, modeling, and structured therapy, children learn to:

    • Read facial expressions and social cues
    • Engage in back-and-forth interactions
    • Build confidence in peer relationships

    Over time, they gain the confidence to initiate and sustain peer relationships. This lays the groundwork for meaningful connections.

    Better Emotional Regulation and Behavioral Adaptation

    Meltdowns. Sensory overload. Sudden shutdowns. These can escalate quickly.

    Autism early intervention teaches children how to self-regulate using:

    • Calming routines
    • Sensory tools
    • Structured transitions

    This support reduces emotional outbursts and helps children respond more adaptively to daily challenges.

    Accelerated Development of Fine and Gross Motor Skills

    From climbing stairs to holding utensils, early intervention in autism improves both:

    • Gross motor skills (balance, coordination, strength)
    • Fine motor skills (grasping, writing, buttoning)

    Targeted therapies during this window help children gain physical confidence and independence.

    Increased Adaptive Skills and Functional Independence

    Feeding. Dressing. Toileting. Brushing teeth. Tasks that once felt impossible become manageable.

    That’s the real power of early autism intervention. It nurtures adaptive functioning, empowering children toward self-reliance and reducing dependence on others in daily life.

    Now that we’ve seen how outcomes improve with early support, let’s explore the proven strategies that make it happen.

    Early Intervention Strategies for Autism

    Early Intervention Strategies for Autism

    So, where do you begin?

    Your first stop should be a developmental pediatrician, clinical psychologist, or rehabilitation psychologist. Ask them to conduct a developmental screening of your child.

    If screening raises concerns, early autism intervention can and should begin right away.

    Here are a few strategies that can make a lasting difference:

    Strategy 1: Build Positive Habits Early with Behavioral Therapy

    Applied Behavior Analysis (ABA) is often among the first therapies introduced. It focuses on reinforcing positive behaviors through structured steps like rewards, routines, and repetition.

    With ABA, children learn to:

    • Ask for help
    • Follow simple instructions
    • Stay regulated in overstimulating environments

    Strategy 2: Boost Connection Through Social Skills Therapy

    Did you know that turn-taking, eye contact, and group play can all be taught?

    Yes, social skills therapy teaches exactly these core relationship-building tools through guided play sessions and one-on-one modeling.

    As Shaireen Ali, Head of Clinical Services at India Autism Center, puts it,

    Strategy 3: Support Self-Expression with Communication Therapy

    Whether your child is verbal, nonverbal, or still finding their voice, speech, and language therapy plays a key role.

    Supports may include:

    • Verbal prompting
    • Picture Exchange Communication System (PECS)
    • Augmentative and Alternative Communication (AAC) devices

    The goal? Help the child express needs, emotions, and ideas on their own terms.

    Strategy 4: Build Independence with Occupational and Sensory Therapy

    Let’s talk about daily life. Eating, dressing, drawing, and holding a spoon.

    In many autistic children, these skills need to be gently built, often from the ground up. That’s where occupational therapy (OT) comes in.

    It helps build:

    • Fine motor skills
    • Body awareness and trunk control
    • Sensory regulation
    • Self-care routines

    As Dr. R. S. Bagga, a renowned Occupational Therapist, shared on the IAC podcast,

    Strategy 5: Strengthen Coordination with Physiotherapy

    Struggling with balance, walking, or climbing stairs?

    Physiotherapy can work like a charm. It helps children improve: 

    • Balance and coordination
    • Muscle strength and tone
    • Gross motor skills

    Strategy 6: Use Assistive Technology to Bridge Gaps in Learning

    Assistive technology can be life-changing.

    Speech tablets, visual timers, picture schedules. These aren’t shortcuts. They’re bridges.

    The right tool, introduced at the right age, can help your child understand the world and be understood in return.

    Strategy 7: Reduce Mealtime Stress with Feeding and Nutrition Therapy

    Many autistic children struggle with textures, chewing, or swallowing.

    This is where feeding and nutrition therapy help. It can:

    • Reduce stress at meals
    • Improve oral-motor coordination
    • Encourage balanced nutrition for better focus and energy

    Strategy 8: Encourage Learning Naturally with Play-Based Therapy

    Play is not a break from learning. It is learning, especially for young children.

    Through pouring rice into cups, pretending to run a tea stall, or simply following a child’s lead in a silly game, play becomes the gateway to communication and emotional connection.

    As Puja Dutta, Clinical Psychologist at India Autism Center, says,

    That’s why play-based therapy works. It doesn’t force a child to fit into a plan. It meets them where they are.

    Strategy 9: Prepare for School with Early Special Education Services

    Preschools with special education services facilitate early intervention for autism. 

    Some preschools offer:

    • Visual supports and structured lessons
    • Individualized learning plans (IEPs)
    • Flexible pacing

    As Shaireen notes,

    Strategy 10: Foster Teamwork with Peer-Based Community Programs

    Children don’t learn in isolation. Peer interaction teaches:

    • Sharing
    • Teamwork
    • Problem-solving

    Whether it’s a playgroup or community event, early exposure builds social confidence that carries into the school years.

    Now that you know how each strategy supports early development, let’s discuss the role parents play in making early intervention for autism truly effective.

    What the Research Says: Evidence Behind Early Intervention

    Evidence Behind Early Intervention

    The benefits of early intervention for autism aren’t just anecdotal. They are backed by decades of rigorous, peer-reviewed research. Here’s what the most important studies actually found – in plain language.

    The Early Start Denver Model (ESDM)

    The landmark study by Dawson et al. (2010), published in Pediatrics, is the most cited randomized controlled trial on early autism intervention. Toddlers aged 18–30 months received ESDM therapy for 20 hours per week over two years. The model combines play-based learning with structured ABA principles and, critically, trains parents to deliver the approach at home.

    The results were striking. Children in the ESDM group improved by an average of 17.6 IQ points on cognitive ability measures – compared to just 7.0 points in the control group receiving standard community treatment. That’s more than double the cognitive gain, from the same two-year window.

    Beyond IQ, the ESDM group showed significantly better adaptive behavior, language development, and reduced autism symptom severity. Notably, this was the first randomized controlled trial to demonstrate measurable developmental benefits for toddlers with ASD. The play-based, parent-training model is now considered a gold-standard approach worldwide.

    The Preschool Autism Communication Trial (PACT)

    The PACT study (Green et al., 2010; Pickles et al., 2016) tested a parent-mediated social communication therapy with preschool-aged autistic children. The intervention trained parents to respond more synchronously to their child’s communication cues – essentially, to follow the child’s lead and build on it.

    The immediate results showed clear improvements in parent-child social communication and increased child communication initiations. More compelling was the six-year follow-up: children in the PACT group showed significantly less severe autism symptoms and better social communication compared to the treatment-as-usual group. The gains held. That’s the kind of long-term evidence that matters for families making decisions today.

    Global Prevalence: Why This Urgency Is Justified

    The CDC’s 2025 ADDM Network report found that 1 in 31 children in the United States is diagnosed with ASD – the highest prevalence ever recorded. While India does not yet have an equivalent national surveillance system, this figure serves as a global reference point. It underscores how common autism is, and why building early identification and intervention capacity is a public health priority everywhere, including here.

    What Long-Term Research Tells Us

    Taken together, the evidence on early intervention points consistently in one direction:

    • Higher rates of mainstream school attendance – studies show children who receive intensive early intervention are significantly more likely to attend regular schools without additional support
    • Reduced support needs in adulthood – early gains in adaptive skills translate to greater independence later in life
    • Improved employment prospects – longitudinal research links early communication and social skill development to better vocational outcomes in adulthood

    The window before age 3 is not a deadline to panic about. It’s an opportunity – one that research tells us is genuinely worth acting on as early as possible.

    What Does Parental Responsibility Look Like in Early Autism Intervention?

    What Does Parental Responsibility Look Like in Early Autism Intervention

    Early intervention for autism is not just about what happens in therapy rooms. It’s about what happens at home. Every single day. 

    Parents should not be passive observers. They are meant to be core members of the intervention team.

    Here’s how you can make your role count.

    Turn Everyday Moments Into Practice Opportunities

    Therapies like ABA, speech, or occupational therapy teach important skills. 

    But real growth happens through repetition at home. Moments such as snack time, playtime, or getting dressed can naturally become practice sessions for communication, social skills, and sensory regulation.

    To make the most of these everyday moments, try to:

    • Encourage your child to request or label items during snack time
    • Use playtime to support turn-taking and social interaction
    • Practice calming techniques during routines like bathing or dressing

    Learn the Techniques and Use Them Confidently

    You don’t need formal training to support your child’s development. You just need curiosity and commitment.

    Observe sessions. Ask questions. Join parent workshops.

    This helps you:

    • Tailor strategies to suit the child’s unique needs
    • Practice consistently across environments
    • Build your confidence by learning why certain approaches work

    Make Your Home a Supportive Learning Space

    A nurturing environment at home can supercharge your child’s comfort and learning.

    Try:

    • Visual schedules to support transitions
    • Sensory-friendly items to ease overwhelm or increase engagement
    • Predictable routines to reduce anxiety and improve cooperation

    More on this later.

    Keep the Conversation Going With Professionals

    Open and regular communication with therapists, educators, and specialists ensures that the child’s needs are met consistently.

    Make it a habit to:

    • Provide updates on what you notice at home and in other settings.
    • Ask questions to clarify goals and strategies.
    • Participate actively in meetings and planning sessions.

    Advocate Strongly for Your Child’s Needs

    You are your child’s loudest and strongest voice. Advocacy means ensuring they get the resources, therapies, and accommodations they need.

    Take initiative by:

    • Learning about available services and autism laws
    • Making detailed requests to schools or healthcare providers
    • Staying updated on local policy or funding changes

    Celebrate Every Step Forward

    Autism early intervention outcomes often come in small, meaningful milestones. Recognizing these moments keeps your child motivated.

    Celebrate by:

    • Noticing new skills, improved behaviors, or moments of independence
    • Praising your child’s effort and persistence
    • Using positive reinforcement to motivate continued growth

    Own Your Role in Your Child’s Progress

    Parental involvement is one of the strongest predictors of success in early autism intervention. 

    Your love, patience, and consistency create the foundation on which everything else is built.

    Own your role by:

    • Being patient with the process and yourself
    • Staying consistent with routines and practice
    • Being the primary champion of your child’s growth

    Therapy doesn’t stop when you leave the clinic. In fact, much of the progress happens through autism early intervention at home.

    Home Activities for Early Intervention in Autism

    Home Activities for Early Intervention in Autism

    Home activities for early autism intervention.

    Therapy hours are valuable. No doubt about that.

    But what happens at home can multiply their impact.

    Here’s how to get the most out of early intervention, right from your living room:

    Play with Purpose

    Play isn’t just fun. It’s how the children learn.

    Activities like stacking blocks, pretending to feed a toy animal, or building with LEGO go beyond creativity. They foster:

    • Joint attention
    • Turn-taking
    • Flexible thinking

    Make Reading Interactive

    Don’t just read. Interact.

    Pause to point out pictures. Name characters. Ask simple questions. Let your child turn the pages.

    Books build vocabulary, listening skills, and future communication, even before your child speaks.

    Bring in Music and Rhythm

    Sing songs with actions. Tap to a beat.

    Use music to teach daily routines, like brushing teeth or cleaning up. Songs create structure and support language, memory, and motor development.

    Strengthen Little Muscles

    Puzzles, finger painting, and stacking rings help build hand-eye coordination.

    Additionally, these activities also prepare children for:

    • Writing
    • Eating independently
    • Dressing skills like buttoning or zipping

    Encourage Movement

    Active play supports sensory regulation and gross motor development.

    Try:

    • Indoor obstacle courses
    • Cushion jumping
    • Outdoor walks or park play

    Make Routines Count

    Bath time. Dressing. Meal prep. These are chores that can double up as learning moments.

    Narrate what you’re doing. Offer choices. Give space for independence.

    Over time, these routines teach sequencing, communication, and daily living skills.

    Support Communication All Day Long

    Use short, clear sentences. Label actions and emotions. Use gestures and visuals where possible.

    Communication isn’t only built-in therapy, it’s reinforced in every shared moment.

    Get Social, Gently

    Start small. Invite cousins over for a short visit. Join a parent-child class. Or start with parallel play at a park.

    Social practice, at a pace your child can handle, builds confidence and connection.

    Create Space for Sensory Needs

    Sensory play helps children self-regulate.

    Water tubs, sand trays, calm-down bottles, or just a quiet corner with a soft blanket can make all the difference on a hard day.

    Early Intervention for Autism in India: What Parents Need to Know

    Early Intervention for Autism in India: What Parents Need to Know

    If you’re a parent in India, the information in this guide is directly relevant to you – but the path to accessing early intervention looks different here than it does in the UK or the US. Understanding the landscape honestly is the first step.

    The Diagnosis Gap in India

    In India, children with autism are diagnosed significantly later than the global best-practice benchmark of age 2. Research published in the Indian Journal of Public Health (2022) found a mean diagnosis age of 4.62 years – and in rural settings, even later. A mixed-methods study from urban North India found that while parents typically noticed developmental concerns around age 2, the actual diagnosis came around age 4. That’s a two-year gap during which the most critical intervention window is passing.

    The reasons are systemic. Awareness of early autism signs remains low among many families and frontline health workers. Developmental pediatricians, child psychiatrists, and multidisciplinary assessment teams are concentrated in metro cities. In Tier 2 and Tier 3 cities – and certainly in rural areas – families often travel hundreds of kilometres for a single diagnostic appointment, then wait months for the next one.

    This is not a failure of parents. It’s a gap in the system. And knowing it exists is the first step to navigating around it.

    Your Child’s Legal Rights: The RPWD Act 2016

    Here’s something every Indian parent of an autistic child needs to know: autism is a recognized disability under the Rights of Persons with Disabilities (RPwD) Act, 2016. The Act, which came into force in April 2017, expanded India’s disability framework to 21 categories – and autism spectrum disorder is explicitly included.

    What this means practically:

    • Free education: Schools cannot deny admission on the basis of disability. Inclusive education is mandated.
    • Reservations: At least 5% of seats in government higher education institutions are reserved for persons with benchmark disabilities, including autism.
    • Government employment: 4% of vacancies in central government establishments are reserved for persons with benchmark disabilities.
    • Non-discrimination: The Act mandates equal treatment and accessibility in public life.

    To access these rights, your child will need a disability certificate issued through a government-notified process. Ask your developmental pediatrician or district hospital about obtaining a UDID (Unique Disability ID) card – this is the gateway to most government benefits.

    The National Trust Act: Welfare and Guardianship

    Alongside the RPwD Act, the National Trust Act (1999) specifically covers autism, cerebral palsy, intellectual disability, and multiple disabilities. It provides legal guardianship frameworks for autistic individuals who need support in adulthood, and it funds welfare schemes through registered organizations. If you’re thinking about long-term planning for your child, the National Trust is a resource worth knowing.

    Key Institutions for Diagnosis and Intervention

    If you’re seeking a formal diagnosis or specialist early intervention, these are the primary referral institutions in India:

    • NIMHANS (National Institute of Mental Health and Neuro Sciences), Bangalore – a leading centre for autism diagnosis and research
    • AIIMS (All India Institute of Medical Sciences), New Delhi – offers multidisciplinary developmental assessment
    • Ali Yavar Jung National Institute of Speech and Hearing Disabilities, Mumbai – specializes in communication disorders and early intervention for children with developmental disabilities

    These institutions have long waiting lists. Start the referral process early, and pursue private assessment in parallel if you can.

    Government Programs: ICDS and Sarva Shiksha Abhiyan

    Some states offer early intervention support through the Integrated Child Development Services (ICDS) scheme, which reaches children from birth to 6 years through Anganwadi centres. The quality of autism-specific support varies widely by state and by the training of local workers.

    For school-age children, Sarva Shiksha Abhiyan (SSA) – now subsumed under the Samagra Shiksha framework – mandates inclusive education for children with disabilities. In practice, the availability of trained resource teachers and support staff in mainstream schools remains inconsistent, particularly outside urban areas.

    The Private-Government Access Gap

    Let’s be direct about something: the majority of quality, evidence-based early intervention in India is currently concentrated in metro cities and delivered through private centres. Families in smaller towns and rural areas face a significant access barrier – both in terms of geography and cost.

    This gap is real. It’s also why specialized centres that combine residential programs, trained therapists, and structured parent training are so important for families who cannot access daily outpatient therapy locally.

    How India Autism Center Can Help

    India Autism Center operates as a specialized residential and training centre designed precisely for this gap. For families who cannot access consistent early intervention locally – whether due to geography, specialist availability, or the need for intensive, structured programming – IAC offers evidence-based programs delivered by trained professionals.

    If your child has recently been diagnosed, or if you’re seeing early signs and don’t know where to start, reach out to India Autism Center for guidance. The team can help you understand what early intervention looks like for your child’s specific profile, and what steps to take next – whether that’s with IAC or with services closer to home.

    Early intervention for autism works. The research is clear. The question for Indian families is not whether to act, but how to find the right path forward. You don’t have to figure that out alone.

    Parting Thoughts: Key Considerations In Early Intervention for Autism

    A strong early intervention program for autism begins with a multidisciplinary assessment. Developmental pediatricians, psychologists, speech therapists, occupational therapists, and special educators come together to understand your child’s unique profile.

    But that’s only part of the picture. Real success comes when support extends to the whole family.

    As Puja emphasizes,

    Also, ensure the professionals delivering early intervention are trained, certified, and experienced.

    For further assistance, feel free to contact us now.

    Frequently Asked Questions

    Does autism get better with early intervention?

    Early intervention doesn’t cure autism. But it can make a lasting impact on a child’s development. Starting support early helps children build critical skills in communication, learning, social interaction, and daily living.

     What should I do if my 2-year-old shows signs of autism?

    Start with a developmental evaluation by a pediatrician or psychologist. If autism is suspected, connect with early intervention services in your area.

    At home, focus on:

    • Play-based interaction
    • Communication-rich environments
    • Establishing consistent daily routines

    What age is considered early intervention for autism?

    Early intervention typically refers to support services provided from birth up to 3 years old.

    What is the best age to start autism treatment?

    There’s no single best age, but the earlier the better. The brain is most adaptable (or plastic) in the first five years of life. Starting therapy as soon as autism is suspected can positively influence learning, social skills, and overall development.

    What is the success rate of early intervention for autism?

    Success varies based on the child’s individual needs, type of intervention, and family involvement.

    Research shows that timely and targeted early autism intervention leads to significant progress in:

    • Language and communication
    • Social interaction
    • Adaptive skills and independence

    Can early intervention cure autism?

    No, early intervention doesn’t cure autism, and it’s not meant to. Autism is a neurodevelopmental condition, not a disease. What early intervention does is help build communication, confidence, and everyday skills.

    Disclaimer: This article is intended for educational and informational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. If you are pregnant or have concerns about medication use during pregnancy, please consult a qualified healthcare provider. If your child has received an autism diagnosis and you have questions about causes or support, please reach out to a trained specialist or an autism-focused organisation for guidance.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

    Useful Sources

  • When Do Kids With Autism Start Talking?

    When Do Kids With Autism Start Talking?

    For many parents of autistic children, the first worry begins with silence. A toddler who doesn’t say “mama” at 18 months. A child who once spoke but then suddenly stops.

    The short answer: there is no single age. Research shows that roughly 25–30% of children with autism remain minimally verbal beyond age five – yet a landmark 2013 study from Kennedy Krieger Institute found that 70% of children with severe early language delay still developed phrase speech, and 47% achieved fluent speech, often with a notable burst between ages 6 and 7.

    So what age do kids with autism start talking? It depends on the child. But the evidence is clear: later is not never. And early, consistent support makes a real difference.

    In this article, we’ll walk through the speech milestones, the factors that shape them, and what parents can do – at home and with professional support – to help their child communicate.

    At What Age Do Kids with Autism Start Talking? Speech Development Timelines in Autism

    Baby learning to speak with speech milestones chart.

    In typical development, speech moves from babbling to first words, short phrases, and then full sentences.

    In autism, these stages may appear later, occur out of order, or look different. Sometimes, there are repeated phrases from others, or long stretches of silence followed by sudden bursts of speech. Parents often ask: “When do autistic kids start talking?” The truth is, the answer varies for each child.

    Here’s how typical timelines compare with those on the spectrum:

    Cooing and Babbling (2–6 months)

    Chart comparing typical and autistic babbling signs in 2-6 month infants.

    For most infants, the soundtrack of early life begins with rounded vowels like “oo” or “ah”. These soon sharpen into rhythmic “ba-ba” and “ma-ma.”

    In autism, these sounds may come later, occur less often, or take different forms such as humming, squealing, or repetitive tones. Sometimes, words appear suddenly and then vanish, leaving parents wondering: “When did your autistic child start talking?”

    First Words (12–18 months)

    Speech regression in toddlers.

    By around 12 to 18 months, children typically begin speaking their first intentional words. Simple ones like “mama” or “ball,” used with meaning.  

    In autism, however, first words may be delayed beyond age two, appear briefly before fading, or emerge inconsistently. This often leads to the question: “Will my autistic son ever talk?” 

    As Puja Dutta, RCI-registered clinical psychologist at the India Autism Center, explains,

    Two-Word Phrases (18–24 months)

    Chart comparing typical and autistic two-word phrase development (18-24 months).

    The leap from words to short phrases, like “want juice” or “go park,” marks a milestone in combining meaning.  

    In autism, this step may be postponed or shaped by echolalia, the repetition of words and phrases borrowed from others, before original pairings begin to emerge. 

    Simple Sentences (2–3 years)

    Chart comparing typical and autistic sentence structure development in 2-3 year old.

    Most children now form 3–4 word sentences such as “I want toy” or “Go see dog.” 

    In autism, sentence-building tends to be slower, often anchored in concrete language, with abstract or flexible use of words taking longer. 

    Conversational Skills (3–5 years)

    Chart comparing typical and autistic conversational skills development (3–5 years).

    By preschool, most children can trade questions and answers, shift tone to suit the moment, and navigate the give-and-take of talk.  

    Autistic children may command a wide vocabulary yet struggle with pragmatics. It’s the unspoken rules and rhythms of conversation that are more elusive to them. Parents often ask: “Do non verbal autistic kids ever talk?” The answer: yes, many do, but at their own pace. 

    Speech Milestone Comparison: Typical Development vs. Autism

    This table draws on data from the Wodka, Mathy & Kalb (2013) study at Kennedy Krieger Institute (535 children from the Simons Simplex Collection) and ASHA’s early intervention guidelines.

    Age RangeTypical DevelopmentAutism Spectrum
    0–6 monthsCooing, vowel sounds (“oo,” “ah”), social smiling, responds to voicesReduced or absent cooing; less varied vocalisation; may not orient to voice consistently
    6–12 monthsBabbling with consonants (“ba-ba,” “da-da”), imitates sounds, responds to nameBabbling may be delayed, less frequent, or atypical in rhythm; inconsistent name response
    12–18 monthsFirst meaningful words (e.g., “mama,” “ball”); 10–20 words by 18 monthsFirst words often delayed beyond 18–24 months; may appear then disappear; speech regression possible
    18–24 monthsTwo-word combinations (“more milk,” “daddy go”); ~50-word vocabularyTwo-word phrases delayed or absent; echolalia common; ~40% of children are minimally verbal at this stage
    2–3 years3–4 word sentences; rapid vocabulary growth; asks simple questionsSentence-building slower; concrete language predominates; some children still pre-verbal
    3–5 yearsFull conversations; adjusts language to listener; narrative abilityWide vocabulary possible but pragmatic difficulties common; many children show a language burst at ages 6–7
    5–8 yearsFluent, flexible speech across contextsPer Kennedy Krieger SSC study: 70% of children with severe early language delay developed phrase speech by age 8; 47% achieved fluent speech

    Verbal and Non-Verbal Development in Autism

    Unlike typical language growth, which follows a fairly predictable path, speech and language development in autism is often uneven. Some individuals on the spectrum speak fluently, while others use only a few words.

    At the same time, this raises another concern: “Do nonverbal autistic children ever speak?” Research and therapy show that yes, many may rely on gestures or augmentative and alternative communication (AAC) devices.  

    Here’s how different communication profiles typically present:

    ProfileKey Characteristics Common Challenges Primary Communication Methods 
    Verbal Autism Spoken words or sentences; may include echolalia, unusual prosody, or highly specific vocabulary Conversational reciprocity; adapting language to context; interpreting tone and social cues Spoken language, sometimes supported by visual aids or AAC 
    Non-Verbal / Minimally Verbal Autism Few or no spoken words; may have strong receptive language skills Initiating speech; sustaining verbal interaction Gestures, facial expressions, sounds, AAC such as picture boards or speech-generating devices 

    In practice, autistic individuals often blend verbal and non-verbal methods depending on the situation. Communication is fluid, not fixed, and the most effective approach is one that adapts to each individual’s strengths. 

    Signs Your Autistic Child May Begin Talking Soon

    Signs an autistic child is about to start talking.

    Early signs of language growth aren’t always about words. They can emerge in tone, rhythm, gesture, or shared engagement. Parents often search for clues about when do kids with autism start talking. 

    Here are some ways your child may show that speech is beginning to take shape: 

    Your child imitates sounds and actions

    Clapping when you clap, humming back a tune, or trying a new consonant sound. All of these show that they’re linking movement, sound, and meaning, laying the groundwork for speech. 

    Your child experiments with babbling and first words

    Playful strings of consonants (“ba-ba,” “ma-ma”) or sporadic single words show that vocal exploration is underway. Speech may come with quirks such as pronoun reversals (“You want cookie” instead of “I want cookie”) or unusual sentence structures. These aren’t errors. They’re milestones in learning how to use language. 

    Your child uses communicative gestures

    Pointing, waving, reaching out, or clapping serve as intentional signals. These gestures bridge the gap between non-verbal interaction and spoken communication.

    Your child repeats words or phrases

    Children may echo what they hear immediately or repeat it later in a new context. What looks like parroting is actually practice. A way to explore rhythm, self-soothe, or begin forming speech patterns. 

    Your child engages in pretend play and turn-taking

    Tea parties, role-plays, or simple back-and-forth games show your child understands shared narratives. These interactive abilities often emerge alongside language growth. 

    Your child responds consistently to their name

    Turning toward you when called reflects growing social awareness and readiness to connect verbal cues with action. 

    Your child takes part in back-and-forth exchanges

    Whether trading facial expressions, gestures, or playful sounds, these mini conversations mirror the give-and-take of spoken dialogue. 

    Your child follows a unique path to language

    Some children may skip traditional steps. They move straight from silence to whole words, or begin with short phrases before single words. Different doesn’t mean delayed; it’s simply a different path. 

    Your child’s speech has distinct vocal qualities 

    Early speech may carry unusual pitch, rhythm, or inflection. While it can sound atypical, it signals that your child is actively experimenting with the mechanics of speech. 

    Your child shares joint attention

    Looking between a toy and you, or drawing your gaze toward an object, reflects the ability to connect experiences with another person. This is one of the strongest predictors of language growth. 

    Factors That Influence When an Autistic Child Starts Talking

    Why does one child start speaking at 2 while another finds their voice at 7? The answer isn’t random. Several well-documented factors shape the trajectory of speech development in autism – and understanding them helps families and clinicians plan more targeted support.

    Cognitive Ability and IQ

    Nonverbal IQ is one of the strongest independent predictors of language outcomes. The Kennedy Krieger SSC study (Wodka et al., 2013) found that children with typical nonverbal IQ reached phrase speech approximately 7 months earlier than children with lower nonverbal IQ scores. This doesn’t mean children with intellectual disability won’t speak – many do – but it does mean the timeline and approach may differ.

    Lower social impairment scores were also associated with better language outcomes in the same study, suggesting that children who engage more readily with others tend to develop speech sooner.

    Early Intervention Timing and Intensity

    The ASHA Practice Portal on Autism is unambiguous: earlier intervention produces better outcomes. There is no “too young” for speech-language support. Children who begin structured intervention before age 3 – particularly intensive, play-based approaches – consistently show greater language gains than those who start later.

    In India, this means acting on concerns as soon as a developmental difference is noticed, rather than waiting for a formal diagnosis. A speech-language pathologist can begin working with a child even before an autism diagnosis is confirmed.

    Sensory Processing Differences

    Many autistic children experience the world with heightened or reduced sensitivity to sound, touch, light, and other sensory input. When a child is in a state of sensory overload – a noisy classroom, a crowded family gathering – verbal output can drop dramatically. The child isn’t choosing not to speak; their nervous system is overwhelmed.

    Recognising these triggers and creating calmer communication environments can make a significant difference. Occupational therapy alongside speech therapy is often recommended for children with significant sensory processing differences.

    Motor Planning and Apraxia

    Childhood Apraxia of Speech (CAS) co-occurs with autism more often than previously recognised. CAS is a motor speech disorder – the child knows what they want to say but the brain struggles to plan and sequence the precise movements needed to produce speech. This is distinct from a language delay.

    Children with both autism and CAS often benefit from specialised approaches like PROMPT (Prompts for Restructuring Oral Muscular Phonetic Targets) therapy, which uses tactile cues to guide the mouth’s movements. Identifying this overlap early prevents years of frustration for both child and family.

    Family Involvement and Communication-Rich Environment

    Parent-mediated intervention is one of the most evidence-backed strategies in autism speech development. When parents learn to use techniques like parallel talk (“you’re rolling the ball”), expansion (“big red ball”), and communication temptations (placing a desired object just out of reach), they create hundreds of natural learning opportunities every day that no clinic session can replicate.

    Studies consistently show that children in language-rich home environments – where caregivers respond to every communicative attempt, verbal or not – develop speech faster and with greater functional use. This is not about pressure or drilling. It’s about making communication feel worthwhile.

    Non-verbalism in Autism vs Non-verbal Learning Disorder (NVLD)

    Non-verbal Autism vs. NVLD comparison.

    Non-Verbal Learning Disorder can be confusing at first glance. Despite the name, children with NVLD often have plenty of words. Sometimes more than expected for their age.  

    What’s missing is not speech itself, but the other half of communication. The unspoken layer.  

    The glance that signals understanding, the pause before answering, the change in tone that shifts a conversation. These subtle cues can slip past unnoticed. 

    In autism, “non-verbal” tends to mean something quite different.  

    Speech may be limited, inconsistent, or absent altogether. Communication often shows up through gestures, body language, scripted phrases, or assistive devices. The social frame is present, but the words themselves may take longer or follow an unexpected path to arrive. 

    Both NVLD and autism reshape how communication unfolds. NVLD leaves the sentences intact but makes the social context harder to grasp. Autism preserves the context but may set words further away. 

    How Non-verbal Differs in Autism and NVLD

    Aspect In Autism In NVLD 
    What non-verbal means Limited, inconsistent, or absent speech Difficulty interpreting unspoken cues (facial expressions, gestures, tone, spatial awareness) 
    Speech Sometimes present, sometimes not; may use devices, gestures, or signs Fluent, often early; vocabulary usually strong 
    Main challenge Expressing thoughts and needs when speech is unreliable Reading the silent language of social interaction 
    In conversation May avoid verbal back-and-forth or speak in a distinct rhythm May speak at length but miss the subtle social undercurrents 
    Underlying difference How language, sensory input, and social cues connect How the brain interprets space, patterns, and non-verbal signals 
    Early years Fewer early words, less babbling, more pointing or gestures Strong with words, but interpreting social cues, puzzles, or spatial tasks can be difficult 

    How Speech Therapy Can Support Your Non-verbal Child

    Speech therapy methods for non-verbal autism support.

    For many parents, the hope begins with a single word. The dream of hearing “mama” or “baba” feels both urgent and fragile. When that word doesn’t come, or when it fades away, the instinct is to look toward speech therapy as the magic key. 

    But here’s the truth: speech therapy isn’t just about getting kids to talk. For non-verbal or minimally verbal autistic children, it’s about finding their language, whether through pictures, signs, devices, or movement, and building on it. Families often ask: “Do nonverbal autistic children ever speak?” Yes, many do with the right support. 

    That’s why modern speech therapy rarely looks like a child sitting at a desk repeating words. It’s individualized, layered, and often creative.  

    A few of the most effective approaches include: 

    • Augmentative and Alternative Communication: AAC tools ranging from picture boards to high-tech devices that generate speech. 
    • Picture Exchange Communication System (PECS): A step-by-step program where children learn to exchange images for what they want, laying the foundation for symbolic language. 
    • Total Communication Approach: Using speech, sign language, gestures, and AAC together—so no door to communication stays closed. 
    • Prompts for Restructuring Oral Muscular Phonetic Targets (PROMPT) Therapy: A tactile method where therapists use touch cues on the child’s face to guide speech movements. 
    • Oral-Motor Therapy: Strengthening and coordinating muscles needed for speech, especially when motor planning challenges are present. 
    • Naturalistic Developmental Behavioral Interventions (NDBI): Embedding communication practice into play and routines, making learning part of daily life. 
    • Vocal Play and Shaping: Moving from hums and sounds toward syllables and words, often supported with visual or tactile prompts. 
    • Joint Attention Interventions: Building the foundation of language by helping the child share focus with another person. 

    Therapy can take place one-on-one, in group sessions, at home with caregiver coaching, or even online. What matters most is that it meets the child where they are, and empowers families to recognize every sound, gesture, or picture as a step toward connection. 

    Assistive Technology and Alternative Communication (AAC)

    For children who are not yet speaking – or who speak inconsistently – AAC is not a last resort. It’s a first line of support. And crucially, using AAC does not prevent speech from developing. Research consistently shows it supports it.

    Here are the main tools families and therapists use:

    • PECS (Picture Exchange Communication System): Children start by handing a picture card to request something they want. Over six structured phases, they build toward sentence strips and spontaneous communication. PECS is widely used in Indian therapy settings and can be implemented at home with training.
    • Speech-generating devices and apps: Apps like Proloquo2Go, TouchChat, or even low-cost alternatives like LetMeTalk (free, Android) allow children to tap symbols that produce spoken output. These give a voice to children who have one – just not yet in the traditional sense.
    • Sign language: Indian Sign Language (ISL) or simplified sign systems can bridge the communication gap, particularly for children with good motor imitation skills. Signs do not replace speech; for many children, they accompany it.
    • Visual supports: Schedules, choice boards, and “first-then” cards reduce anxiety and create predictable communication opportunities throughout the day.

    The ASHA Practice Portal notes there is no minimum age for AAC introduction. If your child is struggling to communicate, ask their speech therapist about AAC options today.

    Home Speech Intervention Strategies

    Speech therapy may happen in a clinic, but the real magic unfolds in kitchens, living rooms, and playgrounds. Everyday routines, the breakfast table, bath time, or a game in the park, are where language comes alive. 

    The principle is simple: when a child makes an attempt and someone notices and responds, they learn that communication works. That lesson, repeated hundreds of times in small ways, is what builds speech. 

    Here are some strategies, backed by decades of speech-language research, that parents can weave into daily life: 

    • Model Functional Language: Use short, clear phrases like “more juice” or “open door.” Repeat them in context so the link between words and actions becomes obvious. 
    • Create Communication Temptations: Place a toy just out of reach, or keep the lid on a snack jar. These small obstacles encourage your child to signal for help. 
    • Narrate Actions (Parallel Talk and Self-Talk): Describe what your child is doing (“rolling ball”) or what you’re doing (“pouring water”). It builds a running language map of the world. 
    • Expand and Extend: If your child says “car,” you might add “big car” or “red car.” This gently models more complex language without pressure. 
    • Use Wait Time: After asking a question or making a comment, pause for a few seconds. That extra space gives your child time to process and respond. 
    • Respond to Every Modality: Whether your child points, vocalizes, signs, or uses AAC, treat it as valid communication. 
    • Let Communication Have Consequences: If they ask for water (in any form), make sure they get water. That link reinforces the purpose of communication. 

    One of the most powerful ingredients here is co-attention. It refers to sharing focus on the same object or activity.  

    Looking at a drawing together, pointing at a toy, or saying, “Wow, you built this tower!” creates a moment of connection. These small exchanges spark curiosity and open the door to new words. 

    Important: Skipping therapist-guided exercises, routines, or prompts may feel small in the moment, but over time, it slows or blocks your child’s gains. Every repetition counts. 

    📥 Free download: Printable daily routine chart for autistic children

    Parting Words: Beyond Speech Alone

    Communication focus beyond speech.

    It’s important to remember that when do autistic kids start talking is only part of the story. Some children may never speak fluently, but still develop meaningful communication through AAC, gestures, or devices. Timing, coordination, and repeated practice all play a role.  

    For some autistic children, additional challenges like dyspraxia or childhood apraxia of speech make producing spoken language even harder. 

    This doesn’t mean they cannot connect with others. It simply means their journey to verbal communication may take a different path.  

    When families and therapists recognize these overlaps, the focus shifts from forcing words to opening multiple avenues for communication. 

    For more information, feel free to contact us. 

    Frequently Asked Questions

    How to know if an autistic child will talk? 

    There’s no fixed formula. However, some signs suggest potential for speech development: 

    • Does the child use gestures (like pointing or waving)? 
    • Do they make meaningful sounds, even if not full words? 
    • Do they show understanding—like responding to their name or following simple instructions? 
    • Are they interested in social interaction or imitating sounds/actions? 

    These are often encouraging signs. Still, some children may use AAC (Augmentative and Alternative Communication) methods instead of spoken words, and that’s equally valid communication. 

    At what age do autistic children talk? 

    It varies a lot. Some autistic children speak on time (around 12–18 months), others may start talking at 2, 3, or even after 5 years old. 

    Some begin with single words, then gradually combine them. Others may have a speech burst later, especially after starting targeted support like speech therapy or play-based interaction. 

    Do autistic kids talk eventually? 

    Many do. But not all. Some become fluent speakers, some develop a few functional words or phrases, and others use nonverbal methods long-term. 

    It’s also common for speech to start and then pause or plateau. This doesn’t always mean it’s lost for good. With the right supports, gains can return or accelerate. 

    When do autistic kids start talking fluently? 

    For those who do become fluent speakers, fluency often emerges between 4 and 7 years, sometimes later. 

    “Fluent” can look different, too: for some, it means full conversations; for others, scripted or echolalic speech may still serve real communication purposes. 

    Important: Fluency doesn’t always mean social ease. Even verbally fluent autistic individuals might struggle with back-and-forth conversation or emotional expression.

    When do autistic kids start talking? 

    Some start with first words as early as 12 to 24 months, but it’s also common for speech to emerge later, 3, 4, or even 5+ years. 

    Others may show early speech that regresses or disappears around age 2, especially in children with co-occurring conditions like childhood apraxia of speech. 

    Do non-verbal autistic kids ever talk? 

    Yes, some do. “Non-verbal” doesn’t mean “never verbal.” 

    Many children once considered non-verbal go on to use spoken words—sometimes after age 5 or even 8—especially with AAC support, language-rich environments, and personalized therapy. 

    At what age does an autistic child speak fluently? 

    If they develop fluent speech, it’s typically around 4 to 7 years old. But this varies. 
    Children who speak early might still struggle with conversational fluency or social use of language well into adolescence. 

    Others may speak fluently in a structured or academic setting, but not in daily social interactions. That’s still valid communication – just with a different style.

    When did your autistic child start talking compared to others? 

    Parents often share very different timelines. Some report their child said first words around age 2, while others mention speech emerging much later, sometimes after 5 years. This variation is normal, and comparing one child’s journey with another’s can cause unnecessary worry. 

    Do nonverbal autistic children ever speak later in life? 

    Yes, some do. Even if a child is nonverbal at age 4 or 5, progress can still happen with therapy, AAC devices, and consistent support. Some individuals develop speech in adolescence or adulthood, though others may prefer nonverbal communication. 

    What therapies help if my autistic child is not talking yet?  

    Speech therapy, AAC tools, and naturalistic play-based approaches are widely used. Programs like PECS and PROMPT therapy are also effective. To know which option best suits your child, you can reach out to our training center for professional guidance. 

    Will my autistic son ever talk if he hasn’t started by age 4?

    Many children show speech growth after age 4, but others may remain minimally verbal. Progress often depends on early intervention, consistency, and tailoring therapy to your child’s strengths. If you’re unsure, it’s a good time to contact our training center for a personalized assessment. 

    At what age do autistic children start talking in complete sentences? 

    Some may form simple sentences around 3–5 years, while others take longer. Many autistic children first echo words or use short phrases before building into fluent sentences. With practice and therapy, even delayed speakers can gain meaningful communication skills.

    Disclaimer: This article is intended for educational and informational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. If you are pregnant or have concerns about medication use during pregnancy, please consult a qualified healthcare provider. If your child has received an autism diagnosis and you have questions about causes or support, please reach out to a trained specialist or an autism-focused organisation for guidance.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

    Useful Sources

  • Common Learning Disabilities in Children

    Common Learning Disabilities in Children

    Every child learns differently, but when a child consistently struggles to read, write, understand numbers, or process information despite receiving appropriate instruction, it may indicate a learning disability. 

    Such neurological differences tend to affect how the brain processes information rather than a child’s intelligence or willingness to learn. According to the research, specific learning disorders affect approximately 5% to 15% of school-aged children across different languages and cultures, making early identification and intervention essential. 

    Understanding all the different types of learning disabilities can help parents, educators, and caregivers recognise challenges early, access the right support, and empower children to develop the skills and confidence they need to thrive both inside and outside the classroom.

    What Are Learning Disabilities?

    Infographic explaining what learning disabilities are and how they affect reading, writing, math, and learning skills in children

    Learning disabilities are lifelong neurological differences that affect the way the brain receives, processes, stores, or communicates information. Poor teaching, low intelligence, hearing problems, or lack of effort do not cause them.

    Children with learning disabilities often have average or even above-average intelligence but struggle in one or more academic areas despite receiving appropriate instruction.

    The list of learning disabilities covers several conditions that affect reading, writing, mathematics, language, motor coordination, memory, and organisation.

    It is important to distinguish learning disabilities from intellectual disability. While intellectual disability affects overall cognitive functioning, learning disabilities impact specific academic skills.

    Learning disabilities can affect:

    • Reading comprehension
    • Writing and spelling
    • Mathematical reasoning
    • Language processing
    • Organisation and planning
    • Attention and memory
    • Motor coordination

    Many children experience more than one learning disability simultaneously, making comprehensive assessment essential.

    What Are the 7 Types of Learning Disabilities?

    Infographic showing the seven types of learning disabilities including dyslexia, dysgraphia, dyscalculia, APD, NVLD, visual processing disorder, and language processing disorder

    Parents and educators often ask: What are the 7 main types of learning disabilities, and how do they affect a child’s development? Learning disabilities are neurological conditions that interfere with the brain’s ability to receive, process, store, or communicate information. 

    Each condition affects a different set of skills, which means children with learning disabilities require tailored support rather than a one-size-fits-all approach.

    It is also important to remember that many children experience more than one learning disability at the same time. For example, a child with dyslexia may also have dysgraphia, while another may have both dyscalculia and attention difficulties. 

    Early diagnosis and evidence-based interventions can dramatically improve academic performance, confidence, and overall wellbeing.

    Below is a comprehensive list of learning disabilities, explaining the seven most recognised types and how they present in children.

    1. Dyslexia

    Dyslexia is the most common type of learning disability and primarily affects reading, spelling, and language processing. It occurs because the brain processes written language differently, making it difficult to recognise words accurately and fluently.

    Children with dyslexia are often intelligent and curious but struggle with decoding words, connecting letters to sounds, and reading smoothly. 

    These challenges can affect reading comprehension and classroom participation if appropriate support is not provided.

    Common signs include:

    • Slow or hesitant reading
    • Difficulty recognising familiar words
    • Frequent spelling mistakes
    • Confusing similar-looking letters or words
    • Trouble remembering letter-sound relationships
    • Avoiding reading aloud

    One of the most common examples of a specific learning disability is a child who can retell a story perfectly after hearing it but struggles to read the same story independently.

    Structured literacy programmes, multisensory phonics instruction, audiobooks, and additional classroom support have been shown to improve reading outcomes for children with dyslexia.

    2. Dysgraphia

    Dysgraphia is a learning disability that typically affects handwriting and written expression. Although children know what they want to say, they often find it difficult to organise their thoughts on paper or write them clearly.

    The difficulty extends beyond poor handwriting. Children may struggle with spelling, sentence construction, grammar, punctuation, and organising ideas into coherent paragraphs.

    Some common signs include:

    • Illegible or inconsistent handwriting
    • Slow writing speed
    • Difficulty copying text
    • Poor spacing between words and letters
    • Hand fatigue while writing
    • Frequent grammatical and spelling errors

    Children with dysgraphia often perform much better during verbal discussions than in written assignments. Occupational therapy, handwriting interventions, keyboard use, and structured writing support can help improve both handwriting and written communication.

    3. Dyscalculia

    Dyscalculia affects a child’s ability to understand numbers, mathematical concepts, and calculations. It is sometimes referred to as “mathematics dyslexia” because of its impact on numerical reasoning.

    Children with dyscalculia may struggle to understand number relationships, estimate quantities, remember mathematical facts, or solve arithmetic problems even after repeated practice.

    Typical difficulties include:

    • Counting accurately
    • Recognising numerical patterns
    • Understanding place value
    • Learning multiplication tables
    • Telling the time
    • Managing money
    • Solving multi-step mathematical problems

    One of the most common examples of a specific learning disability is a child who understands classroom discussions but cannot remember basic addition or subtraction facts despite regular practice.

    Visual teaching methods, number lines, manipulatives, interactive activities, and real-life mathematical examples can help children develop stronger numerical understanding.

    4. Auditory Processing Disorder (APD)

    Auditory Processing Disorder is known to affect how the brain processes sounds rather than how the ears hear them. Children with APD usually have normal hearing but struggle to interpret spoken information, particularly in noisy environments such as classrooms.

    These difficulties can affect listening, communication, and classroom learning.

    Common symptoms include:

    • Frequently asking people to repeat instructions
    • Difficulty following verbal directions
    • Confusing similar-sounding words
    • Trouble understanding speech in noisy settings
    • Difficulty remembering spoken information

    For example, a teacher may give several instructions in class, but the child remembers only the first or last.

    Speech and language therapy, classroom accommodations, assistive listening devices, and reducing background noise can significantly improve learning outcomes.

    5. Visual Processing Disorder

    Visual Processing Disorder primarily affects how the brain interprets visual information. It differs from vision problems, as children can often see clearly during an eye examination yet still struggle to process what they see.

    Children may experience challenges with reading, recognising patterns, understanding spatial relationships, and accurately interpreting visual information.

    Signs may include:

    • Getting confused between similar letters such as “b” and “d”
    • Difficulty copying from the board
    • Problems identifying shapes or patterns
    • Losing their place while reading
    • Difficulty understanding maps, charts, or diagrams

    These challenges may interfere with reading fluency, mathematics, handwriting, and everyday classroom activities.

    Support strategies include using larger print, colour coding, visual organisers, and breaking visual tasks into smaller, manageable steps.

    6. Non-Verbal Learning Disability (NVLD)

    Non-Verbal Learning Disability primarily affects visual-spatial reasoning, motor skills, organisation, and social understanding, while verbal abilities often remain strong.

    Children with NVLD usually develop excellent vocabulary and language skills but find it difficult to interpret non-verbal communication, understand visual information, or organise tasks.

    Common characteristics include:

    • Difficulty understanding facial expressions and body language
    • Poor coordination and motor planning
    • Problems with organisation and time management
    • Difficulty interpreting diagrams and visual instructions
    • Challenges with social interactions

    A child with NVLD may excel in reading and speaking but struggle to complete puzzles, understand graphs, or navigate unfamiliar environments.

    Occupational therapy, social skills training, structured routines, and explicit teaching of organisational skills can help children manage these challenges successfully.

    7. Language Processing Disorder (LPD)

    Language Processing Disorder affects the brain’s ability to understand and express spoken language. It differs from hearing impairment because children can hear sounds normally but have difficulty processing the meaning of language.

    Children with LPD may struggle to understand conversations, remember verbal information, or express themselves clearly.

    Common signs include:

    • Difficulty understanding complex instructions
    • Limited vocabulary for their age
    • Trouble finding the right words
    • Frequently misunderstanding conversations
    • Difficulty answering questions appropriately
    • Challenges following classroom discussions

    Among the different types of learning disabilities, Language Processing Disorder can significantly affect communication, reading comprehension, and academic achievement if left unaddressed.

    Speech and language therapy, simplified instructions, visual supports, and repetition can help children improve both receptive and expressive language skills.

    What Causes Learning Disabilities?

    Infographic illustrating common causes of learning disabilities including genetics, brain development, prenatal factors, and childhood illness

    Researchers believe that learning disabilities result from differences in brain development and functioning rather than parenting style or educational opportunities.

    Several factors may increase the likelihood of developing a learning disability.

    1. Genetic influences

    Learning disabilities often run in families. Studies have shown strong hereditary links, particularly for dyslexia and dyscalculia.

    2. Brain development

    Differences in how certain brain regions process language, numbers, or visual information can contribute to learning challenges.

    3. Premature birth or low birth weight

    Children born prematurely have a higher likelihood of experiencing developmental and learning difficulties.

    4. Prenatal factors

    Exposure to alcohol, drugs, infections, or severe nutritional deficiencies during pregnancy may affect brain development.

    5. Early childhood illness or injury

    Although less common, serious head injuries or neurological illnesses can influence learning abilities.

    Importantly, learning disabilities are not caused by laziness, poor parenting, excessive screen time, or lack of intelligence.

    Early Signs of Learning Disabilities

    Early signs of learning disabilities in children infographic highlighting reading, writing, speech, memory, and organization challenges

    Recognising difficulties early allows children to receive interventions before academic struggles become overwhelming.

    Some common early signs of learning difficulties in students include:

    • Difficulty recognising letters or sounds
    • Delayed speech and language development
    • Persistent spelling mistakes
    • Trouble remembering sequences
    • Difficulty following multiple instructions
    • Slow reading speed
    • Frequent reversal of letters beyond the expected developmental age
    • Difficulty understanding numbers
    • Problems organising schoolwork
    • Poor handwriting
    • Avoidance of reading or writing tasks

    Children with autism may also experience learning disabilities. However, autism and learning disabilities are separate conditions that can occur independently or together. A comprehensive developmental assessment helps identify each child’s unique strengths and support needs.

    Can a Child Have More Than One Learning Disability?

    Infographic explaining that children can have multiple learning disabilities requiring comprehensive assessment and personalized support

    Yes. It is common for children to experience more than one condition from the learning disabilities list. For example, a child with dyslexia may also have dysgraphia, while another may experience dyscalculia alongside Language Processing Disorder.

    Additionally, some children with autism, ADHD, developmental language disorder, or dyspraxia may also have one or more types of learning disabilities. Because these conditions can overlap, a comprehensive assessment by qualified professionals is essential to accurately identify each child’s strengths and challenges.

    Understanding the 7 main types of learning disabilities allows parents and educators to recognise early warning signs and provide timely, evidence-based support. With the right interventions, classroom accommodations, and encouragement, children with learning disabilities can develop effective coping strategies, achieve academic success, and build the confidence needed to thrive throughout their lives.

    How Are Learning Disabilities Diagnosed?

    Learning disabilities diagnosis infographic showing comprehensive assessments by specialists for early intervention

    Recognising the types of learning disabilities is only the first step. An accurate diagnosis is equally important because different learning disabilities require different forms of support. Identifying a child’s specific strengths and challenges early allows families and educators to provide interventions before learning difficulties begin to affect confidence and emotional wellbeing.

    There is no single test that can diagnose all learning disabilities. Instead, specialists carry out a comprehensive assessment that may include:

    • A detailed developmental, medical, and family history
    • Feedback from parents, teachers, and caregivers
    • Standardised assessments of reading, writing, mathematics, and language skills
    • Evaluations of memory, attention, reasoning, and cognitive abilities
    • Vision and hearing tests to rule out sensory impairments

    According to the research, symptoms of a Specific Learning Disorder should generally persist for at least six months despite targeted interventions before a formal diagnosis is made. Once identified, professionals can recommend personalised strategies that address the child’s unique learning needs.

    Supporting Children with Learning Disabilities

    Infographic showing teachers, parents, and therapists supporting children with learning disabilities through personalized learning

    A diagnosis is not a limitation. Instead, it provides a roadmap for helping children learn more effectively. With timely intervention and consistent support, children with learning disabilities can strengthen their academic skills, build resilience, and become confident learners.

    Effective support often combines educational strategies, therapeutic interventions, and family involvement. Depending on the child’s needs, support may include:

    • Multisensory teaching methods that engage visual, auditory, and hands-on learning
    • Structured literacy programmes for reading and spelling difficulties
    • Speech and language therapy to improve communication skills
    • Occupational therapy to develop handwriting, motor skills, and organisation
    • Assistive technologies including text-to-speech software, audiobooks, and speech-to-text tools
    • Breaking complex tasks into smaller, achievable steps
    • Positive reinforcement that celebrates effort and progress

    Schools also play a vital role by creating an inclusive learning environment. Helpful classroom accommodations may include:

    • Extra time during examinations and assignments
    • Visual schedules and graphic organisers
    • Simplified, step-by-step instructions
    • Reduced copying from the board
    • Keyboard use instead of lengthy handwritten work
    • Alternative methods of assessment where appropriate

    Parents can reinforce these strategies at home by maintaining predictable routines, reading together regularly, encouraging strengths beyond academics, and maintaining open communication with teachers and therapists. When families and schools work together, children receive the consistent support they need to thrive.

    Living with Learning Disabilities

    Living with learning disabilities infographic highlighting emotional support, personalized education, and lifelong success

    Learning disabilities are lifelong neurological differences, but they do not prevent children from achieving their goals. With the right support, many children develop effective coping strategies and go on to excel in education, careers, and everyday life.

    However, learning disabilities can influence more than academic performance. Without appropriate support, children may experience:

    • Reduced self-confidence
    • Anxiety about school or examinations
    • Frustration with everyday learning tasks
    • Difficulty building peer relationships
    • Avoidance of reading, writing, or mathematics activities

    Addressing these emotional challenges is just as necessary as improving academic skills. Encouragement, patience, and recognising a child’s strengths can significantly boost their confidence and motivation.

    It is also important to understand that autism and learning disabilities are separate neurodevelopmental conditions, although they can occur together. Some autistic children may also have one or more types of learning disabilities, while others may not. A comprehensive developmental assessment helps professionals understand each child’s complete profile and recommend interventions that support both learning and overall development.

    Supporting Every Child’s Potential with India Autism Center

    India Autism Centre infographic promoting personalized evidence-based support for children with learning disabilities

    At India Autism Center (IAC), we believe every child deserves the opportunity to learn in a way that reflects their individual strengths and needs. Through evidence-based interventions, multidisciplinary expertise, family guidance, and inclusive educational support, we help children with autism and learning disabilities develop academic, communication, social, and life skills. By working closely with families, educators, and therapists, we create an environment where children feel understood, supported, and can achieve their full potential.

    Conclusion

    Conclusion infographic emphasizing early understanding and support for children with learning disabilities

    Understanding the different types of learning disabilities empowers parents, educators, and caregivers to recognise challenges early and provide the right support at the right time. 

    Although these conditions affect how children process and acquire information, they do not define intelligence or future success. 

    With an accurate diagnosis, personalised interventions, collaborative support from families and schools, and a nurturing environment, children who have learning disabilities can build confidence, overcome obstacles, and live an enriched life.

    Frequently Asked Questions

    At what age can learning disabilities be identified?

    Early signs may appear in preschool, but many learning disabilities become more noticeable once children begin reading, writing, and solving mathematical problems in primary school.

    Is dyslexia the most common type of learning disability?

    Yes. Dyslexia is widely recognised as the most common type of learning disability, affecting reading accuracy, fluency, spelling, and language processing.

    Are learning disabilities hereditary?

    Research suggests that several types of learning disabilities, particularly dyslexia and dyscalculia, have a strong genetic component and may run in families.

    Which school accommodations benefit children with learning disabilities?

    Helpful accommodations include additional exam time, assistive technology, simplified instructions, visual organisers, alternative assessments, and reduced copying from the board.

    Can children with learning disabilities succeed academically?

    Absolutely. With early diagnosis, personalised interventions, appropriate classroom support, and family involvement, many children perform well in school and higher education.

  • Autism & Parenting: Why Your Role Matters

    Autism & Parenting: Why Your Role Matters

    Managing autism in a child is one of the most important journeys a parent will ever take. When we talk about the role of parents in managing an autistic child, we’re talking about more than routines and therapies. We’re talking about love, learning, patience, and continuous support.

    Autism spectrum disorder (ASD) affects children differently, and as a parent or caregiver, you are central to your child’s growth, well-being, and future success.

    In this guide, I will share practical insights, educational information, and real-life tips to help you navigate parenting an autistic child with confidence. You’ll learn how to handle an autistic child, what works, what doesn’t, and how your role makes a lasting impact on your child’s life.

    Understanding Autism and Why Parents Matter

    Understanding Autism and Why Parents Matter

    Autism spectrum disorder is a complex neurological condition, often presenting challenges in communication, social interaction, and behavior. No two autistic children are the same — every child has unique strengths and challenges. Parents are usually among the first to notice early signs of autism. That means parents are also the first responders in seeking help and support.

    Your role extends far beyond caregiving. You become:

    • An advocate
    • A teacher
    • A therapist at home
    • And the most important emotional anchor in your child’s life

    And here’s what you can do

    1. Early Intervention: Research from the National Institutes of Health (NIH) has consistently highlighted the significance of early intervention in improving the outcomes of autistic children.

    Parents, being the first to notice developmental differences, play a crucial role in seeking timely intervention. Early diagnosis and intervention, often involving therapies tailored to the child’s unique needs, can lead to substantial improvements in communication skills, behaviour management, and social interactions.

    Here is a comprehensive guide on Early Intervention for Autism: A Parent’s Guide to Better Outcomes.

    2. Individualised Support: No two autistic children are alike, and parents are the ones who best understand their child’s strengths, challenges, and triggers. This insight enables parents to collaborate effectively with healthcare professionals and educators to create individualised support plans. The active participation of parents in crafting these plans ensures that the child’s specific needs are met comprehensively.

    3. Daily Life Skills: Autistic children often require targeted assistance in acquiring daily life skills that neurotypical children may grasp more naturally. Parents are instrumental in teaching essential life skills, ranging from personal hygiene routines to basic communication techniques. Also, don’t forget Social Skills, which is a very common challenge faced by children on the spectrum. This involvement fosters the child’s independence and self-confidence, setting the stage for greater autonomy in adulthood.

    Want to know more? Get in touch with us.

    Challenges Faced by Parents 

    Challenges Faced by Parents of Autistic Child

    Parenting an autistic child can be emotionally and physically demanding. The relentless effort required to provide optimal care, along with potential financial strains from therapy and medical expenses, can take a toll on parental well-being. At India Autism Center (IAC), we are dedicated to autism advocacy, and thus, we recognise the importance of offering parents a support network and resources to navigate these challenges.

    Empowering Parents Through Requisite Knowledge

    Education is an empowering tool for parents of autistic children. Being well-informed about autism spectrum disorder equips parents to make informed decisions, advocate for their child’s needs, and collaborate effectively with professionals. Workshops, webinars, and information-sharing sessions offered by dedicated social organisations serve to enhance parental knowledge and confidence in managing their child’s autism.

    Promoting Emotional Well-being

    The emotional well-being of parents directly influences the support they provide to their autistic children. We emphasise the significance of self-care for parents, encouraging them to seek respite and emotional support when needed. Engaging in peer support groups and counselling sessions can alleviate stress and foster a more resilient caregiving environment.

    Role of Parents in Managing an Autistic Child

    Role of Parents in Managing an Autistic Child

    Parental involvement in autism management not only benefits the child in the present but also lays the foundation for the child’s future. As autistic children grow into autistic adults, they require continued guidance and support from their parents. Equipped with an understanding of their child’s unique strengths, parents can play a vital role in fostering the independence and social integration of autistic adults.

    Personalized Support: Know Your Child Best

    One of the central pillars of parenting an autistic child is understanding your child’s strengths, struggles, and triggers. This knowledge is the foundation for creating a supportive environment at home and beyond. No professional can know your child as you do.

    Here’s what personalized support looks like:

    • Tailor routines to your child’s comfort
    • Use visual schedules or cue cards to prepare them for transitions
    • Modify sensory experiences (noise levels, lighting, textures) based on your child’s preferences

    Such personalization allows your child to feel secure and supported emotionally.

    Building Daily Life Skills

    As a parent, you play a direct role in helping your child build daily living skills — such as feeding, dressing, hygiene, and simple communication. These skills boost independence and self-confidence.

    Simple strategies you can use at home include:

    • Breaking routines into small, manageable steps
    • Using visuals and timers for transitions
    • Celebrating progress, no matter how small

    This kind of hands-on autism management teaches practical life skills while strengthening your bond.

    Want to know more? Get in touch with us.

    Positive Reinforcement: Focus on What Works

    Positive reinforcement is one of the most effective strategies in Tips for Parenting A Child With Autism. It means you praise your child when they show good behavior or achieve a small goal, encouraging them to repeat that behavior. Let’s break this down:

    • Use praise, stickers, favourite activities, or small rewards
    • Notice every improvement — not just perfection
    • Avoid punishment — it often causes confusion or anxiety in autistic children

    This method builds confidence and sets a positive tone for learning and behavior management.

    What Not to Do as a Parent of an Autistic Child

    What Not to Do as a Parent of an Autistic Child

    Equally important in parenting an autistic child is understanding what not to do. Avoiding certain responses can prevent stress and conflict.

    • Avoid sudden changes in routine — these can cause anxiety
    • Do not compare your child to neurotypical peers
    • Don’t ignore your child’s sensory needs (e.g., noisy environments)
    • Avoid traditional punishments — these often confuse rather than teach

    Understanding these “don’ts” is just as valuable as knowing the dos. They help you keep your environment calm, predictable, and supportive.

    Practical Tips You Can Use Today

    Here are quick, actionable tips for daily life:

    • Keep things simple and predictable
    • Praise progress often
    • Use visuals and schedules
    • Watch and respond to non-verbal cues
    • Create sensory-friendly spaces at home
    • Spend quality one-on-one time daily

    Your Role in Your Child’s Therapy – At the Clinic and at Home

    Your Role in Your Child's Therapy

    Here’s a number that changes everything: your child receives professional therapy for 1 to 2 hours per week. They live with you for the other 166 hours. That gap is where parents become the most powerful intervention of all.

    Research consistently shows that children whose parents actively reinforce therapy goals at home make significantly faster progress than those who receive clinic-based therapy alone. You don’t need a degree in psychology to do this. You need consistency, curiosity about your child, and a few practical techniques.

    Applied Behaviour Analysis (ABA): How Parents Reinforce Progress Daily

    ABA is one of the most evidence-based approaches to handling an autistic child. At its core, ABA is about understanding what motivates your child and using that to teach new skills and reduce challenging behaviours. Your child’s therapist designs the programme – but you implement it at home, dozens of times a day.

    What parents can do between sessions:

    • Discrete Trial Training (DTT) at the dinner table: If your child is learning to say “more,” prompt them every time they want more food, wait for the attempt, then reward immediately. Three minutes, three times a day adds up to hundreds of practice trials a week.
    • Natural Environment Teaching (NET): Embed the skill into real life. If the goal is pointing, practise pointing at things during a walk to the park, not just at flashcards.
    • Data collection doesn’t have to be complicated: A simple tick in a notebook – “Did she make eye contact when I called her name today? Yes / No” – gives your therapist gold-standard feedback.
    • Ask your therapist for a “parent cheat sheet” – a one-page summary of the current targets and exactly how to prompt and reward them.

    The principle is simple: therapy teaches the skill, home practice makes it automatic.

    Speech Therapy at Home: Simple Exercises Parents Can Do

    Speech therapy sessions are precious – and short. The exercises your child’s speech-language pathologist (SLP) gives you are not optional homework. They are the main event.

    Practical exercises for parents:

    • Imitation games: Sit face-to-face and take turns making sounds, facial expressions, and simple actions. Start with whatever your child already does – blowing raspberries counts. Imitation is the foundation of language.
    • Narrate everything: “Now we’re washing hands. Water on. Soap. Rub rub rub. Rinse.” Running commentary during daily routines builds vocabulary without any formal “teaching” time.
    • Expand, don’t correct: If your child says “ball,” you say “big red ball” or “roll the ball.” You’re modelling the next level of language without making them feel wrong.
    • Pause and wait: After asking a question or making a request, count silently to 10 before jumping in. Autistic children often need more processing time than we give them.
    • Sing it: Songs and rhymes use different neural pathways than speech. Many children who struggle to say a word can sing it. Use this.

    For non-verbal children, your SLP may introduce AAC (Augmentative and Alternative Communication) – picture cards, speech-generating devices, or apps like Proloquo2Go. Learn to use these tools alongside your child. The more you model AAC use, the faster your child will adopt it.

    Occupational Therapy: Creating Sensory-Friendly Spaces

    Occupational therapists (OTs) work on the sensory processing, fine motor, and daily living skills that help your child function comfortably in the world. Their recommendations for the home environment are not suggestions – they are prescriptions.

    What parents can implement at home:

    • Proprioceptive input before demanding tasks: A few minutes of jumping on a trampoline, carrying a heavy backpack, or pushing a loaded trolley can calm the nervous system and improve focus. Ask your OT what “heavy work” activities suit your child.
    • Tactile desensitisation: If your child hates having their hair washed or nails cut, work with your OT on a gradual desensitisation programme. Don’t force it – that creates trauma. Build tolerance slowly.
    • Vestibular activities: Swinging, rocking, and spinning (in controlled amounts) can be regulating for many autistic children. A garden swing or a rocking chair is a low-cost investment with high returns.
    • Fine motor practice: Playdough, threading beads, tearing paper, and using tongs to pick up objects all build the hand strength needed for writing and self-care.

    The goal is to make your home an extension of the therapy room – a place where your child’s nervous system feels safe enough to learn.

    Creating an Autism-Friendly Home Environment

    Creating an Autism-Friendly Home Environment

    The physical environment of your home sends a constant message to your child’s nervous system: “You are safe here” or “This is overwhelming.” Building an autism-friendly home doesn’t require a renovation. It requires intentionality.

    Visual Schedules and Routine Boards

    Autistic children thrive on predictability. Visual schedules make the invisible structure of the day visible and concrete.

    How to set one up:

    1. Choose your format: A strip of laminated picture cards on a velcro board works brilliantly. So does a printed A4 sheet in a plastic sleeve. In India, you can print picture symbols from free resources like Boardmaker or use hand-drawn pictures – the child’s recognition of the image matters more than its artistic quality.

    2. Cover the whole day: Wake up → brush teeth → breakfast → school → lunch → therapy → play → bath → dinner → bed. Every transition, pictured.

    3. Make it interactive: Have your child physically move the “done” card to a finished pocket. This gives them agency and reinforces the sequence.

    4. Add a “first-then” board for immediate transitions: “First shoes, then park.” Two pictures. Enormous reduction in resistance.

    5. Low-cost Indian options: Lamination pouches (₹5 each at any stationery shop), velcro strips from fabric stores, and printed symbols from free online sources like Widgit Online or Boardmaker Share make this completely affordable.

    Sensory Corners and Calm-Down Spaces

    Every autistic child needs a place in the home where they can go when the world gets too loud, too bright, or too much. This is not a punishment corner. It is a regulation station.

    What to include:

    • Dim lighting: A string of warm fairy lights or a salt lamp is far less harsh than overhead tube lights.
    • Compression: A beanbag, a weighted blanket (around 10% of body weight), or even a pile of cushions provides deep pressure that many autistic children find calming.
    • Sensory tools: Fidget toys, a small tray of kinetic sand, noise-cancelling earmuffs (available on Amazon India for ₹800–₹1,500), or a simple stress ball.
    • Favourite comfort items: A beloved soft toy, a picture of the family, a favourite book.
    • Clear rules: This space is always available, never taken away as punishment, and never used to isolate the child against their will.

    Teach your child to go to this space proactively – before they reach meltdown – by practising during calm moments.

    Communication Aids: PECS, AAC Devices, and Picture Cards

    For children who are minimally verbal or non-verbal, communication aids are not a last resort. They are a first right.

    • PECS (Picture Exchange Communication System): A structured programme where the child learns to hand a picture card to a communication partner to make a request. It begins with a single picture for a highly desired item and builds to multi-card sentences. PECS can be implemented at home with guidance from a trained SLP.
    • Low-tech AAC: A simple communication book – a ring binder of laminated picture cards organised by category (food, feelings, activities, people) – costs under ₹500 to make and can transform a non-verbal child’s ability to communicate.
    • High-tech AAC: Apps like Proloquo2Go, TouchChat, or LetMeTalk (free on Android) turn a tablet into a speech-generating device. The Government of India’s ADIP (Assistive Devices for Persons with Disabilities) scheme provides subsidised assistive technology for eligible families.
    • Core vocabulary boards: A small laminated card with 20–30 high-frequency words (more, stop, help, want, go, no, yes, I, you) placed in every room of the house gives your child communication access wherever they are.

    The research is unambiguous: using AAC does not prevent speech development. It supports it.

    Advocating for Your Child in India – Schools, Rights, and Resources

    Advocating for Your Child in India - Schools, Rights, and Resources

    This is where many Indian parents feel most lost. The therapy world has a language. The school world has a different one. And the legal world has yet another. Here’s what you need to know – in plain terms.

    Understanding the RPWD Act 2016 and Your Child’s Legal Rights

    The Rights of Persons with Disabilities Act, 2016 (RPWD Act 2016) is the most important piece of legislation for Indian families navigating RPWD Act 2016 autism rights. Autism spectrum disorder is explicitly listed as a recognised disability under this Act – which means your child has enforceable legal rights, not just moral claims.

    Key rights under the RPWD Act 2016:

    • Right to free education (ages 6–18): Children with benchmark disability (40% or more) are entitled to free education in a neighbourhood school or a special school of their choice.
    • Right to inclusive education: Government-funded and government-recognised schools cannot refuse admission to a child on the basis of disability. They must provide reasonable accommodation – adapted teaching methods, accessible infrastructure, and support staff.
    • Right to reasonable accommodation: Schools must make adjustments so that the child can participate equally. This includes extra time in exams, a scribe, modified question papers, or a separate room for assessments.
    • Right against discrimination: Any school that refuses admission or expels a child because of autism is violating the law.
    • Disability certificate: Issued by a government-authorised medical authority, this certificate is the gateway to all legal protections and government schemes. Apply at your nearest government hospital or district disability rehabilitation centre (DDRC).

    How to use this: If a school refuses your child admission or fails to provide support, you can file a complaint with the State Commissioner for Persons with Disabilities. The RPWD Act gives the Commissioner powers to investigate and direct corrective action.

    How to Work with Schools: IEP Equivalents in India

    India does not have a formal Individualised Education Programme (IEP) system mandated by law the way the US does under IDEA. However, the spirit of the IEP – a customised learning plan – is embedded in the RPWD Act’s requirement for “reasonable accommodation” and “special provisions.”

    What parents can do:

    • Request a written support plan from the school at the beginning of each academic year. Put your request in writing (email or letter) so there is a record.
    • Identify the school’s special educator or resource room teacher – this is your primary contact. Many government and private schools now have resource rooms under the Samagra Shiksha Abhiyan.
    • Share your child’s assessment reports with the school. A psychoeducational assessment from a clinical psychologist or a developmental paediatrician gives teachers concrete, actionable information.
    • Ask for specific accommodations in writing: Preferential seating, reduced homework, oral exams instead of written, a buddy system, or a quiet space for breaks.
    • Attend school meetings prepared. Bring a written list of your child’s current skills, challenges, and what works at home. Teachers implement what they understand.

    Managing Behavioural Challenges – A Parent’s Crisis Toolkit

    Managing Behavioural Challenges - A Parent's Crisis Toolkit

    Every parent of an autistic child has been there: a public meltdown in a crowded market, a two-hour refusal to get dressed, a head-banging episode that leaves you shaking. These moments are not failures of parenting. They are communication – your child’s nervous system telling you it is overwhelmed.

    Understanding the Triggers Behind Meltdowns

    The first step in managing an autistic child meltdown is understanding what it actually is – and what it isn’t.

    A meltdown is not a tantrum. This distinction matters enormously.

    MeltdownTantrum
    CauseNeurological overload – sensory, emotional, or cognitiveGoal-directed – to get something or avoid something
    ControlThe child has little to no controlThe child has some control and adjusts based on audience
    ResolutionNeeds time, space, and calm – cannot be reasoned with mid-episodeCan be resolved by giving in, ignoring, or redirecting
    AfterChild is often exhausted, confused, or distressedChild typically recovers quickly

    Common triggers for meltdowns include:

    • Sensory overload: Loud noise, bright lights, strong smells, uncomfortable clothing, crowded spaces
    • Routine disruption: An unexpected change in schedule, a different route home, a substitute teacher
    • Communication frustration: Not being understood, not being able to express a need
    • Transition stress: Moving from a preferred activity to a non-preferred one
    • Fatigue or hunger: Basic physiological needs that are harder for some autistic children to self-identify and communicate

    Keep a trigger diary. For two weeks, note the time, location, what happened just before, and what the meltdown looked like. Patterns emerge. Patterns can be prevented.

    De-escalation Techniques That Work

    When a meltdown is building – you’ll learn to recognise the early signs (increased stimming, withdrawal, covering ears, repetitive questioning) – act immediately. The window for prevention is short.

    The 3-Step De-escalation Framework:

    Step 1: Reduce the load. Remove or reduce the trigger if possible. Turn off the TV. Move to a quieter space. Loosen tight clothing. Don’t add more words – every instruction is additional sensory input. Silence is your first tool.

    Step 2: Stay regulated yourself. Your child’s nervous system co-regulates with yours. If you are panicking, they escalate. Slow your breathing deliberately. Lower your voice to just above a whisper. Crouch to their level. Your calm is contagious – and so is your anxiety.

    Step 3: Offer comfort, not correction. During a meltdown, your child cannot learn, reason, or respond to instructions. Don’t try to teach. Don’t threaten consequences. Offer a comfort item, a weighted blanket, or simply your quiet presence nearby. Wait. Recovery takes as long as it takes – typically 20 to 45 minutes for a full meltdown.

    After the meltdown: Once your child is calm and regulated – not immediately after – you can gently explore what happened. Use pictures or simple language. This is when learning is possible.

    When to Seek Professional Help

    Most behavioural challenges can be managed with the strategies above. But some situations require professional support:

    • Self-injurious behaviour (head-banging, biting self, scratching) that causes physical harm
    • Aggression toward others that cannot be safely managed
    • Behaviours that are escalating in frequency or intensity despite consistent intervention
    • Sleep disturbances that are severely impacting the whole family
    • Your own mental health is suffering to the point where you cannot function

    In these situations, a Board Certified Behaviour Analyst (BCBA) or a clinical psychologist with autism specialisation can conduct a Functional Behaviour Assessment (FBA) – identifying exactly why a behaviour is occurring – and design a targeted intervention plan. Don’t wait until crisis point. Early professional support for behavioural challenges is far more effective than crisis management.

    Planning for Life Transitions – From Early Childhood to Adulthood

    Planning for Life Transitions - From Early Childhood to Adulthood

    Autism is a lifelong condition. The role of parents in autism doesn’t end when a child turns 18 – it evolves. Planning for each life stage proactively, rather than reactively, makes an enormous difference to outcomes.

    Early Childhood (0–6): The Window of Opportunity

    The first six years of life are a period of extraordinary neuroplasticity. The brain is more malleable, more responsive to intervention, and more capable of forming new connections during this window than at any other time.

    This is why Early Intervention for Autism is not a recommendation – it is an urgency.

    What to prioritise in the 0–6 window:

    • Diagnosis as early as possible: Autism can be reliably diagnosed from 18 months. If you have concerns, don’t wait for your child to “grow out of it.” Seek a developmental paediatrician or child psychiatrist immediately.
    • Start therapy within weeks of diagnosis: Speech therapy, occupational therapy, and behavioural intervention should begin as soon as possible. Waiting lists are real – get on them early.
    • Enrol in a structured early intervention programme: Look for programmes that involve parents actively, not just the child.
    • Focus on communication above everything else: Whether verbal or AAC-based, giving your child a reliable way to communicate is the single most important thing you can do in these years.
    • Build your own knowledge: Attend every parent training session your therapy centre offers. The more you understand, the more effective your home practice becomes.

    School Years (6–18): Building Independence and Social Skills

    The school years are about two things: academic access and social participation. Neither happens automatically for autistic children – both require active parent involvement.

    Academic access:

    • Use your RPWD Act 2016 rights to ensure your child has the accommodations they need (see the advocacy section above).
    • Stay in regular contact with teachers – not just at parent-teacher meetings, but through a communication diary that travels between home and school daily.
    • If mainstream school is not working despite accommodations, explore special schools or hybrid models. There is no shame in choosing the environment where your child actually thrives.

    Social skills:

    • Social skills don’t develop through osmosis for most autistic children. They need explicit teaching – naming emotions, practising conversations, role-playing social scenarios.
    • Structured social skills groups (run by psychologists or special educators) are more effective than unstructured playdates for building specific skills.
    • Identify your child’s interests and use them as social bridges. A child passionate about trains will connect more easily with other train enthusiasts than in a generic social situation.

    Independence:

    • Every year, add one new self-care or life skill to your child’s repertoire. By 18, the goal is that your child can manage as many daily tasks as possible independently.
    • Use task analysis (breaking a skill into tiny steps) and visual supports consistently.
    • Resist the urge to do things for your child that they can do themselves, even if it’s slower or messier.

    The Transition to Adulthood: Vocational Training and Residential Care in India

    The transition to adulthood is the point where most Indian families feel the ground disappear beneath them. School ends. Therapy centres have age limits. Society has no clear place for autistic adults. And parents – who have given everything – are getting older.

    This is not a reason for despair. It is a reason to plan early.

    Vocational training for autistic adults in India is a growing field. Many autistic adults, with the right support and training, can work in structured environments – data entry, packaging, food preparation, horticulture, craft production, and more. The key is matching the individual’s strengths and sensory profile to the right role, and providing job coaching support during the transition.

    India Autism Center’s vocational training program is designed specifically for this transition – building work-readiness skills, social communication in professional settings, and the stamina and routine management that employment requires.

    For families considering residential care:

    As parents age, the question of “what happens when we’re no longer here?” becomes unavoidable. Autism residential care India options are limited but growing. A good residential facility for autistic adults is not an institution – it is a supported living community where individuals have privacy, agency, meaningful daily activity, and professional care.

    India Autism Center’s residential facility offers exactly this: a full-time, supported, and safe residential ecosystem with family housing and daytime support facilities. It is designed so that families can remain involved while knowing their adult child is safe, stimulated, and cared for by trained professionals.

    The earlier you begin planning for this transition – ideally when your child is in their early teens – the more options you have and the smoother the transition will be.

    Conclusion

    The role of parents in managing an autistic child cannot be overstated. From early intervention to advocating for their child’s needs, parents are the driving force behind their child’s growth and development. 

    At India Autism Center, we acknowledge and celebrate parents’ dedication on this journey. By offering resources, education, and a supportive community, we aim to empower parents to provide the best possible care for their autistic children, ensuring a brighter future for both the child and their family.

    Some of our crucial initiatives for helping autistic individuals include:

    • Offering a full-time supported and safe residential ecosystem 
    • Family housing and daytime support facilities
    • A fully equipped and scalable digital platform enabling enhanced speed of service and product delivery
    • Imparting autism management training to create a global, accessible, and scalable workforce of professionals

    Frequently Asked Questions(FAQs)

    What is the role of parents in managing an autistic child?

    The role of parents in managing an autistic child includes providing emotional support, maintaining daily routines, encouraging communication, and collaborating with therapists and educators. Parents help create a safe, structured environment that supports learning, behavior, and overall autism management.

    How can parents handle an autistic child at home?

    To handle an autistic child at home, parents should follow consistent routines, use clear and simple language, offer visual cues, and practice positive reinforcement. Understanding sensory sensitivities and responding calmly to challenging behaviors also plays a key role.

    What are the best tips for parenting a child with autism?

    Some effective tips for parenting a child with autism include being patient, focusing on strengths, using visual schedules, celebrating small achievements, and maintaining open communication. Seeking professional guidance and parent support groups also helps in long-term autism management.

    What should parents avoid when raising an autistic child?

    Parents should avoid sudden changes in routine, harsh discipline, comparisons with other children, and ignoring sensory or emotional needs. Understanding what not to do as a parent of an autistic child helps reduce anxiety and builds trust and emotional security.

    How does parenting an autistic child help in autism management?

    Parenting an autistic child plays a crucial role in autism management by reinforcing therapy goals at home, supporting emotional regulation, and helping the child develop daily living and social skills through consistent care and guidance.

    Can parents support an autistic child without professional therapy?

    Parents can support their autistic child through structured routines, communication strategies, and home-based activities. However, professional therapies and guidance from specialised autism centres significantly enhance outcomes and provide parents with the right tools and direction.

    Disclaimer: This article is intended for educational and informational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. If you are pregnant or have concerns about medication use during pregnancy, please consult a qualified healthcare provider. If your child has received an autism diagnosis and you have questions about causes or support, please reach out to a trained specialist or an autism-focused organisation for guidance.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

    Useful Sources

  • Coping with an Autism Diagnosis: Your Guide to What Comes Next

    Coping with an Autism Diagnosis: Your Guide to What Comes Next

    Coping with autism can feel like a sudden shift in gravity. Relief and grief, clarity and confusion, all crowd in at once. There is the label (with that comes the stigma), the paperwork, and the inevitable questions.

    And then the quiet pause of “Now what?”

    Long before that moment, though, many live through a drawn-out pre-diagnosis phase. Includes studying, noting patterns, and preparing questions for the consultant. These steps, modest as they seem, help steady the ground and make the conversation ahead more coherent.

    Our guide on coping with autism diagnosis is meant as a compass through both stages—the groundwork before diagnosis and the path that unfolds after. Up next, we’ll break down what the diagnosis truly means and how to cope with autism in daily life.

    Read on.

    Coping with Autism Diagnosis: What It Means

    Coping with Autism Diagnosis

    You’ve heard the word. You’ve sat through the explanation.

    Now you’re holding a diagnosis that’s supposed to help, but doesn’t quite tell you how. Even with a name, coping with autism spectrum disorder is rarely straightforward – it often opens a new set of questions you didn’t know you’d be asking.

    Pam Aculey, parent of a child on the spectrum, says, “Receiving our son’s autism diagnosis was a life-changing moment. Whilst it provided us with an explanation… it also instilled panic, confusion and uncertainty for the road ahead.”

    That mix of clarity and overwhelm is something many families feel in the days that follow. Understanding the different diagnostic labels is the first step in finding autism coping skills that actually fit.

    Your child meets the criteria for Autism Spectrum Disorder Level 2

    child meets the criteria for Autism Spectrum Disorder Level 2

    This statement reflects the current diagnostic model under the DSM-5, where autism is recognized as a spectrum rather than distinct subtypes like Asperger’s or PDD-NOS.

    Level 2 suggests substantial support needs, especially in areas like social interaction, communication, behavioral flexibility, and sensory regulation.

    You may notice:

    • Frequent meltdowns when routines change
    • Limited back-and-forth interaction
    • Delayed speech or unusual language patterns
    • High sensitivity to noise, touch, or crowds

    What this might mean:

    • Referrals for speech therapy, occupational therapy, and behaviour-based interventions
    • Likely need for a special educator or shadow teacher in inclusive settings
    • Monthly therapy expenses in private setups can run ₹15,000–₹30,000+
    • Eligible for disability certification under the RPwD Act, which can support access to schools, concessions, and future government schemes

    Often, children at this level may also be evaluated for co-occurring conditions like ADHD, sensory processing difficulties, or speech apraxia. Each of these can shape therapy goals and timelines. Families often ask how to cope with autism when support needs are substantial. At this level, coping strategies for autism usually include speech therapy, occupational therapy, structured routines, and professional guidance.

    Traits consistent with autism, Level 1

    Level 1 autism indicates milder but still impactful support needs. Individuals may have fluent language and average cognitive abilities, but experience difficulty with social nuance, rigidity, anxiety, or sensory overload. These are often internal struggles that others don’t easily see.

    This is where high functioning autism coping strategies often come into play – building social confidence, coaching for executive skills, and offering tailored counseling.

    What this might mean:

    • May go unnoticed in school unless academic or emotional challenges appear
    • Needs may include counseling, executive function coaching, or group therapy
    • Girls and verbally articulate children may mask symptoms, leading to delayed or missed diagnosis
    • Support may feel optional to others, but burnout and withdrawal are real risks
    • Financially, it often means unstructured, ongoing out-of-pocket expenses for private support with little formal recognition

    Diagnosis at this level may be made later in life, especially in women, nonbinary individuals, or those misdiagnosed with anxiety, OCD, or depression. For adults, it can feel like both clarity and reckoning.

    📥 Free download: Printable daily routine chart for autistic children

    ADHD and autistic features are both present

    This is a dual diagnosis that’s becoming more widely recognized. ADHD and autism often overlap, with each condition amplifying the other’s challenges. A child might struggle to sit still and also resist transitions. An adult might be impulsive, yet hyper-focused and anxious in new social situations.

    What this might mean:

    • Need for a combined intervention plan: behavioral therapy, sensory tools, and classroom strategies
    • In some cases, medication may be advised to manage inattention or hyperactivity
    • School systems may struggle to support both diagnoses simultaneously
    • Costs can quickly add up—between therapy, psychiatric consults, and parental guidance
    • Most insurance plans don’t fully cover these needs in India

    Clinicians often highlight this combination to explain why a child doesn’t respond to a single therapy style—or why social skills improve, but regulation doesn’t.

    Parents may need to explore combined coping mechanisms for autism and ADHD, including behavioral therapy and school accommodations.

    Social Pragmatic Communication Disorder fits better

    This diagnosis is given when social interaction is affected—like difficulty understanding tone, taking turns in conversation, or interpreting gestures—but without the repetitive behaviors or sensory differences seen in autism.

    It’s considered distinct from ASD, but support is still essential. What this might mean:

    1. May be referred to speech-language therapy focused on social communication
    2. Often excluded from autism-specific school accommodations and benefits
    3. Teachers may misread challenges as immaturity or rudeness

    Parents sometimes ask how they’re supposed to hold it all together. The answer isn’t about perfection so much as steadiness.

    Puja Dutta, RCI-registered Clinical Psychologist at India Autism Center

    Long-term support is still needed, but legal protections and public funding are limited. This diagnosis can feel ambiguous for parents, but the key is not waiting. Social communication skills can improve dramatically with early, targeted support.

    Even without a full autism diagnosis, families benefit from autism coping skills for adults and children alike – skills like emotional regulation, communication strategies, and sensory support.

    Developmental delay with autistic features; we’ll reassess

    Used for children under 5 when delays are observed across areas—like speech, motor skills, or play—but a full autism diagnosis is not yet confirmed. It’s a watch-and-intervene approach.

    This overlaps with Global Developmental Delay (GDD), a term that gives space to monitor evolving needs.

    What this might mean:

    • Begin early intervention immediately: speech, OT, special education
    • Track milestones closely, with reassessments every 6–12 months
    • May receive temporary disability certification to access early support
    • Therapy costs are often high upfront, with limited public provision
    • Diagnosis may later evolve into ASD, ID, or a learning disability, depending on the child’s developmental path

    Early intervention here focuses less on labels and more on developing autism coping skills – speech, play-based learning, and structured support routines.

    So, now that you’ve unpacked the language, let’s move toward what to actually do with it.   Next up: building a plan, finding the right support, and making this diagnosis work for you.

    Personalizing Support: What to Focus on, What to Let Go

    Personalizing Support

    Parents of autistic children are often handed a flood of advice. New therapies, new strategies, new “essentials.” What gets lost in that rush is a quieter truth: not every approach matters equally. What matters most is finding coping strategies for autism that fit the child in front of you.

    Support becomes clearer when you slow down long enough to notice. Which moments seem to calm? What sparks tension? Which gestures or sounds carry meaning? A pattern begins to reveal itself, and with it, the outline of a plan.

    Seen this way, the next steps become clear.

    Decode Sensory Clues Before Labeling Behavior

    A child covering their ears in a crowded room is not being difficult; they are signaling distress. A refusal to wear a certain shirt may point less to stubbornness than to the irritation of a seam. Behavior, in this sense, is language—sometimes subtle, often urgent.

    Check these common sensory signals found in autism and ways to respond:

    If You Notice ThisIt May ReflectYou Can Try
    Hands clamped over earsAuditory sensitivityNoise-canceling headphones, quiet breaks
    Refusal of clothes/shoesTactile discomfortSofter fabrics, tagless clothing
    Chewing on sleeves or pencilsOral sensory-seekingChewelry, crunchy snacks
    Pacing, spinning, or jumpingNeed for movementSwings, trampolines, and climbing breaks
    Withdrawal in bright roomsVisual overloadDim lighting, sunglasses

    When interpreted this way, behavior shifts from being a problem to be managed to a clue about how the world is being experienced.

    This forms part of everyday coping mechanisms for autism, helping children regulate without escalating stress.

    Use Routine to Create Safety, Not Rigidity

    Routines are often described as restrictive, but for many autistic children, they serve as anchors. Predictability eases anxiety, creates a sense of safety, and makes daily life less chaotic. The goal is not rigid adherence to schedules but a rhythm steady enough to provide reassurance.

    Ways routines can ease daily life:

    GoalTool That Helps
    Calmer morningsPicture strip by the mirror
    Smoother bedtimesDimmer switch + checklist
    Easier transitionsCountdown timer + verbal cue
    Less chaotic weekends“Today’s Plan” fridge chart

    Sometimes the most effective support is not a full overhaul but a small, consistent addition that lowers stress.

    For many families learning how to live with autism, routines become a key autism coping skill that provides both safety and flexibility.

    Expand Communication Beyond Speech

    Spoken words often arrive unevenly, or not at all. Yet communication rarely disappears. It shows up in gestures, repeated phrases, the rhythm of movement, or with the help of assistive devices. To recognize those signals is to widen the frame of what language looks like.

    Ways to make communication more accessible:

    • Offer clear picture choices instead of open-ended questions
    • Treat repeated scripts as openings, not interruptions
    • Allow extra pauses before stepping in
    • Keep AAC tools close during everyday routines

    By shifting attention from what is absent to what is present, communication begins to feel broader, more possible.

    Communication supports are essential coping skills for autism spectrum disorder, especially when speech is delayed or absent.

    Teach Regulation Before the Storm

    Meltdowns rarely arrive without warning. They build gradually—restlessness, escalating scripts, withdrawal. These are not minor inconveniences but early signals that the child is nearing a breaking point. Intervening before escalation often means the difference between a spiral and a moment of calm.

    Here are some early clues and supports that prove useful:

    Early ClueHelpful Support
    Pacing or restless handsFidget tools, deep pressure
    Escalating scriptsCalm break, quiet corner
    Covering ears or eyesHeadphones, dim lights
    Repeated questionsVisual schedule, consistent reply

    Calm practices introduced early and often, not in the midst of a crisis, are the ones most likely to take hold. These proactive methods are some of the most reliable autism coping skills for adults and children.

    Start With Strengths, Not Deficits

    The impulse to focus on delays is strong, but strengths are often the more reliable path forward. A child’s fascinations, talents, or even quirks can become tools for learning and connection. What lights them up can also guide them toward growth.

    Transform strengths into supports:

    StrengthHow to Build On It
    Fascination with trainsCounting, turn-taking, sequencing
    Love of drawingSelf-made visual schedules
    Strong memory for patternsAnchoring routines and rules
    Mimicry of soundsSocial scripts and play
    Passion for animalsResponsibility and empathy-building

    When growth is anchored in strength, progress often feels less like correction and more like expansion. This strength-based model not only builds skills but also teaches coping strategies for autism by creating positive learning anchors.

    Support, then, is not about adding more. It is about finding the shape that matches a child’s needs and leaning into it. Observed closely, the outline is already there.

    Use Cognitive Training to Strengthen Core Skills

    In India, cognitive training is slowly gaining traction as an essential part of intervention for children with developmental differences. Unlike therapies that target specific behaviors, cognitive training strengthens the “thinking skills” beneath them with flexibility, self-regulation, multitasking, working memory, and problem-solving. These are the foundations that help a child adapt in the classroom, manage frustration, and carry new learning into daily life.

    Why it matters: Without these skills, even strong abilities, like language or memory, may not translate into independence. A child who can memorize facts may still struggle to shift when plans change; one who speaks fluently may still be derailed by poor regulation. Cognitive training fills these gaps by teaching children how to manage information, not just absorb it.

    For many, especially when coping with ASD as an adult, cognitive training becomes a crucial tool for independence and daily functioning.

    What it looks like:

    1. Memory and sequencing games to strengthen working memory
    2. Structured play that encourages flexible thinking
    3. Daily activities that demand planning and self-monitoring

    Talking to Siblings About Autism

    Talking to Siblings About Autism

    When a child receives an autism diagnosis, the conversation that often gets postponed the longest is the one with the other children in the family. It feels complicated. You’re still processing it yourself. You don’t want to say the wrong thing.

    But siblings notice. They notice the extra appointments, the changed routines, the meltdowns they don’t quite understand. Silence doesn’t protect them – it just leaves them to fill the gap with their own explanations, which are rarely accurate and often unkind to themselves.

    The good news: you don’t need a perfect script. You need an honest, age-appropriate conversation that you’re willing to return to.

    What to Say at Each Age

    Ages 3–5 (keep it concrete and brief): “Your brother’s brain works a little differently. Loud places feel very big to him, so sometimes he needs quiet. That’s not your fault, and it doesn’t mean he loves you less.”

    Ages 6–10 (add a little more detail): “Autism means some parts of the brain develop differently. It can make talking, or being in noisy places, or changes in plans feel really hard. That’s why she has therapy – to help her with those things. She’s really good at other things too, like [specific strength].”

    Teenagers (be direct and specific): Teens can handle the full picture. Talk about what autism means, how it affects daily life, what the therapy goals are, and – importantly – what you expect from them as a sibling. Acknowledge that it’s sometimes unfair. Don’t pretend otherwise.

    Reassurance That Every Sibling Needs to Hear

    • “Nothing you did caused this.”
    • “Autism is not contagious.”
    • “You are allowed to feel frustrated sometimes. That’s normal.”
    • “You will still get your time, your attention, your space.”

    Involving Siblings Without Burdening Them

    There’s a meaningful difference between including a sibling and making them a caregiver. Invite them to join a therapy activity once in a while – not to help, but to understand. Let them see what their brother or sister is working on. Celebrate shared wins.

    At the same time, protect their childhood. A sibling should not be managing meltdowns, explaining autism to classmates on behalf of the family, or feeling responsible for their brother’s or sister’s wellbeing. That weight belongs with the adults.

    Watch for signs of resentment or withdrawal – a sibling who goes very quiet, who stops inviting friends home, or who starts acting out at school may be carrying more than they’re saying. A few sessions with a counselor, just for them, can make a real difference.

    Navigating Parental Guilt After an Autism Diagnosis

    Navigating Parental Guilt After an Autism Diagnosis

    Let’s say it plainly: the guilt is real, it’s common, and it makes complete sense.

    Almost every parent we work with at India Autism Center describes some version of it. Did I miss the signs too early? Was it something I did during pregnancy? Did I wait too long to get help? The mind goes back and forth, looking for a cause, looking for something to hold responsible. And it lands on you.

    Research published in the Journal of Autism and Developmental Disorders confirms what clinicians see every day: parental guilt after diagnosis is one of the most consistent emotional responses, particularly in mothers, and it’s tied not to actual wrongdoing but to the shock of reinterpreting a child’s history through a new lens.

    Here’s what we want you to hear clearly: you did not cause your child’s autism.

    Autism has a strong genetic basis. It is not caused by parenting style, diet, screen time, vaccines, or anything you did or didn’t do. The guilt you feel is a measure of how deeply you love your child – not evidence of failure.

    Reframing the Guilt: Four Mindset Shifts

    1. “I missed the signs” → “I noticed something was different and I kept looking.” Most parents who reach a diagnosis did so because they kept pushing, kept asking, kept advocating. That persistence is not a failure. It’s the reason your child has a diagnosis at all.

    2. “I should have acted sooner” → “I acted when I had the information I needed.” Autism diagnosis in India is still delayed for many families – the average age of diagnosis remains above 4 years in most studies. The system is not built for early detection. You were navigating that system. Give yourself credit for getting here.

    3. “I’m not doing enough” → “I’m learning what ‘enough’ looks like for my child.” There is no universal checklist for autism parenting. What works for one child may not work for another. You are figuring out your child specifically. That takes time, and it’s not a deficit.

    4. “I feel guilty, so something must be wrong” → “Guilt is a feeling, not a verdict.” Feelings are real. They are not always accurate. Guilt in this context is a grief response – it’s part of how parents process a major life shift. It deserves compassion, not more self-punishment.

    When Guilt Becomes Something More

    If the guilt is persistent, if it’s interfering with your ability to be present with your child, or if it’s tipping into depression or anxiety – please reach out to a mental health professional. Parent wellbeing is not a luxury. It is part of your child’s support system.

    You cannot pour from an empty cup. And your child needs you steady, not perfect.

    India-Specific Support: Government Schemes & Resources

    India-Specific Support: Government Schemes & Resources

    One of the most practical things you can do right after an autism diagnosis in India is to understand what the government has already put in place for your family. Most parents don’t know these schemes exist. Many who do know struggle to navigate them. Here is a clear, actionable breakdown.

    Step 1: Get the Disability Certificate (UDID Card)

    This is the foundation of everything else. Without a disability certificate, your child cannot access most government schemes, school accommodations, or financial benefits.

    The process:

    • Get a written diagnostic report from a qualified specialist (developmental paediatrician, child psychiatrist, or neurologist)
    • Visit your nearest government hospital and request an assessment by the Disability Assessment Board
    • The board uses the Indian Scale for Assessment of Autism (ISAA) to determine the disability percentage
    • Submit your application with: diagnostic report, identity proof, address proof, birth certificate, and passport-size photographs
    • The certificate should be issued within 30 days of application

    The disability percentage matters: 40%+ qualifies for most benefits; 80%+ opens additional entitlements. Apply through your district DDRC (District Disability Rehabilitation Centre) or the UDID portal.

    Legal basis: The Rights of Persons with Disabilities (RPwD) Act, 2016 explicitly includes autism as a specified disability. This law mandates equal opportunity, reasonable accommodation in schools and workplaces, and access to government schemes.

    Step 2: Access Inclusive Education via Samagra Shiksha Abhiyan (SSA)

    If your child is school-age, Samagra Shiksha Abhiyan is the central government scheme that funds inclusive education in government and government-aided schools across India.

    What SSA provides for children with autism:

    • Identification and assessment support
    • Special educators and resource teachers in schools
    • Aids and assistive devices
    • Therapeutic services (speech, OT) through Block Resource Centres
    • Teacher sensitization and training
    • Barrier-free school infrastructure

    To access SSA support, approach your child’s school principal or the Block Resource Centre in your district. The school should coordinate with the state SSA office to arrange a special educator or resource support.

    Step 3: Register with the National Trust

    The National Trust is a statutory body under the Ministry of Social Justice and Empowerment that runs three schemes directly relevant to autism:

    SchemeWhat It CoversWho It’s For
    NiramayaHealth insurance up to ₹1 lakh/year – OPD, diagnostics, therapies, corrective surgeries, transportAll ages, no age bar
    VikaasDay care, interpersonal skills, and vocational trainingPersons with autism aged 10+
    GharaundaLifelong residential care and shelterAdults with autism

    How to apply: Register your child with the National Trust through a Local Level Committee (LLC) in your district. The LLC is usually hosted by a registered NGO. Find your nearest LLC on the National Trust website.

    Note: Niramaya is particularly urgent to apply for early – it covers therapy costs that can otherwise run to ₹15,000–₹30,000 per month in private settings.

    Step 4: Tap Into NIMHANS and NIMH Resources

    • NIMHANS (National Institute of Mental Health and Neuro Sciences), Bengaluru, has a dedicated Child and Adolescent Psychiatry department that offers assessment, therapy, and parent training programs. It is a government institution, which means significantly subsidized costs.
    • NIMH (National Institute for the Mentally Handicapped), now called NIEPID (National Institute for Empowerment of Persons with Intellectual Disabilities), Secunderabad, offers training, rehabilitation, and resource support for families of children with developmental disabilities including autism.

    Both institutions also train professionals and publish resources that can help parents understand autism diagnosis India-specific pathways more clearly.

    Step 5: Connect with State-Level Autism Societies

    Every major Indian state has at least one autism society or parent network that can guide you through local resources, school options, and government scheme applications.

    Key organizations:

    • Action for Autism (AFA) – New Delhi; India’s oldest autism advocacy organization; runs the National Centre for Autism
    • Autism Society of India (ASI) – national body with state chapters
    • Ummeed Child Development Centre – Mumbai; multidisciplinary assessment and therapy
    • The Banyan – Chennai; mental health and disability support
    • AADI (Action for Ability Development and Inclusion) – New Delhi

    These organizations often run helplines, parent support groups, and workshops – many of them free. Connecting with other parents who have navigated the same system is one of the most underrated autism diagnosis next steps you can take.

    Looking Ahead: Financial Foundations for Lifelong Support

    Financial planning becomes essential once an autism diagnosis enters a family’s life. It is the start of a long journey to ensure your child’s needs are met today and protected for tomorrow. A strong financial plan is just as vital as therapies and coping skills for autism. It ensures that support systems continue long-term, especially as children transition into adulthood.

    In India, families can explore government-supported Niramaya Health Insurance, covering hospitalization and therapy, or private options like Star Special Care, which includes medical, therapy, and hospital expenses. Internationally, programs such as UnitedHealthcare Special Needs Plans or AXA disability coverage offer comprehensive long-term support. These plans do more than pay bills. They create a safety net that lets daily life unfold with less uncertainty.

    A thoughtful financial strategy brings calm and confidence. Planning early safeguards not just care, but your child’s dignity and future possibilities. If you’re unsure which options fit best, a consultation with a specialist can help map the path forward.

    Frequently Asked Questions

    What are the first steps after an autism diagnosis in India?

    Start with three things: understand the specific diagnosis and what level of support it implies, apply for the disability certificate (UDID card) under the RPwD Act 2016, and connect with a multidisciplinary therapy team. These autism diagnosis next steps create the foundation for everything that follows.

    How do I cope with an autism diagnosis as a parent?

    Give yourself permission to grieve and to feel overwhelmed – both are normal. Then focus on one step at a time. Connect with other autism parents, seek professional guidance, and remember that how to cope with an autism diagnosis is not a question you have to answer alone. Support groups, parent counseling, and organizations like Action for Autism can help.

    Is autism covered under the RPwD Act 2016?

    Yes. The Rights of Persons with Disabilities Act 2016 explicitly lists autism spectrum disorder as a specified disability. This entitles your child to a disability certificate, school accommodations, government scheme access, and legal protections against discrimination.

    How do I explain autism to my other children?

    Use simple, concrete language matched to their age. For young children: “Your brother’s brain works differently.” For older children: add detail about what autism means in daily life. Reassure them that nothing they did caused it, that autism is not contagious, and that they will still get your time and attention.

    What is the Niramaya scheme and how do I apply?

    Niramaya is a National Trust health insurance scheme that covers up to ₹1 lakh per year for OPD, diagnostics, therapies, and more – with no age bar. Apply through a Local Level Committee (LLC) registered with the National Trust. Find your nearest LLC at nationaltrust.nic.in.

    My child was diagnosed late. Did I fail them?

    No. The average age of autism diagnosis in India remains above 4 years for most children, and many are diagnosed even later. The system is not built for early detection. You got here. That matters. Focus on what you can do now – early intervention at any age produces meaningful outcomes.

    What government schools support for autism is available?

    Under Samagra Shiksha Abhiyan (SSA), government and government-aided schools are required to provide inclusive education support – including special educators, assistive devices, and therapeutic services – for children with autism. Contact your child’s school or the district Block Resource Centre to initiate this.

    Disclaimer: This article is intended for educational and informational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. If you are pregnant or have concerns about medication use during pregnancy, please consult a qualified healthcare provider. If your child has received an autism diagnosis and you have questions about causes or support, please reach out to a trained specialist or an autism-focused organisation for guidance.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

  • Dyslexia Symptoms in Kids: The Subtle Clues Most Parents Miss

    Dyslexia Symptoms in Kids: The Subtle Clues Most Parents Miss

    If your child finds reading, spelling or writing much harder than their classmates despite regular practice, it is natural to wonder whether something more than a learning delay is involved. Dyslexia in children is one of the most common specific learning difficulties, affecting how the brain processes written language. 

    As per reports, around 10% of the population has dyslexia, with approximately 4% experiencing severe dyslexia. Dyslexia is not linked to intelligence, vision or motivation, and with the right support, children can thrive both academically and socially. Recognising dyslexia symptoms in children early allows families to access timely interventions that improve literacy, confidence and overall learning outcomes. 

    This guide explains the early warning signs, age-specific symptoms and practical ways to support children with dyslexia.

    What Does Dyslexia Look Like in Children?

    Children experiencing reading and letter-recognition difficulties associated with dyslexia

    Many parents assume that dyslexia means reading letters backwards, but the reality is far more complex. Dyslexia in children affects how the brain processes language, making it harder to recognise sounds in words, connect letters to those sounds and read fluently. These challenges often become noticeable when children begin school, although subtle signs may appear much earlier.

    A child with dyslexia may be bright, curious and highly creative, yet continue to struggle with reading tasks that seem easy for their peers. They may understand stories when someone reads aloud, but find it difficult to read the same text independently. Similarly, they may have an excellent spoken vocabulary but struggle to express those ideas in writing.

    Dyslexia is one of several learning-related conditions that come under recognised disability categories. You can explore all types of disability to understand how conditions like dyslexia are classified.

    Some common signs that parents and teachers notice include:

    • Reading more slowly than classmates.
    • Difficulty remembering letter sounds.
    • Frequent spelling mistakes, even with familiar words.
    • Trouble sounding out unfamiliar words.
    • Forgetting verbal instructions.
    • Avoiding reading or writing activities.
    • Mixing up words that sound similar.
    • Becoming frustrated with homework involving literacy.

    These signs alone do not confirm dyslexia. However, when several difficulties persist over time despite regular classroom support, it is worth discussing them with your child’s teacher or a qualified professional.

    📥 Free download: Printable daily routine chart for autistic children

    What Is the Meaning of Dyslexia?

    Children reading books with scattered letters, illustrating how dyslexia affects reading, spelling and language processing

    Understanding what dyslexia means can help clear up many common misconceptions.

    The British Dyslexia Association defines dyslexia as a specific learning difficulty that impacts the skills required for accurate and fluent word reading as well as spelling. It often involves difficulties with phonological awareness, verbal memory and processing speed. These challenges exist on a continuum, ranging from mild to more significant.

    Importantly, dyslexia is not caused by poor intelligence, laziness or lack of effort. Many children with dyslexia often have average or above-average intelligence and often demonstrate strengths in creativity, problem-solving, visual thinking and reasoning.

    Dyslexia also affects every child differently. While one child may struggle mainly with reading accuracy, another may find spelling, writing or remembering sequences more challenging. Some children develop coping strategies that hide their difficulties, making identification more difficult until academic demands increase.

    Recognising these individual differences is essential because support should always be tailored to the child’s unique learning profile rather than based solely on a label.

    Early Signs and Symptoms of Dyslexia

    Child surrounded by mixed-up letters, representing early dyslexia signs and phonological processing difficulties

    The early signs and symptoms of dyslexia often appear long before formal reading lessons begin. While not every child showing these behaviours has dyslexia, a combination of persistent difficulties may indicate that further assessment is needed.

    Many early signs involve spoken language rather than reading itself because reading relies on strong language-processing skills.

    Parents may notice that their child:

    • Starts talking later than expected.
    • Has difficulty learning nursery rhymes.
    • Finds it hard to recognise rhyming words.
    • Mixes up similar-sounding words.
    • Has trouble remembering the names of familiar objects.
    • Struggles to learn the alphabet.
    • Finds it difficult to remember sequences, such as days of the week.
    • Needs repeated instructions to complete simple tasks.

    Research has consistently shown that phonological awareness, the ability to recognise and manipulate speech sounds, plays an important role in learning to read. Children with dyslexia often experience difficulties in this area from an early age, even before they enter school.

    It is important to remember that one or two of these signs do not necessarily indicate dyslexia. Many young children develop these skills at different rates. However, when several signs persist for months and begin to affect learning, seeking professional advice can make a meaningful difference.

    Want to know more? Get in touch with us.

    Dyslexia Symptoms in 5-Year-Olds

    Five-year-old child struggling with letters in a book, illustrating early reading and language-processing difficulties

    The first year of formal schooling is when dyslexia symptoms in 5-year-olds often become easier to recognise. At this stage, children are expected to learn letter sounds, begin reading simple books and develop early writing skills. While every child progresses differently, persistent literacy challenges may warrant closer attention.

    Some of the most common dyslexia symptoms in 5-year-olds include difficulty remembering the sounds associated with letters, confusing letters with similar shapes, struggling to blend sounds into simple words and finding it hard to recognise familiar sight words. Many children also experience difficulty remembering sequences such as the alphabet or counting patterns.

    Parents and teachers may also notice behaviours such as:

    • Getting confused with letters like b, d, p and q.
    • Reversing letters beyond what is typically expected for their age.
    • Difficulty identifying the first or last sound in a word.
    • Trouble clapping syllables in simple words.
    • Avoiding activities involving books.
    • Becoming upset or frustrated during reading practice.
    • Difficulty following instructions with two or three steps.

    Letter reversals alone should not be viewed as evidence of dyslexia because they are common during early writing development. Instead, professionals look for a broader pattern of language-processing difficulties alongside reading and spelling challenges.

    Types of Dyslexia Symptoms in Children at Primary School

    Four common dyslexia symptoms in children: reading, spelling, organisation and emotional or behavioural difficulties

    As children move through primary school, reading and writing become central to almost every subject. Lessons shift from “learning to read” to “reading to learn”. This is often when dyslexia symptoms in children become more noticeable, as classroom tasks demand greater reading fluency, accurate spelling and independent writing.

    It is important to remember that dyslexia affects every child differently. Some children may struggle mainly with reading accuracy, while others find writing, organisation or remembering information more challenging. Looking at patterns across different learning activities provides a much clearer picture than focusing on a single difficulty.

    Reading Difficulties

    Reading is one of the areas most commonly affected by dyslexia. Children may know the individual sounds of letters but find it difficult to blend them into words quickly or accurately. As a result, reading can become slow, effortful and tiring.

    Common reading-related dyslexia symptoms in kids include:

    • Reading more slowly than classmates.
    • Guessing unfamiliar words instead of sounding them out.
    • Losing their place while reading.
    • Skipping or adding words when reading aloud.
    • Difficulty recognising common sight words automatically.
    • Reading accurately one day but struggling with the same words the next.
    • Finding it difficult to understand a passage because so much effort is required to decode the words.

    A child may also enjoy listening to stories but avoid reading independently. This difference between listening comprehension and reading ability is often an important clue that should not be overlooked.

    Writing and Spelling Challenges

    Writing requires several skills to work together, including planning ideas, remembering spelling patterns, organising sentences and controlling handwriting. For children with dyslexia, managing all these processes simultaneously can be difficult.

    You may notice that your child:

    • Frequently misspells familiar words.
    • Spells the same word differently within one piece of writing.
    • Leaves out letters or syllables.
    • Uses very simple vocabulary despite having a strong spoken vocabulary.
    • Takes much longer than classmates to complete written work.
    • Has untidy or inconsistent handwriting.
    • Finds copying from the board particularly challenging.

    These difficulties are often mistaken for carelessness. In reality, many children with dyslexia work much harder than their peers to produce a short piece of writing.

    Memory and Organisation Difficulties

    Although dyslexia is primarily associated with literacy, many children also experience challenges with working memory and processing speed. These skills help children remember information while completing a task, follow instructions and organise their work.

    Some symptoms of dyslexia in children include:

    • Forgetting multi-step instructions.
    • Difficulty remembering spellings learned the previous day.
    • Losing track of classroom routines.
    • Struggling to remember sequences such as days of the week or multiplication tables.
    • Misplacing books, homework or stationery.
    • Taking longer to complete classroom tasks.

    Emotional and Behavioural Signs

    Not all dyslexia symptoms in children involve reading or writing. Some children begin to show emotional or behavioural changes as they become aware that learning feels more difficult for them.

    Parents and teachers may observe that a child:

    • Avoids reading aloud in class.
    • Says they “hate reading” or “can’t do it”.
    • Appears anxious before literacy lessons.
    • Becomes frustrated with homework.
    • Gives up quickly when faced with reading tasks.
    • Seems unusually tired after school.
    • Shows declining confidence despite trying hard.

    These behaviours are not signs of laziness. They often reflect repeated experiences of finding classroom activities more demanding than expected. Providing encouragement and recognising effort can make a significant difference to a child’s confidence.

    Why Early Recognition Matters?

    Child speaking with a specialist and reading independently, showing the benefits of early dyslexia recognition

    Recognising the symptoms of dyslexia in children early allows families to access interventions before reading difficulties begin to affect confidence and emotional wellbeing.

    Children who repeatedly experience failure in literacy tasks may come to believe they are less capable than their peers. Over time, this can reduce motivation, increase anxiety around school and make learning even more challenging.

    The encouraging news is that dyslexia can be effectively supported through evidence-based teaching approaches. Early intervention helps children build essential literacy skills while reinforcing their confidence and willingness to learn.

    When Should Parents Seek an Assessment?

    Professional reviewing dyslexia assessment records for a child with persistent literacy difficulties

    Many young children occasionally reverse letters, forget spellings or need extra help with reading. These behaviours are a normal part of learning. However, if difficulties continue over several months despite consistent teaching, it is worth seeking professional advice.

    Consider discussing your concerns with your child’s teacher if your child:

    • Continues struggling with reading despite regular practice.
    • Finds spelling significantly harder than classmates.
    • Avoids reading or writing whenever possible.
    • Shows several of the early signs and symptoms of dyslexia.
    • Appears increasingly frustrated or anxious about schoolwork.

    A comprehensive assessment may involve an educational psychologist or another qualified specialist who evaluates reading accuracy, spelling, language processing, memory and other cognitive skills. The goal is not simply to provide a label but to understand how your child learns best and identify the support they need.

    Early identification is associated with better educational outcomes because interventions can begin before literacy gaps widen.

    How to Teach a Child with Dyslexia?

    Teacher using structured multisensory phonics activities to help children with dyslexia develop literacy skills

    Parents often ask how to teach a child with dyslexia at home. While every child has unique learning needs, research consistently supports structured, explicit and multisensory teaching approaches.

    The aim is not simply to help children memorise words but to build a strong understanding of how spoken sounds connect to written language.

    Some practical strategies include:

    • Break reading tasks into short, manageable sessions.
    • Teach letter sounds systematically rather than relying on memorisation.
    • Use multisensory activities such as tracing letters in sand, using magnetic letters or writing with finger paints.
    • Read aloud together every day, even if your child cannot yet read independently.
    • Encourage audiobooks alongside printed books to build vocabulary and comprehension.
    • Give one instruction at a time and check understanding.
    • Celebrate effort and progress rather than focusing only on correct answers.
    • Allow additional time for homework and reading activities.

    Many parents also search online for dyslexia reading answers, hoping to find a single solution. In reality, there is no universal programme that works for every child. Effective support combines evidence-based teaching, patience, regular practice and encouragement tailored to the child’s individual strengths and challenges.

    Several research studies emphasise that structured literacy approaches, particularly those focusing on phonics, phonological awareness and decoding skills, provide the strongest evidence for improving reading outcomes in children with dyslexia.

    Want to know more? Get in touch with us.

    Supporting Children with Learning Differences at India Autism Center

    Therapist providing personalised play-based learning support to a child at India Autism Centre

    Every child deserves the opportunity to learn in a way that builds on their strengths. While dyslexia in children is a specific learning difficulty and not a form of autism, some children may experience co-occurring developmental or learning differences that require a multidisciplinary approach. 

    Early identification and personalised support can help children develop literacy skills, improve confidence and participate more fully at school and at home.

    At India Autism Center, families have access to evidence-based services that support children’s overall development. Depending on a child’s individual needs, this may include developmental assessments, early intervention programmes, speech and language therapy, occupational therapy, special education and parent guidance. 

    By working closely with families, educators and therapists, the centre aims to create personalised learning pathways that help every child reach their full potential.

    Conclusion

    Family consulting a specialist and teacher supporting children through early dyslexia recognition and personalised learning

    Recognising dyslexia in children early can make a lasting difference to their learning journey and overall wellbeing. While every child develops at their own pace, persistent reading, spelling and language difficulties deserve timely attention. 

    With the right support, structured teaching and encouragement, children with dyslexia can build strong literacy skills and thrive both academically and personally. Seeking professional guidance early empowers families to address challenges effectively, helping children gain the confidence, resilience and skills they need to reach their full potential.

    Frequently Asked Questions

    At what age can dyslexia in children be identified?

    Some early signs of dyslexia in children may appear as young as 4 or 5 years old, particularly when a child struggles with rhyming, letter recognition or learning sounds. However, a comprehensive assessment is usually more reliable once formal reading instruction has begun.

    Are letter reversals a definite sign of dyslexia?

    No. Reversing letters such as b and d is common during early writing development. It becomes a concern only when it persists alongside other dyslexia symptoms in children, such as poor phonological awareness and ongoing reading difficulties.

    Can bilingual children develop dyslexia?

    Yes. Dyslexia can occur in children who speak one language or multiple languages. Difficulties with reading and spelling may appear in each language, although the way they present can vary depending on the language’s writing system.

    Is dyslexia hereditary?

    Research suggests that genetics plays an important role in dyslexia. Children with a parent or sibling who has dyslexia are more likely to develop similar reading and language-processing difficulties than children without a family history.

    Can children with dyslexia become fluent readers?

    Yes. With evidence-based teaching approaches, regular practice and personalised support, many children with dyslexia develop significantly stronger reading skills and become confident learners. However, they may continue using different learning strategies.

    Disclaimer: This article is intended for educational and informational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. If you are pregnant or have concerns about medication use during pregnancy, please consult a qualified healthcare provider. If your child has received an autism diagnosis and you have questions about causes or support, please reach out to a trained specialist or an autism-focused organisation for guidance.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.