Category: Understanding Autism

  • 2026 Study | Young Women with ADHD Are at Higher Risk of Serious Health Problems

    2026 Study | Young Women with ADHD Are at Higher Risk of Serious Health Problems

    A recent study on Attention-Deficit/Hyperactivity Disorder (ADHD) in young women reveals that girls diagnosed with ADHD in childhood are significantly more likely to develop multiple serious health conditions as young adults. A landmark 2026 study published in Nature Mental Health found that when childhood poverty is also present, the risk compounds dramatically — with nearly 39% of the health burden driven by the interaction between ADHD and deprivation alone.

    This isn’t a minor footnote in ADHD research. It’s a wake-up call.

    What Did The 2026 Study On ADHD And Women’s Health Actually Find?

    What Did the 2026 Study on ADHD and Women's Health Actually Find?

    The study — Wilson et al. (2026), published in Nature Mental Health — followed a large population-based cohort of females born in Wales between 1991 and 1998. Researchers tracked their health records from childhood through early adulthood (ages 18–32) using linked primary and secondary care data.

    Three major findings came out of it:

    • Girls with childhood ADHD had a significantly higher risk of adult multimorbidity — 2.38 times higher than matched controls, even after accounting for other factors.
    • When childhood poverty was also present, that risk jumped to 3.91 times — far higher than either risk factor alone.
    • The most severe health cluster, seen predominantly in the ADHD group, was marked by a high burden of psychiatric conditions including PTSD and borderline personality disorder.

    Multimorbidity means having two or more long-term health conditions at the same time. This isn’t just about mental health. It spans respiratory, metabolic, gastrointestinal, autoimmune, and psychiatric conditions — all co-occurring in young women who were diagnosed with ADHD as children.

    Want to know more? Get in touch with us.

    Why Are Girls With ADHD Still Being Missed?

    Why Are Girls with ADHD Still Being Missed?

    This is the question that underpins everything else.

    ADHD was historically considered a condition that mostly affected hyperactive boys. That framing shaped the diagnostic criteria, the research, and the clinical instincts of generations of healthcare providers.

    Girls don’t usually present the same way.

    How ADHD typically looks in girls:

    Trait in Boys (more commonly recognised)Trait in Girls (more commonly missed)
    Hyperactivity, fidgeting, running aroundDaydreaming, appearing “spacey”
    Impulsivity, blurting out answersEmotional dysregulation, crying easily
    Disruptive classroom behaviourQuiet, inattentive, “tries hard but scattered”
    Externally visible struggleInternalised anxiety and self-criticism

    Girls tend to mask — consciously or unconsciously hiding their symptoms to fit social expectations. From a young age, girls are socialised to be well-behaved, attentive, and composed. So many girls with ADHD sit quietly in class with their minds racing, spending enormous energy keeping up appearances.

    By the time they’re adults, masking has become a way of life. They stay late at work to compensate for lost focus. They tell themselves they’re just anxious, just not smart enough, just lazy.

    They’re not. They were missed.

    Research confirms that diagnostic rates are higher among boys than girls at a 2:1 ratio in childhood — and experts believe this gap reflects systemic underdiagnosis of females, not a genuine male predisposition to ADHD.

    There’s more to it; read: Why Are Fewer Girls Diagnosed with Autism?

    What Long-Term Health Conditions Are These Women Developing?
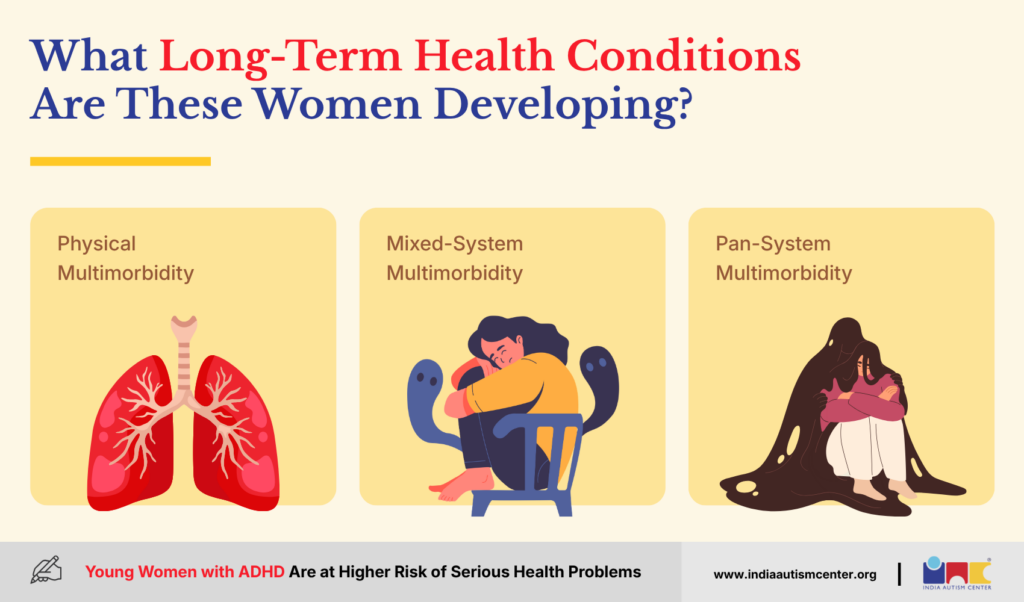
    What Long-Term Health Conditions Are These Women Developing?

    The 2026 study identified three distinct clusters of health conditions — and the pattern in women with childhood ADHD is notably more severe.

    Cluster 1: Physical Multimorbidity

    Conditions concentrated in physical health domains — respiratory, metabolic, gastrointestinal. This cluster was seen only in women without a childhood ADHD diagnosis.

    Cluster 2: Mixed-System Multimorbidity

    Both physical conditions and common psychiatric conditions like anxiety and depression. Present in both groups, but more loaded in the ADHD group.

    Cluster 3: Pan-System Multimorbidity (most severe)

    A high burden of conditions spanning nearly every body system — and in the ADHD group specifically, a significantly higher concentration of:

    • Post-traumatic stress disorder (PTSD)
    • Borderline personality disorder (BPD) — uniquely concentrated in this cluster for those with childhood ADHD, virtually absent from all other clusters
    • Anxiety and depression at elevated rates
    • Physical conditions across multiple systems

    This pan-system cluster also had the highest number of hospital admissions and the longest total days spent in hospital. The health toll is real, measurable, and preventable.

    Other research adds further context. Girls and women with ADHD carry higher risk of eating disorders, suicide attempts, suicidal ideation, and dying younger — compared not just to the general population, but also compared to boys and men with ADHD.

    Why Does Poverty Make Everything Worse?

    Why Does Poverty Make Everything Worse?

    The study didn’t just look at ADHD in isolation. It asked: what happens when a girl grows up with ADHD and in socioeconomic deprivation?

    The answer is stark.

    Girls with both ADHD and childhood poverty had odds of multimorbidity nearly 4 times higher than those with neither. Crucially, 39% of that excess risk was driven by the interaction between the two — not just their individual effects added together. That’s a synergistic effect, where two vulnerabilities collide to create something worse than the sum of their parts.

    Think about what poverty actually does to a child with ADHD:

    • Reduced access to timely diagnosis and specialist support
    • Higher exposure to adverse childhood experiences and trauma
    • Greater stress on the family system, limiting parental capacity to advocate
    • Less access to tutoring, therapy, or coping strategies
    • Heightened biological stress responses from chronic environmental pressure

    ADHD rarely occurs in a vacuum. The biological pathways — dysregulated stress responses, inflammation, impulsivity — interact with social and structural disadvantage. Girls from deprived backgrounds with ADHD carry both, and the healthcare system largely fails to address them together.

    What Happens When ADHD Goes Undiagnosed for Years?
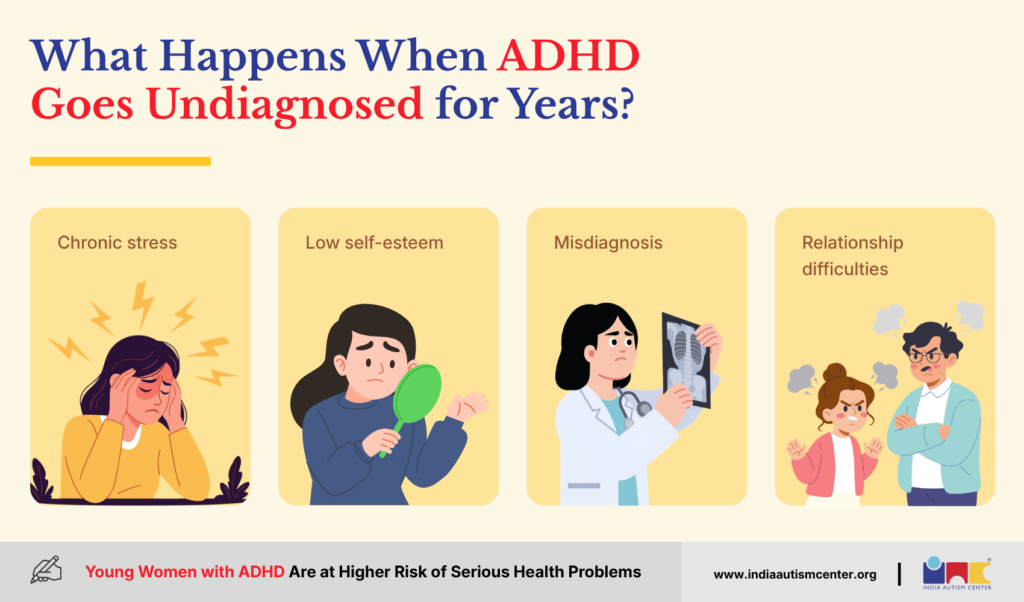
    What Happens When ADHD Goes Undiagnosed for Years?

    The consequences of missed diagnosis are not abstract. They accumulate over time.

    Women with undiagnosed ADHD are more likely to experience:

    • Chronic stress from years of compensating without understanding why
    • Low self-esteem — often internalising failure as a character flaw rather than a neurological difference
    • Misdiagnosis — being treated for anxiety or depression while the underlying ADHD goes untreated
    • Relationship difficulties — higher rates of partner abuse, unplanned pregnancies, and social isolation

    One 2025 study in Scientific Reports found that women with late-diagnosed ADHD commonly reported guilt, shame, and deeply negative self-perception as a direct result of delayed diagnosis. Many described the diagnosis itself as revelatory — their lives finally making sense.

    The life expectancy data is sobering. A 2025 study tracking over 30,000 adults with ADHD found that women with ADHD had an average life expectancy of 75.15 years, compared to 83.79 years for women without ADHD. That’s nearly a nine-year gap.

    We have a very detailed, comprehensive article on Attention Deficit Hyperactivity Disorder (ADHD, read it to get more clarity and in-depth understanding

    Want to know more? Get in touch with us.

    How Do Hormones Complicate ADHD In Females?

    How Do Hormones Complicate ADHD In Females?

    Hormones interact with ADHD symptoms throughout a woman’s life in ways that are still being understood — and often dismissed.

    Research from Monash University’s HER Centre, published in the Journal of Psychiatric Research, surveyed 600 women with ADHD and found:

    • 88% reported changes in ADHD symptoms during their menstrual cycle — particularly in the two weeks before their period
    • More than 70% said their symptoms worsened after having a baby
    • 97% said their symptoms were exacerbated during menopause

    This is significant. It means that even women who have learned to manage their ADHD may find their coping strategies collapsing at key hormonal transition points — puberty, pregnancy, postpartum, perimenopause. And because clinicians often don’t connect hormonal shifts to ADHD, these women frequently get sent down the wrong diagnostic path again.

    Anxiety. Depression. Mood disorder. Not ADHD.

    What Does This Mean If You’re a Parent or Caregiver of a Girl with ADHD?

    What Does This Mean If You're a Parent or Caregiver of a Girl with ADHD?

    If your daughter has been diagnosed with ADHD, or if you suspect she might have it, this research carries a direct message: early identification and support matter enormously for her long-term health — not just her school performance.

    Here’s what to watch for:

    Signs of ADHD in girls that are commonly overlooked:

    • Difficulty sustaining attention on tasks that aren’t inherently interesting
    • Losing track of conversations, instructions, or belongings
    • Emotional sensitivity that seems disproportionate to the situation
    • Perfectionism and overcompensation as a way of hiding struggles
    • Social anxiety or difficulty maintaining friendships
    • Fatigue from the effort of masking

    What you can do:

    • Push for a comprehensive assessment if you see these patterns — don’t accept “she seems fine in class” as a complete answer
    • Address co-occurring anxiety or depression alongside ADHD, not instead of it
    • Consider socioeconomic stressors as part of the picture — practical and material support matters too
    • Connect with specialists who understand female presentations of ADHD

    The 2026 study is explicit: girls with ADHD from disadvantaged backgrounds are a high-risk group for long-term health complications and need earlier, more integrated care.

    📥 Free download: Printable daily routine chart for autistic children

    What Should Clinicians And Healthcare Systems Do Differently?

    What Should Clinicians and Healthcare Systems Do Differently?

    The research is clear about the gap between what we know and what clinical practice currently delivers.

    Mental health and medical practitioners need better training in how ADHD presents in girls — including the role of gender expectations, racial and cultural stereotypes, and masking behaviour. Assessment tools designed around male presentations will continue to miss girls.

    More importantly, clinical care needs to address social circumstances alongside neurological ones. Treating the ADHD without addressing poverty, trauma, or lack of support is incomplete care.

    The study calls for public health strategies that treat neurodevelopmental conditions and social determinants of health together — not as separate silos. That shift in thinking, at a systems level, is what could meaningfully reduce the long-term health burden these women carry.

    Key Takeaways at a Glance

    FindingDetail
    Multimorbidity risk in women with childhood ADHD2.38x higher than matched controls
    Risk with ADHD + childhood poverty3.91x higher
    Portion of risk driven by their interaction39%
    Most severe health clusterPan-system multimorbidity with high psychiatric burden
    Unique conditions in ADHD groupPTSD, borderline personality disorder
    Life expectancy gap (women)~8.6 years shorter than women without ADHD
    Diagnostic ratio (boys to girls, childhood)2:1 — likely reflecting systemic underdiagnosis

    Frequently Asked Questions

    Do girls with ADHD grow out of it?

    Not always. Approximately 65% of children diagnosed with ADHD continue to experience symptoms into adulthood. For girls, these symptoms often shift in how they present rather than disappearing entirely.

    Can childhood ADHD cause health problems in adulthood?

    Yes. Research now shows that children and adolescents with ADHD tracked into adulthood have worse health outcomes than their non-ADHD peers — including higher rates of smoking, increased BMI, substance use, diabetes, and chronic respiratory conditions.

    Why are girls with ADHD less likely to be diagnosed?

    Girls tend to present with inattentive, internalised symptoms rather than hyperactive or disruptive ones. Combined with social pressure to mask struggles, this means their ADHD is frequently missed or misidentified as anxiety or depression.

    How does poverty affect ADHD outcomes in women?

    Poverty independently increases the risk of multimorbidity — and when combined with childhood ADHD, the two interact synergistically to create a health burden significantly greater than either factor alone. 39% of the excess risk in the most deprived ADHD group was attributable to that interaction specifically.

    What is multimorbidity?

    Multimorbidity means having two or more long-term health conditions simultaneously. In the context of this research, it includes both physical conditions (respiratory, metabolic, gastrointestinal) and psychiatric conditions (PTSD, depression, borderline personality disorder).

    What are the signs of ADHD in girls that are often missed?

    Key signs include difficulty sustaining attention, emotional dysregulation, perfectionism used to mask struggles, daydreaming, social difficulties, and extreme fatigue from the ongoing effort of appearing “fine.”


    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

    Disclaimer: This article is intended for educational and informational purposes only. It does not constitute medical advice, diagnosis, or treatment. If you have concerns about your child’s development, attention, or behaviour, please consult a qualified healthcare professional. The research cited here reflects findings at the time of writing and should not be used as a substitute for personalised clinical guidance.


  • How the Brain Processes Social vs. Nonsocial Rewards in Autism

    How the Brain Processes Social vs. Nonsocial Rewards in Autism

    In autism, the brain processes social rewards — like smiles, praise, or eye contact — differently from nonsocial rewards like food or sensory experiences. This isn’t indifference. Specific brain circuits that connect emotional value to social signals show reduced functional connectivity in individuals with higher autistic traits. That distinction changes everything about how we support autistic people.

    What Are Social and Nonsocial Rewards — and Why Does the Difference Matter?

    What Are Social and Nonsocial Rewards — and Why Does the Difference Matter?

    Before we get into the neuroscience, it helps to be clear on what we mean.

    Social rewards are things that feel good because they involve human connection. A smile from a parent. A “well done” from a teacher. Eye contact that signals approval.

    Nonsocial rewards are things that are intrinsically satisfying — independent of another person. Food, money, a favourite object, a particular texture or sound.

    For most neurotypical people, social rewards feel powerful and motivating from birth. For many autistic individuals, this isn’t the case — and understanding why at a brain level is what the latest research is finally beginning to explain.

    How Does the Neurotypical Brain Respond to Social Rewards?

    How Does the Neurotypical Brain Respond to Social Rewards?

    The brain doesn’t have one single “reward centre.” It has a whole network of regions that work together.

    When a neurotypical person receives a social reward — say, a warm smile — several brain areas activate in coordination:

    Brain RegionRole in Reward Processing
    Medial Orbitofrontal Cortex (mOFC)Assigns value to an experience — tells you if it’s worth seeking again
    Ventral StriatumDrives motivation and anticipation of reward
    Anterior Insula (AI)Processes emotional and bodily feelings; makes social moments feel significant
    Anterior Cingulate Cortex (ACC)Integrates emotion and decision-making; tracks whether things are “going well”
    Fusiform Gyrus (FG)Specialises in face recognition and reading social cues
    AmygdalaTags experiences with emotional salience

    Social rewards activate all of these regions. More importantly, these regions talk to each other. It’s the connectivity between them — the neural conversation — that gives social rewards their motivating power.

    Want to know more? Get in touch with us.

    What Is the Social Motivation Hypothesis of Autism?

    What Is the Social Motivation Hypothesis of Autism?

    The social motivation hypothesis is one of the most influential frameworks in autism research.

    The idea is this: autistic individuals may experience social stimuli as less rewarding from early in development. Because social rewards don’t activate the brain’s reward system as strongly, there’s less drive to seek out social interaction. Less interaction means fewer opportunities to develop social skills. This compounds over time.

    It’s a cascade — not a single deficit.

    The hypothesis suggests that what looks like a “social communication difficulty” on the outside is, at its root, a difference in how the brain assigns value to social experiences. The brain isn’t broken. It’s running a different calculation.

    This theory has been supported by neuroimaging studies, but the picture is far more nuanced than the original hypothesis suggested. And that’s what makes recent research so important.

    What Does the 2025 fMRI Study Actually Show?

    What Does the 2025 fMRI Study Actually Show?

    A 2025 study published in Personality Neuroscience — co-authored by researchers affiliated with the University of Reading and India Autism Center, Kolkata — looked directly at how autistic traits affect the brain’s response to social versus nonsocial rewards.

    Here’s what makes this study stand out: most earlier research used artificial stimuli — strangers’ faces, abstract symbols. This study used real-world images, carefully matched for emotional intensity, brightness, and arousal levels. That makes the findings much closer to everyday life.

    What they did:

    • 37 adults underwent fMRI brain scanning
    • Participants viewed social reward images (e.g., warm, genuine smiles) and nonsocial reward images matched for emotional valence
    • Researchers measured both brain activity and subjective ratings of how positive each image felt

    What they found:

    Individual preference for social images was linked to stronger functional connectivity between two specific pairs of brain regions:

    • The left anterior insula (LAI) and the medial orbitofrontal cortex (mOFC)
    • The left fusiform gyrus (LFG) and the anterior cingulate cortex (ACC)

    In individuals with higher autistic traits, both of these connections were weaker.

    Those same individuals also rated social images as less positive — their subjective experience matched the reduced brain activity. This is significant. It means the difference isn’t just detectable on a brain scan. It shows up in how people actually feel about social moments.

    Which Brain Regions Are Most Affected in Autism’s Reward System?

    Which Brain Regions Are Most Affected in Autism's Reward System?

    Let me break this down simply.

    The anterior insula is what helps you feel why something matters emotionally. When it doesn’t communicate well with the mOFC (which assigns value to experiences), social moments don’t get flagged as worth repeating.

    The fusiform gyrus is your brain’s face-processing hub. When it doesn’t connect strongly to the ACC (which tracks social outcomes), reading and responding to others’ expressions becomes harder to integrate with decision-making.

    In short: the individual parts of the brain may be functioning. But the pathways between them are weaker. It’s like having all the instruments in an orchestra but the musicians aren’t hearing each other clearly.

    Is It Social Rewards Specifically — or All Rewards?

    Is It Social Rewards Specifically — or All Rewards?

    This is one of the most debated questions in the field. And the honest answer is: it depends.

    Some studies show reduced reward responses only in the social domain. Others find that reward processing differences in autism span both social and nonsocial categories — including monetary rewards.

    What recent evidence suggests is a more nuanced position:

    • Reward processing in autism is not absent — it is differently calibrated
    • The brain may still process nonsocial rewards quite typically in many autistic individuals
    • The specific disruption appears to be in how social information gets translated into reward value
    • This means autistic individuals can and do experience strong reward responses — just often through nonsocial channels (interests, sensory experiences, objects)

    This has real implications for how we design therapy, learning environments, and motivational strategies.

    What’s the Difference Between Reward Anticipation and Reward Reception in Autism?

    Difference Between Reward Anticipation and Reward Reception in Autism

    This distinction often gets overlooked — but it matters practically.

    Research using EEG (measuring electrical brain activity) has found that autistic individuals and those with higher autistic traits actually show heightened brain responses during the anticipation phase of reward — the moment when you’re expecting something good to happen.

    But during the reception of social rewards — when the smile or praise actually arrives — the neural response is attenuated, particularly for social rewards.

    Think of it this way: the autistic brain may expect a reward with as much (or more) excitement as anyone else. But when the reward is a social one — a nod, a smile, a word of approval — it doesn’t land with the same neural weight.

    This is a crucial distinction for parents and educators. It means the issue isn’t low motivation overall. It’s that social feedback specifically may not register as the powerful signal it does for neurotypical peers.

    Does This Look the Same for Autistic Girls and Boys?

    Does This Look the Same for Autistic Girls and Boys?

    No — and this is an important gap in the original social motivation theory.

    Research using fMRI in children and adolescents found that autistic girls showed increased neural activity to social rewards — not decreased. Specifically, autistic girls showed greater activity in the nucleus accumbens (a core reward region) and the anterior insula compared to typically developing girls.

    This is the opposite of what’s been found in autistic boys.

    What this tells us:

    • Reduced social reward sensitivity is not universal across all autistic people
    • The neural profile may differ significantly between autistic males and females
    • This likely contributes to why autistic girls are frequently missed in diagnosis — their social reward processing may not match the pattern that diagnostic criteria were originally built to detect

    The science is still developing here. But it’s a reminder that “autism” is not one brain type.

    How Does This Research Change the Way We Should Support Autistic Individuals?

    How Does This Research Change the Way We Should Support Autistic Individuals?

    Understanding the neuroscience shifts the frame entirely.

    When an autistic child doesn’t respond to praise or social approval the way a parent or teacher expects, it isn’t stubbornness, lack of effort, or emotional disconnection. The brain’s reward circuitry is genuinely processing that social signal differently.

    Here’s what this means practically for:

    Families:

    • Combining social rewards with preferred nonsocial rewards (a favourite activity, a sensory item) can be more effective than relying on praise alone
    • Noticing and responding to what does register as rewarding for your specific child is more useful than assuming praise should motivate them
    • Recognising that reduced social reward responsivity is neurological — not a choice — can reduce blame and conflict at home

    Educators and therapists:

    • Motivational systems that assume social approval is inherently reinforcing may need to be redesigned for autistic learners
    • Strength-based approaches that lean into genuine interests and nonsocial reward preferences are neurologically consistent with what the brain is actually doing
    • The goal isn’t to force social reward sensitivity — it’s to build meaningful engagement in ways the autistic brain can sustain

    Researchers:

    • The 2025 study introduces a new experimental paradigm that could contribute to transdiagnostic biomarkers for social cognitive processes — markers that go beyond diagnosis categories and speak to underlying brain function

    Want to know more? Get in touch with us.

    What Does This Mean for Early Development?

    What Does This Mean for Early Development?

    The social motivation cascade matters most early.

    If social stimuli aren’t registering as rewarding in infancy and early childhood, fewer social interactions happen. Fewer interactions mean less practice with reading faces, interpreting tone, and building the social pattern recognition that most people develop automatically.

    This isn’t irreversible. But it does mean that early intervention — designed with an understanding of how the autistic brain processes social information — will be more effective than approaches that assume a neurotypical reward system.

    The aim should never be to make social rewards feel “normal” through pressure. The aim should be to meet the brain where it is and build genuine connection from there.

    What Does the Research Still Not Know?

    What Does the Research Still Not Know?

    It’s worth being honest about the limits here.

    • The 2025 fMRI study had 37 participants — a relatively small sample
    • Most neuroimaging studies in this area still have sample sizes under 50
    • The majority of participants in this field historically have been male, white, and Western — limiting generalisability
    • We don’t yet have strong longitudinal data on how these brain patterns change across the lifespan
    • The relationship between neural reward differences and specific everyday behaviours is still being mapped

    The field is moving fast. But we’re still at the point where the findings are highly important directionally, even if the full picture isn’t complete.

    📥 Free download: Printable daily routine chart for autistic children

    Conclusion

    The science of social reward processing in autism is young — but it’s already telling us something important. The autistic brain is not unmotivated. It is not emotionally empty. It is processing the world through a different neural architecture, one where social signals carry less automatic reward weight.

    That understanding should change how we talk about autism. It should change how we design support. And it should deepen our respect for the way autistic individuals navigate a world built largely around social reward systems they experience differently.

    At India Autism Center, our research division Khoj is committed to building an evidence base that reflects the actual diversity of autistic experience — including how the brain’s reward system works differently across individuals. Because better science leads to better support.

    Key Takeaways

    • Social rewards (smiles, praise, approval) and nonsocial rewards (food, money, sensory experiences) are processed by overlapping but distinct brain networks
    • In individuals with higher autistic traits, functional connectivity between the anterior insula and mOFC, and between the fusiform gyrus and ACC, is reduced
    • This reduced connectivity correlates with lower subjective ratings of social images — meaning the brain difference shows up in lived experience
    • The issue is not that autistic individuals can’t feel rewards. It’s that social signals don’t reliably trigger the same reward response as they do in neurotypical brains
    • Autistic girls may show an opposite neural pattern to autistic boys — more activity, not less, to social rewards
    • Practical support should work with the brain’s actual reward preferences, not against them

    Frequently Asked Questions

    Does the autistic brain feel no social rewards at all? 

    No. The autistic brain can and does respond to social stimuli. The difference is in the strength and consistency of the neural signal — reduced functional connectivity between reward-related regions means social rewards may not register as strongly or reliably.

    Can therapy improve social reward processing in autism? 

    Some interventions — particularly those that pair social experiences with preferred nonsocial rewards — may help build positive associations over time. The goal is building genuine engagement, not forcing neurotypical reward responses.

    Is reduced social reward sensitivity the same in all autistic people?

    No. Research shows significant variability — particularly between autistic males and females. Autistic girls, for example, have been found to show increased neural activity to social rewards in some studies, not decreased.

    What brain regions are most involved in social reward processing?

    The anterior insula, medial orbitofrontal cortex, fusiform gyrus, anterior cingulate cortex, and ventral striatum are the most studied. The connections between these regions matter as much as the regions themselves.

    What is the social motivation hypothesis of autism?

    It’s a theory suggesting that autistic individuals experience social stimuli as less rewarding, leading to reduced motivation for social interaction, which then compounds into broader social communication differences over development.

    Educational Disclaimer: This article is intended for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. The research discussed is ongoing and findings from animal or laboratory studies do not automatically translate to clinical recommendations for humans. Parents and caregivers should always consult a qualified medical professional — including a paediatrician, neurologist, or clinical nutritionist — before making any decisions about supplementation or dietary changes for a child with autism. India Autism Center does not endorse any specific supplement, treatment, or brand.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

  • ADHD Meltdown vs Autism Meltdown: Key Differences that Parents Must Know

    ADHD Meltdown vs Autism Meltdown: Key Differences that Parents Must Know

    When your child experiences an intense emotional outburst, it can feel highly overwhelming. Parents do not understand what triggered the outburst or how they can handle it. Moreover, if your child is Neurodivergent, such intense episodes are not just temper tantrums. They are actually biological responses that are labelled as meltdowns.

    Before you decide on the right approach to handle these meltdowns, it is important to understand the difference between an ADHD vs autism meltdown. Both look identical to someone with no idea about neurodivergence. However, the root causes, triggers, and management strategies differ significantly.

    As per the World Health Organisation, 1 in 127 people worldwide is expected to be on the autism spectrum. Besides that, some studies show that 50% to 70% of individuals who have ASD also meet the diagnostic criteria for ADHD.

    The co-occurrence rate can often make distinguishing between an ADHD meltdown and an autistic emotional response very complex. 

    Today, we are going to understand the unique mechanics of an ADHD crisis versus an autism crisis. It will help you move away from traditional disciplinary measures and towards empathetic, proactive care.

    Understanding Neurodivergent Meltdown: Beyond the Surface Behaviour

    Child experiencing a neurodivergent meltdown caused by overwhelming stress

    When comparing ADHD vs autism meltdown, it is important to understand what a meltdown is. Essentially, a neurodivergent meltdown is an involuntary and biological coping mechanism. It happens when the individual’s nervous system is overwhelmed, triggering a primitive fight, flight, or freeze response in the brain.

    When the meltdown happens, the brain’s executive functioning temporarily shuts down. Therefore, the child attempts to lose total control over their emotional regulation, as well as their verbal and physical movements. Parents need to know that it is not an act of defiance, manipulation, or even intentional bad behaviour.

    It is also important to know that these emotional episodes do not only happen to a child with ADHD or autism, but ADHD meltdowns in adults are also very common. It can happen due to workplace stress, sensory overload, or even executive dysfunction, piling up beyond the capacity of a person.

    📥 Free download: Printable daily routine chart for autistic children

    What Does an ADHD Meltdown Look Like?

    Common signs of an ADHD meltdown in children, including rapid emotional escalation

    If you often wonder, what does an ADHD meltdown look like? It is necessary to know that an emotional dysregulation deficit in executive functioning drives frustration.

    ADHD often affects the brain’s frontal lobe, which is responsible for impulse control, emotional processing, working memory, and, more importantly, patience. An emotional eruption occurs when these systems fail.

    Signs and characteristics of ADHD meltdown

    To understand the concept of autism vs ADHD meltdown, it is important to know the correct signs and characteristics of an ADHD meltdown:

    • Sudden Explosive Escalation

    A sudden change in a plan, a boundary being set, or a task that feels impossibly frustrating can be the trigger that sparks an ADHD episode out of nowhere.

    • Verbally and Physically Expressive

    Since hyperactivity and impulsivity are the core features of ADHD, the emotional energy is directed outward. So an ADHD driven episode is where children and adults might shout, slam doors, and throw objects around.

    • Driven by Impulsivity and Frustration

    An ADHD meltdown can happen when a person is reacting to a perceived rejection, the inability to delay gratification, or when they feel failed.

    • Rapid De-escalation

    It is often found that a person who has an ADHD episode comes down relatively quickly once the anger or frustration is expressed or the external trigger is removed. They also feel exhausted immediately after.

    The behaviour of a child during an ADHD meltdown is often due to school or transition between activities, or feeling overwhelmed due to long instructions. However, when it comes to an ADHD meltdown in adults, it often looks like a sudden and intense verbal outburst, which can happen due to a high-stress meeting or when a person breaks down due to a simple routine not going correctly.

    What Does an Autism Meltdown Look Like?

    Common signs of an autism meltdown caused by sensory and cognitive overload

    Contrary to an ADHD meltdown, an autistic meltdown is often a reaction to sensory, cognitive, and emotional overload. Autistic brains process environmental stimuli differently. It absorbs sights, sounds, smells, and textures at a very high intensity when the brain does not process the incoming data, resulting in a system crash.

    Signs and characteristics of an autism meltdown:

    Here are the signs and characteristics that differentiate autism meltdowns from ADHD meltdowns:

    • Sensory and Cognitive Overload

    Autism meltdowns, at times, happen when there is an overload of sensory inputs, like bright lights, a crowd, uncomfortable clothing, or even loud noises. A meltdown can also happen due to cognitive strain, like processing complex social cues. 

    • Complete Loss of Environmental Awareness

    When an autism meltdown happens, the child or adult tends to disconnect from their surroundings completely. They are therefore not able to process verbal commands, nor can they negotiate or reason.

    • A Gradual Rumble Phase

    An autistic meltdown has a building phase. Before the individual loses control or a meltdown begins, they might show signs of distress. They may cover their ears, rock back and forth, keep humming, or pace from one place to another. 

    • Prolonged Recovery

    It is not simple to recover from an autism meltdown. The brain of a person with ASD may take hours or even days to return to normalcy. To recover, a person often needs isolation and experiences physical fatigue. 

    • Inward or Outward Expression

    Not every autism meltdown will have outward expression. At times, instead of an intense reaction or outburst, you may see the individual shutting down. The individual becomes completely mute, still unresponsive. 

    Want to know more? Get in touch with us.

    Key Differences: ADHD Meltdown vs Autism Meltdown

    Key differences between ADHD meltdowns and autism meltdowns in children

    It is possible to differentiate between ADHD meltdown and autism meltdown when you know the timeline, the triggers and the recovery needs. 

    The table below explains how these two neurological experiences are different from one another:

    FeatureADHD MeltdownAutism Meltdown
    Primary Root CauseExecutive dysfunction, poor impulse control, and intense emotional dysregulation.Sensory overload, cognitive saturation, or an inability to process environmental changes.
    Common TriggersFrustration, boredom, being told “no,” sudden transitions, or tasks requiring sustained mental effort.Loud noises, bright lights, unpredictable social situations, changes in routines, or sensory discomfort.
    Onset SpeedRapid, impulsive, and explosive, often occurring immediately after a specific frustrating event.Gradual, building up over time through a noticeable “rumble phase” as sensory data accumulates.
    Awareness During EpisodeThe individual generally remains aware of their environment but lacks the emotional control to stop their behaviour.The individual experiences a temporary sensory and cognitive disconnect, becoming unaware of external reasoning.
    Manifestation StylesAlmost always externalised, featuring verbal expressions, emotional outbursts, or physical movement.Can be externalised (screaming, thrashing) or completely internalised as a quiet, unresponsive “shutdown.”
    Recovery MechanismCalms down relatively quickly once the immediate frustration passes or the trigger is addressed.Requires an extended recovery period involving sensory deprivation, quiet spaces, and deep rest.

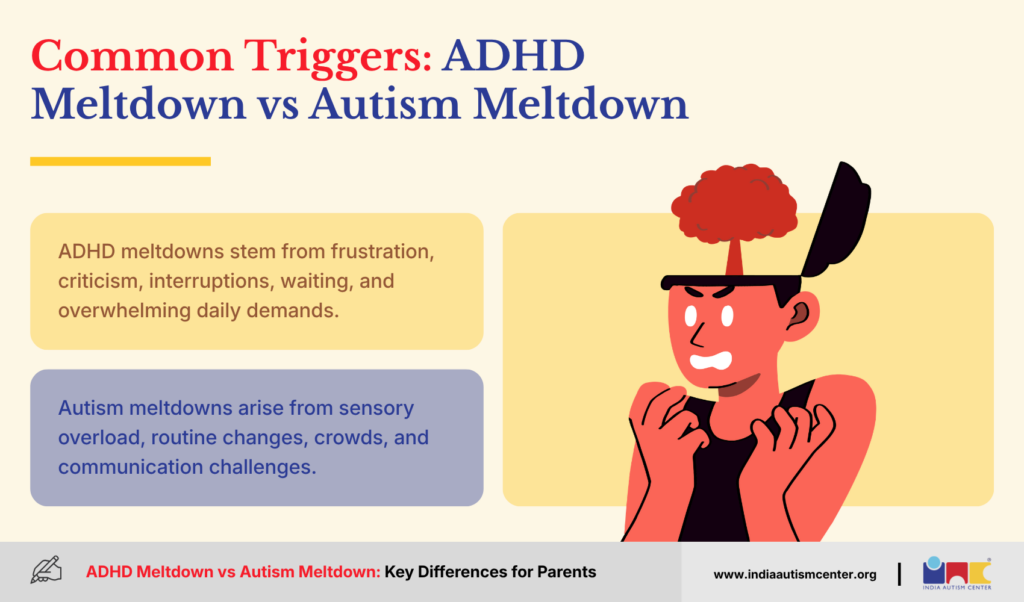
    Common Triggers: ADHD Meltdown vs Autism Meltdown

    Common triggers of ADHD and autism meltdowns, including frustration and sensory overload

    Parents and caregivers can easily prevent many meltdowns if they know how to recognise the triggers. However, every individual is different, and certain situations may be more commonly associated with one condition than another.

    Common ADHD Meltdown Triggers

    Individuals with ADHD tend to become overwhelmed when they are:

    • Being interrupted while they’re engaged in an activity that they prefer.
    • Waiting for a long period of time.
    • Frustrated after repeated mistakes,
    • Feeling criticised or rejected.
    • Looking at sudden changes in expectations.
    • Finding it difficult to complete tasks
    • Bombarded with too many demands at once

    At times, even simple, daily activities can become mentally exhausting and can thus trigger an ADHD meltdown.

    Common Autism Meltdown Triggers

    Autism meltdown triggers become very common when autistic individuals are exposed to:

    • Unexpected changes in their routine,
    • Bright lights, strong smells, or loud and unpredictable noises.
    • Heavily crowded places.
    • Social pressure from family and friends
    • Difficulty in communication
    • Sensory discomfort from food, texture, and clothing

    Autism meltdowns are mostly caused by sensory overload.

    The basic distinction between the two is that ADHD meltdowns happen due to emotional frustration, and autism meltdowns happen due to sensory and environmental factors.

    How Can Parents Tell the Difference Between ADHD and Autism Meltdown?

    How parents can identify differences between ADHD and autism meltdowns

    Parents and caregivers often look for a simple way to understand which type of meltdown the child is experiencing. Parents need to consider three important questions rather than just focusing on the child’s behaviour.

    Below are all the questions that parents must consider:

    1. What happened right before the meltdown started?

    Suppose a child gets upset after losing a game, feels frustrated, or agitated when they’re corrected; it is more likely to be an ADHD meltdown.

    On the other hand, if the meltdown happens after a loud noise, a change in the routine or any other overwhelming sensory experience, then autism may be the case.

    2. What does your child need during a meltdown?

    The child benefits from emotional reassurance. Once they begin to calm down, it is mostly ADH hd meltdown.

    However, if a child seems first to need a quiet and low-stimulation environment before they can actually communicate, then it is more likely to be an autism meltdown.

    3. How did the recovery happen?

    If you find that your child gradually comes down as the emotion settles, it is an ADHD meltdown.

    But if your child needs additional recovery time because the nervous system remains overactive, then your child might be experiencing an autism meltdown.

    Want to know more? Get in touch with us.

    What Should Parents Do During a Meltdown?

    Parent calmly supporting a distressed child during a meltdown

    In both cases, the goal is not to stop the behaviour immediately. First, make sure your child feels safe, then regulate their nervous system.

    Here are some helpful strategies that parents can try:

    • Stay calm and make sure to use a gentle tone when talking to them.
    • Reduce unnecessary talking and keep the instructions brief.
    • Remove any possible and immediate safety risks. Aim to reduce sensory input whenever possible.
    • Give the child physical space if needed.
    • Make sure to validate their emotions without reinforcing unsafe behaviour.
    • Before discussing what happened, make sure that your child is calm.

    Parents often feel the need to teach their kids a lesson during a meltdown. However, it is important to know that the brain is not ready to learn while the meltdown is happening. Hence, problem-solving needs to occur only after emotional regulation has returned.

    How Can the India Autism Center Be Helpful?

    India Autism Center providing developmental assessment and support to a family

    At India Autism Center, we understand that every child experiences the world differently, and hence, families receive evidence-based guidance tailored to each child’s developmental profile.

    Support is provided through comprehensive assessment, early intervention programmes, various therapies, and behavioural support. The Center empowers the children to reach their potential. 

    With a multidisciplinary approach and a strong focus on inclusion, India Autism Center works alongside many families throughout the journey.

    Conclusion

    Supportive responses for children experiencing ADHD or autism meltdowns

    When parents can understand the key differences between an ADHD meltdown and an autism meltdown, it can be a transformative step. Both types represent a state of neurological stress. However, it is important to know whether that episode is driven by acute frustration of ADHD or the sensory saturation of autism.

    This helps you to respond with the correct support that your child needs in that moment. When parents treat episodes as cries for help rather than behavioural defiance, they can create a safe and supportive environment for a neurodivergent child, who can then navigate the world with peace of mind and confidence.

    Frequently Asked Questions

    What is the primary difference between an ADHD meltdown and an autism meltdown?

    The main differences are that ADHD is triggered by emotional frustration, difficulty regulating emotions, or even impulsivity. However, meltdowns are often caused by overload, unexpected changes, or environmental or communication challenges.

    Can a child have both ADHD and autism?

    Yes, ADHD and autism can co-exist. In fact, some studies suggest that about 30 to 50% of people who are autistic also have ADHD.

    Do ADHD meltdowns happen in adults?

    Yes, ADHD meltdowns can happen in adults as well. The most common symptoms include emotional responses such as irritability, crying, anger, or shutting down.

    How long does an ADHD meltdown usually last?

    The time period for which an ADHD meltdown lasts can vary from person to person. Some ADHD symptoms last only a few minutes, while others can last longer. 

    What should parents avoid during an ADHD meltdown?

    It is best if parents avoid shouting, threatening to punish, forcing eye contact, or asking too many questions. These responses can increase the emotional distress and the meltdown.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

  • Can Zinc Help the Autistic Brain? New Study 2026

    Can Zinc Help the Autistic Brain? New Study 2026

    A new study at the University of Auckland is testing whether zinc can improve communication between human brain cells linked to autism. This is the first time zinc has been tested on human brain cells in a lab setting. The findings could eventually open a treatment path — but experts say we are not there yet.

    What Is The New Zinc And Autism Study About?

    What Is The New Zinc And Autism Study About?

    This is a world-first. Professor Johanna Montgomery at the University of Auckland’s Centre for Brain Research is leading a study that tests the effects of zinc directly on human brain cells grown in a laboratory.

    The research team includes PhD student Zoe Payne, Professor James Ellis from the University of Toronto, and Dr Kevin Lee from the University of California, San Francisco.

    What makes this different from past research is the subject: human brain cells, not mice. Previous studies used animal models. This study bridges that gap.

    The lab process works like this:

    • Blood samples are taken from people with Phelan-McDermid syndrome — a condition linked to autism caused by deletion of the SHANK 3 gene
    • Cell samples from individuals with SHANK 2 gene variants, associated with severe autism, are also included
    • These blood cells are “trained” in incubators and multiplied into thousands of brain cells
    • Electrodes then measure how well signals travel between brain cells — before and after a dose of zinc

    The hypothesis is that zinc strengthens communication between brain cells. The mouse research already proved this. Now the team wants to know if it holds true in human cells.

    What Did Earlier Zinc And Autism Research Find?

    What Did Earlier Zinc And Autism Research Find?

    Professor Montgomery has spent 15 years studying the relationship between autism and SHANK genes. That background matters here because it explains why zinc became a focus.

    SHANK genes are responsible for building the proteins that allow neurons to talk to each other. When SHANK genes are missing or altered — as they are in some people with autism — those communication pathways break down.

    Here is what the mouse research found:

    Research StageKey Finding
    Zinc given to pregnant and lactating miceOffspring showed fewer autistic behaviours (less anxiety, fewer repetitive actions, better social interaction)
    Zinc given after weaningBeneficial effects still observed — some autistic behaviours reversed
    Best outcomesIn some mice, autistic behaviours completely disappeared

    A separate 2024 study from Academia Sinica in Taiwan added to this picture. Researchers found that a low-dose combination of zinc, serine, and branched-chain amino acids restored more typical synaptic protein patterns and reduced excessive amygdala activity across three autism mouse models.

    The consistency across different research groups is what makes this area genuinely exciting.

    Want to know more? Get in touch with us.

    Why Does Zinc Matter For Brain Development?

    Why Does Zinc Matter For Brain Development?

    Zinc is not just an immune-boosting mineral you take when you have a cold. It plays a deep, structural role in how the brain forms and functions.

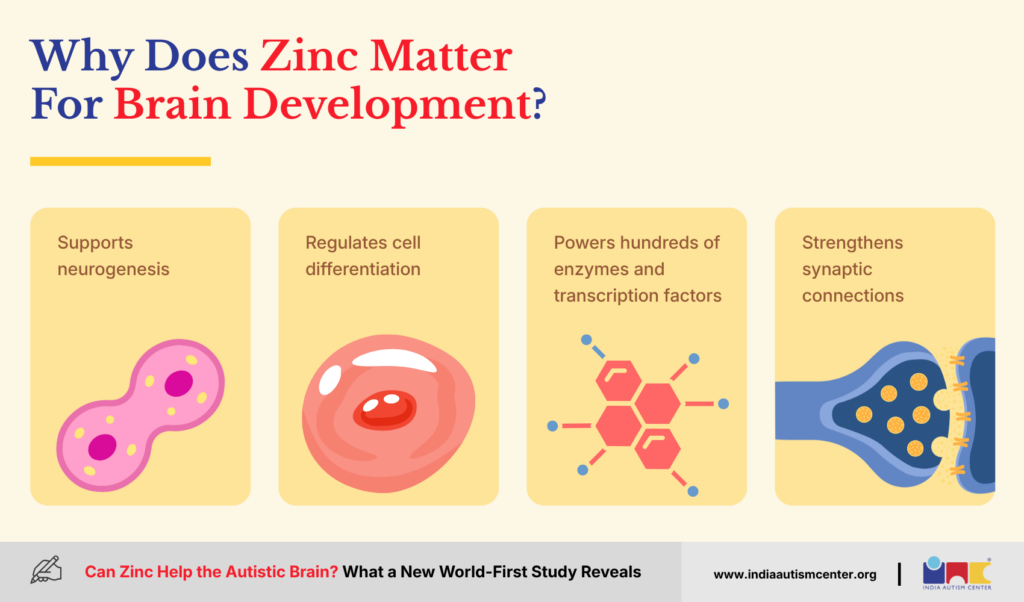
    Here is what zinc does in the brain specifically:

    • Supports neurogenesis — the formation of new brain cells
    • Regulates cell differentiation — determining what type of cell a brain cell becomes
    • Powers hundreds of enzymes and transcription factors that control gene expression
    • Strengthens synaptic connections — the junctions where brain cells communicate

    The body cannot store large amounts of zinc. It has to come in regularly through food. When intake is inadequate or absorption is poor, deficiency builds up — and developing brains are especially vulnerable to that.

    The SHANK gene connection is particularly important here. Zinc physically interacts with SHANK proteins at the synapse. When zinc levels are low, those proteins may not function correctly — which, in some individuals with specific gene variants, could contribute to the communication difficulties seen in autism.

    Is There A Proven Link Between Low Zinc Levels And Autism?

    Is There A Proven Link Between Low Zinc Levels And Autism?

    The evidence is growing — and it is more consistent than many people realise.

    A 2025 systematic review and meta-analysis published in Frontiers in Nutrition analysed 25 case-control studies involving nearly 4,800 children and adolescents. The conclusion was clear: blood zinc levels are associated with autism spectrum disorder.

    Earlier, a study published in Frontiers in Molecular Neuroscience suggested that zinc deficiency in early childhood may contribute to autism — particularly through its effect on developing synapses.

    Researchers at the Autism Research Institute have gone further, proposing a framework in which disrupted zinc homeostasis may act as a modifiable risk factor in a gene-environment interaction model of ASD.

    What does that mean in plain language? Some children may have a genetic predisposition to autism that is worsened by insufficient zinc during critical windows of brain development.

    A few important caveats:

    • Correlation is not causation. Low zinc has been observed in children with autism, but we cannot yet say it causes autism.
    • Not every child with autism has low zinc levels.
    • The zinc-autism connection is strongest in individuals with specific SHANK gene variants — not necessarily across the entire autism spectrum.

    If you want to learn more about Autism in detail, refer to our comprehensive article on the A to Z of Autism.

    What Is Phelan-McDermid Syndrome And Why Is It The Starting Point For This Research?

    What Is Phelan-McDermid Syndrome

    Phelan-McDermid syndrome is a rare genetic condition caused by the partial or complete deletion of the SHANK 3 gene on chromosome 22. It typically presents with:

    • Autism or autistic traits
    • Severely impaired learning and speech
    • Gastrointestinal disorders
    • Seizures
    • Low muscle tone

    Professor Montgomery spent years building relationships with families of people with this condition. Those partnerships matter — because families are directly involved in providing the blood samples for the research.

    The reason this specific population is the entry point for the study is strategic. Phelan-McDermid syndrome gives researchers a clean genetic variable — the SHANK 3 deletion is clearly defined. This allows them to study zinc’s effects in a controlled biological context before expanding to the broader autism population.

    The roadmap after the brain-cell experiments is a pilot clinical trial examining the effects of zinc supplementation on:

    1. Social behaviours

    2. Cognitive abilities

    The trial will start with people with Phelan-McDermid syndrome, then broaden to include people with severe autism.

    Want to know more? Get in touch with us.

    Should Children With Autism Take Zinc Supplements Right Now?

    Should Children With Autism Take Zinc Supplements Right Now?

    The direct answer is: no, not yet.

    Professor Montgomery is explicit on this. Zinc can cause harmful effects at the wrong dosage. Taking too much zinc is not safe — and without knowing the precise dosage that may be helpful, supplementation at this stage could do more harm than good.

    There is also a deeper issue. Numerous factors lead to Autism. Not all of those factors are linked to SHANK gene variants. Even if zinc proves beneficial for individuals with Phelan-McDermid syndrome or specific SHANK mutations, that does not automatically extend to everyone on the autism spectrum.

    What I would suggest for parents reading this:

    • Do not self-supplement based on this research
    • Speak with your child’s paediatrician or clinical nutritionist if you have concerns about zinc levels
    • If your child has a known SHANK gene variant, it may be worth discussing blood zinc screening with your specialist
    • Focus on dietary zinc through food — the safest and most balanced approach

    The science is promising. The clinical path is real. But the research is still in progress — and acting ahead of it is not the right call.

    What Foods Are Naturally High In Zinc?

    What Foods Are Naturally High In Zinc?

    While we wait for the clinical evidence to mature, supporting healthy zinc levels through diet is a sensible and safe step.

    Animal-based zinc sources (highest bioavailability):

    FoodNotes
    OystersRichest known food source of zinc
    Red meat (lamb, beef)High in zinc and well-absorbed
    Poultry (chicken, turkey)Good everyday source
    Seafood (crab, shrimp)Solid zinc content
    Eggs and dairyModerate zinc, widely accessible

    Plant-based zinc sources:

    FoodNotes
    Pumpkin seedsOne of the best plant sources
    Hemp seedsHigh in zinc and easy to add to food
    CashewsPractical snack-based source
    Chickpeas, lentils, rajmaExcellent for Indian diets
    Whole grains (atta, oats)Fortified cereals also contribute
    Sesame seeds (til)Common in Indian cooking, good zinc source

    One important note for plant-based diets: Phytates — found in legumes and whole grains — can reduce zinc absorption. Soaking, sprouting, or fermenting these foods before eating can meaningfully improve absorption.

    For families in India, combining these traditional ingredients intelligently can support adequate zinc intake without supplementation.

    What Does This Mean For Autism Research And Families Going Forward?

    What Does This Mean For Autism Research And Families Going Forward?

    Let me put this in perspective. Globally, autism affects around 1 in 100 people. In India, estimates suggest anywhere from 1 to 1.5 crore individuals live with autism — and there is currently no drug treatment approved specifically for autism.

    That is the gap this research is trying to address — not with a cure, but with a targeted, biologically grounded treatment possibility for a specific subgroup.

    Here is where the research stands and where it is going:

    Stage 1 (Current)

    Testing zinc on human brain cells grown from blood samples of people with Phelan-McDermid syndrome and SHANK 2 variants → measuring changes in brain cell signalling via electrodes.

    Stage 2 (Upcoming)

    Pilot clinical trial testing zinc supplementation on social behaviour and cognitive ability in people with Phelan-McDermid syndrome.

    Stage 3 (Future)

    Expanding the trial to include people with severe autism more broadly.

    This is a multi-year process. The early findings are promising, but science moves carefully — and in this case, that caution protects the very people the research is trying to help.

    What this research does signal, for families and organisations working in autism care, is that the nutritional and metabolic dimensions of autism are no longer on the fringe of research. They are being taken seriously at the highest levels of neuroscience.

    📥 Free download: Printable daily routine chart for autistic children

    Conclusion

    • A world-first study at the University of Auckland is testing zinc on human brain cells linked to autism — specifically in people with Phelan-McDermid syndrome and SHANK 2 gene variants.
    • Earlier mouse research showed zinc can prevent or reverse some autistic behaviours, particularly when given during early brain development.
    • Blood zinc levels are consistently lower in children with ASD across multiple large studies.
    • The mechanism involves zinc’s interaction with SHANK proteins at the synapse — critical junctions for brain cell communication.
    • Experts advise against zinc supplementation without medical guidance. The wrong dosage can cause harm.

    • Supporting zinc levels through diet — particularly oysters, pumpkin seeds, legumes, and seeds — is a safe and practical approach.
    • A pilot clinical trial is in development and will eventually move from Phelan-McDermid syndrome to broader autism populations.

    Frequently Asked Questions

    Does zinc deficiency cause autism?

    Not directly. Low zinc levels are consistently observed in children with ASD, particularly those with SHANK gene variants. Researchers believe zinc deficiency during early brain development may contribute to or worsen autistic traits in genetically predisposed individuals — but it is not established as a standalone cause.

    Can zinc supplements help children with autism?

    Current evidence does not support using zinc supplements without medical supervision. Studies in mice are promising, but the human brain cell study is still underway. A clinical trial is being developed. Parents should consult a paediatrician before making any changes

    What is the SHANK gene and how does it connect to zinc?

    SHANK genes code for proteins that build synaptic structures — the connection points between brain cells. Zinc interacts directly with these proteins. When SHANK genes are altered or deleted, as in some people with autism or Phelan-McDermid syndrome, zinc’s role in keeping synaptic communication functioning may be disrupted.

    What is Phelan-McDermid syndrome?

    A rare genetic condition caused by partial or complete deletion of the SHANK 3 gene. It typically includes autism, intellectual disability, speech difficulties, gastrointestinal issues, and low muscle tone. It is the focus of the current zinc study because it provides a clearly defined genetic context for research.

    Which foods are highest in zinc for children?

    Oysters, red meat, poultry, eggs, and dairy have the highest bioavailable zinc. For vegetarian diets, pumpkin seeds, cashews, chickpeas, lentils, and sesame seeds are good sources. Soaking legumes before cooking improves zinc absorption.

    When will zinc treatment for autism be available?

    There is no timeline yet. The human brain cell study must first yield results. Then a pilot clinical trial will follow. This is a multi-stage process likely spanning several years before any treatment recommendations could be made.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.


    Educational Disclaimer: This article is intended for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. The research discussed is ongoing and findings from animal or laboratory studies do not automatically translate to clinical recommendations for humans. Parents and caregivers should always consult a qualified medical professional — including a paediatrician, neurologist, or clinical nutritionist — before making any decisions about supplementation or dietary changes for a child with autism. India Autism Center does not endorse any specific supplement, treatment, or brand.

  • Does Speech Therapy Work? Here’s What the Evidence Actually Says

    Does Speech Therapy Work? Here’s What the Evidence Actually Says

    Does Speech Therapy Work? The quick answer is yes, speech therapy works. Research consistently shows that structured speech and language therapy improves communication outcomes across age groups and conditions — including autism, Down syndrome, cerebral palsy, stroke, and learning disabilities. The earlier therapy begins, the stronger the results. But it also works for adults, and it’s never too late to start.

    What Exactly Happens In Speech And Language Therapy?

    What exactly happens in speech and language therapy?

    Speech and language therapy (SLT) is a clinical intervention that addresses difficulties with communication, language, voice, fluency, and swallowing. A licensed speech-language pathologist (SLP) assesses where the breakdown is — whether it’s in articulation, comprehension, social language, or something else — and builds a plan around that.

    The process is structured, goal-driven, and highly individualised. No two therapy plans look the same, because no two people communicate the same way.

    Sessions can be one-on-one, group-based, or a combination. They happen in clinics, schools, hospitals, or even online. What makes therapy effective isn’t just the technique — it’s consistency, family involvement, and early identification.

    What Does Speech And Language Therapy Actually Treat?

    What does speech and language therapy actually treat?

    This is a question worth answering clearly, because many families think SLT is only for children who stutter or mispronounce words. It’s far broader than that.

    SLT addresses:

    ConditionWhat SLT Targets
    Autism Spectrum DisorderSocial communication, AAC, pragmatic language
    Down SyndromeArticulation, vocabulary, functional communication
    Cerebral PalsyMotor speech, alternative communication systems
    Stroke / AphasiaLanguage recovery, word retrieval, reading
    Learning DisabilitiesPhonological awareness, reading foundations
    Selective MutismAnxiety-linked speech, graduated exposure
    Voice DisordersVocal hygiene, resonance, pitch
    DysphagiaSafe swallowing, food textures, oral motor skills
    Intellectual DisabilitiesExpressive language, life-skills communication

    If communication is the challenge — in any form — speech and language therapy is the clinical pathway.

    Does Speech Therapy Work For Children?

    Does speech therapy work for children?

    Yes, children’s speech and language therapy has one of the strongest evidence bases in all of rehabilitation medicine. The brain’s neuroplasticity — its ability to form new connections — is at its peak during the early years. This is why early intervention matters so much.

    Children who receive therapy between ages 2 and 5 tend to show significantly faster progress. But even children who begin later still benefit from structured intervention.

    What therapy typically works on in children:

    • Phonological awareness (the foundation of reading and spelling)
    • Expressive vocabulary (putting words and sentences together)
    • Receptive language (understanding instructions and questions)
    • Pragmatics (taking turns, reading facial expressions, staying on topic)
    • Articulation (clear sound production)
    • Fluency (managing stuttering)

    The goal isn’t to make a child sound “normal.” The goal is to give them the tools they need to communicate effectively in the environments that matter to them — home, school, friendships.

    Want to know more? Get in touch with us.

    Does Speech And Language Therapy Work For Down Syndrome?

    Does speech and language therapy work for Down syndrome?

    This is one of the most common questions I encounter. And the answer is: yes, meaningfully so.

    Down syndrome affects speech and language in specific, well-documented ways. Low muscle tone (hypotonia) makes articulation difficult. Shorter working memory affects sentence processing. Hearing issues — very common in Down syndrome — compound the challenge.

    Speech and language therapy for Down syndrome targets all of these simultaneously.

    Key approaches used in Down syndrome SLT:

    • Oral motor exercises — to build lip, tongue, and jaw strength
    • Total Communication — combining speech with sign language and visuals
    • AAC (Augmentative and Alternative Communication) — devices, boards, or apps for those who need them
    • Phonological awareness training — critical for literacy
    • Short, structured language input — matched to processing speed
    • Reading-based language intervention — individuals with Down syndrome often learn through reading, which supports spoken language development

    Research from the Down Syndrome Education International has shown that structured, consistent SLT — started early and sustained across childhood — leads to measurable gains in vocabulary, intelligibility, and literacy. The therapy doesn’t “fix” Down syndrome. It addresses the specific communication challenges that come with it, directly and practically.

    Does Speech Therapy Work For Adults?

    Does Speech Therapy Work For Adults?

    Absolutely. This is one of the most underappreciated areas of the field.

    Speech and language therapy for adults covers post-stroke aphasia, acquired brain injury, Parkinson’s disease, voice disorders, and stuttering. Adults recovering from stroke, for example, can regain significant language function through intensive SLT — even months or years after the event.

    The adult brain retains neuroplasticity. It adapts more slowly than a child’s brain, but it adapts. Programmes like LSVT LOUD (for Parkinson’s) and Constraint-Induced Language Therapy (for aphasia) have clinical trial data showing real, sustained improvements.

    Why adults delay or avoid SLT:

    • Assumption that “it’s too late”
    • Limited awareness that services exist for adults
    • Stigma around communication difficulties
    • Access and cost barriers

    None of these makes the therapy less effective. They make access harder — which is a systemic problem worth naming.

    Refer to our detailed blog on Speech Therapy for Adults

    What Speech And Language Therapy Techniques Are Actually Used?

    What Speech And Language Therapy Techniques Are Actually Used?

    This varies by condition and age, but here are the evidence-based techniques you’ll most commonly encounter:

    Articulation Therapy

    The SLP works on specific sounds the person struggles to produce, using repetition, auditory feedback, and visual cues. Most effective for children with phonological disorders.

    Language Intervention Activities

    Structured play and conversation activities that target specific language goals. The therapist models correct language and builds on what the child produces.

    Augmentative and Alternative Communication (AAC)

    For individuals who cannot rely on speech alone. Includes low-tech options (picture boards) and high-tech (speech-generating devices). AAC doesn’t replace speech — it supports communication and often facilitates speech development.

    Social Communication Therapy

    Targets pragmatic skills — understanding context, reading non-verbal cues, initiating and maintaining conversations. Frequently used in autism therapy.

    Fluency Shaping

    Used for stuttering. Teaches slower, relaxed speech patterns to reduce disfluency.

    Voice Therapy For vocal nodules, paralysis, or misuse injuries. Includes vocal hygiene education, breath support training, and resonance work.

    PROMPT Therapy

    A tactile-kinaesthetic approach where the therapist physically guides jaw, lip, and tongue movements. Used for motor speech disorders like apraxia.

    Narrative and Literacy-Based Therapy

    Uses stories and books to build sentence structure, vocabulary, and inferential language. Particularly effective for school-age children.

    This blog will help you get better insights 5 Effective Speech Therapy Techniques for Autism

    What Are Speech And Language Therapy Assessments Like?

    What are speech and language therapy assessments like?

    Before therapy begins, a comprehensive assessment is done. This is not a pass/fail test. It’s a diagnostic process that helps the therapist understand exactly where and how communication is breaking down.

    A standard SLT assessment typically includes:

    • Case history — medical background, developmental milestones, family concerns
    • Standardised tests — norm-referenced tools that compare performance to age peers
    • Informal observation — watching the person communicate in natural settings
    • Oral motor examination — checking the structure and function of speech muscles
    • Parent/caregiver interviews — understanding daily communication at home
    • Hearing screening — often conducted in conjunction with SLT assessment

    For adults, assessment also covers reading, writing, and cognitive-communication. For children with autism or Down syndrome, assessments are often multidisciplinary — involving OT, psychologist, and the SLT together.

    The report that follows guides the entire therapy plan. It’s a clinical document, but a good SLT will walk you through it in plain language.

    Want to know more? Get in touch with us.

    What Is The Importance Of Speech And Language Therapy For Learning Disabilities?

    What is the importance of speech and language therapy for learning disabilities?

    Communication is the gateway to almost every other skill. When a person with a learning disability struggles to express needs, follow instructions, or connect socially, it affects education, employment, relationships, and mental health.

    Learning disability speech and language therapy takes a functional approach. The goal isn’t always “correct grammar.” It’s often about giving the person the tools to communicate what they need, when they need it, in the environments that matter most.

    Specific goals in LD-focused SLT:

    • Building vocabulary for daily life and work
    • Developing scripts for common social situations
    • Supporting literacy and numeracy language
    • Teaching self-advocacy language (“I need help with this”)
    • Introducing AAC where verbal communication is limited

    This kind of therapy is also deeply tied to quality of life and independence. When someone can communicate their needs and preferences clearly, they exercise more control over their own life. That’s not a small thing.

    What Makes Speech And Language Therapy Services Effective?

    What makes speech and language therapy services effective?

    Not all SLT is created equal. Evidence points to several factors that consistently determine outcomes:

    FactorWhy It Matters
    Early identificationThe earlier the intervention, the higher the impact
    Therapy intensityMore frequent sessions within a focused period outperform sporadic therapy
    Family involvementCarryover practice at home is critical for generalisation
    Goal specificityVague goals produce vague progress — specific, measurable targets work better
    Therapist expertiseSpecialist experience with the individual’s condition matters
    Multidisciplinary coordinationSLT working alongside OT, psychologist, and educators produces better outcomes
    Environmental supportTeachers, employers, and family members who understand the person’s communication profile help generalise skills

    Families often ask: “How long will my child need therapy?” There’s no universal answer. But generally, the clearer the goals and the more consistent the input, the faster the progress.

    Can Speech Therapy Work Without The Child’s Cooperation?

    Can speech therapy work without the child's cooperation?

    This is a real concern, especially for parents of young children or individuals with significant behavioural challenges.

    Good speech and language therapists are trained to work with resistance. Play-based therapy, child-led sessions, and high-preference activities are all strategies that help. The session doesn’t need to look like a structured lesson to be therapeutic.

    That said, cooperation does improve outcomes. When a child feels safe, understood, and engaged — they learn faster. This is why the relationship between the therapist and the individual matters as much as the technique.

    For adults who are resistant or withdrawn — especially post-stroke — motivational approaches and meaningful, functional goals tend to unlock engagement better than abstract exercises.

    Watch this video on

    https://youtu.be/YU2Qcp2A09M?si=pBH-LYWPK4O_YC3T

    What Should I Look For In A Speech And Language Therapy Programme?

    What should I look for in a speech and language therapy programme?

    If you’re evaluating services — for a child or an adult — here’s what to look for:

    • RCI-registered therapist (in India, the Rehabilitation Council of India is the governing body)
    • Clear assessment before therapy begins
    • Written goals that are reviewed regularly
    • Active involvement of family or caregivers
    • Transparency about progress — you should know if it’s working
    • Coordination with the school, medical team, or other therapists
    • Flexibility to adapt when something isn’t working

    At India Autism Center, our speech and language therapy services are integrated within a multidisciplinary care model. Our therapists work alongside occupational therapists, behaviour analysts, and special educators to ensure every communication goal is connected to real life — not just clinic performance.

    📥 Free download: Printable daily routine chart for autistic children

    Conclusion

    Speech and language therapy works. It works for children and adults. It works across diagnoses — autism, Down syndrome, learning disabilities, stroke, and more. The evidence is strong, and the impact on quality of life is real.

    The biggest barrier isn’t the therapy itself. It’s awareness, access, and the belief that help is available. If you’re asking “does speech therapy work?” — you’re already asking the right question. The next step is finding the right team.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.


    Disclaimer: This article is intended for educational purposes only. The information provided here does not constitute medical or clinical advice and should not be used as a substitute for professional assessment, diagnosis, or treatment. If you have concerns about your child’s or a family member’s communication development, please consult a qualified speech-language pathologist or medical professional.

  • How Genetics and Family Environment Shape Autism Risk

    How Genetics and Family Environment Shape Autism Risk

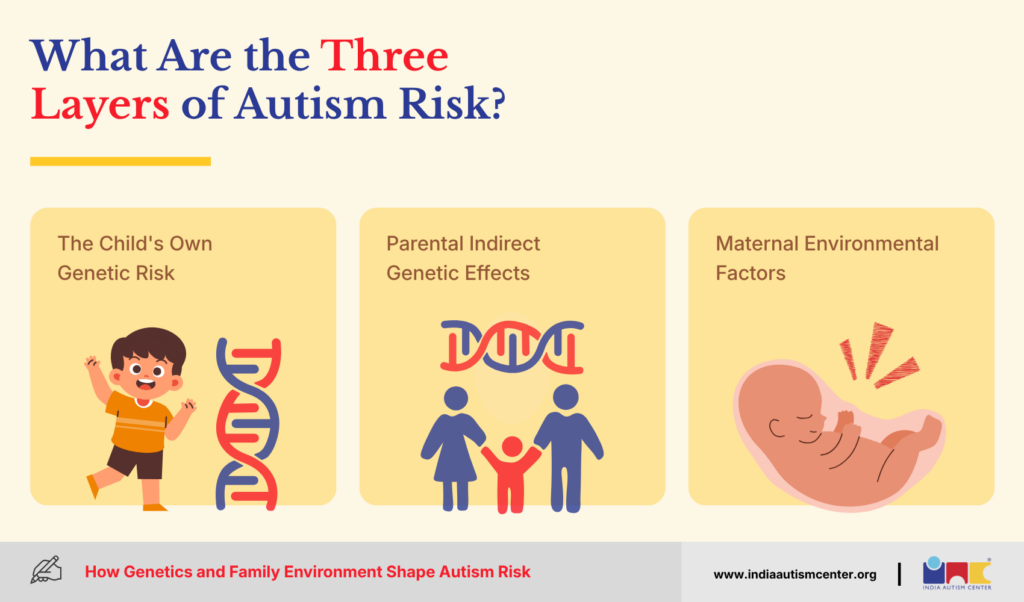
    Is autism genetic? Well, autism risk is shaped by three interlocking forces: a child’s own DNA, the indirect influence of each parent’s genes, and environmental factors like maternal nutrition and metabolic health. No single gene causes autism. A landmark 2026 study published in Nature Genetics — analysing over 18,000 families — has now mapped exactly how these forces work together

    Is Autism Genetic? What the Research Actually Says

    Is Autism Genetic? What the Research Actually Says

    Yes — but not in the way most people imagine.

    Autism is highly heritable, with heritability estimated between 70–90%. That means genetics plays a major role. But heritable does not mean inevitable, and it does not mean a single gene is passed from parent to child like eye colour.

    Autism emerges from a complex interaction between hundreds of genetic variants, each contributing a small amount of risk, and the developmental environment the child grows in — starting from the womb.

    There are three distinct genetic pathways that researchers have identified:

    • De novo variants — new gene mutations that appear in the child but are not present in either parent
    • Inherited variants — gene variants passed down from one or both parents
    • Polygenic risk — the cumulative effect of hundreds of common genetic variants, each with a tiny individual impact

    Most autistic children carry a combination of all three.

    What Is a Polygenic Score — and Why Does It Matter for Autism?

    What Is a Polygenic Score — and Why Does It Matter for Autism?

    A polygenic score (PGS) is a DNA-based calculation that estimates a person’s predisposition to a condition based on how many genetic risk variants they carry. Think of it as a genetic risk calculator — not a diagnosis, but a probability estimate.

    Large-scale studies have developed polygenic scores for autism over the past decade. What was missing, until recently, was a framework that could analyse these scores in the context of families, taking into account not just the child’s DNA, but the mother’s and father’s genetic backgrounds separately.

    That is exactly what the 2026 Johns Hopkins study set out to do.

    Want to know more? Get in touch with us.

    What Did the 2026 Johns Hopkins Study Find?

    What Did the 2026 Johns Hopkins Study Find?

    Researchers at Johns Hopkins Bloomberg School of Public Health, Johns Hopkins University School of Medicine, and Kaiser Permanente Northern California developed a new statistical framework called PGS-TRI, designed specifically for case-parent trio studies.

    A trio study analyses an autistic child and both biological parents together. This design reveals things that standard population studies cannot: specifically, how a parent’s genes shape a child’s risk not through direct inheritance, but through the environment the parent creates.

    The team applied PGS-TRI to 18,383 autism trios drawn from the Simons Foundation Powering Autism Research (SPARK) consortium — one of the largest and most diverse autism genetic datasets in the world.

    Their findings revealed three distinct layers of risk.

    What Are the Three Layers of Autism Risk?

    What Are the Three Layers of Autism Risk?

    Layer 1: The Child’s Own Genetic Risk

    The child’s inherited polygenic score for autism directly increases their probability of diagnosis. This is the most intuitive finding — and it confirms what earlier research had suggested.

    But the child’s autism PGS is only part of the picture.

    Layer 2: Parental Indirect Genetic Effects

    This is the study’s most significant — and most surprising — finding.

    The researchers found that parents’ polygenic scores for BMI and several neurocognitive traits had significant indirect effects on their child’s autism risk. In other words, a parent’s genetic predisposition for high BMI or certain cognitive traits influenced the child’s autism risk — not by passing those genes directly to the child, but by shaping the developmental environment.

    Here is what makes this important: the mother’s and father’s indirect contributions are not equal. PGS-TRI was built to detect this asymmetry. The data suggests that maternal and paternal indirect effects operate through different biological and behavioural pathways.

    📥 Free download: Printable daily routine chart for autistic children

    Notably, the study found no significant indirect effect from the parents’ own autism polygenic score — only from BMI and neurocognitive traits. This tells us that what a parent does developmentally and metabolically may matter as much as what genes they pass on.

    Layer 3: Maternal Environmental Factors

    The framework was also designed to detect gene–environment interactions — specifically how maternal lifestyle factors like diet, weight, and metabolic health interact with a child’s genetic risk.

    This is not about blame. A parent’s BMI or cognitive profile is itself genetically influenced. What it signals is that modifiable factors during pregnancy — nutrition, folic acid supplementation, managing metabolic health — can interact with genetic predispositions in meaningful ways.

    How Do Gene–Environment Interactions Work in Autism?

    How Do Gene–Environment Interactions Work in Autism?

    A gene–environment interaction (G×E) happens when a genetic predisposition expresses differently depending on the environment it encounters.

    A simple way to understand this: imagine two children who carry the same autism polygenic risk score. One grows in a nutrient-rich prenatal environment with no significant stressors. The other is exposed to nutritional deficiencies or high maternal cortisol levels in utero. The genetic risk is identical — but the developmental outcome can differ.

    Known environmental modulators in autism research include:

    Environmental FactorWhat the Research Shows
    Prenatal folic acidAdequate intake linked to reduced neural tube and neurodevelopmental risk
    Maternal BMIHigh pre-pregnancy BMI associated with elevated autism risk in offspring
    Maternal ageAdvanced maternal age correlates with increased de novo mutation rates
    Paternal ageOlder paternal age linked to higher rates of new genetic mutations in children
    Prenatal stressElevated maternal cortisol may alter fetal brain development trajectories
    Infections during pregnancyImmune activation in utero has been studied as a potential risk modulator

    These are modulators, not causes. Autism is not caused by a parent’s diet or stress levels. These factors influence how a genetic predisposition unfolds — nothing more.

    Does Ancestry Affect Genetic Risk Scores for Autism?

    Yes — significantly. And this matters deeply for Indian and South Asian families.

    The study found that existing polygenic risk scores predict autism more accurately in individuals of European ancestry than in other populations. The reason: most large-scale genetic studies that created these scores used predominantly European cohorts. When applied to South Asian or East Asian individuals, the scores lose predictive accuracy.

    The Johns Hopkins team demonstrated that this drop-off is not random — it follows a continuous attenuation pattern based on how genetically distant the target population is from the population the score was trained on.

    What this means for families in India:

    • Consumer genetic tests or research polygenic scores built on European data may underestimate or misrepresent autism risk in Indian children
    • Clinical diagnosis through developmental assessment remains the most reliable approach for Indian families
    • There is an urgent need for South Asian representation in autism genetic databases — studies like these need data from families like yours

    This is a research gap, not a permanent limitation. It will close as diversity in autism datasets grows.

    Want to know more? Get in touch with us.

    What Are the Sibling Recurrence Rates for Autism?

    What Are the Sibling Recurrence Rates for Autism?

    If you have one autistic child, this is almost certainly a question you have asked.

    The research is consistent here. Sibling recurrence rates for autism are meaningfully higher than the general population rate of approximately 1–2%. Studies suggest:

    • Full siblings of an autistic child have roughly a 10–20% recurrence risk
    • Identical (monozygotic) twins: concordance rates of 70–90%
    • Fraternal (dizygotic) twins: concordance rates of 30–40%

    These numbers reflect shared genetics and shared prenatal environment — which is why identical twins, despite identical DNA, do not show 100% concordance. The environment inside the womb still matters.

    If you are planning another pregnancy and have concerns, speaking with a developmental paediatrician or genetic counsellor is the most productive next step.

    Should Families Consider Genetic Testing for Autism?

    Should My Family Consider Genetic Testing for Autism?

    This depends on what you are looking for — and it is worth being honest about what genetic testing can and cannot tell you.

    What genetic testing can identify:

    • Specific high-impact single gene variants associated with autism (e.g., mutations in SHANK3, CHD8, PTEN, MECP2)
    • Chromosomal differences like copy number variations (CNVs)
    • Conditions like Fragile X syndrome or Angelman syndrome where autism is a common feature

    What genetic testing cannot currently do:

    • Confirm or rule out an autism diagnosis
    • Give a reliable polygenic risk probability for most non-European populations
    • Predict severity or trajectory

    Polygenic scores are research tools, not clinical diagnostic instruments. If your child is showing developmental differences, the priority is developmental assessment — not a DNA test.

    What Does This Mean for Parents Right Now?

    What Does This Mean for Parents Right Now?

    Let me be direct about what this research does and does not imply.

    It does not mean:

    • You caused your child’s autism
    • You could have prevented it with a different lifestyle
    • Your child’s autism is a genetic error

    It does mean:

    • Autism risk is multifactorial — genetics, parental biology, and developmental environment all interact
    • Prenatal health — particularly maternal nutrition, folic acid intake, and metabolic health — is worth prioritising in any pregnancy
    • Early identification and structured intervention remain the most evidence-based response, regardless of genetic profile

    The researchers behind the PGS-TRI framework have stated that their goal is to enable better discovery of risk factors and biomarkers — not to predict or prevent autism, but to understand it more completely so that families and clinicians can make better-informed decisions.

    What Is Coming Next in Autism Genetics Research?

    What Is Coming Next in Autism Genetics Research?

    The Johns Hopkins team has outlined several directions for extending this work:

    • Applying PGS-TRI to broader family structures — including grandparents, siblings, and extended relatives — to capture more nuanced patterns of indirect genetic effects
    • Integrating transcriptomics and metabolomics data (gene expression and metabolite profiles) into risk modelling — the 2026 study piloted this approach
    • Building ancestry-diverse datasets so that polygenic scores become equally predictive across all populations

    This is a field moving quickly. The science of autism genetics in 2026 is substantially more nuanced than it was even five years ago — and the direction of travel is clearly toward understanding autism as a deeply individual, multifactorial condition rather than a uniform diagnostic category.

    Want to know more? Get in touch with us.

    Conclusion

    • Autism heritability is 70–90%, but no single gene causes autism
    • Risk comes from the child’s DNA, indirect parental genetic effects, and gene–environment interactions
    • A parent’s BMI and neurocognitive genetic profile can influence a child’s autism risk indirectly — through the developmental environment
    • Maternal lifestyle factors (nutrition, metabolic health) are modulators, not causes
    • Polygenic risk scores are less accurate for non-European populations — Indian families should rely on clinical assessment
    • Sibling recurrence risk is 10–20% for full siblings; family genetic counselling is available and worthwhile
    • Early identification and structured intervention remain the most evidence-based response for any family

    This article is intended for educational purposes only. It does not constitute medical advice, genetic counselling, or a clinical recommendation. If you have concerns about your child’s development or wish to discuss genetic testing, please consult a qualified developmental paediatrician, clinical geneticist, or autism specialist. Families in India can contact India Autism Center for guidance on appropriate assessment and support pathways.


    Source: Wang Z, Grosvenor L, Ray D, et al. “Estimation of Direct and Indirect Polygenic Effects and Gene–Environment Interactions using Polygenic Scores in Case-Parent Trio Studies.” Nature Genetics, June 2026. DOI: 10.1038/s41588-026-02601-2

  • Autism and Aggression: A Calm, Practical Guide for Overwhelmed Parents

    Autism and Aggression: A Calm, Practical Guide for Overwhelmed Parents

    The cup hits the wall. Your child is on the floor, and you’re standing in the doorway, not knowing whether to move toward them or back away. Autism and aggression rank among the hardest things parents navigate together, and most families spend months reacting before they find the root. For the estimated 1.8 to 2 million children with ASD in India, outbursts are often the most distressing challenges their families face, alongside the sensory challenges in autism that often precede them. This guide explains what drives the behaviour, what it is telling you, and where to start.

    What Is the Connection Between Autism and Aggression?

    Connection between autism, communication difficulties, sensory distress, and aggression

    Autism and aggression often occur together because many autistic children cannot yet express pain, fear, or frustration in words. When a child hits, bites, throws, or scratches, they are not being defiant or dangerous. These are common symptoms of aggression that are serving as communication. The child is telling you something they do not yet have the words for. Finding out what that something is makes all the difference.

    Why Does Aggression Happen in Children with Autism?

    Child with autism showing aggression due to sensory overload or communication difficulties

    When a child becomes aggressive, the instinct is to focus on what just happened. Most of the time, the real answer is in what happened before it. Aggression in autistic children almost always traces back to one of two places: sensory overload or the absence of a reliable way to communicate. The challenges in autism linked to sensory overload push the nervous system into fight-or-flight when a transition feels unsafe, or a sound becomes unbearable.

    Sensory Overload and Communication Frustration

    When the nervous system hits its ceiling, physical exit or attack becomes the only available response for a child who has no faster or more reliable signal. A child who hits when a request is ignored is not being defiant. They have run out of options.

    Most families focus on the outburst itself rather than the ten minutes leading up to it. That is where the real trigger almost always lies.

    Medical Pain as a Hidden Trigger

    Medical pain is the most overlooked trigger in autism-related aggression, and the hardest to catch precisely because nonverbal children cannot report it. Chronic gastrointestinal discomfort, untreated ear infections, and dental pain all surface as behavioural distress before they surface as anything else. A paediatric review before any behaviour plan is not optional; it is the first step most families skip.

    Think about a nonverbal 7-year-old whose molar has been aching for six days. He cannot point to his jaw or say it hurts. His sleep has been broken for four nights. By Tuesday afternoon at school, the plate gets thrown, and the teacher logs it as an unprovoked outburst. The dentist appointment three weeks later tells a different story. If you have ever felt like the aggression came out of nowhere, it is worth asking whether your child has had a recent physical check-up.

    Trigger CategoryWhat It Looks LikeWhy It Drives Aggression
    Sensory overloadCovering ears, withdrawing, becoming rigid before the outburstThe nervous system hits a ceiling; physical exit or attack becomes the only available response
    Communication frustrationHitting when a request is ignored or misunderstoodThe child has no faster or more reliable signal available
    Routine disruptionOutbursts at transitions, school pick-up, or unexpected schedule changesPredictability reduces anxiety; its removal triggers acute stress
    Undetected medical painAggression spiking without an obvious behavioural triggerPain cannot be reported verbally and surfaces as distress behaviour
    Demand avoidanceOutbursts in response to direct instructions or requestsThe demand activates a threat response rather than deliberate defiance

    Children who are nonverbal or minimally verbal cannot distinguish between “I am in pain” and “I am overwhelmed” in their own signalling. That gap is where most families lose months. A 2024 comprehensive review published in Cureus noted that 1 in 65 Indian children aged 2 to 9 are affected by ASD, a figure that underscores how many families are navigating this without adequate guidance.

    📥 Free download: Printable daily routine chart for autistic children

    What Do the Symptoms of Aggression in Autism Look Like?

    Common signs and symptoms of aggression in children with autism

    The symptoms of aggression in autism range from hitting, biting, scratching, and throwing objects to self-directed harm such as head-banging. What distinguishes these from tantrums is that they are rarely goal-directed. The child is not trying to get something or manipulate a situation. They are overwhelmed, in pain, or out of options, and the aggression is the only signal available to them.

    How Aggression Differs from a Meltdown

    Aggression during a meltdown is a pressure release, not a tactic. Treating it like one makes every outburst worse.

    The distinction matters because the response that helps in one situation actively escalates the other. During a meltdown, staying quiet and reducing input are what help. During instrumental aggression, neutral redirection works. Confusing the two is one of the most common reasons families feel like nothing is working, no matter how hard they try.

    What It Looks Like in Level 1 and Level 2 Autism

    Children with level 1 autism can show aggression too. It just looks quieter and gets missed because they seem to be communicating fine. A child who storms out of a classroom or slams a door repeatedly is showing symptoms of aggression that often go unaddressed because they are not hitting anyone. Children with level 2 autism tend to show more intense and frequent outbursts, often because communication gaps are wider and sensory thresholds are lower. The intervention approach differs between levels, which is why a one-size strategy rarely holds across both.

    A mother tries a firm “no” the moment her son begins hitting. The hitting escalates. She later recognised it as an autism meltdown that had been building since the car ride home, not a response to what she said.

    FeatureAggressionMeltdown
    IntentMay be directed at a specific person or objectNo specific target; a full release of accumulated overload
    Trigger clarityUsually traceable to a specific denied requestMay appear sudden; builds from accumulated sensory input
    Recovery timeShorter once the trigger is removedLonger; the child needs quiet time and space to regulate
    What helpsNeutral redirection; removing the reinforcing responseReducing all sensory input; calm, wordless presence
    What makes it worseShouting, restraint, or negotiating mid-episodeEye contact, touch, or raising your voice

    A 2024 longitudinal study from the Semel Institute at UCLA, tracking 254 autistic individuals from toddlerhood to adulthood, found that 31% showed persistent aggression across their lifespan while 23% saw it decrease over time, with early intervention as the clearest differentiating factor.

    Want to know more? Get in touch with us.

    What Can Parents Do About Autism Behaviour Issues?

    Parent calmly supporting a distressed child during aggressive behaviour

    Managing autism behaviour issues related to aggression works in three phases: in-the-moment safety, post-episode investigation, and structured replacement. Most families reach the third phase first, which is why the same outburst recurs within days.

    What to Do During an Outburst

    What a parent does in the first thirty seconds of an outburst either shortens it or extends it. Lowering your voice, reducing visual input, and moving toward safety without restraint are the three actions that consistently work across outburst types. Eye contact, physical touch, and verbal explanation during the peak almost always make things worse, regardless of how calmly they are delivered.

    One father tracked his son’s outbursts for two weeks, logging time, location, and what preceded each one. The pattern that surfaced was precise: every incident occurred within twenty minutes of a screen transition, not during the activities his teachers had flagged. Two weeks of data told him more than six months of reacting had.

    Investigation and Structured Replacement

    • Track triggers for 7 days: Log time, location, activity before the outburst, and who was present. Patterns surface faster than most parents expect.
    • Request a Functional Behaviour Assessment (FBA): A Board Certified Behaviour Analyst identifies exactly what function the aggression is serving, which determines the appropriate replacement strategy.
    • Use Functional Communication Training (FCT): Teach one alternative signal, a gesture, a card, or a sound, that gets the child the same result faster than hitting does.
    • Introduce aggression replacement: Aggression replacement training pairs the safe alternative with immediate, consistent reinforcement every single time it is used. The replacement must be quicker and easier than hitting.
    • Rule out physical causes first: If aggression spikes without a clear behavioural trigger, request a paediatric review for gastrointestinal discomfort, dental pain, or ear infection before advancing any behaviour plan.

    The Autism Research Institute’s E-2 database of over 2,300 cases found that 59% of individuals with ASD engage in aggression, self-injury, or destructiveness at some point in their lifetime. That number is not meant to discourage you. It is meant to show that this is not rare, not your fault, and not something families have to figure out alone.

    India Autism Center: Structured Support for Families Navigating Behavioural Challenges

    India Autism Center providing structured behavioural support to a child and family

    Finding the right support when aggression is severe can feel impossible. India Autism Center (IAC) offers structured, long-term residential care for autistic individuals with complex behavioural needs.

    The Samaavesh campus near Kolkata opens in November 2026. Enquire about admission or family support today.

    Conclusion

    Aggression in autism is a signal before it is a problem. Most of what parents experience as a behavioural crisis is a child hitting the limit of their available communication. Once you know what the outburst is doing for your child, the next step gets clearer. Pain points toward a medical review. Demand avoidance points toward communication support. Sensory overload points toward environment changes.

    The question worth sitting with is this: what has your child been trying to say for weeks that no one has been able to hear yet? For a broader view of strategies, see our guide to managing autistic behaviour.

    Figuring out triggers, coordinating professionals, and staying calm through repeated outbursts takes a toll that most parents carry quietly. You do not have to work this out from scratch on your own.

    Frequently Asked Questions

    Is aggression a symptom of autism?

    Autism and aggression often co-occur, but aggression is not a core diagnostic feature of ASD, and the symptoms of aggression vary widely between children. A 2024 longitudinal study from UCLA tracking 254 individuals found aggression peaks at school age, with 69% of participants showing it between ages 6 and 12, making it the most critical window for early structured intervention.

    What triggers aggression in children with autism?

    Sensory overload, routine disruption, and communication frustration are the most common triggers, with the BC Medical Journal estimating aggression prevalence in ASD at 25% to 68% depending on the population studied. Anticipatory anxiety builds across hours: a schedule change announced at breakfast can surface as an outburst at lunch. Trigger logs that cover the full day, not just the thirty minutes before an incident, catch patterns most parents miss.

    How do I stop my autistic child from hitting?

    Identifying what the child was trying to communicate matters more than stopping the hitting in the moment. Board Certified Behaviour Analysts use Functional Communication Training (FCT) to teach a specific alternative, such as tapping an arm or handing over a PECS card, that yields the same result faster than hitting. Most families see a measurable reduction in hitting within 8 to 12 weeks of consistent FCT application.

    What is aggression replacement training?

    Aggression replacement training (ART) teaches autistic children a safer alternative that serves the same function as hitting, whether that is escaping a demand, signalling pain, or gaining attention. Reinforcement must happen every time the alternative is used. Without that consistency across all caregivers and settings, the safer behaviour will not hold.

    Does aggression in autism get better with age?

    Aggression in autism can decrease with age, but improvement is not automatic. A 2024 UCLA longitudinal study tracking 254 autistic individuals found 23% saw aggression decrease over time, with fewer repetitive behaviours and early structured intervention as the strongest predictors. For 31%, aggression remained persistent without dedicated support.

    Disclaimer: This article is intended for educational and informational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. If you are pregnant or have concerns about medication use during pregnancy, please consult a qualified healthcare provider. If your child has received an autism diagnosis and you have questions about causes or support, please reach out to a trained specialist or an autism-focused organisation for guidance.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

  • Aggressive Behavior in Autism: What Every Parent Needs to Know

    Aggressive Behavior in Autism: What Every Parent Needs to Know

    If you’re reading this, chances are you’ve been hit, kicked, bitten, or screamed at by your own child — and you didn’t know what to do. Maybe you cried afterward or felt guilty for getting frustrated. Maybe you Googled “why does my autistic child get aggressive suddenly” at midnight, desperate for something — anything — that would help.

    I want you to know: you are not a bad parent. And your child is not a bad kid.

    Aggressive behavior in autism is one of the most exhausting, heartbreaking, and misunderstood challenges that autism families face. It affects an estimated 25–30% of autistic children at some point, and for many families, it’s the number one reason they seek help.

    This guide is written for you — the parent who is in the thick of it. I’m going to walk you through what’s actually happening when your child lashes out, what’s causing it, and most importantly, what you can do about it in a way that actually works.

    Have a look at What Is Autism? Signs, Causes & Truths Explained Simply 

    What Is Aggressive Behavior in Autism? 

    What Is Aggressive Behavior in Autism? 

    When we talk about aggressive behaviour in autism, we’re talking about a wide range of behaviors that can include:

    • Hitting, slapping, or punching (often directed at parents or caregivers)
    • Biting — themselves or others
    • Kicking, scratching, or pulling hair
    • Throwing objects
    • Head-banging or other forms of self-injury
    • Screaming or extreme emotional outbursts

    Here’s the most important thing I want you to hold onto as you read this: aggression in autism is almost always a form of communication. Your child isn’t hitting you because they’re mean or manipulative. They are overwhelmed, in pain, frustrated, or terrified — and they don’t have the words or the tools to tell you that.

    Think of it this way: if you were locked in a room where everything was too loud, too bright, and too overwhelming, and nobody understood what you were saying, you might start acting out, too.

    This doesn’t mean the behavior is okay or that you just accept it. But understanding the why behind the behavior is the very first step toward actually changing it.

    Who does autism aggression affect?

    Autism aggression can happen at any age — it’s common in young children, but it can persist into the teen years and even adulthood if not properly addressed. It can affect autistic individuals at every level of the spectrum, but it tends to be more frequent and intense in children who have limited verbal communication.

    Autism Meltdowns vs. Tantrums — What’s the Difference?

    Autism Meltdowns vs. Tantrums — What's the Difference?

    One of the most common mistakes parents and even professionals make is treating a meltdown like a tantrum. These are two completely different things, and responding to them the same way can actually make things worse.

    MeltdownTantrum
    What it isA neurological response to overwhelming sensory or emotional inputGoal-directed behavior to get something or avoid something
    Is the child in control?No — they’ve lost controlSomewhat — they’re aware of what they’re doing
    Does it stop when they get what they want?NoOften yes
    What triggers it?Sensory overload, anxiety, communication breakdownBeing told “no,” not getting a preferred item, transitions
    How long does it last?Can last minutes to over an hourUsually shorter once need is met
    What helps?Reduce stimulation, wait it out, stay calmSet clear boundaries, do not give in to demands
    What makes it worse?Trying to reason, punishing, high-stimulation responsesGiving in every time, escalating conflict

    A meltdown is not manipulation. Your child is not “doing this for attention.” During a meltdown, their nervous system has completely overloaded — it’s closer to a panic attack than a deliberate choice. Punishing them for it doesn’t work because they aren’t in a state where learning can happen.

    A tantrum, on the other hand, does involve some degree of awareness. A child having a tantrum might sneak glances at you to see your reaction. They may stop the moment they get what they want.

    Knowing which one you’re dealing with changes everything about how you respond. Read Autism Meltdown in Different Age Groups.

    What Causes Aggression in Autism? 

    What Causes Aggression in Autism? 

    There is no single answer to the question of what causes aggression in autism — it’s usually a combination of factors. Here are the most common ones:

    Sensory Overload

    Many autistic individuals experience sensory input very differently from neurotypical people. Sounds that seem normal to you — a crowded mall, a TV in the background, fluorescent lights humming — can feel like physical pain to them. When the sensory world becomes too much, aggression can be the result of complete overwhelm.

    Communication Frustration

    This is huge, especially in younger children and those with limited verbal speech. Imagine desperately needing something — to be left alone, to have the TV turned off, to have a specific toy — and not being able to say so. You’ve tried to communicate in every way you know how, and nobody is understanding you. That kind of frustration can quickly boil over into physical behavior.

    For nonverbal or minimally verbal autistic children, hitting and biting are often the most “effective” communication tools they have — because they get an immediate response.

    📥 Free download: Printable daily routine chart for autistic children

    Anxiety and Fear

    Autism and anxiety often go hand-in-hand. In fact, up to 40–50% of autistic individuals also have an anxiety disorder. When an autistic child feels unsafe, unsure, or threatened — even by something that seems small to you, like a change in routine — the fight-or-flight response can kick in. Aggression is sometimes literally the body’s fear response.

    Disruption to Routine

    Many autistic children rely heavily on routine and predictability. When something unexpected happens — the usual route to school is different, a parent is late, a planned activity gets cancelled — it can trigger intense distress that comes out as aggression.

    Unmet Physical Needs

    This one is often overlooked. A child who is hungry, tired, or in physical pain is far more likely to be aggressive. Autistic children often have difficulty identifying and communicating internal body states (a condition called interoception differences). So instead of saying “my tummy hurts,” they might just explode.

    Hidden medical causes like ear infections, gastrointestinal pain, headaches, or dental pain are a surprisingly common driver of sudden aggression in autistic children who can’t verbally explain what’s wrong.

    Emotional Dysregulation

    Many autistic individuals have difficulty regulating their emotions. They can go from calm to completely overwhelmed very quickly, with little awareness of how or why. They may not yet have the emotional toolkit to manage big feelings — and aggression is what happens when those feelings have nowhere else to go.

    Common Autism Aggression Triggers — And How to Spot Them

    Common Autism Aggression Triggers — And How to Spot Them

    Understanding autism aggression triggers is one of the most powerful things you can do as a parent. Because if you can predict when a meltdown is coming, you can often prevent it — or at least reduce its intensity.

    Every autistic child is different, but here are the most common triggers I hear parents describe:

    Sensory triggers:

    • Loud or sudden noises (fireworks, alarm bells, other children screaming)
    • Crowded or busy environments
    • Certain textures of clothing, food, or objects
    • Bright or flickering lights
    • Strong smells

    Routine and transition triggers:

    • Unexpected changes to the schedule
    • Transitions between activities (especially stopping a preferred activity)
    • New environments or unfamiliar situations
    • Arrival of visitors or changes in who’s present at home

    Communication triggers:

    • Being unable to express a need or want
    • Not being understood
    • Being asked to do something they don’t understand

    Internal triggers:

    • Hunger or thirst
    • Fatigue
    • Illness or pain
    • Anxiety about an upcoming event

    How to track your child’s triggers

    One of the best tools available to you is the ABC chart — short for Antecedent, Behavior, Consequence. For every aggressive episode, jot down:

    • A (Antecedent): What happened right before the behavior? Where were they? Who was there? What time was it?
    • B (Behavior): What exactly did they do?
    • C (Consequence): What happened after? What did you do? Did the behavior stop? Did they get what they seemed to want?

    After a week or two of tracking, patterns start to emerge. You might notice that most aggressive incidents happen right before dinner (hunger), during transitions from screen time, or in specific environments. That information is gold.

    How to Handle an Aggressive Autistic Child: Step-by-Step 

    How to Handle an Aggressive Autistic Child: Step-by-Step

    When aggression is happening in the moment, most of us react on instinct — and our instincts aren’t always helpful. Here’s a calmer, more effective approach:

    Step 1: Keep yourself calm first

    I know this is the last thing you want to hear when your child has just bitten your arm. But your nervous system directly influences your child’s nervous system. If you escalate, they escalate. Slow, deep breaths. Lower your voice. Soften your posture. You are the regulation they can’t find in themselves right now.

    Step 2: Ensure physical safety

    Move dangerous objects out of reach. If your child is hitting, create physical distance without escalating. If there are other children present, remove them from the area calmly.

    Step 3: Reduce stimulation immediately

    Turn off the TV. Dim the lights if you can. Reduce noise. Move to a quieter space if possible. You’re trying to reduce the input their nervous system is trying to process.

    Step 4: Use minimal language

    During a meltdown or aggressive episode, your child’s brain is not in a state to process complex language. Don’t lecture or explain consequences. Don’t ask “why did you do that?” Keep it to one or two words maximum: “Safe now.” “It’s okay.” Or nothing at all.

    Step 5: Give them space

    This doesn’t mean abandonment — it means not hovering over them or demanding eye contact or compliance. Sit nearby, stay present and calm, and let the storm pass.

    What NOT to do:

    • Don’t punish them during a meltdown. It doesn’t teach anything and increases distress.
    • Don’t physically restrain unless absolutely necessary for safety. Physical restraint can be traumatic.
    • Don’t match their emotional energy. Yelling back, crying, or threatening escalates the situation.
    • Don’t take it personally in the moment. I know that’s hard. But this is not about you.
    https://youtu.be/smKWM9ItC-0?si=iqmIjBbowv0-n9D9

    How to Calm an Autistic Meltdown in the Moment

    How to Calm an Autistic Meltdown in the Moment

    Once you’ve followed the steps above, here are specific things that can help your child come back to a regulated state:

    Sensory tools that help many children:

    • Weighted blanket or lap pad (the deep pressure is calming)
    • Noise-cancelling headphones
    • A favorite comfort object or fidget tool
    • A cool cloth on the face or back of the neck
    • Gentle, rhythmic movement (rocking, swinging)

    Environmental adjustments:

    • A designated “calm-down corner” in your home — a low-stimulation space with soft lighting, sensory tools, and a few comfort items. This is not a punishment space. It’s a safe haven they can learn to use proactively.

    What to say (and how to say it):

    • Speak slowly and quietly
    • Use your child’s name calmly at the start
    • Acknowledge their feelings without interrogating: “You’re really upset. I’m right here.”
    • Avoid questions during the peak of the meltdown

    Wait it out. The hardest part of calming an autistic meltdown is that you can’t rush it. The brain needs time to come back down from that level of activation. Trying to force the process — demanding they stop, removing privileges, applying consequences in the moment — extends it.

    After the meltdown has passed and your child is calm — this is when reconnection and gentle conversation can happen, if they’re ready for it.

    Here is a detailed blog on How to Handle Autism Meltdown: Complete Guide for Parents and Caregivers 

    How to Stop Hitting in Autism: Long-Term Strategies 

    How to Stop Hitting in Autism: Long-Term Strategies 

    In-the-moment management is only half the picture. The longer-term goal is to reduce the frequency and intensity of aggressive behavior over time. Here’s what actually works:

    Teach an alternative communication method

    If hitting is being used to communicate “stop,” “I need help,” “I’m overwhelmed,” or “I want that” — you need to give your child another way to say those things.

    This might look like:

    • Picture Exchange Communication System (PECS): Using picture cards to communicate
    • Augmentative and Alternative Communication (AAC) devices: Tablet-based apps like Proloquo2Go
    • Sign language: Even a few basic signs (more, stop, help, no) can dramatically reduce frustration-based aggression
    • Visual cues: Emotion cards or “first-then” boards

    The research is clear: teaching communication reduces aggression. These aren’t workarounds — they’re powerful, evidence-based tools.

    Functional Behavior Assessment (FBA)

    An FBA is a formal process where a specialist (usually a Board Certified Behavior Analyst, or BCBA) figures out the function of the aggressive behavior — what need it is serving. Is it to escape a task? To get attention? To get a preferred item? To communicate sensory discomfort?

    Once you know the function, you can address it directly rather than just trying to suppress the behavior.

    Evidence-based therapies

    Applied Behavior Analysis (ABA): When delivered ethically and with your child’s wellbeing at the center, ABA therapy  can be highly effective at reducing aggressive behavior and teaching replacement behaviors. Look for providers who take a neurodiversity-affirming, naturalistic approach.

    Positive Behavior Support (PBS): A framework that focuses on understanding behavior, reducing triggers, and teaching new skills — without punishment-based strategies.

    Occupational Therapy (OT): Particularly effective when sensory processing is a major driver of aggression. An Occupational Therapy can develop a “sensory diet” — a personalized plan of sensory activities that help regulate your child’s nervous system throughout the day.

    Speech-Language Therapy: Essential for children whose aggression is rooted in communication frustration. And this why we have A Comprehensive Guide to Speech and Language Therapy for Autism 

    Teach replacement behaviors

    Instead of just trying to eliminate hitting, explicitly teach what to do instead. Practice saying “stop” or handing over a “break” card. Role-play scenarios when your child is calm. Reinforce the replacement behavior consistently and enthusiastically.

    Autism Behavior Management at Home: Daily Strategies 

    Autism Behavior Management at Home: Daily Strategies 

    The home environment is where you have the most control — and that’s actually great news. Here are day-to-day strategies that make a real difference:

    Build predictable routines

    Predictability is genuinely calming for the autistic brain. A consistent daily schedule — wake up, breakfast, activities, meals, wind-down, bed — reduces anxiety and therefore reduces the likelihood of aggressive outbursts.

    When you know a disruption is coming (a doctor’s appointment, a trip, a visitor), prepare your child in advance. Talk about it. Show them a picture schedule of what’s happening. Give them as much notice as possible.

    Use visual schedules

    Words are harder to process than visuals for many autistic children — especially when emotions are already elevated. A simple visual schedule (pictures or symbols showing the sequence of the day) gives your child a way to know what’s coming without relying on you to constantly explain.

    Social stories

    Social stories are short, simple narratives that walk your child through a situation they find challenging — from their perspective. You can create one for almost anything: “When I feel angry, I can go to my calm corner.” “When it’s time to turn off the TV, I can give my tablet to Mum.” These aren’t magic, but used consistently they build new neural pathways.

    Create a calm-down corner

    Set up a small space in your home — a corner of their room, under the stairs, anywhere quiet — with items that help your child self-regulate. Think: soft cushions, sensory toys, headphones, a lava lamp, weighted blanket. Make it a positive place they want to go, not a punishment room.

    Positive reinforcement

    Catch your child being calm, cooperative, or using their words (or AAC device) — and make a big deal of it. Specific, enthusiastic praise (“I love how you used your words to tell me you needed a break!”) reinforces the behaviors you want to see more of.

    Token boards and reward systems can work well for some children — they provide visible, predictable reinforcement for positive behavior.

    Proactive sensory strategies

    Don’t wait for your child to become overwhelmed — build sensory breaks into their day before they need them. This might mean 10 minutes of jumping on a trampoline before homework, a fidget toy available during meals, or noise-canceling headphones for the school run.

    Managing Aggression in Non-verbal Autistic Children 

    Managing Aggression in Non-verbal Autistic Children 

    Nonverbal autism aggression deserves its own section, because the dynamics are somewhat different — and the stakes feel higher.

    When a child has very limited verbal communication, aggression often becomes their most effective communication tool. If hitting makes you leave the room when they need alone time, or makes you give them the toy they want, or makes you turn off the overwhelming TV — then from their perspective, hitting works.

    This is not manipulation in the way we typically think of it. It’s a child doing the best they can with the tools they have. Your job — with professional support — is to give them better tools.

    What helps most for nonverbal children

    Prioritize communication above everything else. This is the single most impactful thing you can do. Work with a speech-language pathologist to find the right AAC system for your child. Research consistently shows that robust communication support reduces aggressive behavior — often dramatically.

    Become a body language expert. Before your child reaches the point of aggression, there are usually early warning signs — if you know what to look for. Learn your child’s individual signs of rising distress: increased stimming, avoiding eye contact, tensing up, pulling at clothes, becoming very still, a particular sound or expression. These are your windows for early intervention.

    Use visual supports everywhere. “First-then” boards, choice boards, emotion charts, and picture schedules can give nonverbal children a way to navigate their world with more autonomy and less frustration.

    Reduce demands when they’re already at the edge. If you can tell your child is getting close to their limit, it’s not the time to push through homework or practice transitions. Strategic retreating is not giving in — it’s smart parenting.

    Strategies for Aggressive Behavior in Autistic Adults

    Strategies for Aggressive Behavior in Autistic Adults

    Aggression doesn’t automatically resolve when an autistic child becomes an adult — and for families still supporting adult autistic children at home, this can be an incredibly isolating experience.

    Aggression in autistic adults often looks different from childhood aggression. It may be less frequent but more physically significant. It may be triggered by workplace stress, relationship difficulties, or the ongoing exhaustion of navigating a neurotypical world.

    What helps for autistic adults:

    Emotional regulation support: Adapted DBT (Dialectical Behavior Therapy) and CBT for autism can help autistic adults build emotional regulation skills. Look for therapists with experience in autism — not just anxiety or depression.

    Sensory accommodations: Adults still have sensory needs. Noise-cancelling headphones at work, control over lighting at home, the ability to take sensory breaks — these aren’t accommodations to be ashamed of. They’re necessary for wellbeing.

    Communication support: Some autistic adults who can speak find that their verbal communication breaks down under stress. Having a written or AAC-based backup can prevent communication-related frustration from boiling over.

    Addressing the underlying cause: Very often, aggression in autistic adults is a sign that something is seriously wrong — they’re being pushed past their limits at work, dealing with an unaddressed mental health condition, or in an environment that isn’t meeting their needs. The aggression is the symptom. Find the cause.

    Psychiatric evaluation: For some autistic adults, co-occurring conditions like ADHD, OCD, anxiety, or depression significantly contribute to aggression. Medication, when appropriate and carefully managed, can make a real difference — but it should always be part of a broader support plan, not the only intervention.

    https://youtu.be/9Ds1HolJ5Wk?si=tzDhsnEGM2g4aa__

    When to Seek Professional Help

    There’s no shame in needing a team. In fact, managing significant autism aggression at home without any professional support is extremely hard, and it’s not what you should be expected to do alone.

    Seek professional help when:

    • The aggression is frequent (multiple times per week or daily)
    • Someone is getting hurt — your child, you, or siblings
    • You’ve tried behavior strategies consistently and they’re not helping
    • The aggression is getting more intense over time
    • Your child seems to be in pain, or aggression is sudden and unexplained (rule out a medical cause first)
    • Your mental health or the family’s wellbeing is significantly impacted

    Who to contact:

    • Pediatrician or GP: Start here. Rule out medical causes for a sudden increase in aggression (ear infections, constipation, GI issues, dental pain). Also discuss referrals.
    • Board Certified Behavior Analyst (BCBA): For a Functional Behavior Assessment and behavior support plan.
    • Occupational Therapist (OT): For sensory-based strategies and a sensory diet.
    • Speech-Language Pathologist (SLP): For AAC and communication-based intervention.
    • Child Psychiatrist or Psychologist: For co-occurring anxiety, ADHD, or other conditions that may be driving aggression.

      Watch what experts say about Autism aggression:Why Aggression Happens in Autism and What Actually Helps | India Autism Center

    📥 Free download: Printable daily routine chart for autistic children

    Conclusion

    Living with autism aggression is hard in a way that’s difficult to put into words. On the days when you’ve been hurt, or you’ve watched your child suffer through a meltdown, or you’ve had to cancel another outing because you didn’t know what might trigger an episode — it can feel impossibly lonely.

    But I want you to hear this: things can get better. With the right support, the right strategies, and the right team around your family, aggressive behaviour in autism can improve — often dramatically. Your child is not broken. They are communicating the only way they know how right now. Your job isn’t to fix them. It’s to understand them and to build a bridge.

    You are already doing that — just by being here and reading this far.

    If this article helped you, share it with another autism parent who might need it. And if you’d like support tailored to your child’s specific needs, please reach out to your local autism support organisation or speak to your pediatrician about a referral.

    Frequently Asked Questions

    Why does my autistic child hit me and not other people?

    This is actually a sign of attachment and trust. Your child hits you because you are safe. They know you won’t abandon them, won’t hurt them back, and will still love them. It doesn’t make it okay, but it means something important about your relationship.

    Is aggression more common in boys with autism?

    Studies do show higher rates of externalised aggression in autistic boys, while autistic girls tend to internalise distress. However, aggression can occur in autistic children of any gender.

    My autistic child was calm for months and suddenly became aggressive. Why?

    Sudden-onset aggression in a child who was previously calm is a red flag for an unaddressed medical issue — particularly pain. Rule out ear infections, constipation, dental pain, and gastrointestinal issues first. A change in environment, school stress, or puberty can also be triggers.

    Can aggression in autism be cured?

    “Cured” isn’t quite the right word — but aggression can absolutely improve significantly with the right support, communication tools, and environmental adjustments. Many children who were significantly aggressive at age 4 are living calm, connected lives by their teens with proper intervention.

    Should I call the police if my child is being aggressive?

    This is a deeply difficult question. Most autism parents exhaust every other option first — and rightfully so, because police involvement can be traumatic and dangerous for autistic individuals. If you are genuinely in danger, call for help. But also speak to your child’s BCBA or psychiatrist about a safety plan for severe episodes before they happen, so you have a protocol ready.

    At what age does autism aggression typically peak?

    For many children, aggression peaks in the early to middle childhood years (ages 4–10) and often reduces with proper intervention and as communication skills grow. However, puberty can bring a new wave of challenging behavior for some families.

    Is it okay to walk away during a meltdown?

    If you need a moment to regulate yourself, stepping away briefly — while ensuring your child is physically safe — is okay. You cannot help your child if you’re completely dysregulated yourself.


    This article is for informational purposes only and is not a substitute for professional medical, psychological, or behavioural advice. If your child is experiencing significant aggressive behavior, please consult a qualified professional.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

  • How to Join an NGO Without Experience: Step-by-Step Guide (2026)

    How to Join an NGO Without Experience: Step-by-Step Guide (2026)

    Let me be honest with you.

    When people first decide that they want to work for an NGO, they are excited, motivated, and completely clueless. They have a degree, a burning desire to “do something meaningful,” and zero experience in the development sector. Every job posting they opened asked for “2+ years of field experience” or a “background in humanitarian work.” Many don’t have any of that.

    And if you’re reading this, I’m guessing you’re in a similar spot.

    Here’s the good news: you don’t need years of experience to start your NGO journey. What you need is the right strategy, a little patience, and the willingness to show up. In this guide, I’m going to walk you through exactly how to break into the NGO sector — step by step — even if you’re starting from zero.

    What is an NGO, and why is it Different from a Regular Job?

    What is an NGO and Why is it Different from a Regular Job?

    Before we talk about how to join one, let’s quickly understand what an NGO actually is — because “NGO” is a broad term that means different things in different contexts.

    An NGO (Non-Governmental Organisation) is a non-profit organisation that operates independently of the government. Its goal is to address social, environmental, humanitarian, or developmental issues. NGOs are funded through donations, grants, and sometimes government partnerships — but they aren’t government bodies themselves.

    There are different types of NGOs you might want to work with:

    • Local/grassroots NGOs — small organisations working within a specific community or city (like an NGO in Kolkata working on child education)
    • National NGOs — organisations working across a country (like Pratham or Goonj in India)
    • International NGOs (INGOs) — global organisations like Oxfam, Save the Children, or Médecins Sans Frontières
    • UN Agencies — like UNICEF, UNDP, or WHO (technically intergovernmental, but many entry-level roles exist here too)

    NGO roles span a wide range: program delivery, field work, communications, fundraising, research, monitoring & evaluation (M&E), grant writing, finance, and administration. There’s genuinely a place for almost every skill set.

    Why NGOs Don’t Always Need “Experienced” Candidates

    Why NGOs Don't Always Need "Experienced" Candidates

    Here’s something most job seekers get wrong: NGOs say they want experience, but what they really want is commitment.

    In corporate jobs, experience signals competence. In the NGO sector, experience signals something deeper — that you understand the reality of working in challenging conditions, that you’re not going to quit after three months, and that you genuinely care about the cause.

    But here’s the thing: you can demonstrate all of those things without prior NGO experience.

    Many entry-level NGO roles — especially volunteering positions, internships, and fellowship programs — are specifically designed for people without formal experience. Organisations like UN Volunteers, AmeriCorps, and hundreds of local Indian NGOs actively recruit fresh graduates and career changers.

    What they’re looking for isn’t a resume full of NGO stamps. They’re looking for:

    • Genuine passion for the cause
    • Transferable skills (communication, data, project management, writing)
    • Flexibility and adaptability
    • A growth mindset and willingness to learn

    So if you’re sitting there thinking “I have nothing to offer” — stop. You likely have more than you think.

    7 Proven Ways to Join an NGO Without Experience

    7 Proven Ways to Join an NGO Without Experience

    This is the core of what I want to share with you. These are real, actionable pathways — not vague advice like “follow your passion.”

    1. Start as a Volunteer

    Volunteering is the single fastest way to get your foot in the door. Almost every NGO has volunteer programs, and most of them require nothing more than willingness and reliability.

    When I say volunteering, I don’t mean just weekend clean-up drives. I mean structured, skill-based volunteering where you contribute meaningfully:

    • Help an NGO manage their social media
    • Assist with data collection or field surveys
    • Support their event planning or fundraising drives
    • Teach a skill (English, computers, art) in their programs

    Not only does this give you experience to put on your resume, but it also gets you inside the organisation. You build relationships, understand how the sector works, and often get first notice when paid positions open up.

    Where to find volunteering opportunities:

    • Volunteering India (volunteeringindia.com)
    • iVolunteer (ivolunteer.in)
    • United Way India
    • Your city’s local NGO directories
    • Google: “volunteer with NGO in [your city]”

    2. Apply for Internships

    NGO internships are one of the best-kept secrets for career switchers and fresh graduates. Many of them are paid (especially at larger national and international organisations), and they are explicitly designed for people with little to no prior experience.

    Internships give you:

    • Real work experience with a legitimate organisation
    • A professional reference (huge for future applications)
    • Clarity on whether NGO work is actually right for you
    • A direct line to full-time hiring

    Where to find NGO internship:

    • India Autism Center – one of the best NGOs in Neurodivergent sector
    • Idealist.org — one of the best global platforms
    • DevNetJobs.org — focused on development sector roles
    • NGO Jobs India
    • LinkedIn — search “NGO intern” or “non-profit intern”
    • Organisation websites directly (check their “Careers” or “Get Involved” pages)

    Pro tip: Don’t wait for internship listings to appear. Send a direct email to organisations you admire, expressing your interest and attaching a short proposal on how you can help. NGOs often create opportunities for motivated people who reach out.

    3. Leverage Your Transferable Skills

    This one changed the way I looked at my own resume.

    You don’t need NGO experience to be valuable to an NGO. You need skills — and skills transfer across industries. Here’s how to map what you already know:

    Your BackgroundTransferable NGO Skill
    Marketing / Social MediaCommunications, digital outreach, fundraising
    Teaching / TrainingCapacity building, field education programs
    Data Analysis / ExcelM&E (Monitoring & Evaluation), impact reporting
    Finance / AccountingGrant management, budgeting
    Writing / JournalismGrant writing, reports, donor communications
    IT / TechDatabase management, digital tools for development
    HealthcareCommunity health programs, public health initiatives
    LawHuman rights, legal aid programs

    Look at your existing skills and ask: “How would an NGO use this?” Then write your resume and cover letter through that lens.

    4. Build a Cause-Specific Portfolio

    If you don’t have NGO experience, create it yourself. A portfolio of cause-related work is surprisingly powerful — especially for roles in communications, research, or program design.

    Here are practical ways to build one:

    • Start a blog or newsletter about issues you care about (child rights, climate change, women’s empowerment)
    • Create social media content advocating for a cause and build a small, engaged following
    • Write research summaries or policy briefs on development issues
    • Organise a community initiative — even something small like a local food drive or awareness campaign
    • Contribute to open-source development projects that support social causes

    When you apply to an NGO, you’ll be able to show — not just tell — that you care. That makes a massive difference.

    5. Take Relevant Online Courses and Certifications

    This one is simple, affordable, and often underused. There are excellent courses available — many of them free or low-cost — that give you foundational knowledge in the development sector.

    Courses worth exploring:

    • Coursera / edX: Search for courses on “International Development,” “Public Health,” “Human Rights,” “Sustainable Development Goals (SDGs)”
    • NPTEL (for Indian learners): Development economics, social policy
    • UN SDG Academy: Free online learning on global development
    • UNHCR’s Learning Hub: Refugee and humanitarian response training
    • Google.org Skills: Digital skills for the social sector

    Even completing one or two relevant courses shows initiative. List them on your LinkedIn and resume under “Certifications” — they signal that you’re investing in this career switch seriously.

    6. Network Inside the Sector

    I’ll be direct: the NGO world is relationship-driven. A lot of hiring happens through word of mouth, referrals, and internal networks. If you’re only applying cold through job portals, you’re fighting the hardest battle.

    Here’s how to network effectively:

    • LinkedIn: Follow NGOs you admire, engage with their posts, connect with program officers and HR managers
    • Attend events: Webinars, panel discussions, development conferences, TEDx talks — show up and introduce yourself
    • Info interviews: Reach out to people working in NGOs and ask for a 20-minute call to learn about their journey. Most people are happy to help — and these conversations often lead somewhere unexpected
    • Join sector communities: Facebook groups, WhatsApp communities, Reddit threads focused on non-profit work
    • Alumni networks: Your college alumni working in NGOs are your warmest possible introduction

    Don’t network just to “get a job.” Network to genuinely learn, build relationships, and contribute. The opportunities follow naturally.

    7. Apply for Fellowship Programs

    Fellowship programs are structured, time-bound experiences designed specifically to bring talented people into the social sector — often without prior NGO experience required.

    Fellowships worth researching (India & Global):

    • Teach For India Fellowship — education-focused, 2-year teaching fellowship
    • Gandhi Fellowship — rural education and community leadership
    • Acumen India Fellowship — social entrepreneurship and leadership
    • Atlas Corps — international NGO placement fellowship
    • Echidna Global Scholars — girls’ education focus
    • LAMP Fellowship (India) — legislative research and public policy
    • UN Young Professionals Programme (YPP) — entry into the UN system

    Most fellowships come with a stipend, training, and mentorship. They’re an excellent launchpad — and they look exceptional on your resume.

    How to Write an NGO Resume When You Have No Experience

    How to Write an NGO Resume When You Have No Experience

    Your resume is your first impression. In the NGO sector, a resume isn’t just a career document — it’s a statement of values. Here’s how to write one that works:

    1. Start with a strong objective/summary Lead with 2–3 lines that communicate your motivation and what you bring. Example:

    “A communications professional with 3 years of digital marketing experience, transitioning into the development sector with a focus on women’s empowerment and community engagement. Passionate about using storytelling for social impact.”

    2. Reframe your experience using impact language Even if your jobs weren’t NGO-related, describe them in terms of outcomes and people impacted.

    3. Highlight volunteering and community work Don’t bury it at the bottom. If your NGO-relevant experience is volunteering, make it prominent.

    4. Add a skills section List both hard skills (Excel, research, social media, content writing) and soft skills (communication, adaptability, cross-cultural sensitivity).

    5. Tailor every application Read the organisation’s mission carefully. Mirror their language. Show that you understand their specific work — not just “NGOs in general.”

    Crafting a Cover Letter That Actually Gets Read

    Crafting a Cover Letter That Actually Gets Read

    In corporate hiring, cover letters are often skimmed or ignored. In the NGO sector, they matter a lot.

    NGO hiring managers want to know why you care — and a well-written cover letter is your chance to show them.

    Structure your cover letter like this:

    Paragraph 1 — Hook with your ‘why’ Tell them why this specific organisation and cause matters to you. Make it personal. Be specific.

    Paragraph 2 — Show you understand their work Mention a specific program, initiative, or impact report you’ve read. Demonstrate that you’ve done your homework.

    Paragraph 3 — Connect your skills and experience Explain clearly what you bring to the table and how your background maps to their needs.

    Paragraph 4 — Close with intent Express your enthusiasm, mention you’d love to discuss further, and include a clear call to action.

    Mistakes to avoid:

    • Starting with “I am writing to apply for…” (boring, skip it)
    • Copy-pasting the same letter to multiple organisations
    • Focusing only on what you want to gain, rather than what you’ll contribute
    • Using corporate jargon (“synergize,” “leverage bandwidth”) — keep it warm and human

    Where to Find NGO Job Opportunities

    Where to Find NGO Job Opportunities

    Here’s a consolidated list of the best places to look:

    Job Boards:

    Other Channels:

    • LinkedIn — follow NGOs, set job alerts, use keywords like “program associate,” “social sector,” “development sector fresher”
    • Organisation websites — bookmark and check “Careers” pages of your target organisations regularly
    • Facebook groups — search “NGO jobs India,” “development sector jobs,” “social sector careers”
    • WhatsApp groups — many sector-specific networks share openings informally

    How to Ace the NGO Interview

    How to Ace the NGO Interview

    Getting the interview is half the battle. Here’s how to make it count.

    Before the interview:

    • Read everything on their website — mission, programs, annual reports, recent news
    • Understand their “theory of change” (how they believe their work creates impact)
    • Research the sector they work in so you can speak knowledgeably

    Common NGO interview questions — and how to think about them:

    • “Why do you want to work in the development sector?” — Be honest and specific. Avoid generic answers like “I want to make a difference.” Talk about a real moment or experience that shaped your interest.
    • “What do you know about our organisation?” — This is a test of preparation. Have 2–3 specific things ready about their programs, geography, or recent impact.
    • “How would you handle working in a resource-constrained environment?” — They want to know you can be creative, flexible, and resilient. Give a real example if you can.
    • “Do you have experience with [specific skill — e.g., M&E, grant writing]?” — If not, don’t bluff. Be honest, express your eagerness to learn, and mention any adjacent experience or courses.

    Questions you should ask them:

    • “What does success look like in this role in the first 6 months?”
    • “What are the biggest challenges your team is currently navigating?”
    • “How does the organisation support the professional development of new team members?”

    Asking good questions signals genuine interest and maturity.

    Frequently Asked Questions

    Can I join an NGO without a degree?

    Yes. Many NGOs — especially at the grassroots level — hire based on skills, experience, and commitment rather than formal qualifications. Volunteering, certifications, and demonstrated passion can outweigh a degree in many cases.

    Do NGOs pay their workers?

    Yes, NGOs do pay salaries — they are not entirely run by volunteers. However, compensation is generally lower than the corporate sector, especially at entry level. International NGOs and UN agencies tend to offer more competitive packages.

    How do I find NGOs near me?

    Search “[your city] NGO list” or check your state’s NGO directory. In India, you can also explore the NITI Aayog NGO Darpan portal (ngodarpan.gov.in), which lists thousands of registered NGOs across the country

    What skills do NGOs look for?

    Communication, research, project management, data analysis, community engagement, grant writing, and digital skills are highly valued. Beyond technical skills, NGOs look for empathy, cultural sensitivity, adaptability, and a genuine commitment to the cause.

    Is volunteering the only way to enter an NGO?

    No. Volunteering is one of the easiest entry points, but internships, fellowships, direct applications for junior roles, and networking are all valid paths. Many people enter through lateral moves from related fields like public health, education, or government.

    Can I join an international NGO without experience?

    It’s harder, but not impossible. UN Volunteers, the UN Young Professionals Programme, and international fellowship programs like Atlas Corps are specifically designed to bring in candidates with limited formal experience. Start with these, build your experience, and move up from there.

    Conclusion

    I want to leave you with this: the NGO sector needs people like you.

    It needs people who bring fresh perspectives, cross-sector skills, and genuine motivation. The world’s most pressing problems — poverty, inequality, climate change, displacement — aren’t going to be solved by people who already have all the answers. They’ll be solved by people who are willing to show up, learn, and contribute.

    You don’t need a perfect resume. You need a clear starting point.

    So here’s your action step for this week: pick one thing from this list and do it. Apply for a volunteering role. Sign up for an online course. Send one networking message on LinkedIn. Reach out to a local NGO.

    Every career in the development sector started with one small step. Yours starts now.


    Found this guide helpful? Share it with someone who’s looking to make the switch into the social sector. And if you have questions, drop them in the comments — I read every one.

  • Autism in Twins: What Every Parent Needs to Know

    Autism in Twins: What Every Parent Needs to Know

    If you’re a parent of twins and autism has entered your world — whether through a recent diagnosis, a nagging worry, or a question your paediatrician raised — I want you to know something first: you are not alone, and you are asking exactly the right questions.

    Twin studies have shaped nearly everything we know about autism. For decades, researchers have looked at twins to understand why autism happens, how much of it is genetic, and what it means when one twin is diagnosed. The answers are nuanced, sometimes surprising, and — most importantly — genuinely useful for parents like us.

    In this article, we are going to walk you through what the science actually says, in plain language. No jargon, no scary statistics without context. Just the honest, evidence-based information you need to understand your children and support them well.

    What Is Autism, and Why Do Twin Studies Matter?

    What Is Autism, and Why Do Twin Studies Matter

    Autism Spectrum Disorder (ASD) is a neurodevelopmental condition that affects how a person communicates, socialises, and experiences the world. The word “spectrum” is key — autism looks very different from one person to the next. Some autistic individuals are highly verbal and academically gifted; others may have significant support needs. Many fall somewhere in between.

    According to the CDC, about 1 in 36 children in the United States is diagnosed with ASD. Globally, the World Health Organisation estimates 1 in 100 children is on the spectrum, though rates vary by country and diagnostic criteria.

    So why are twins so central to autism research?

    Because twins give scientists a rare natural experiment. When researchers study twins — especially identical ones who share the same DNA — they can start to separate what’s caused by genes from what’s caused by environment. If autism were purely genetic, identical twins would always both be autistic. If it were purely environmental, the rates would look similar in identical and fraternal twins. The truth, as we’ll see, is somewhere more interesting than either extreme.

    Identical Twins vs. Fraternal Twins: What’s the Difference?

    Identical Twins vs. Fraternal Twins: What's the Difference?

    Before we get into the research, it helps to understand the two types of twins and why scientists treat them differently.

    Identical twins (monozygotic, or MZ) come from a single fertilised egg that splits into two. This means they share virtually 100% of their DNA. They are always the same sex, and they often look strikingly similar.

    Fraternal twins (dizygotic, or DZ) come from two separate eggs fertilised by two separate sperm. They share roughly 50% of their DNA — the same as any two siblings. They can be the same sex or different sexes, and they may or may not look alike.

    This genetic difference is exactly why researchers love studying both types together. By comparing how often autism appears in identical versus fraternal twin pairs, scientists can get a clearer picture of just how much genetics is driving the condition.

    📥 Free download: Printable daily routine chart for autistic children

    What Does the Research Actually Tell Us?

    Here is where things get genuinely fascinating — and reassuring in some ways, and sobering in others.

    The Concordance Rate: What It Means for Your Family

    In research, the word “concordance” simply means both twins sharing the same trait or diagnosis. A concordance rate of 100% would mean that if one identical twin has autism, the other always does too. A rate of 0% would mean it never happens.

    The numbers from decades of twin studies are striking:

    • In identical (MZ) twins, the concordance rate for autism is roughly 60–90%. Some studies put it even higher when they include the broader autism phenotype — meaning milder autistic traits that don’t meet the full diagnostic threshold.
    • In fraternal (DZ) twins, the concordance rate is significantly lower, around 10–40%.

    For comparison, the general population rate is about 2–3%. So even being a fraternal twin of an autistic child raises the chances meaningfully.

    The gap between those two numbers — 60–90% versus 10–40% — is what tells us genetics is playing a major role. But notice that even in identical twins, concordance isn’t 100%. If autism were entirely down to genes, identical twins would always share the diagnosis. The fact that they don’t tells us something equally important: environment, and other biological factors, matter too.

    Want to know more? Get in touch with us.

    Is Autism Genetic? Understanding Heritability

    Is Autism Genetic? Understanding Heritability

    One of the most common questions parents ask is: “Did I pass this on to my child?”

    It’s an emotionally loaded question, and it deserves an honest answer.

    Autism is one of the most heritable neurodevelopmental conditions we know of. Heritability estimates from twin studies typically range from 64% to 91%. That means somewhere between 64 and 91 cents of every metaphorical dollar of autism risk comes from genetic factors.

    But here’s what heritability does not mean: it doesn’t mean autism is caused by a single “autism gene” that parents pass down. It doesn’t mean you did something wrong. And it doesn’t mean the outcome is fixed.

    Autism is polygenic — meaning hundreds, possibly thousands, of genes are each contributing a tiny bit of risk. Some of these variants are inherited; others arise as new mutations (called de novo mutations) that weren’t present in either parent. This is why autism can appear in a family with no prior history of it, and why siblings of autistic children have elevated risk even when parents are neurotypical.

    What about the environment?

    Environmental factors also play a real role — and this is important for parents to understand, because it is not about anything you did or didn’t do during pregnancy.

    Research has linked a higher likelihood of autism to factors including:

    • Advanced parental age (particularly paternal age over 40)
    • Premature birth and low birth weight
    • Prenatal exposure to certain medications (notably valproate, used for epilepsy)
    • Complications during labour and delivery

    None of these is a guarantee, and none of them is anyone’s fault. They are risk factors in a statistical sense — they shift probabilities slightly, they don’t determine outcomes. Most children exposed to these factors are not autistic, and most autistic children were not exposed to them.

    The Epigenetics Piece: Why Identical Twins Can Be Different

    Here’s something that surprises many parents: identical twins can have the same DNA and still have very different experiences of autism, or one can be autistic while the other is not.

    How is that possible?

    The answer lies in epigenetics — the study of how genes are switched on or off by biological and environmental influences. Even though identical twins start with the same genetic code, over time, their gene expression can diverge. Different experiences in the womb (one twin may receive slightly more nutrients or be in a different position), different immune responses, different early-life exposures — all of these can change how genes are expressed without changing the underlying DNA sequence.

    This is actually a hopeful finding, in a way. It tells us that genes are not destiny. The environment — including early intervention, therapy, and support — can genuinely make a difference.

    If One of My Twins Has Autism, What Are the Chances for My Other Twin?

    If One of My Twins Has Autism, What Are the Chances for My Other Twin

    This is the question most parents come here to answer, and I want to give you the clearest possible picture.

    Twin TypeRisk if the Other Twin Has Autism
    Identical (MZ)Approximately 60–96%
    Fraternal (DZ)Approximately 20–40%
    Non-twin siblingApproximately 10–20%
    General populationApproximately 2–3%

    A few things worth noting:

    Severity can differ significantly. Even when both twins in an identical pair are autistic, they may present very differently. One might be minimally verbal with high support needs; the other might be highly verbal with milder challenges. Same genes, different expression.

    The broader autism phenotype matters. In many cases where one twin is autistic and the other isn’t formally diagnosed, the undiagnosed twin still shows some subclinical autistic traits — slightly different social communication patterns, particular sensory preferences, narrow interests. Researchers call this the “broader autism phenotype” (BAP). It’s not autism, but it’s a sign the genes are present even if the full condition isn’t expressed.

    What should you do with this information? If one of your twins has been diagnosed, I’d strongly recommend asking your paediatrician about developmental monitoring for the other twin, even if they seem to be developing typically. The earlier a diagnosis is made, the earlier support can begin — and early intervention has consistently been shown to make a meaningful difference.


    Diagnosing Autism in Twins: The Unique Challenges

    Diagnosing Autism in Twins

    Diagnosing autism in twins comes with a set of challenges that many parents and even some clinicians don’t anticipate.

    The Masking Problem

    When one twin is clearly autistic, attention often focuses on that child. The other twin may actually be masking autistic traits — subconsciously learning to imitate their twin’s social behaviour or compensating with their own strategies. This is especially common in girls, who tend to mask more effectively than boys regardless of whether they have a twin.

    The “Speaking For” Dynamic

    Twin pairs often develop tight communication shortcuts. The more verbally fluent twin may answer questions for both, fill in silences, or guide their co-twin through social situations. In a diagnostic assessment, this can make the quieter twin appear more socially capable than they actually are without their twin present.

    What Good Assessment Looks Like

    A thorough evaluation should assess each twin independently — in separate rooms, with separate sessions. The gold standard tools are:

    • ADOS-2 (Autism Diagnostic Observation Schedule) — a structured observation
    • ADI-R (Autism Diagnostic Interview – Revised) — a detailed parent interview
    • M-CHAT-R/F — a screening tool used in toddlers (18–30 months)

    If you feel that your concerns about the second twin aren’t being taken seriously because “we already assessed the other one and they’re fine,” advocate clearly. Each child deserves their own thorough evaluation.

    📥 Free download: Printable daily routine chart for autistic children

    Supporting Your Twins: Practical Guidance for Parents

    Supporting Your Twins: Practical Guidance for Parents

    Learning that one or both of your twins is autistic doesn’t change who your children are. It changes what you now know about them, and it opens the door to support that is genuinely life-changing when started early and sustained consistently.

    Treat Each Twin as an Individual

    This might seem obvious, but it’s easy to fall into patterns where twins are treated as a unit — same school, same class, same therapy group. In families with autism in the mix, this needs careful thought. Each child’s needs are different. Each child’s pace of development is their own.

    Create space for each twin to have their own relationships with you, their own achievements, and their own identity outside of being “the twins.”

    Therapies and Interventions That Help

    The most effective approaches are individualised — designed around each child’s specific profile of strengths and challenges. Depending on your child’s needs, these may include:

    • Speech and language therapy — for communication development, whether verbal or AAC (augmentative and alternative communication)
    • Occupational therapy (OT) — for sensory processing, fine motor skills, and daily living skills
    • Applied Behaviour Analysis (ABA) — structured skill-building; look for providers who take a naturalistic, child-led approach
    • Social skills groups — for children who want to build peer connections
    • Parent-mediated approaches — programmes like JASPER, ESDM, and Hanen that train you to support your child in everyday interactions

    None of these are one-size-fits-all. A good therapist will regularly review progress and adjust the approach.

    Don’t Forget the Neurotypical Twin

    If one of your twins is autistic and the other is not, the neurotypical child has their own emotional journey to navigate. They may feel overlooked when their sibling needs more attention. They may feel confused about why their twin is different and may internalise worry or feel pressure to compensate.

    Acknowledge their feelings directly. Keep some time that is just for them. Consider sibling support groups, many of which are offered by autism organisations and are specifically designed for brothers and sisters of autistic children.

    School Placement: Together or Apart?

    This is one of the most common questions twin parents ask, and there’s no universal right answer.

    Some twins thrive in the same classroom — the familiar presence of their sibling is regulating and comforting. Others do better in separate classes, where the autistic child can receive more targeted support without being compared to their twin, and where both children have the chance to build their own friendships independently.

    Talk openly with your school’s SENCO (Special Educational Needs Coordinator) or equivalent, consider your children’s individual preferences, and revisit the decision each year — what’s right at age five may not be right at age nine.

    Look After Yourself Too

    Parenting twins is demanding under the best of circumstances. Add an autism diagnosis — or two — and the weight can feel immense. The research is detailed that parental well-being directly affects child outcomes. This isn’t a guilt trip; it’s a reason to prioritise your own support.

    Seek out parent support groups (online and in-person), be honest with your GP about how you’re coping, and remember that asking for help is one of the best things you can do for your children.

    https://youtu.be/yr1zmIysrmM?si=uGMrn0WCBox9fDWy

    Conclusion

    If there’s one thing I hope you take from this article, it’s this: autism in twins is not a mystery beyond your understanding, and it is not outside your ability to respond to meaningfully.

    The science tells us that genetics matters enormously — but it is not destiny. Epigenetics, environment, early intervention, and the quality of daily support all make a real difference to how autistic children develop and thrive.

    If one of your twins has been diagnosed, get the other assessed. If both have been diagnosed, seek individualised support for each. And through all of it, take care of yourself — because your children need you at your best, not just your most exhausted.

    You are already doing the most important thing: you are trying to understand.

    Frequently Asked Questions

    Are twins more likely to have autism than singletons?

    Some research suggests a modest increase in autism rates among twins compared to singletons, though findings have been mixed. What is well-established is that twins are more likely than the general population to have a co-twin with autism if they are an identical twin of an autistic child.

    Can twins have completely different levels of autism?

    Yes, absolutely. Even identical twins with shared DNA can present very differently. One might need significant daily support while the other needs minimal accommodations. Autism is a spectrum, and gene expression varies even between genetically identical individuals.

    Is autism caused by genetics or the environment?

    Both play a role. Genetics accounts for roughly 64–91% of autism risk based on twin studies. Environmental factors — including prenatal exposures, birth complications, and parental age — contribute the remainder. Neither is “the cause” on its own; it’s an interaction.

    At what age should I screen my twin for autism if the other has already been diagnosed?

    As soon as possible. Screening tools like the M-CHAT-R/F are used from 18 months. If your other twin is already past that age and hasn’t been evaluated, speak to your paediatrician about a formal developmental assessment. Don’t wait for obvious signs — many children on the spectrum don’t show clear signs until 2–3 years of age, and some not until school age.

    Do identical twins always share an autism diagnosis?

    No. The concordance rate for identical twins is high (60–96%) but not 100%. Epigenetic differences, in-womb environmental variations, and other biological factors mean that one identical twin can be autistic while the other is not.


    Disclaimer: This article is intended for educational and informational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. If you are pregnant or have concerns about medication use during pregnancy, please consult a qualified healthcare provider. If your child has received an autism diagnosis and you have questions about causes or support, please reach out to a trained specialist or an autism-focused organisation for guidance.

    This article is for informational purposes only and does not constitute medical advice. If you have concerns about your child’s development, please consult a qualified healthcare professional.