Category: Understanding Autism

  • Autism Therapies: Guide to Treatment, Technique and More

    Autism Therapies: Guide to Treatment, Technique and More

    Autism therapies are structured, evidence-based interventions designed to support individuals on the autism spectrum in developing communication, social, behavioural, sensory and daily living skills. No single therapy works for everyone; rather, a personalised combination of approaches tends to produce the most meaningful outcomes.

    Autism therapies form the cornerstone of support for individuals diagnosed with Autism Spectrum Disorder (ASD). Whether a child is newly diagnosed or an adult has been living with autism for decades, the right therapy — or combination of therapies — can significantly improve quality of life, independence, and the ability to connect with others.

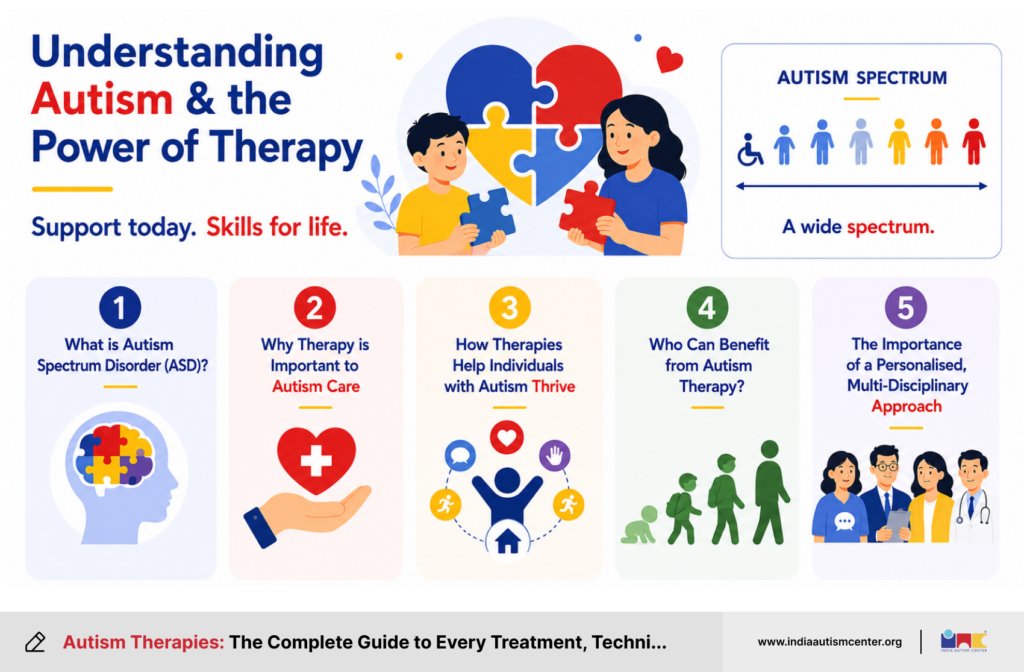
    What is Autism Spectrum Disorder (ASD)?
    understanding-autism_and_the_power_of_therapy

    Autism Spectrum Disorder is a neurodevelopmental condition that affects how a person communicates, interacts socially, processes sensory information, and regulates behaviour and emotion. The word “spectrum” is key: autism presents differently in every individual, ranging from those who are non-verbal and require significant support to those who are highly verbal and largely independent but struggle with social nuance or sensory sensitivities. Because of this wide spectrum, autism therapies must be equally diverse and adaptable.

    Why Therapy is Important to Autism Care

    Unlike many medical conditions, autism does not have a pharmaceutical cure. Instead, therapy is the primary tool used to help individuals develop skills they find challenging and manage difficulties that affect their daily lives. Therapy does not aim to “fix” or change a person’s fundamental identity. Rather, it equips individuals with strategies, skills, and tools so that they can navigate the world more comfortably and communicate their needs more effectively.

    How Therapies Help Individuals with Autism Thrive

    Autism therapies address a broad range of areas, including language and communication, emotional regulation, sensory processing, motor skills, social interaction, and adaptive daily living skills. When delivered consistently and tailored to the individual’s profile, therapies can lead to measurable improvements in functioning, confidence, and overall well-being. Over time, therapeutic gains often extend beyond the clinic — into the home, school, and community.

    Who Can Benefit from Autism Therapy?

    Autism therapies benefit individuals across all age groups and ability levels. Young children benefit enormously from early intervention programmes that target foundational communication and social skills during the most developmentally receptive years of the brain. School-age children benefit from therapies that support academic participation, peer relationships and self-regulation. Adolescents and adults benefit from therapies focused on independence, vocational skills, emotional wellbeing, and community integration. In short, there is no age at which therapy becomes irrelevant.

    The Importance of a Personalised, Multi-Disciplinary Approach

    No two individuals with autism are alike, and therefore no single therapy suits everyone. The most effective approach is one that is tailored to the individual’s unique profile — their strengths, challenges, learning style, sensory needs, and family context. A multi-disciplinary team, which may include a speech-language therapist, occupational therapist, behaviour analyst, psychologist, and paediatrician, works collaboratively to design and review an integrated therapy plan. This coordinated approach ensures that all areas of development are addressed in a cohesive and complementary manner.

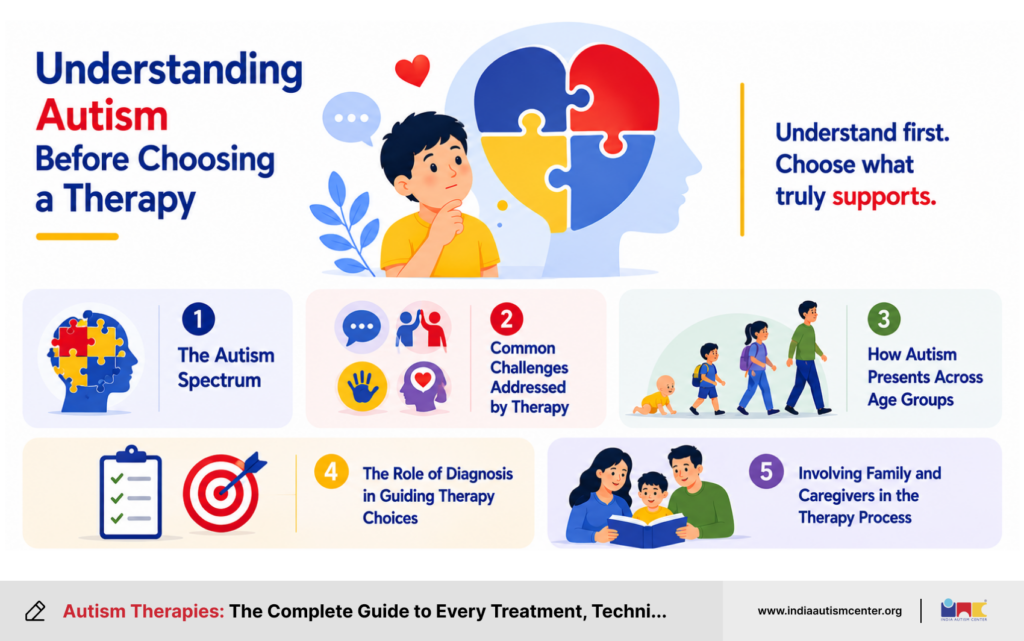
    Understanding Autism Before Choosing a Therapy
    Understanding Autism Before Choosing a Therapy

    Before selecting an autism therapy, it is essential to understand how autism presents in the individual. Autism affects communication, social interaction, sensory processing, behaviour, and motor skills — but the degree and combination of these challenges varies widely. A thorough diagnostic assessment helps identify which areas need the most support and which therapies are best matched to the individual’s profile.

    Selecting the right autism therapy is not a one-size-fits-all process. Understanding the specific ways in which autism affects the individual is the necessary first step. This section outlines the core areas that autism therapies are designed to address and the importance of working from a well-informed foundation.

    The Autism Spectrum: What It Means and Why It Matters for Treatment

    The term “spectrum” reflects the enormous variability in how autism presents. Some individuals experience profound challenges across communication, behaviour and sensory processing, while others display highly specific difficulties, such as social anxiety, sensory sensitivity or rigid thinking patterns. Treatment must be matched to the individual’s actual profile — not to a generalised idea of what autism looks like. This is why a detailed diagnostic assessment, conducted by a qualified professional, is always the starting point.

    Common Challenges Addressed by Therapy

    • Communication and Language Deficits: Many individuals with autism experience difficulties with both verbal and non-verbal communication. Some are non-verbal or minimally verbal, relying on gestures, pictures, or communication devices. Others speak fluently but struggle with pragmatic language — the social rules of conversation, such as turn-taking, topic maintenance, or understanding sarcasm. Speech and language therapy specifically targets these areas.
    • Social Skills and Interaction: Difficulties with social interaction are a defining characteristic of autism. Individuals may find it hard to initiate conversations, read facial expressions, understand unspoken social rules, or make and maintain friendships. Therapies such as social skills groups, play therapy, and Applied Behavior Analysis (ABA) target these challenges directly.
    • Sensory Processing Differences: Many individuals with autism are hypersensitive (over-responsive) or hyposensitive (under-responsive) to sensory input — including touch, sound, light, taste, smell, and movement. These sensory differences can make everyday environments overwhelming or disorienting. Sensory integration therapy and occupational therapy address these needs directly.
    • Behavioural and Emotional Regulation: Challenging behaviours — such as meltdowns, self-injurious behaviour, aggression, or extreme rigidity — are often the result of unmet communication needs, sensory overload, anxiety, or an inability to regulate overwhelming emotions. ABA, Cognitive Behavioral Therapy (CBT), and sensory therapies all contribute to improving emotional and behavioural regulation.
    • Motor and Coordination Issues: Many individuals with autism also experience motor difficulties, including poor fine motor control (affecting writing and self-care), gross motor challenges (affecting balance, gait, and coordination), and low muscle tone. Occupational therapy and physical therapy address these motor needs.
    • Cognitive and Learning Differences: Autism is often accompanied by differences in learning style, attention, executive functioning, and memory. Some individuals have exceptional abilities in specific areas, while others have co-occurring intellectual disabilities. Therapies that incorporate visual supports, structured routines, and step-by-step instruction help bridge cognitive differences.

    How Autism Presents Differently Across Age Groups

    Autism looks different at different life stages. During infancy and toddlerhood, early signs may include a lack of eye contact, delayed babbling, or reduced response to one’s name. In school-age children, difficulties with peer relationships, rigid adherence to routines, and sensory sensitivities often become more prominent. In adolescence, social complexity increases and mental health challenges such as anxiety and depression frequently emerge. And in adulthood, challenges around independent living, employment, and relationships come to the fore. Therapy must be responsive to these changing developmental demands.

    Read our article on Autism Getting Worse With Age? The Truth No One Tells You 

    The Role of Diagnosis in Guiding Therapy Choices

    A formal diagnosis of autism, made by a qualified clinical team, provides the foundation for all subsequent therapy decisions. The diagnostic process typically includes detailed developmental history, standardised assessments, direct observation, and input from parents and educators. The results identify not only that autism is present, but also the individual’s cognitive level, language profile, adaptive functioning, and co-occurring conditions — all of which directly inform which therapies should be prioritised.

    Involving Family and Caregivers in the Therapy Process

    Family involvement is one of the strongest predictors of positive therapy outcomes. Parents and caregivers who understand the principles behind therapy are far better equipped to reinforce skills at home, respond to challenging behaviours effectively, and advocate for their child’s needs in educational and community settings. Most evidence-based autism therapies actively involve family training as a core component of the intervention.

    The Importance of Early Intervention Therapy for Autism
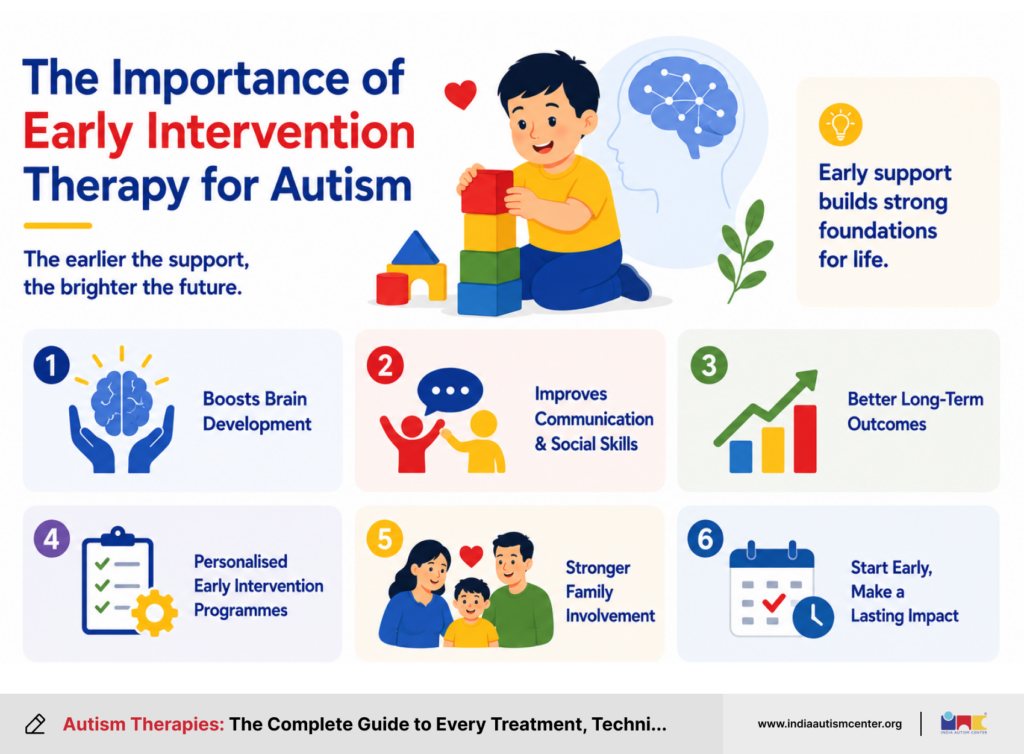
    Importance of Early Intervention Therapy for Autism

    Early intervention for autism refers to structured therapeutic support provided to children, ideally before the age of five, during the most critical window of brain development. Research consistently shows that children who receive intensive, targeted therapy in the early years achieve significantly better outcomes in communication, social skills, and adaptive behaviour than those who begin later.

    What is Early Intervention?

    Early intervention refers to a range of therapeutic programmes and support services delivered to young children — typically between birth and five years of age — who show signs of developmental delay or have received a confirmed autism diagnosis. The goal is to target developmental challenges during the period when the brain is most adaptable, responsive and capable of forming new neural pathways. Early intervention for autism typically encompasses ABA, speech and language therapy, occupational therapy and developmental play-based approaches.

    The Science Behind Early Brain Plasticity

    The concept underpinning early intervention is neuroplasticity — the brain’s remarkable ability to reorganise and form new connections in response to experience and learning. This capacity is at its peak in the early years of life. During this window, the brain is uniquely receptive to learning new skills, forming communication pathways, and developing social understanding. Neuroscience research confirms that the earlier a therapeutic intervention begins, the greater the potential for reshaping developmental trajectories and establishing foundational skills.

    When Should Therapy Begin?

    Therapy can and should begin as soon as concerns about development are identified — even before a formal diagnosis is confirmed. In many countries, children can access early intervention services based on developmental delay alone, without waiting for a definitive autism diagnosis. The general consensus among clinicians and researchers is that the most significant improvements are seen when intervention begins before the age of three. However, it is equally important to note that meaningful progress is possible at any age and that it is never “too late” to begin therapy.

    Types of Early Intervention Programmes

    Several structured early intervention programmes have been developed specifically for young children with autism. The Early Start Denver Model (ESDM) integrates ABA principles with developmental and relationship-based strategies in a play-based format. The LEAP (Learning Experiences and Alternative Programme for Preschoolers) model emphasises inclusive peer interactions. Hanen’s “More Than Words” programme equips parents with the skills to support their child’s communication development at home. Each of these approaches shares a common emphasis on communication, social engagement, and learning through positive interaction.

    Outcomes and Long-Term Benefits of Starting Early

    Children who receive intensive early intervention therapy for autism frequently demonstrate improvements across multiple domains: greater gains in language development, improved social communication, higher adaptive behaviour scores, reduced severity of autism symptoms, and improved cognitive functioning. Many children who receive high-quality early intervention are subsequently able to participate in mainstream education with fewer additional supports. Over the long term, early gains in communication and social skills also contribute to better mental health outcomes in adolescence and adulthood.

    For a deep dive into this topic, refer to our blog on The Role of Early Intervention in Autism Spectrum Disorder. 

    Signs That Your Child May Need Therapy

    Key early signs that may warrant a therapy referral include: not babbling or pointing by 12 months, not using single words by 16 months, not using two-word phrases by 24 months, a loss of previously acquired language or social skills, limited or absent eye contact, lack of response to their name, and very limited pretend play. If any of these signs are present, a referral to a developmental paediatrician, speech-language therapist or early intervention service should be sought without delay.

    How to Get an Early Intervention Assessment

    Parents who are concerned about their child’s development should begin by speaking to their GP or paediatrician. In many countries, early intervention assessments are available through public health services, developmental paediatric clinics, or specialist autism assessment centres. The assessment typically involves a multi-disciplinary team and results in a profile of the child’s strengths and needs, alongside a tailored early intervention plan. Private assessment pathways are also available for families who wish to access services more quickly.

    Detailed blog on Early Intervention for Autism: A Parent’s Guide to Better Outcomes 

    Overview of All Autism Therapy Types
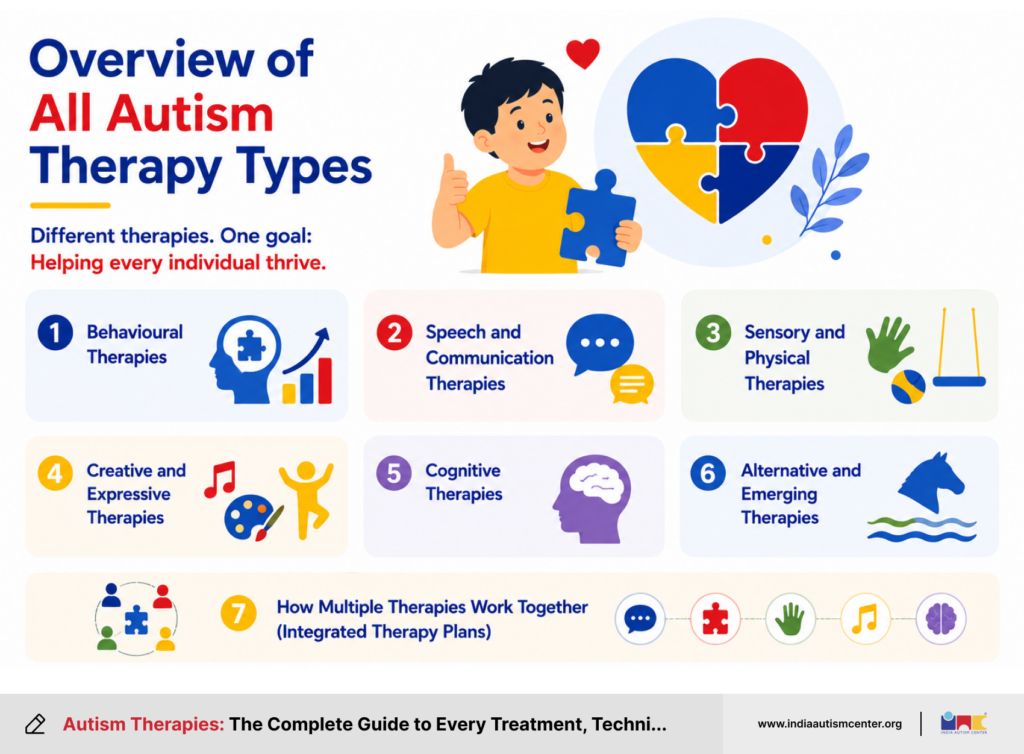
    Overview of All Autism Therapy Types

    Autism therapies can be grouped into five broad categories: behavioural therapies (such as ABA), communication therapies (such as speech and language therapy), sensory and physical therapies (such as occupational therapy and sensory integration therapy), creative and expressive therapies (such as music, dance and art therapy), and cognitive therapies (such as CBT). Most individuals benefit from a combination of therapies drawn from more than one of these categories.

    Understanding the landscape of autism therapies before exploring each one in depth helps families and individuals approach decision-making with clarity and confidence. The following overview introduces each category and explains why an integrated approach is generally considered the gold standard.

    Behavioural Therapies

    Behavioural therapies focus on understanding and modifying behaviour by systematically applying learning principles. Applied Behaviour Analysis (ABA) is the most widely researched and implemented behavioural therapy for autism. These therapies analyse the relationship between the environment and behaviour, then use structured strategies to increase helpful behaviours and reduce those that interfere with learning or safety.

    Speech and Communication Therapies

    Speech and language therapy addresses the full range of communication challenges associated with autism — from pre-verbal communication and early language development to complex pragmatic and social communication skills. This category also includes the use of Augmentative and Alternative Communication (AAC) systems for non-verbal or minimally verbal individuals.

    Here is  A Comprehensive Guide to Speech and Language Therapy for Autism 

    Sensory and Physical Therapies

    Sensory and physical therapies address how the body receives, processes, and responds to sensory information, as well as motor and physical functioning. Occupational therapy, sensory integration therapy, and physical therapy all fall within this category. These therapies play a critical role in supporting daily living skills, sensory regulation, and physical development.

    Creative and Expressive Therapies

    Creative therapies harness the power of non-verbal, expressive modalities — music, movement, art, drama, and water — to reach individuals with autism in ways that traditional talk-based therapies may not. These approaches are particularly valuable for individuals who find verbal communication challenging and for those who respond strongly to sensory-based or creative experiences.

    Cognitive Therapies

    Cognitive therapies, most notably Cognitive Behavioural Therapy (CBT), target the relationship between thoughts, feelings and behaviours. These therapies are typically most suitable for individuals who are higher-functioning and have sufficient verbal and cognitive skills to engage with structured self-reflection and problem-solving.

    Alternative and Emerging Therapies

    In addition to the well-established approaches above, a number of alternative and emerging therapies are used in autism care. These include aquatic therapy, equine-assisted therapy, and neurofeedback. While the evidence base for some of these approaches is still developing, many families report meaningful benefits, and they may serve as valuable complements to core therapies.

    How Multiple Therapies Work Together (Integrated Therapy Plans)

    The most effective autism therapy programmes draw on multiple approaches simultaneously, with all therapists working towards a shared set of goals. For example, a child’s speech therapy goals around requesting may be reinforced within ABA sessions; sensory strategies from occupational therapy may be embedded into the home environment; and music therapy may provide a motivating context for practising turn-taking and communication. An integrated therapy plan, coordinated by the family and the multi-disciplinary team, ensures coherence, avoids contradiction, and maximises the transfer of skills across settings.

    Want to know more? Get in touch with us.

    Applied Behaviour Analysis (ABA) Therapy for Autism

    Applied Behaviour Analysis (ABA) Therapy for Autism

    ABA therapy for autism is a structured, evidence-based intervention that applies the science of behaviour and learning to increase useful skills and reduce harmful or disruptive behaviours. It is widely considered the most extensively researched autism therapy available and is recommended by numerous clinical and governmental bodies worldwide.

    What is ABA Therapy for Autism?

    Applied Behaviour Analysis (ABA) is a therapy grounded in the scientific study of behaviour and learning. It operates on the principle that behaviour is learned and influenced by the environment. By systematically modifying environmental factors and using positive reinforcement, ABA therapy helps individuals with autism learn new skills, build on existing strengths, and reduce behaviours that interfere with learning or daily functioning. ABA is not a single technique; rather, it is a framework from which a range of specific interventions are derived.

    How ABA Therapy Works

    • The A-B-C Model (Antecedent, Behaviour, Consequence): At the heart of ABA is the A-B-C framework. The Antecedent is the event or situation that occurs immediately before a behaviour. The Behaviour is the response that follows. The Consequence is what happens immediately after the behaviour. By carefully analysing this chain of events, therapists identify patterns and design precise interventions to encourage desired behaviours and discourage problematic ones.
    • Positive Reinforcement Strategies: ABA relies heavily on positive reinforcement — the delivery of a rewarding consequence immediately following a desired behaviour — to increase the likelihood that the behaviour will occur again. Reinforcers are highly individualised and may include verbal praise, access to preferred toys, social attention, food, or any other item or experience that the individual finds motivating. The power of ABA lies in identifying what truly motivates each individual and using that strategically to drive learning.
    • Data Collection and Progress Tracking: One of the hallmarks of ABA is its rigorous, ongoing data collection. Therapists record performance on every skill target during every session. This data is then analysed regularly to determine whether the individual is progressing, plateauing, or regressing. Data-driven decision-making ensures that the therapy plan is always based on objective evidence rather than subjective impression.

    Methods and Techniques in ABA Therapy

    • Discrete Trial Training (DTT): DTT is a highly structured teaching method in which skills are broken down into small, distinct components and taught one at a time through repeated practice. Each trial has a clear instruction, a prompted or independent response, and an immediate consequence. DTT is particularly effective for teaching foundational skills such as early language, imitation, and basic academic concepts.
    • Natural Environment Teaching (NET): NET involves teaching skills within the context of the individual’s natural environment and daily routines — such as during play, mealtimes, or outdoor activities. This approach promotes the generalisation of skills across different settings and people, making it a powerful complement to more structured teaching methods.
    • Pivotal Response Treatment (PRT): PRT targets “pivotal” areas of development — such as motivation, self-management, and social initiation — that are foundational to a wide range of other skills. By improving these pivotal behaviours, PRT produces broad improvements across multiple developmental domains simultaneously.
    • Verbal Behaviour Therapy: Drawing on Skinner’s analysis of language, Verbal Behaviour (VB) therapy categorises language into functional units — such as requesting (mands), labelling (tacts), and imitating (echoics) — and teaches each one systematically. This approach is particularly effective for building functional communication in early language learners.
    • Incidental Teaching: Incidental teaching capitalises on naturally occurring opportunities to teach skills during everyday activities. The therapist follows the child’s lead and embeds learning within motivating, child-initiated interactions, making the process feel less structured and more enjoyable for the learner.

    Benefits of ABA Therapy for Autism

    • Improving Communication and Language: ABA therapy is highly effective in developing both verbal and non-verbal communication skills, particularly in young children who are early language learners. Through structured and naturalistic teaching, individuals learn to request, label, respond, and eventually converse.
    • Reducing Problem Behaviours: By understanding the function of challenging behaviours — such as avoiding demands, accessing attention, or seeking sensory stimulation — ABA therapists design targeted interventions that reduce these behaviours while simultaneously teaching more appropriate alternatives.
    • Building Social Skills: ABA incorporates specific social skills programmes that teach foundational skills such as joint attention, imitation, turn-taking, and peer interaction. These skills form the building blocks of meaningful relationships.
    • Increasing Independence: ABA targets daily living skills — such as dressing, toileting, mealtime routines, and community safety — equipping individuals with the practical skills they need to function as independently as possible.

    Effectiveness of ABA Therapy

    ABA therapy has the most extensive evidence base of any autism intervention. Numerous systematic reviews and randomised controlled trials have demonstrated significant improvements in language, adaptive behaviour, social skills, and cognitive functioning in individuals who receive intensive, high-quality ABA therapy. The US Surgeon General, the American Academy of Pediatrics, and the UK’s National Institute for Health and Care Excellence (NICE) all recognise ABA as an evidence-based treatment for autism.

    Criticisms and Debates Around ABA: It is important to acknowledge that ABA is not without controversy. Some autistic advocates and self-advocates have raised concerns about historical ABA practices that focused heavily on eliminating autistic behaviours rather than addressing genuine wellbeing. Modern ABA has evolved significantly and now emphasises naturalised, strength-based and child-led approaches. Families are encouraged to seek practitioners who apply contemporary, humane and developmentally appropriate ABA principles.

    ABA Therapy at Home

    Many ABA principles can be incorporated into home routines by parents and caregivers who have received training from a BCBA. Home-based ABA allows for consistent reinforcement of skills in the natural environment, promotes generalisation, and reduces the burden of frequent clinic visits. A trained professional should always guide the design and oversight of a home ABA programme.

    📥 Free download: Printable daily routine chart for autistic children

    Speech and Language Therapy for Autism
    Speech and Language Therapy for Autism

    Speech and language therapy for autism is a specialised intervention that targets communication skills across all modalities — verbal, non-verbal and augmentative. Delivered by a qualified Speech-Language Pathologist (SLP) or Speech and Language Therapist (SaLT), it addresses not only how a person speaks, but how they understand and use language to connect with others. It is recommended for virtually all individuals on the autism spectrum.

    What is Speech Therapy for Autism?

    A common misconception is that speech therapy for autism is solely about helping children to speak. In reality, the scope of speech therapy is far broader. It encompasses understanding and using language (both spoken and non-spoken), pragmatic and social communication, voice and fluency, feeding and swallowing, and the use of alternative communication tools for those who cannot yet speak reliably. For many individuals with autism, the ultimate goal is not necessarily verbal speech but effective communication — however that is achieved.

    How Speech Therapy Works for Autism

    Speech therapy begins with a comprehensive communication assessment that evaluates the individual’s receptive language (understanding), expressive language (use), pragmatics (social communication), articulation, fluency, and voice. Standardised tools such as the CELF (Clinical Evaluation of Language Fundamentals) and ADOS (Autism Diagnostic Observation Schedule) communication subtests are frequently used. The assessment identifies not only weaknesses but also strengths and preferred communication modalities.

    Verbal vs. Non-Verbal Communication Strategies

    Not all individuals with autism will develop reliable spoken language, and that is a perfectly valid outcome. Speech therapy supports both verbal and non-verbal pathways to communication. For individuals who are non-verbal or minimally verbal, the focus may be on building functional communication through AAC systems, gesture, picture exchange, or digital communication devices. For verbal individuals, therapy may focus on conversational skills, understanding and using figurative language, or managing communication anxiety.

    Speech Therapy Techniques for Autism

    • PECS (Picture Exchange Communication System): PECS is a structured programme that teaches individuals to communicate by exchanging pictures. It begins with the exchange of a single picture for a desired item and progressively builds towards sentence-level communication and commenting. PECS is evidence-based and particularly effective for young or minimally verbal children.
    • Augmentative and Alternative Communication (AAC) Devices: AAC encompasses any tool or strategy that supplements or replaces natural speech. This ranges from low-tech systems such as communication boards and PECS to high-tech Speech-Generating Devices (SGDs) and tablet-based apps. Research strongly supports the use of AAC for non-verbal individuals with autism and confirms that AAC does not prevent speech development — in fact, it often supports it.
    • Social Stories and Scripts: Social Stories, developed by Carol Gray, are short, personalised narratives that describe a social situation, skill, or concept from the individual’s perspective. They help individuals with autism understand what is expected in specific situations and how others might feel. Social scripts provide practised language for common interactions, reducing the cognitive demand of navigating social situations in real time.
    • Oral Motor Exercises: For individuals who have difficulties with the physical production of sounds due to oromotor weaknesses, targeted exercises targeting the lips, tongue, jaw, and palate may be incorporated into therapy. These exercises support clearer articulation and can improve speech intelligibility.
    • Pragmatic Language Therapy: Pragmatic language refers to the social use of language — understanding and following conversational rules, interpreting implied meaning, adjusting language for different audiences, and recognising non-literal language such as humour, sarcasm, and idioms. Pragmatic language therapy teaches these skills explicitly, using structured activities, role-play, and video modelling.
    • Functional Communication Training (FCT): FCT teaches individuals to replace challenging behaviours — such as screaming, hitting, or throwing — with a more acceptable form of communication that serves the same function (e.g., requesting a break, seeking attention, or escaping a difficult task). FCT is typically implemented in close collaboration with the ABA team.

    The Speech Therapy Process

    • Initial Evaluation: The therapy process begins with a detailed evaluation of the individual’s communication profile. This includes a parent or caregiver interview, direct assessment, observation in natural settings (where possible), and review of relevant reports from other professionals.
    • Setting Communication Goals: Based on the evaluation, the SLT collaborates with the individual and their family to establish clear, functional, and measurable communication goals. These goals are reviewed regularly and updated as progress is made.
    • One-on-One and Group Sessions: Speech therapy may be delivered in individual sessions, small group settings, or both. Individual sessions allow for intensive, targeted skill work, whilst group sessions provide a supported environment for practising communication skills with peers.
    • Home Practice Programmes: Because communication occurs throughout every waking moment, the generalisation of skills to the home and community is essential. Speech therapists typically provide home practice programmes that guide parents and caregivers in embedding communication targets into daily routines and play activities.

    Benefits of Speech Therapy for Autism

    1. Improved Verbal Communication: For individuals who have the potential for verbal speech, consistent speech therapy can accelerate language development, increase vocabulary, improve sentence structure, and build conversational competence.
    2. Enhanced Non-Verbal Communication: Even for individuals who do not develop verbal speech, speech therapy builds rich non-verbal communication repertoires — including gesture, eye gaze, pointing, and the use of AAC — that allow meaningful communication to occur.
    3. Better Social Interactions: By targeting pragmatic language and social communication skills, speech therapy helps individuals with autism navigate conversations, build relationships, and participate more fully in social life.
    4. Reduced Frustration and Behavioural Issues: Many challenging behaviours in autism arise from the inability to communicate needs or feelings effectively. As communication improves, frustration decreases, and challenging behaviours often reduce as a natural consequence.

    Effectiveness of Speech Therapy

    Speech therapy is one of the most consistently recommended and evidence-supported interventions for autism. Meta-analyses of intervention research confirm significant improvements in expressive and receptive language, social communication, and AAC use following targeted speech therapy. The combination of speech therapy with early intensive behavioural intervention (such as ABA) produces particularly strong outcomes for young children.

    Finding Speech Therapy for Autism Near You

    When seeking a speech therapist for autism, families should look for an SaLT with specific experience in autism spectrum disorders and AAC. Referrals can be obtained through GPs, paediatricians, schools, or autism diagnostic services. Waiting times in publicly funded services can be lengthy; private SaLT services offer shorter waiting periods for families who are able to access them. Teletherapy (online speech therapy) has also become widely available and is a viable and evidence-supported option, particularly for home-based practice.

    Occupational Therapy for Autism

    Occupational Therapy for Autism

    Occupational therapy (OT) for autism helps individuals develop the everyday skills needed for self-care, learning, play, and participation. OT targets fine and gross motor skills, sensory processing, daily living skills, and visual-motor integration. It is one of the most widely recommended autism therapies and plays a vital role in supporting independence across the lifespan.

    For more detailed information, read our blog Occupational Therapy for Autism: Complete Guide (2026) 

    What is Occupational Therapy for Autism?

    Occupational therapy is a health profession that focuses on enabling people to participate in the activities of daily life that are meaningful to them — referred to as “occupations.” For children with autism, these occupations include playing, dressing, eating, writing, engaging in school activities, and socialising. For adults, they extend to work, community participation, and independent living. The occupational therapist identifies barriers to participation and implements targeted interventions to overcome them.

    Role of the Occupational Therapist (OT): Occupational therapists working with autistic individuals possess specialist training in sensory processing, fine and gross motor development, neurodevelopment, adaptive equipment, and environmental modification. They work across a variety of settings, including specialist clinics, schools, community centres, and homes.

    How Occupational Therapy Works

    Occupational Profile and Assessment: OT begins with a comprehensive assessment that creates an occupational profile — a detailed picture of the individual’s daily routines, challenges, priorities, and goals. Assessment tools used in autism OT include the Sensory Profile, the Peabody Developmental Motor Scales, the Bruininks-Oseretsky Test of Motor Proficiency, and clinical observation.

    Setting Functional Goals for Daily Life: Goals in OT are always functional and meaningful to the individual and their family. Rather than targeting isolated skills in a vacuum, OT frames every goal in the context of real-life participation — for example, improving pencil grip so that the child can write comfortably at school, or building dressing skills so that the young person can manage their morning routine independently.

    The Role of Occupational Therapy in Autism

    Fine Motor Skill Development: Fine motor skills involve the coordinated use of the small muscles of the hands and fingers. Many children with autism have difficulties with fine motor tasks such as writing, using cutlery, fastening buttons, and manipulating small objects. OT uses targeted activities to strengthen hand muscles, improve bilateral coordination, and develop the precision needed for these tasks.

    Gross Motor Skills and Coordination: Gross motor skills involve the large muscle groups used for whole-body movements such as running, jumping, climbing, and balancing. Children with autism frequently experience motor coordination difficulties, which can affect physical education participation, playground inclusion, and general physical confidence. OT and physical therapy both contribute to improving gross motor functioning.

    Self-Care and Daily Living Skills: One of the most practically significant roles of OT is developing independence in self-care tasks — such as dressing, undressing, toileting, bathing, brushing teeth, and preparing simple meals. These skills are foundational to independence and quality of life. OT uses task analysis, visual supports, adaptive equipment, and repeated practice to build self-care competence.

    Sensory Processing and Regulation: Sensory processing differences are among the most common and impactful features of autism. Many OTs have specialist training in sensory integration and develop individualised “sensory diets” — tailored programmes of sensory activities that help regulate the individual’s arousal level and sensory comfort throughout the day.

    Visual-Motor Integration: Visual-motor integration — the ability to coordinate visual information with hand movements — is essential for reading, writing, drawing, and many functional tasks. OT activities targeting eye-hand coordination and spatial perception build this critical skill.

    Social Participation: Through structured group activities, play-based learning, and environmental adaptations, OT supports social participation by equipping individuals with autism with the motor, sensory, and organisational skills they need to engage successfully with peers.

    Here is a detailed article on The Crucial Role of Occupational Therapy for Autistic Children 

    Occupational Therapy Activities for Autism

    Handwriting and Pencil Grip Exercises: Programmes such as “Handwriting Without Tears” are frequently used by OTs to address handwriting difficulties in children with autism. Activities include pre-writing exercises, correct grip training, and pencil-control games.

    Play-Based Activities: Play is the primary occupation of childhood and a critical context for learning. OT uses structured and semi-structured play activities to build fine motor skills, sensory tolerance, social interaction, and problem-solving.

    Sensory Play Activities: Sensory play activities — such as playdough manipulation, finger painting, sand and water play, and textured materials exploration — provide controlled sensory input that supports sensory processing development and tolerance.

    Life Skills Training Activities: Practical activities such as cooking simple recipes, managing money, using public transport, and operating home appliances are incorporated into OT for older children and adults to build real-world independence.

    Social Skills Activities: Group OT sessions may incorporate board games, cooperative building activities, and role-play scenarios that provide a structured context for practising turn-taking, sharing, communication, and social problem-solving.

    Occupational Therapy at Home for Autism

    Home-based OT is a highly effective complement to clinic-based intervention. Parents and caregivers are taught to embed OT goals into daily routines — for example, practising fine motor skills through cooking activities, building sensory tolerance through bathtime play, and targeting gross motor coordination through outdoor games. A qualified OT should design and regularly review any home programme.

    Benefits of Occupational Therapy for Autism

    Occupational therapy delivers wide-ranging benefits, including improved self-care independence, better academic participation through improved motor and sensory skills, enhanced social inclusion, reduced sensory overwhelm, improved concentration and learning readiness, and increased confidence in daily activities. Families consistently report that OT makes a profound practical difference to daily life.

    Finding Occupational Therapy for Autism Near You

    OT for autism is available through the NHS in the UK, through public health services in many countries, and through private clinics. When selecting a paediatric OT for autism, families should seek a practitioner with experience in sensory integration, autism spectrum profiles, and functional skills development.

    Sensory Integration Therapy for Autism
    Sensory Integration Therapy for Autism

    Sensory integration therapy for autism is a specialised form of occupational therapy that addresses the way the brain receives and processes sensory information. Developed by occupational therapist Dr A. Jean Ayres in the 1970s, it uses specific sensory experiences — movement, deep pressure, touch and proprioceptive input — to improve the brain’s ability to organise and respond to sensory stimuli. It is widely used for autistic individuals who experience sensory hypersensitivity, hyposensitivity, or sensory-seeking behaviours.

    What is Sensory Integration Therapy?

    Understanding Sensory Processing Disorder (SPD) in Autism: Many individuals with autism experience significant difficulties in how their nervous system registers and responds to sensory input. This is often referred to as Sensory Processing Disorder (SPD). Some individuals are over-responsive — finding ordinary sensory input (such as a clothing tag or background noise) intensely uncomfortable or painful. Others are under-responsive — seeking out intense sensory stimulation to register their environment. Still others show a mixed profile. These sensory differences significantly affect behaviour, learning, and daily functioning.

    Jean Ayres’ Sensory Integration Framework: Dr Ayres proposed that the brain’s ability to organise sensory information is a fundamental prerequisite for learning and behaviour. When sensory integration is disrupted, the brain cannot efficiently use sensory information to plan and execute appropriate responses. Her therapeutic approach uses graded, purposeful sensory activities to challenge the nervous system and improve its processing efficiency.

    Sensory Therapy Techniques for Autism

    • Deep Pressure Therapy: Deep pressure — applied through massage, compression clothing, weighted items, or firm squeezing — activates the proprioceptive system and produces a calming, organising effect on the nervous system. Many autistic individuals are drawn to deep pressure input and find it highly regulating.
    • Brushing Protocol (Wilbarger Protocol): The Wilbarger Protocol, developed by Patricia Wilbarger, involves systematic, firm brushing of the skin using a specialised surgical brush, followed by joint compressions. It must be administered by a trained OT and carried out multiple times per day. It is used to reduce tactile hypersensitivity and improve sensory tolerance.
    • Weighted Vests and Blankets: Weighted vests and blankets provide proprioceptive input that many individuals with autism find calming and focusing. They are used during specific activities (such as seatwork or transitions) and are prescribed as part of a broader sensory diet.
    • Swinging and Vestibular Activities: The vestibular system, which controls balance and spatial orientation, is often dysregulated in autism. Swinging on a therapy swing, using a hammock, or engaging in rocking and spinning activities provides vestibular input that can have a powerful organising or calming effect on the nervous system.
    • Tactile Bins and Textures: Tactile exploration activities — such as playing with dried beans, sand, water, or textured materials — systematically expose the individual to a range of textures, supporting the development of tactile tolerance and discrimination over time.
    • Proprioceptive Input Activities: Activities that involve pushing, pulling, carrying, climbing, and jumping provide proprioceptive input (feedback from joints and muscles) that supports body awareness, motor planning, and self-regulation. Proprioceptive activities are commonly incorporated into sensory diets as regulating strategies.

    The Sensory Integration Therapy Process

    • Sensory Profile Assessment: The process begins with a comprehensive sensory assessment — such as the Sensory Profile 2 (Winnie Dunn) — completed by parents and caregivers, combined with direct clinical observation by the OT. This assessment identifies the individual’s specific sensory processing patterns across all sensory systems.
    • Creating a Sensory Diet: A sensory diet is an individualised plan of sensory activities prescribed throughout the day to maintain the individual’s optimal arousal and regulation state. The OT designs the sensory diet based on the assessment findings and teaches the family and school how to implement it consistently.
    • Monitoring Sensory Responses: Sensory responses are closely monitored over time. The OT observes changes in sensory tolerance, regulation, behaviour, and participation, adjusting the sensory diet and clinic-based activities as the individual’s sensory needs evolve.

    Benefits of Sensory Integration Therapy for Autism

    Sensory integration therapy delivers significant benefits for autistic individuals with sensory processing difficulties. These include reduced sensory overload and meltdowns, improved focus and attention for learning, better behavioural regulation, enhanced motor planning, increased tolerance of everyday sensory experiences, and a greater sense of comfort and safety in daily environments.

    Sensory Therapy at Home

    Parents can support sensory integration between therapy sessions by implementing the sensory diet at home and creating a sensory-friendly environment. This includes providing access to regulating sensory equipment (such as therapy swings or sensory corners), using calming sensory strategies before transitions, and avoiding sensory triggers where possible.

    Cognitive Behavioural Therapy (CBT) and Autism
    Cognitive Behavioural Therapy (CBT) and Autism

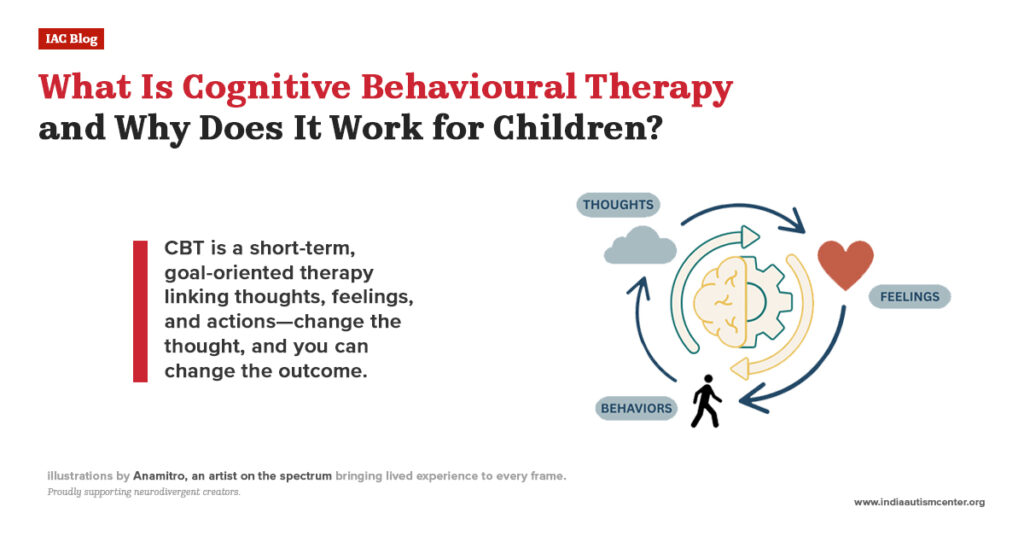
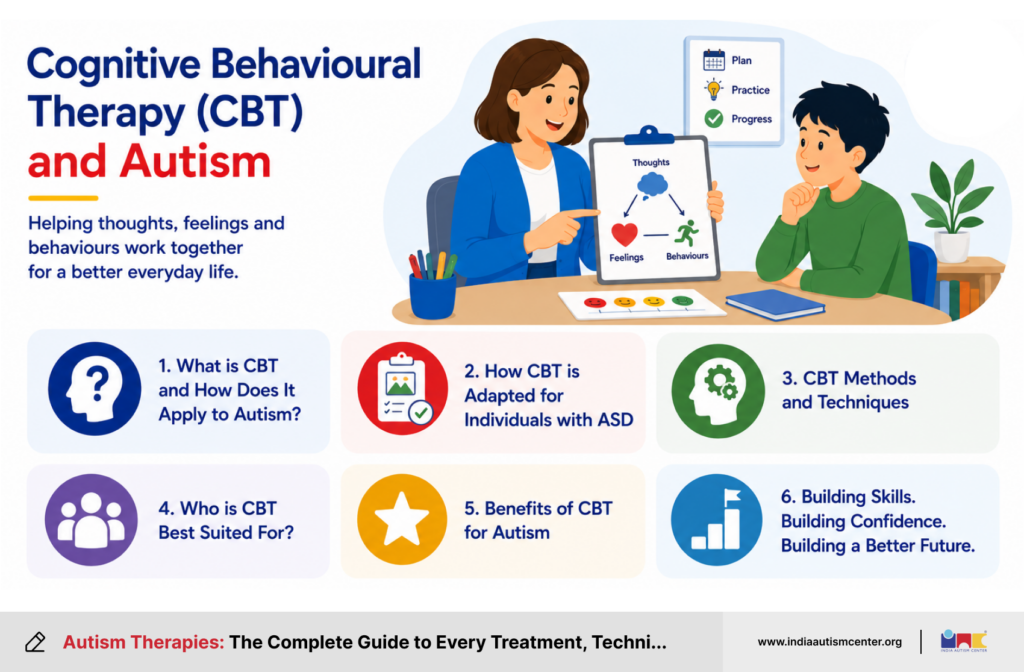
    Cognitive Behavioural Therapy (CBT) is a structured, evidence-based psychological therapy that helps individuals understand the connections between their thoughts, feelings and behaviours. For autistic individuals — particularly those with higher cognitive functioning — CBT is effective in addressing anxiety, depression, obsessive-compulsive behaviours and emotional dysregulation. It is typically adapted with visual supports, explicit instruction and concrete examples to suit autistic learning styles.

    What is CBT and How Does It Apply to Autism?

    CBT is based on the principle that unhelpful thought patterns contribute to emotional distress and problematic behaviours. By identifying and challenging these thoughts and developing more balanced cognitive perspectives, individuals are able to change how they feel and behave. In autism, CBT is most frequently used to address the high rates of co-occurring anxiety (present in approximately 40–50% of autistic individuals), as well as depression, anger regulation, and repetitive or obsessive behaviours.

    How CBT is Adapted for Individuals with ASD

    Standard CBT assumes strong verbal reasoning, abstract thinking, and the ability to identify and discuss emotions — abilities that may be less readily available in autistic individuals. Autism-adapted CBT makes a number of key modifications: it uses visual aids, worksheets, and diagrams to represent abstract concepts concretely; it incorporates the individual’s specific interests to enhance engagement; it builds explicit emotion recognition skills before progressing to cognitive restructuring; and it reduces the metaphor and ambiguity common in standard CBT language, replacing these with clear, direct instruction.

    CBT Methods and Techniques Used in Autism

    • Thought-Emotion-Behaviour Triangle: The foundational model of CBT is the triangle connecting thoughts, emotions and behaviours. CBT explicitly teaches the individual to identify where they are in the cycle — for example, recognising that a thought such as “nobody likes me” contributes to feelings of sadness and behaviours such as withdrawal — and then to examine and challenge that thought.
    • Emotion Identification and Regulation: Many autistic individuals have alexithymia — difficulty identifying and describing their own emotions. CBT sessions may begin with explicit emotion identification work, using visual emotion scales (such as the “anxiety thermometer”) to help the individual recognise the signs of different emotional states in their body.
    • Cognitive Restructuring: Cognitive restructuring involves identifying unhelpful automatic thoughts (such as catastrophising or black-and-white thinking), evaluating the evidence for and against them, and developing more balanced alternative thoughts. In autism, this process is typically made more concrete by using structured thought records and written worksheets.
    • Exposure and Response Prevention (ERP): For autistic individuals with significant anxiety or OCD-type behaviours, Exposure and Response Prevention — a specific CBT technique — is used to systematically and gradually confront feared situations whilst resisting the urge to engage in avoidance or compulsive behaviours. This is conducted in a carefully planned, paced, and supportive manner.

    Who is CBT Best Suited For?

    CBT is generally most suitable for autistic individuals who are higher-functioning, have verbal communication skills, and possess sufficient cognitive ability to reflect on their own thoughts and feelings. It is widely used with older children, adolescents, and adults on the autism spectrum. It is less suitable for individuals who are non-verbal or who have significant intellectual disabilities, for whom other emotional regulation approaches (such as sensory-based strategies or visual supports) may be more appropriate.

    Benefits of CBT for Autism

    CBT offers meaningful benefits to autistic individuals who are well-suited to the approach. These include significantly reduced anxiety symptoms, better management of obsessive and repetitive thoughts and behaviours, improved emotional regulation and frustration tolerance, enhanced social confidence, and a stronger sense of self-efficacy and personal control.

    Want to know more? Get in touch with us.

    Music Therapy for Autism
    Music Therapy for Autism

    Music therapy for autism is an evidence-based therapeutic intervention in which a qualified music therapist uses musical experiences — including singing, playing instruments, movement to music, and improvisation — to address communication, social, emotional, and sensory goals. Research consistently demonstrates that music therapy produces meaningful improvements in communication and social interaction in autistic individuals, including those who are non-verbal.

    What is Music Therapy for Autism?

    Music therapy is a clinical discipline in which music is used purposefully and systematically as a therapeutic tool. Unlike music lessons or recreational music participation, music therapy is led by a trained clinician who sets specific goals and uses musical experiences to achieve them. Music engages multiple areas of the brain simultaneously and can reach individuals with autism who are less responsive to verbal or behavioural approaches.

    Who is a Certified Music Therapist? A certified music therapist holds a recognised qualification in music therapy and has training in clinical assessment, intervention planning, and evaluation. In the UK, music therapists are registered with the Health and Care Professions Council (HCPC).

    How Music Therapy Works

    The Connection Between Music and the Autistic Brain: Research in neuroscience has revealed that music activates a remarkably broad network of brain areas, including those responsible for emotion, memory, motor control, attention, and language. Notably, many autistic individuals show preserved or heightened musical perception and processing abilities, making music a particularly accessible and motivating medium for therapy. Music also provides a structured, predictable, and non-threatening context for interaction, which reduces the social anxiety that often accompanies other forms of engagement.

    Active vs. Receptive Music Therapy: Active music therapy involves the individual directly creating music — through singing, instrument playing, or improvisation. Receptive music therapy involves listening to music that is selected or played by the therapist to elicit specific emotional, physical, or cognitive responses. Both forms are used in autism practice, often within the same session.

    Music Therapy Techniques for Autism

    Rhythmic Auditory Stimulation (RAS): RAS uses rhythmic musical cues to support motor function and movement. In autism, RAS is used to improve coordination, gait, and motor sequencing, as well as to regulate attention and arousal.

    Neurologic Music Therapy (NMT): NMT is a neuroscientific approach to music therapy that uses specific music-based techniques to address cognitive, communicative, sensory, and motor functions. NMT is grounded in research on the neural mechanisms that underpin the music-brain relationship.

    Improvisational Music Therapy: Improvisation allows the individual to explore music freely and spontaneously, without a prescribed structure. The therapist responds to the individual’s musical expressions — mirroring, complementing, and building upon them — creating a musical dialogue that parallels and supports the development of communication and social reciprocity.

    Songwriting and Lyric Analysis: Composing original songs provides a creative and emotionally meaningful channel for self-expression. Lyric analysis involves exploring the themes and messages within songs, which can support emotional literacy, perspective-taking, and social understanding.

    Movement to Music: Combining music with movement supports body awareness, motor coordination, rhythm perception, and social engagement. Dance and movement to music is used within music therapy sessions, as well as in dedicated dance and movement therapy (see Section 15).

    Benefits of Music Therapy for Autism

    The benefits of music therapy for autism are well-documented in the research literature and include: enhanced verbal and non-verbal communication; improved joint attention and social reciprocity; reduced anxiety and emotional distress; better sensory regulation through auditory and rhythmic input; increased motivation and engagement in therapeutic activities; and improved self-expression and emotional wellbeing. Notably, music therapy is particularly effective for non-verbal individuals who may not engage readily with language-based therapies.

    Music Therapy at Home — Activities for Parents

    Parents can support music therapy goals at home through simple activities such as singing during daily routines (bath time, mealtimes, transitions), using percussion instruments to encourage turn-taking, playing preferred music during times of emotional dysregulation to provide comfort, and exploring music improvisation through household items.

    Sound Therapy for Autism

    Sound Therapy for Autism

    Sound therapy for autism uses specific auditory stimuli — including modulated music, specific frequencies, and filtered sound programmes — to address auditory processing difficulties, sensory hypersensitivities, attention, and language processing. The most widely used forms are Auditory Integration Training (AIT) and the Tomatis Method. While evidence is still developing, many families report reduced sound sensitivity and improved communication following sound therapy.

    What is Sound Therapy for Autism?

    Sound therapy and music therapy are distinct disciplines that are often confused. Music therapy is a clinically established profession using music to address a range of goals; it is delivered by a qualified therapist and is built on a robust evidence base. Sound therapy, by contrast, uses specific acoustic stimuli — often electronically filtered or modulated — to target auditory processing and nervous system regulation. Sound therapy is delivered by practitioners trained in specific auditory programmes and has a smaller but growing evidence base.

    Types of Sound-Based Interventions: The main sound therapy programmes used in autism practice include Auditory Integration Training (AIT), the Tomatis Method, Therapeutic Listening (developed by Sheila Frick), and Berard AIT (developed by Dr Guy Berard). More recently, binaural beats and brain entrainment approaches have also gained attention, although evidence for these is preliminary.

    How Sound Therapy Works

    Auditory Processing and Autism: Many autistic individuals have hypersensitive auditory systems — they are disturbed by sounds that others barely notice, experience physical pain from certain pitches, or find it extremely difficult to filter relevant sounds from background noise. These auditory processing difficulties affect behaviour, communication, learning, and sensory comfort. Sound therapy aims to retrain and recalibrate the auditory system through repeated exposure to carefully structured sound stimuli.

    How Specific Frequencies Affect the Nervous System: Different sound frequencies are thought to activate different parts of the auditory and nervous system. Sound therapy programmes exploit this by selectively filtering and modulating sound frequencies to provide the auditory system with novel, challenging input that encourages processing adaptation over time.

    Sound Therapy Methods and Techniques

    Auditory Integration Training (AIT): AIT, developed by Dr Guy Berard, involves listening to electronically modulated music through headphones for two sessions of 30 minutes per day over ten days. The music is filtered to remove frequencies at which the individual shows auditory hypersensitivity, identified through an initial audiogram. AIT aims to reduce auditory hypersensitivities and improve auditory processing efficiency.

    The Tomatis Method: Developed by French ENT physician Dr Alfred Tomatis, this method uses electronically filtered and modulated sound — primarily classical music and the mother’s voice — to stimulate and retrain the auditory system and the vestibular-cochlear connection. The method aims to improve listening, language, communication, and sensory integration.

    Therapeutic Listening: Therapeutic Listening, developed by OT Sheila Frick, involves listening to electronically altered music through high-quality headphones as part of a broader sensory integration programme. It is used to modulate sensory processing, improve attention, and support self-regulation.

    You may find this useful: Sound Therapy for Autism: Methods & Effectiveness. 

    Benefits of Sound Therapy for Autism

    Reported benefits of sound therapy for autism include reduced hypersensitivity to everyday sounds, improved listening and auditory processing, enhanced language comprehension, better attention and concentration, reduced anxiety in auditory environments, and improved communication. The strength of these benefits varies between individuals and programmes, and it is important to seek programmes delivered by qualified and experienced practitioners.

    Visual Therapy for Autism
    Visual Therapy for Autism

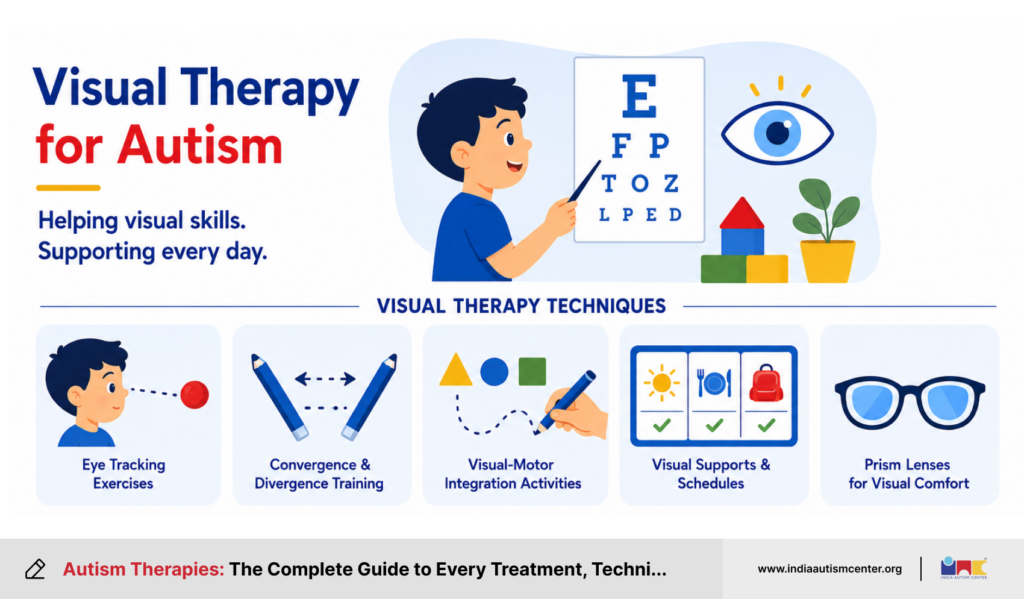
    Visual therapy for autism addresses difficulties in how the brain processes and uses visual information. Delivered by a developmental optometrist or trained vision therapist, it uses targeted exercises and visual tools to improve eye tracking, visual perception, and visual-motor integration. It also encompasses the broad use of visual supports — such as visual schedules, choice boards, and social stories — as strategies throughout autism intervention.

    What is Visual Therapy for Autism?

    Understanding Visual Processing Differences in ASD: Many autistic individuals experience differences in visual processing that go beyond simple visual acuity (sharpness of sight). These include difficulties with visual tracking, visual-spatial perception, depth perception, and the ability to process visual information efficiently during movement or in visually complex environments. These differences can affect reading, learning, coordination, and daily functioning.

    Role of a Developmental Optometrist: A developmental optometrist is a specialist who evaluates not only the physical structure of the eye but also how the brain processes and uses visual information. Developmental optometrists can identify visual processing difficulties that may be contributing to the learning and behavioural challenges commonly seen in autism, and can prescribe targeted vision therapy programmes.

    Visual Therapy Techniques for Autism

    • Eye Tracking Exercises: Smooth pursuit and saccadic eye movement exercises train the eyes to track moving objects accurately and to shift focus efficiently between targets. Poor eye tracking can affect reading fluency, attention, and coordination, and is frequently identified in autistic individuals.
    • Convergence and Divergence Training: Convergence (the ability to turn both eyes inward to focus on a near target) and divergence (the ability to turn eyes outward to shift to a far target) are essential for comfortable near and far vision. Difficulties in these areas can cause eye strain, headaches, and avoidance of visual tasks, which may manifest as learning resistance or challenging behaviour.
    • Visual-Motor Integration Activities: Visual-motor integration activities link visual perception with fine motor execution — for example, copying shapes, tracing patterns, completing mazes, and constructing block designs. These activities develop the foundational skills required for handwriting, drawing, and many academic tasks.
    • Use of Colour and Visual Schedules: The use of colour coding, visual schedules (sequences of pictures showing the day’s activities), and visual organisers supports attention, prediction, and understanding of routines in autistic individuals. These visual tools reduce reliance on verbal instruction, which can be harder for many individuals with autism to process.
    • Prism Lenses: Some developmental optometrists prescribe tinted or prism lenses for individuals with autism who experience visual stress or perceptual distortions. These lenses can modify the way light reaches the visual cortex and may reduce visual discomfort and improve attention.

    Benefits of Visual Therapy for Autism

    Visual therapy offers benefits including improved reading fluency and comprehension, better visual-motor coordination, reduced visual stress and eye strain, enhanced eye contact and visual engagement, and improved academic and learning performance. The use of visual supports as a broader autism strategy — which is supported by extensive research — significantly improves understanding, compliance with routines, and communication.

    Physical Therapy for Autism
    Physical Therapy for Autism

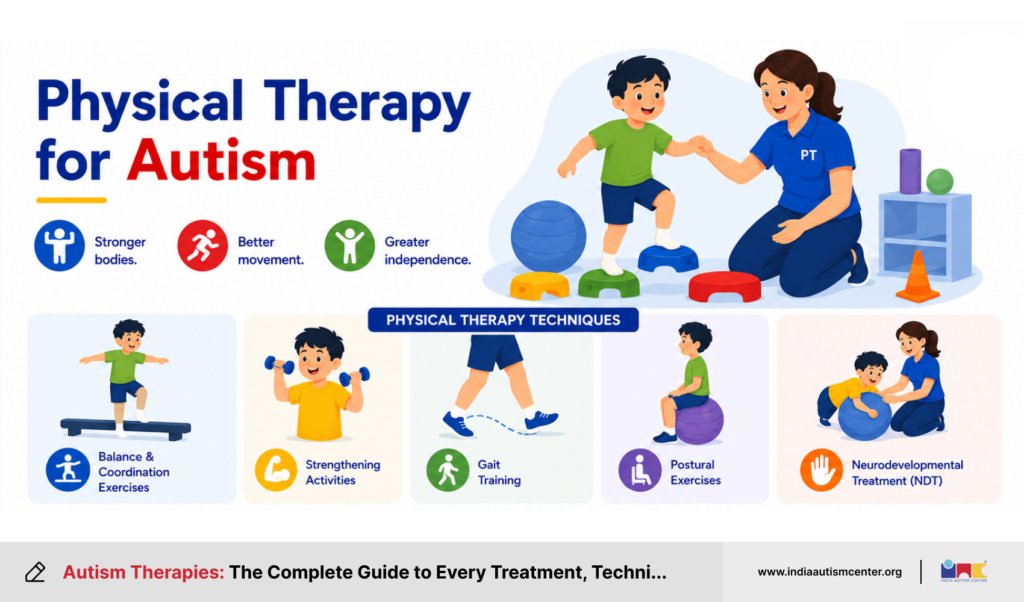
    Physical therapy (PT) for autism addresses motor development, coordination, strength, balance, and gait. Delivered by a paediatric physiotherapist, PT helps autistic individuals overcome gross motor difficulties that affect their participation in physical activities, school, and daily life. It is particularly valuable for individuals with low muscle tone, coordination disorders, or delayed motor milestones.

    What is Physical Therapy for Autism?

    Physical therapy for autism focuses on improving the physical and motor aspects of functioning that are affected by autism and its common co-occurring conditions. Many autistic individuals have low muscle tone (hypotonia), poor motor coordination (dyspraxia), an atypical gait pattern, or delayed gross motor milestones. Physical therapy addresses these challenges directly, improving physical capability, safety, and participation.

    Physical Therapy Techniques for Autism

    Balance and Coordination Exercises: Activities such as standing on one leg, walking on a balance beam, catching and throwing balls, and obstacle courses challenge and develop balance and whole-body coordination skills that are often underdeveloped in autism.

    Strengthening Activities: Core and limb strengthening exercises, adapted for the individual’s ability and interests, build muscle strength and endurance. Stronger muscles support better posture, more controlled movement, and greater physical confidence.

    Gait Training: Many autistic individuals have an unusual walking pattern — such as toe-walking, a wide-based gait, or poor arm swing — that can affect comfort, endurance, and physical development. Gait training uses targeted exercises and sometimes orthotic devices to improve walking mechanics.

    Postural Exercises: Poor posture — often related to low muscle tone and reduced proprioceptive awareness — affects seated attention, handwriting, and physical comfort. Postural exercises and positioning strategies support better alignment and endurance.

    Neurodevelopmental Treatment (NDT): NDT is a hands-on physiotherapy approach that uses facilitation techniques to improve movement patterns, reduce abnormal muscle tone, and promote typical motor development.

    Benefits of Physical Therapy for Autism

    Physical therapy delivers benefits including improved gross motor skills and coordination, better posture and gait, increased physical strength and endurance, enhanced body awareness and proprioception, greater participation in sports and physical activities, and improved overall physical health and wellbeing. Physical fitness is also closely linked to mental health, and regular physical activity has been shown to reduce anxiety and repetitive behaviours in autistic individuals.

    Play Therapy for Autism

    Play Therapy for Autism

    Play therapy for autism uses play — the natural language of childhood — as a therapeutic medium to develop social, communication, emotional and cognitive skills. Approaches such as DIR/Floortime, Theraplay and play-based social skills groups are specifically designed to meet the developmental and relational needs of autistic children in a child-led, warm and engaging way.

    What is Play Therapy for Autism?

    Play therapy recognises that children communicate and learn most naturally through play. For autistic children, play development is often delayed, atypical, or primarily solitary. Play therapy aims to enrich the child’s play repertoire, build meaningful engagement with adults and peers, and use the motivating context of play to develop key developmental skills.

    Play Therapy Methods and Techniques

    Floortime (DIR/Floortime Model): Developed by Dr Stanley Greenspan, the Developmental, Individual-Difference, Relationship-based (DIR) model — commonly known as Floortime — emphasises following the child’s lead and joining them in their play world. The therapist and parent get down on the floor with the child, engage with their interests, and use playful interaction to expand circles of communication, emotional connection, and cognitive complexity. Floortime is particularly effective for building the foundational social-emotional developmental milestones that precede higher-level communication.

    Relationship Development Intervention (RDI): RDI is a parent-guided programme that focuses specifically on building dynamic intelligence — the ability to engage flexibly in social and real-world situations. RDI uses structured, graded activities to develop joint attention, experience sharing, and collaborative problem-solving.

    Theraplay: Theraplay is a structured, short-term therapy that uses playful, nurturing activities to build attachment, self-esteem, and trust between child and caregiver. Sessions involve four dimensions — nurture, structure, engagement, and challenge — and are conducted with parents present and active.

    Symbolic and Pretend Play Training: Many autistic children have limited pretend or imaginative play. Targeted pretend play training — in which therapists model and scaffold increasingly complex pretend play scenarios — helps children develop the symbolic thinking that underpins language, social interaction, and creativity.

    Benefits of Play Therapy for Autism

    Play therapy builds social reciprocity and joint attention, develops communication through joyful interaction, improves imagination and flexible thinking, strengthens the parent-child relationship, reduces anxiety around social engagement, and provides a motivating and enjoyable context for therapeutic growth.

    Dance and Movement Therapy for Autism
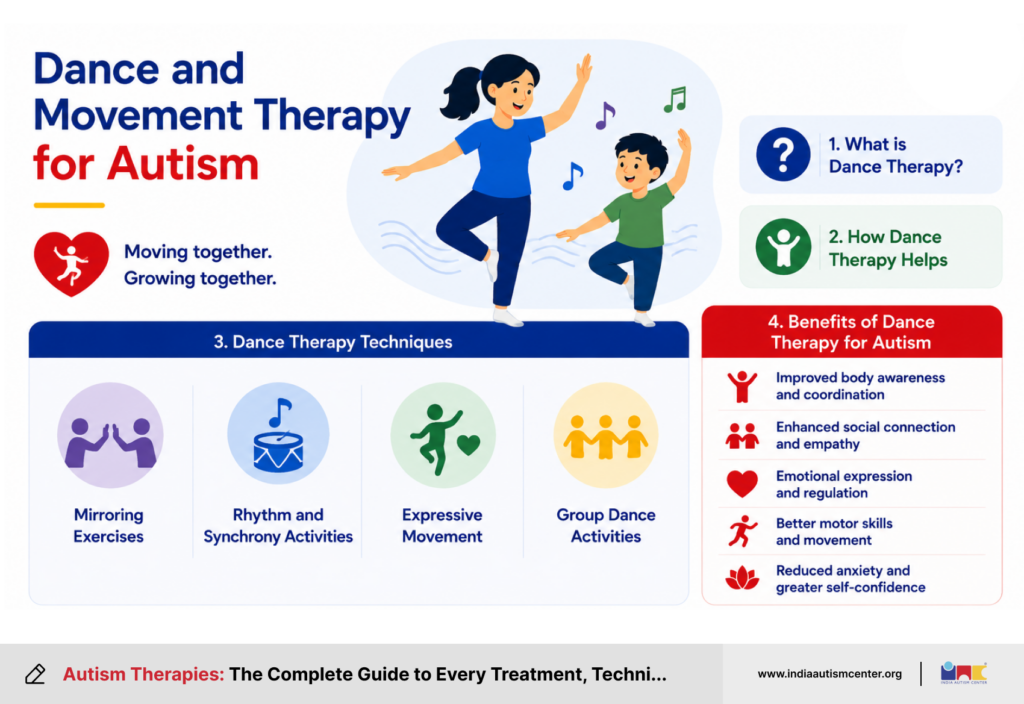
    Dance and Movement Therapy for Autism

    Dance and movement therapy (DMT) for autism uses body movement as a primary medium for therapeutic intervention. It supports body awareness, self-expression, emotional regulation, and social connection. DMT is particularly valuable for individuals who find verbal communication challenging and who respond well to non-verbal, physical modes of interaction.

    What is Dance Therapy for Autism?

    Dance and movement therapy is a psychotherapeutic discipline based on the premise that body and mind are deeply interconnected. Changes in movement quality, posture, and physical engagement reflect and influence psychological and social functioning. A qualified Dance/Movement Therapist (DMT) uses structured and improvised movement experiences to support the individual’s emotional, social, physical, and cognitive development.

    Dance Therapy Techniques

    Mirroring Exercises: The therapist mirrors the child’s spontaneous movements, reflecting them back without direction or correction. This validates the child’s self-expression, builds a sense of being seen and understood, and creates the conditions for genuine social connection without the demands of verbal communication.

    Rhythm and Synchrony Activities: Moving in synchrony with another person — to music, percussion, or spoken rhythm — supports the development of social attunement, timing, and cooperative engagement. Research shows that moving in synchrony also increases feelings of connection and prosocial behaviour.

    Expressive Movement: Individuals are encouraged to use their bodies to express emotions, stories, and experiences. This is particularly powerful for individuals who have limited verbal emotional expression and can significantly reduce anxiety and emotional tension.

    Group Dance Activities: Group sessions use structured dances, movement games, and cooperative activities to develop social skills, body awareness, turn-taking, and a shared sense of belonging within a group.

    Benefits of Dance Therapy for Autism

    Dance and movement therapy supports improved body awareness and proprioception, enhanced social connection and empathy, emotional expression and regulation, physical coordination and motor skills, reduced anxiety, and a heightened sense of joy and self-confidence.

    Want to know more? Get in touch with us.

    Water Therapy and Swimming Therapy for Autism

    Water Therapy and Swimming Therapy for Autism

    Water therapy (aquatic therapy) for autism uses the therapeutic properties of water — including buoyancy, hydrostatic pressure, warmth and resistance — to support motor development, sensory regulation and social skills. Many autistic children are drawn to water, making it a highly motivating therapeutic medium. Swimming therapy also provides critical safety skills for children who are at high risk of water-related accidents.

    What is Water Therapy for Autism?

    Aquatic therapy for autism is delivered in a heated pool or warm water environment by a trained aquatic therapist or physiotherapist. The physical properties of water create a unique sensory and motor environment that is often deeply regulating for autistic individuals — many of whom find water intrinsically calming and enjoyable.

    Aquatic Therapy Techniques for Autism

    Watsu (Water Shiatsu): Watsu involves passive, flowing movements in warm water, with the therapist supporting the individual throughout. It provides deep relaxation, sensory integration, and physical release, and is particularly beneficial for individuals with significant sensory sensitivities or high anxiety.

    Halliwick Method: The Halliwick Method is a structured ten-point programme for teaching swimming and water independence to people with physical and developmental disabilities. It focuses on water safety, balance, and independent movement in water.

    Structured Swimming Lessons: Adapted swimming lessons, designed with the sensory, communication and motor needs of autistic individuals in mind, develop swimming skills progressively whilst building water confidence and physical fitness.

    Autism Swimming Therapy: Safety in Water

    Drowning is a serious concern for autistic children — research indicates that they are at a disproportionately higher risk of drowning than the general population, partly due to a strong attraction to water and a tendency to wander. Water and swimming therapy should therefore include an explicit focus on water safety awareness alongside therapeutic goals. Specialist swimming programmes for autistic children, led by qualified instructors with ASD training, are available in many communities.

    Benefits of Water Therapy for Autism

    Aquatic therapy delivers a unique set of benefits, including deep sensory regulation and calming, improved gross motor skills and coordination, enhanced body awareness, increased physical fitness, social interaction in group swimming settings, growing confidence and independence in water, and the development of critical water safety skills.

    Home-Based Therapy for Autism

    Home-Based Therapy for Autism

    Home-based therapy for autism delivers therapeutic intervention within the individual’s home environment, either by visiting therapists or by trained parents and caregivers guided by professionals. It promotes the generalisation of skills to real-life settings, increases family involvement, reduces the disruption of frequent clinic travel, and can be highly effective when implemented consistently.

    What is Home-Based Autism Therapy?

    Home-based therapy for autism is any structured therapeutic support that is delivered primarily in the home. This may involve a therapist visiting the home to deliver sessions, or a professionally designed programme that parents implement during daily routines. The home environment offers a uniquely powerful context for therapy: it is the setting in which the individual spends the most time, the place where skills must ultimately be functional, and the environment most familiar and comfortable to the individual.

    Types of Therapies That Can Be Delivered at Home

    Home-Based ABA: ABA is one of the most commonly delivered home-based therapies for autism. Home-based ABA allows skills to be taught directly within the natural environment, making it easier to generalise them to daily life. A BCBA supervises the programme and trains parents and caregivers to implement strategies consistently.

    Occupational Therapy at Home for Autism: Home-based OT embeds therapeutic activities into daily routines — such as dressing, mealtimes and play — making learning practical and immediately relevant. The occupational therapist designs a home programme and visits regularly to review progress and update strategies.

    Speech Therapy at Home: Home-based speech therapy allows communication goals to be practised during natural daily interactions — conversations, shared reading, mealtime chat, and play — which is where communication generalisation ultimately needs to occur.

    Sensory Activities at Home: Parents can implement sensory diets at home under the guidance of an occupational therapist, using simple activities and sensory tools to support their child’s regulation throughout the day.

    Autism Therapies at Home: Types, Benefits, and How-to Guide 

    Setting Up a Home Therapy Space

    An effective home therapy space does not require expensive equipment. Key elements include a calm, low-distraction area for structured activities; access to sensory tools such as a mini trampoline, therapy ball, or sensory bin; a visual schedule on the wall showing the day’s activities; and a selection of motivating toys and materials for teaching and play. A qualified therapist can advise on specific equipment based on the individual’s goals.

    Therapy Toys for Autism

    Therapy toys play an important role in both clinic-based and home-based autism therapy. Sensory toys — such as fidget tools, weighted lap pads, tactile materials, and noise-cancelling headphones — support sensory regulation. Fine motor toys — such as threading beads, construction sets, and playdough — develop hand strength and coordination. Communication aids — including PECS boards, picture communication apps and speech-generating devices — support language development. Cognitive and learning toys — such as sorting games, matching activities and simple puzzles — develop foundational academic skills.

    Also Read: Home-based Treatment vs. Specialised Autism Center: Which is Best for Your Child? 

    Benefits of Home-Based Therapy

    Home-based therapy offers a range of compelling benefits: the child learns in their most familiar and comfortable environment, which reduces anxiety and increases engagement. Skills that are practised in the home generalise more readily to daily life. Family members develop confidence and competence in supporting their child’s development. The intensity of intervention can be greater when parents implement strategies throughout the day. Finally, home-based therapy is often more accessible and affordable than full-time clinic-based provision.

    Choosing the Right Therapy for Your Child
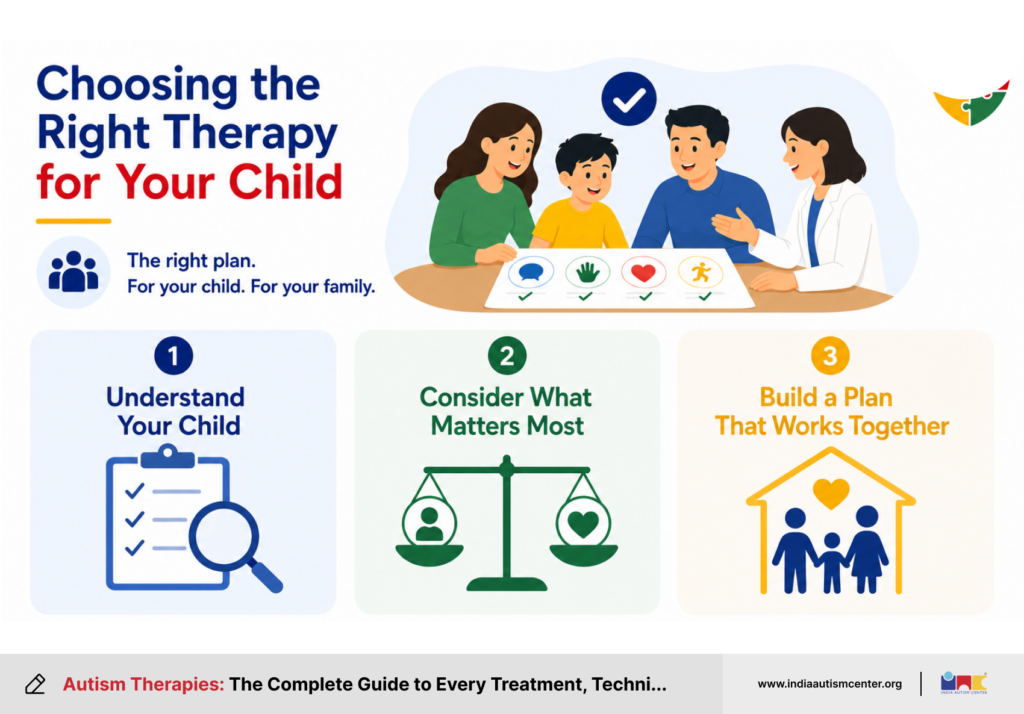
    Choosing the Right Therapy for Your Child

    Choosing the right autism therapy depends on the individual’s specific profile — their age, developmental level, communication abilities, sensory needs, co-occurring conditions, and family goals. The best approach is to work with a qualified multi-disciplinary team to build a personalised, integrated therapy plan that targets the most impactful areas first whilst remaining responsive to the individual’s changing needs over time.

    How to Assess Your Child’s Individual Needs

    Before selecting therapies, families need a clear picture of the individual’s strengths, challenges, learning style and sensory profile. This picture is best built through formal assessment by qualified professionals, supplemented by parents’ own knowledge and observation. Understanding which areas are most significantly impacting daily life — communication, behaviour, sensory processing, motor skills, social participation — helps prioritise where to focus therapeutic effort.

    Factors to Consider When Choosing a Therapy

    Age and Developmental Level: Younger children benefit most from intensive early intervention programmes such as ABA and speech therapy. Older children, adolescents and adults may benefit more from CBT, social skills groups, vocational programmes and life skills training. The developmental level of the individual — rather than their chronological age — should guide therapy selection and approach.

    Severity and Profile of Autism: The specific pattern of strengths and difficulties shapes therapy priorities. A non-verbal child needs intensive communication support; a highly verbal adolescent with significant anxiety may benefit most from CBT and social skills training. Always match therapy type to the individual’s actual profile, not to diagnostic labels or assumptions.

    Co-occurring Conditions: Many autistic individuals have co-occurring conditions such as ADHD, anxiety, dyspraxia, sensory processing disorder, intellectual disability, or epilepsy. These co-occurring conditions significantly influence which therapies are most appropriate and how they are delivered.

    Evidence Base and Research Support: Families should prioritise therapies with a strong, peer-reviewed evidence base — such as ABA, speech therapy, OT and CBT — particularly as the primary components of the therapy plan. Less well-evidenced therapies may still be valuable as complements to core interventions, but should not replace them.

    Therapist Qualifications and Credentials: Always verify that any therapist you engage is registered with the relevant professional body, holds recognised qualifications, and has demonstrated experience working with autistic individuals. Do not hesitate to ask about credentials, supervision, and approaches used.

    Financial Considerations: Autism therapy can be expensive, particularly when accessed privately. Families should explore all available funding options, including public health service entitlements, educational therapy funding, charitable grants, and insurance coverage. Early investment in high-quality therapy often reduces the long-term cost of support.

    Building an Integrated Therapy Plan

    The most effective therapy programme is one in which multiple therapists share goals, communicate regularly, and coordinate their approaches. When building an integrated plan, families should ensure that therapy goals are linked to real-life outcomes (such as communicating at school or managing the supermarket), that all therapists are aware of each other’s work, and that the plan is reviewed at least annually or when significant changes occur.

    For more details, read Key Factors to Consider When Selecting an Autism Therapy Center. 

    Autism Therapy Centres — Finding the Right One
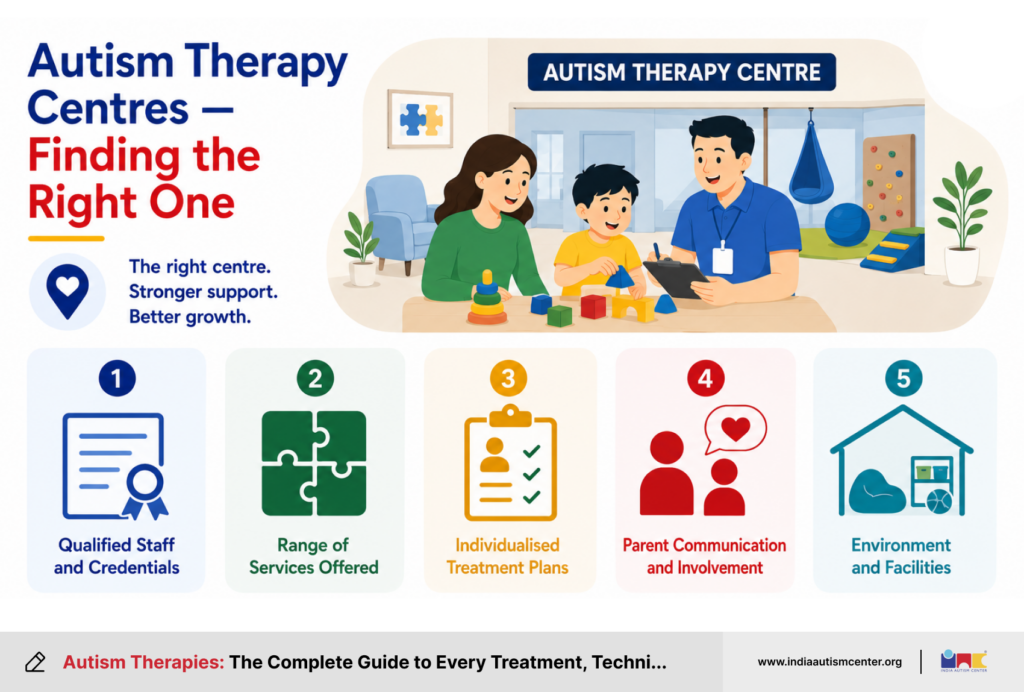
    Autism Therapy Centres — Finding the Right One

    A high-quality autism therapy centre offers a qualified, multi-disciplinary team; individualised assessment and treatment planning; regular parent involvement; transparent progress reporting; and a supportive, sensory-aware environment. When searching for autism therapy centres near you, it is important to assess not just location and availability, but the quality of clinical practice and the extent to which the centre takes a holistic, family-centred approach.

    What to Look for in an Autism Therapy Centre

    • Qualified Staff and Credentials: All therapists at the centre should hold recognised qualifications in their respective disciplines and be registered with relevant professional bodies. The centre should have BCBAs for ABA, registered SaLTs for speech therapy, HCPC-registered OTs, and so on.
    • Range of Services Offered: The best centres offer a comprehensive range of services under one roof — including ABA, speech therapy, occupational therapy, sensory integration therapy, and psychological support — enabling families to access a coordinated multi-disciplinary team without needing to travel to multiple locations.
    • Individualised Treatment Plans: Every individual with autism deserves a treatment plan that is tailored to their unique profile, goals, and circumstances. Be cautious of centres that offer a standardised “one-size-fits-all” programme without conducting a thorough individual assessment first.
    • Parent Communication and Involvement: A good centre will involve families as genuine partners in the therapy process. This means regular progress meetings, home programme guidance, transparent reporting, and a culture in which parents’ observations and concerns are welcomed and acted upon.
    • Environment and Facilities: The physical environment matters enormously for autistic individuals. Look for a centre with sensory-friendly spaces, low-arousal décor, minimal clutter and noise, access to a sensory room or gym, and separate areas for structured work and free play.

    Therapy Across the Lifespan — Age-Specific Guidance
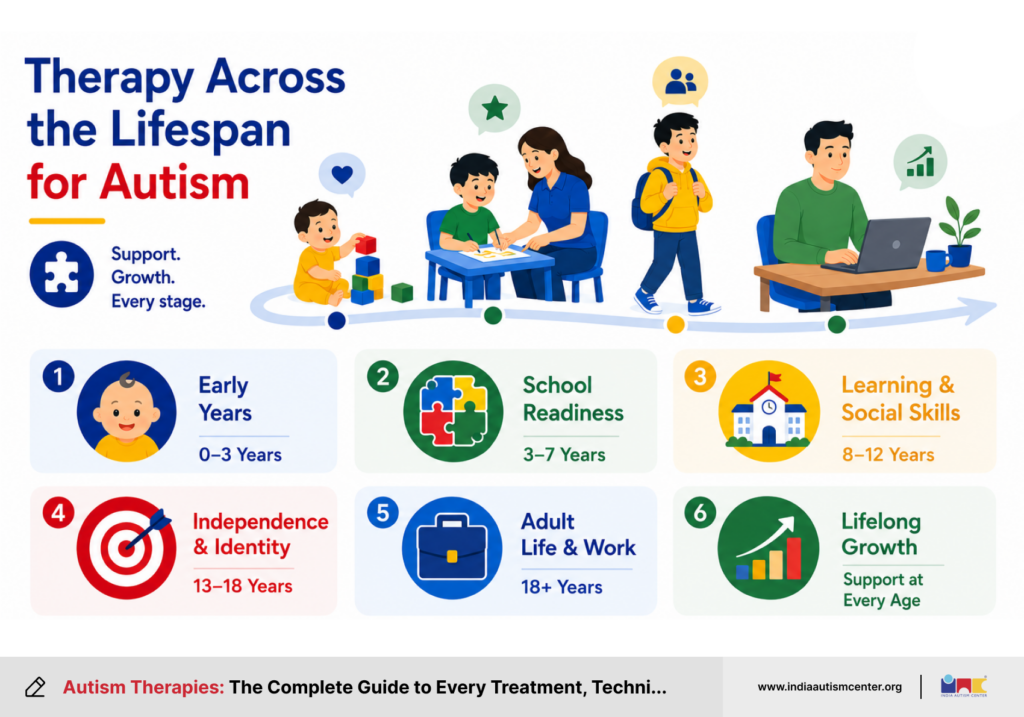
    Therapy Across the Lifespan

    Autism therapy needs change significantly across the lifespan. Early childhood therapy focuses on building communication and social foundations; school-age therapy targets academic participation and peer relationships; adolescent therapy addresses independence, identity, and mental health; and adult therapy focuses on vocational skills, community integration, and sustained wellbeing. Therapy is not only for children — meaningful progress and improved quality of life are achievable at every stage of life.

    Therapy for Toddlers and Infants (0–3 Years)

    This is the most critical period for intervention. The primary goals are to build pre-verbal and verbal communication, promote social engagement and joint attention, support sensory regulation, and involve parents as active therapeutic partners. The most effective approaches at this age are naturalistic, play-based and family-centred — such as the Early Start Denver Model and DIR/Floortime — combined with speech therapy and occupational therapy.

    Therapy for Young Children (3–7 Years)

    As children enter preschool and school, therapy increasingly targets school readiness skills — including fine motor ability, communication with peers, emotional regulation, self-care, and the ability to follow group instructions. ABA, speech therapy, and OT remain central, and social skills groups become increasingly valuable. School inclusion support and collaboration between therapists and educators is essential during this period.

    Therapy for School-Age Children (8–12 Years)

    During middle childhood, academic demands increase and peer relationships become more complex. Therapy at this stage increasingly addresses academic participation (through OT and speech therapy), social skills within peer group contexts (through social skills groups and CBT), and the management of co-occurring challenges such as anxiety, ADHD, and learning differences. Homework and classroom adaptations guided by the OT and SaLT become important components of the support plan.

    Therapy for Adolescents (13–18 Years)

    Adolescence is a period of heightened social complexity, identity development, hormonal change, and increased mental health vulnerability. Therapy for autistic adolescents should address: social and relationship skills in age-appropriate contexts; emotional regulation and anxiety management through CBT; self-advocacy and understanding of one’s own autism; puberty-related education; and transition planning — preparing for post-school education, employment, and independent living.

    Therapy for Adults with Autism

    Autism is a lifelong condition, and therapeutic support continues to be valuable in adulthood. Adults may benefit from vocational therapy to support employment, occupational therapy for independent living skills, CBT for anxiety and depression, social skills coaching for workplace and relationship contexts, and ongoing speech therapy for communication support. The autism community increasingly advocates for adult services that respect autistic identity, support self-determination, and go beyond a solely deficit-based model of care.

    Measuring Therapy Effectiveness and Tracking Progress
    Measuring Therapy Effectiveness and Tracking Progress

    Therapy effectiveness in autism is measured by tracking progress towards specific, measurable goals across communication, behaviour, social skills, sensory processing, and daily living. Progress monitoring uses a combination of standardised assessments, therapist-collected data, and parent and teacher observations. Regular review ensures that therapy remains aligned with the individual’s changing needs and that resources are being directed where they will have the most impact.

    How to Know If Therapy is Working

    Meaningful progress in autism therapy does not always look like dramatic, rapid change. In many cases, it is gradual and incremental. Signs that therapy is working include: the individual demonstrating skills in real-life settings that were previously only seen in the therapy room; fewer and less intense challenging behaviours; increased initiation of communication; greater participation in family, school and community activities; and improved wellbeing and mood. Regular review meetings with the therapy team allow families to gain an accurate picture of progress.

    Setting SMART Goals for Autism Therapy

    All therapy goals should be Specific, Measurable, Achievable, Relevant, and Time-bound (SMART). For example, a SMART speech therapy goal might be: “Within three months, [child’s name] will independently use a two-word request to ask for preferred items in at least 80% of opportunities across three different settings.” SMART goals make it possible to objectively evaluate whether therapy is producing results and to make evidence-based decisions about adjustments.

    Tools and Methods for Tracking Progress

    Therapist Assessments and Reports: Qualified therapists use standardised assessment tools at regular intervals to measure change in specific domains. Examples include the VABS (Vineland Adaptive Behaviour Scales) for adaptive functioning, the PLS (Preschool Language Scales) for communication, and the Sensory Profile 2 for sensory processing.

    Parent Observation Checklists: Parents are in a unique position to observe progress in everyday settings. Structured observation checklists — provided by the therapy team — allow parents to record the frequency and quality of target behaviours at home, providing rich real-world data to complement clinic-based assessments.

    When to Consider Changing Approaches

    If a therapy has been implemented consistently and with high fidelity for a reasonable period — typically three to six months — without evidence of meaningful progress, it is appropriate to reconsider the approach. This does not necessarily mean abandoning the therapy entirely; it may mean adjusting the goals, techniques, intensity, or therapist. Regular, honest review conversations with the therapy team are essential to ensure that every intervention is delivering genuine value.

    Frequently Asked Questions About Autism Therapies

    What is the most effective therapy for autism? 

    There is no single “most effective” therapy for all individuals with autism, because autism presents differently in every person. However, Applied Behaviour Analysis (ABA), Speech and Language Therapy, and Occupational Therapy have the strongest and most consistent evidence bases. Early, intensive, multi-disciplinary intervention tends to produce the best outcomes overall.

    At what age should autism therapy start? 

    Therapy should begin as soon as developmental concerns are identified — ideally before the age of three — to capitalise on the brain’s maximum plasticity. However, meaningful progress is achievable at any age, and it is never too late to begin or add therapy.

    Can autism be treated without medication? 

    Yes. Therapy — rather than medication — is the primary treatment for autism. Medication may be used to manage specific co-occurring symptoms, such as anxiety, ADHD, or sleep disturbance, but it does not address the core features of autism. Therapy is always the foundation of an autism support plan.

    How long does a child need therapy for autism? 

    The duration of therapy varies greatly between individuals. Some children make rapid early gains and require less intensive support as they grow; others benefit from ongoing therapy throughout childhood and into adulthood. Regular reassessment helps determine appropriate therapy intensity and duration at each life stage.

    What is the difference between ABA therapy and speech therapy? 

    ABA therapy is a broad behavioural intervention that targets a wide range of skills, including communication, social skills, behaviour, and daily living. Speech therapy specifically targets communication — including language development, social communication, articulation, and the use of AAC systems. Both are frequently used together, with ABA and speech therapy goals complementing and reinforcing each other.

    Can occupational therapy and ABA be done together? 

    Absolutely. In fact, combining OT and ABA is considered best practice. OT addresses sensory processing, motor skills, and daily living, while ABA targets behaviour, communication, and social skills. The two disciplines share many goals, and each strengthens the other’s outcomes.

    Is music therapy scientifically proven for autism? 

    Yes. Music therapy for autism is supported by a growing and robust evidence base. Multiple systematic reviews and randomised controlled trials have demonstrated significant improvements in social interaction, communication, and emotional wellbeing following music therapy. It is recognised as an evidence-based intervention by international autism and music therapy professional bodies.

    What therapies work best for non-verbal children with autism? 

    Non-verbal children benefit greatly from AAC-focused speech therapy, ABA with a verbal behaviour approach, sensory integration therapy, music therapy, aquatic therapy, and play-based approaches such as DIR/Floortime. The priority is to establish a functional communication system — whether verbal or alternative — as early as possible.

    What is the cost of autism therapy in India? 

    The cost of autism therapy in India varies widely depending on the type of therapy, city, and whether services are accessed publicly or privately. In cities such as Kolkata, Delhi, Mumbai, and Bengaluru, private therapy sessions typically range from ₹500 to ₹3,000 per session,n depending on the therapist’s qualifications and the specialisation required. Government-supported early intervention services are available through the National Trust and other schemes, though availability and quality vary by region. Families are advised to contact their nearest autism resource centre or developmental paediatric service for a current and local guide to costs and funding options.

    Can parents do therapy at home without a therapist? 

    Parents play a vital role in therapy at home, but should always be guided and supervised by a qualified professional. Home programmes designed and overseen by a BCBA, SaLT, or OT allow parents to embed therapy goals into daily routines safely and effectively. Attempting to implement autism therapy without professional guidance risks inconsistency, ineffective strategies, or inadvertent reinforcement of problematic behaviours.

    How do I know which therapy is right for my child? 

    The best way to identify the right therapies for your child is to undergo a comprehensive assessment by a multi-disciplinary team — including a developmental paediatrician, SaLT, OT, and psychologist — who can map your child’s profile and recommend a prioritised, integrated therapy plan. Families are also encouraged to trust their own knowledge of their child and to remain active, informed participants in all therapy decisions.

    Want to know more? Get in touch with us.

    📥 Free download: Printable daily routine chart for autistic children

    Next Steps for Families

    If you are at the beginning of your journey with autism therapies, the following steps will help you to access the right support:

    First, seek a formal diagnostic assessment through your GP, paediatrician, or local developmental service. A diagnosis provides the foundation for accessing appropriate therapy funding and provision. Next, request referrals to a speech and language therapist and an occupational therapist, both of whom can assess your child and begin early intervention whilst you await a full multi-disciplinary assessment. From there, work with your clinical team to develop an integrated therapy plan with clear, functional goals, and review this plan regularly as your child grows and develops. Finally, connect with your local autism community — parent support groups, carer networks, and national organisations — who can provide invaluable guidance, peer support, and advocacy resources.

    Autism therapies are a lifelong journey, not a short-term fix. With the right team, the right approach, and a committed family behind them, every individual with autism has the potential to grow, thrive, and live a meaningful and fulfilling life.


    This guide is intended for informational and educational purposes only. It does not constitute medical advice. Always consult a qualified healthcare professional before beginning any new therapy programme.


  • Animal-Assisted Therapy for Autism: Does It Really Improve Communication?

    Animal-Assisted Therapy for Autism: Does It Really Improve Communication?

    Have you ever watched a child who struggles to speak suddenly light up and say a word to a dog? We have, and it feels like magic. But it is not magic—it is Animal-Assisted Therapy.

    If you are a parent, therapist, or educator working with a child on the autism spectrum, you have likely asked this question: Can animal-assisted therapy improve communication in autism?

    In this article, you will learn exactly how animal therapy for autism works, what the communication benefits of animal-assisted therapy in autism really are, and why so many families are turning to autism communication therapy with animals.

    What Is Animal Assisted Therapy? 

    What Is Animal Assisted Therapy

    First, let me clarify what we mean by Animal-Assisted Therapy. You might confuse it with simply owning a pet. But there is a big difference. Animal-assisted therapy is a structured, goal-directed intervention. 

    A trained therapist works alongside a specially screened animal—often a dog, horse, or even a guinea pig. Together, they target specific skills like speech, eye contact, or social turn-taking.

    I like to think of it as a partnership. The animal acts as a co-therapist. You set clear objectives. For example, you might want a non-verbal child to point at a picture of a “dog” or say “ball.” The animal provides comfort, motivation, and a non-judgmental presence. This is not just playtime. It is therapy with a tail wag.

    So, can animal-assisted therapy improve communication in autism? The short answer is yes, and the long answer is even more exciting. Let me show you why.

    Understanding Communication Challenges in Autism: Why We Need New Tools

    Understanding Communication Challenges in Autism

    Before we explore how animals help, you need to understand the problem. Autism Spectrum Disorder (ASD) often affects two key areas of communication: verbal expression and social pragmatics.

    A child might have delayed speech. They might repeat words (echolalia) without meaning. Or they might struggle with non-verbal cues—like understanding your smile or matching your tone of voice. Some individuals are non-speaking. Others speak fluently but cannot hold a back-and-forth conversation.

    I have worked with children who want to connect but feel overwhelmed by human interaction. A direct question from a therapist can feel threatening. A demand to “look at me” can trigger anxiety. This is where animal therapy for autism steps in. Animals ask for nothing. They simply exist, and that existence creates a safe bridge.

    You see, a dog does not judge a stutter. A horse does not care if you avoid eye contact. This lack of social pressure is exactly why autism communication therapy with animals works so well.

    We also have a blog on Different Autism Therapies, which you can read later for a deeper understanding.

    Want to know more? Get in touch with us.

    How Animal-Assisted Therapy Works: The Science Behind the Bond

    How Animal Assisted Therapy Works

    Now, let me explain the mechanism. You might wonder, “Is this just a nice story, or is there real science?” I can assure you, the research is robust.

    When a person interacts with a calm, friendly animal, their body releases oxytocin. You probably know oxytocin as the “love hormone.” It lowers stress, reduces cortisol, and increases feelings of safety. For an autistic person who is often in a state of high arousal (due to sensory sensitivities or social anxiety), this biochemical shift is huge.

    Lower stress means better learning. Better learning means more communication attempts.

    Additionally, animals provide predictable, rhythmic input. Stroking a dog’s fur or grooming a horse creates a repetitive, calming motion. This can help an autistic person regulate their sensory system. Once regulated, they can focus on a communication task.

    I have seen a non-speaking child hum along to a song about a cat. I have watched a teenager with severe social anxiety order a guinea pig’s food at a pet store — because the animal gave them a reason to speak. These are not miracles. They are the communication benefits of animal – assisted therapy in autism in action.

    Key Communication Benefits of Animal-Assisted Therapy in Autism (A Detailed List)

    Communication Benefits of Animal Assisted Therapy in Autism

    Let me break down the specific ways Animal-Assisted Therapy improves communication. You can use this list to set goals for your own child or client.

    1. Initiating Speech and Vocalisations

    Many autistic children rarely start a conversation. But an animal creates a natural reason to speak. For example, a child might say “more” to request another treat for the dog. I have seen children produce their first intentional word—like “woof” or “go”—during a therapy session with a trained dog. The animal never pressures them. It just waits, and that waiting invites a response.

    2. Improving Non-Verbal Communication

    Communication is more than words. Animal therapy for autism targets eye contact, pointing, and facial expressions. You might ask a child to point to the dog’s nose. Or you might reward a glance toward the handler. Horses, in particular, are sensitive to body language. If a child slumps, the horse stops. The child quickly learns that their posture “speaks” to the animal.

    3. Enhancing Social Turn-Taking

    Conversation requires back-and-forth. Animals are natural at this. You throw a ball; the dog fetches it. You say “sit”; the dog sits. This predictable exchange teaches turn-taking without complex social rules. I often use a simple game: “Your turn to brush the horse, my turn to feed the carrot.” The child internalises the rhythm of interaction.

    4. Reducing Anxiety That Blocks Communication

    Anxiety is the enemy of speech. When you are scared, your brain’s Broca’s area (responsible for language production) shuts down. Animal-Assisted Therapy lowers that anxiety. A child who refuses to speak in a clinical room might whisper to a rabbit in a quiet corner. The animal acts as a social lubricant. You are not talking to a therapist; you are talking about the animal.

    5. Generalising Skills to Real Life

    This is the ultimate goal. You do not want a child to only talk to animals. You want them to talk to people, too. The good news is that skills learned with animals often transfer. I have seen a child learn to ask “Can I pet your dog?” on a walk, and then generalise that sentence structure to ask “Can I play with your toy?” at school. How animals help with autism communication is by providing a bridge from the therapy room to the real world.

    Autism Communication Therapy with Animals: Techniques and Approaches You Can Use

    Techniques and Approaches

    You might be thinking, “This sounds great, but how do we actually do it?” Let me give you specific techniques that therapists use in autism communication therapy with animals.

    The “Ask the Animal” Technique

    Instead of asking the child a direct question (which can feel threatening), you ask them to ask the animal. For example: “Can you ask the dog if he wants a walk?” The child then speaks to the dog. The pressure is off. You can fade this later by having the dog “answer” through the therapist.

    Commenting and Labelling

    You place the child in front of the animal and model simple comments. “Dog is brown.” “Cat is sleeping.” The child is more likely to imitate because the animal is interesting. I use this for children with echolalia—they repeat the phrase happily because they associate it with the furry friend.

    Requesting and Choice-Making

    Hold two items (a brush and a ball). Ask the child to tell the animal what they want. “Do you want to brush the horse or play fetch with the dog?” The child points, signs, or speaks. The animal then receives the action. This teaches purposeful communication.

    Social Stories with Animals

    You can write a social story about a dog who learns to say “hello.” Read it together. Then act it out with the real animal. The child sees that communication has consequences—the dog wags its tail when you speak nicely.

    All of these techniques rely on one core principle: the animal is a motivator. You do not have to force communication. The child wants to interact with the animal, so they find a way.

    Want to know more? Get in touch with us.

    Animal-Assisted Intervention Autism: Which Animals Work Best?

    Animal Assisted Intervention Autism

    You might assume dogs are the only option. But animal-assisted intervention for autism includes many species. Each has unique advantages.

    Dogs

    Dogs are the most common. They are trainable, affectionate, and responsive. A therapy dog remains calm in chaotic environments. They tolerate hugs, loud noises, and sudden movements. I recommend dogs for children who need high-energy interaction—like playing fetch or practising commands.

    Horses

    Horses are powerful for body awareness and non-verbal communication. They mirror your emotions. If you are anxious, the horse becomes tense. This gives immediate feedback. Horses work well for older children and teens who need to regulate their own state before speaking.

    Guinea Pigs and Rabbits

    Small mammals are perfect for non-speaking or highly anxious children. They are quiet, soft, and non-threatening. You can hold them in your lap. I often start with guinea pigs for children who are completely non-verbal. The child just needs to sit and stroke the fur. Eventually, they whisper a sound.

    Cats

    Cats are more independent, but some therapy cats exist. They work for children who prefer calm, still companionship. A cat sitting on a child’s lap can encourage whispering and quiet vocalisations.

    Dolphins

    You may have heard of dolphin-assisted therapy. I want to be honest: the evidence is weak, and there are ethical concerns. I do not recommend it. Stick with land animals that you can interact with regularly.

    Practical Considerations for Starting Animal-Assisted Therapy

    Practical Considerations for Starting Animal Assisted Therapy

    You are probably excited. But let me give you a few practical tips before you start.

    1. Work with a Certified Team

    Animal Assisted Therapy requires a trained therapist and a certified therapy animal. Do not just bring your family pet into a session. Even a gentle dog can get stressed by an autistic child’s sensory behaviours. A certified team knows how to read the animal’s stress signals and keep everyone safe.

    2. Start with Short Sessions

    A 20-minute session is often enough. Autistic children can become overstimulated by the animal’s movements, smells, or sounds. Watch for signs of distress—covering ears, turning away, or tensing up. End on a positive note.

    3. Pair with Speech-Language Therapy

    Animal-assisted therapy is not a replacement for speech therapy. It is a supplement. You should continue working with a speech-language pathologist (SLP). Ideally, the SLP incorporates the animal into their existing goals. I have seen the best results when the animal is a tool in a larger communication plan.

    4. Address Allergies and Phobias

    Some autistic children have severe animal phobias or allergies. Do not force it. You can start with photos, videos, or robotic stuffed animals. Slowly desensitise them. For allergies, consider hypoallergenic breeds (poodles) or animals like reptiles (though they offer less social feedback).

    5. Measure Progress

    Keep a simple log. Note how many vocalisations, gestures, or initiations occur per session. You want to see a clear increase over the weeks. If you do not, reassess the approach.

    What Does the Research Say? Evidence for Communication Benefits

    Evidence for Communication Benefits

    I promised you science, so let me deliver. Multiple studies have examined how animals help with autism communication.

    • A 2019 randomised controlled trial (O’Haire et al.) found that children with ASD who participated in animal-assisted intervention autism showed significantly more social talk and positive affect compared to a control group. They also displayed fewer instances of social withdrawal.
    • A 2021 meta-analysis of 24 studies concluded that animal therapy for autism has a moderate to large effect on social communication behaviours, including joint attention, verbal initiations, and facial orienting.
    • A 2022 study on equine-assisted therapy reported that 80% of autistic participants increased their use of multi-word phrases after 10 sessions.

    I will be transparent: not every study shows massive gains. Some children respond better than others. But the overall direction is clear. Animal-assisted therapy is an evidence-based complementary approach.

    Want to know more? Get in touch with us.

    Addressing Common Concerns and Myths

    Common Concerns and Myths

    Let me tackle a few doubts you might have.

    Myth 1: “The child will only talk to animals, not people.”
    This is rare. In fact, the opposite happens. The animal acts as a stepping stone. Once the child experiences success (e.g., saying “sit” to a dog and seeing the dog sit), they gain confidence. That confidence spills over into human interactions.

    Myth 2: “It is too expensive.”
    Yes, professional Animal-Assisted Therapy can cost $75–$150 per session. But some non-profits offer scholarships. You can also look for “animal-assisted activities” at local libraries or schools—these are less formal but still beneficial. Alternatively, consider adopting a calm pet and working with a volunteer trainer.

    Myth 3: “My child is afraid of animals.”
    Start extremely slowly. Use stuffed animals, then videos, then a very small caged animal (like a hamster). Do not rush. For some children, fear of animals is a sensory issue (unpredictable movement). Desensitisation works, but consult an occupational therapist.

    Don’t forget to read our blog on A Comprehensive Guide to Speech and Language Therapy for Autism

    A Step-by-Step Plan for You to Get Started

    Step-by-Step Plan for

    If you are ready to try Animal Assisted Therapy, here is my recommended roadmap.

    1. Talk to your child’s SLP or behavioural therapist. Ask if they have experience with animals.
    2. Search for a certified therapy animal organisation. In the US, look for Pet Partners or Therapy Dogs International. They can connect you to a local team.
    3. Visit a session without your child first. Watch how the animal interacts. Ask about their safety protocols.
    4. Bring your child for a short meet-and-greet. No goals. Just let them see the animal.
    5. Set three communication goals. For example: “Point to the dog’s nose” or “Say ‘more’ twice per session.”
    6. Commit to 6–8 sessions. Then reassess. Have you seen improvement?

    📥 Free download: Printable daily routine chart for autistic children

    Conclusion: Can Animal-Assisted Therapy Improve Communication in Autism?

    Let me give you my final answer. Yes, animal-assisted therapy can absolutely improve communication in autism. But it is not a magic wand. It is a tool—a beautiful, furry, feathery, or four-legged tool that lowers anxiety, provides motivation, and creates a safe space for practising speech and social skills.

    You have learned how animal therapy for autism works at a biochemical level and the communication benefits of animal-assisted therapy in autism through real-life stories. Now you understand how animals help autism communication by acting as non-judgmental co-therapists. And you have specific techniques for autism communication therapy with animals, plus a guide to different species in animal-assisted intervention for autism.

    I encourage you to take the next step. Call a local therapy animal organization. Ask questions. Observe a session. Your child or client might just find their voice—with a little help from a loyal friend.

    After all, communication is connection. And animals are masters of connection. Let us use their gift to unlock ours.

    Do you have experience with Animal-Assisted Therapy? I would love to hear your story in the comments below. And if you found this article helpful, please share it with another parent or therapist who needs hope.

    Frequently Asked Questions (FAQs)

    Can animal-assisted therapy improve communication in autism?

    Yes, animal-assisted therapy can significantly improve communication in autism. It creates a low-pressure, emotionally safe environment where individuals feel more comfortable expressing themselves. Over time, this leads to better verbal attempts, improved non-verbal cues, and increased social interaction.

    How does animal therapy help autism communication?

    In animal therapy autism, animals act as social bridges. They motivate individuals to communicate through commands, play, and interaction. This encourages both verbal and non-verbal communication while reducing anxiety, making communication more natural and spontaneous.

    Is animal-assisted therapy effective for non-verbal children with autism?

    Yes, animal-assisted therapy for autism can be highly beneficial for non-verbal children. It helps develop foundational communication skills like gestures, eye contact, and sounds. In some cases, it may even support the development of verbal speech over time.

    What animals are commonly used in autism communication therapy with animals?

    Common animals used in autism communication therapy with animals include:

    Small animals like rabbits or guinea pigs (for sensory comfort and gentle interaction)

    Dogs (most widely used for emotional bonding and commands)

    Horses (used in equine therapy for non-verbal communication and confidence)

    What are the benefits of animal-assisted therapy in autism?

    The key benefits of animal-assisted therapy in autism include:

    Enhanced emotional connection and bonding

    Improved communication skills (verbal and non-verbal)

    Reduced anxiety and stress

    Better social interaction and engagement

    Increased motivation to communicate

    Can animal-assisted therapy replace speech therapy for autism?

    No, animal-assisted therapy should not replace speech therapy. Instead, it works best as a complementary approach. When combined with speech and occupational therapy, it enhances overall outcomes, especially in improving communication and social skills.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

  • High Functioning Autism: Meaning, Symptoms, Diagnosis and Support

    High Functioning Autism: Meaning, Symptoms, Diagnosis and Support

    Autism exists on a spectrum. Every autistic person has different abilities, challenges, and support needs. However, you may often hear the term high-functioning autism used to describe people who can communicate, learn, and manage daily tasks with relatively less support.

    In this guide, we will explain what high-functioning autism is, its symptoms, diagnosis, characteristics, and strengths. We will also clarify common questions such as “Is high-functioning autism a disability?” and “Is Level 2 autism high functioning?” and we will cover newer ground: the debate around the term itself, how autism presents in adults, common co-occurring conditions, the Asperger’s history, and what support looks like in India.

    What Is High-Functioning Autism?

    High Functioning Autism

    High-functioning autism is an informal term used to describe individuals on the autism spectrum who have average or above-average intelligence and relatively strong language skills. These individuals can usually speak, read, write, and perform daily living activities independently.

    However, even though they may appear independent, they can still experience difficulties with social interaction, communication, sensory sensitivities, and adapting to change.

    It is important to know that high-functioning autism is not an official medical diagnosis. Doctors diagnose people with Autism Spectrum Disorder (ASD) and classify it based on the level of support required.

    In many cases, people described as having high-functioning autism fall under Level 1 autism, which means they require some support but can function relatively independently.

    Why the Label Is Falling Out of Favour

    The autistic community and many clinicians have raised two serious objections to the high/low-functioning binary.

    First, it masks real challenges. Calling someone “high-functioning” can lead families, schools, and employers to assume that person needs little or no support. In reality, a highly functional autistic person may be exhausted by the daily effort of navigating a neurotypical world, struggling silently with anxiety, sensory overload, or executive dysfunction – challenges that are invisible precisely because the person has learnt to mask them.

    Second, it is reductive about everyone else. The flip side of “high-functioning” is “low-functioning” – a label that strips away the strengths, preferences, and inner life of people who need more support. Autistic self-advocates have pointed out that functioning labels describe what a person does for others, not who they are.

    Identity-First vs Person-First Language

    This debate sits alongside a broader conversation about language. Person-first language (“a person with autism”) was the standard for decades, emphasising that autism is one part of a whole person. Identity-first language (“an autistic person”) is increasingly preferred by many autistic adults and advocacy groups, who see autism as an integral part of identity rather than something separate from the self.

    There is no single correct answer. The most respectful approach is to follow the preference of the individual you are speaking with or about.

    High Functioning Autism vs Autism Spectrum Disorder

    High Functioning Autism vs Autism Spectrum Disorder

    To understand high-functioning autism better, we must first understand Autism Spectrum Disorder.

    ASD is a neurodevelopmental condition that affects how a person communicates, interacts socially, and processes information.

    Key differences

    AspectHigh Functioning AutismAutism Spectrum Disorder
    Medical diagnosisNot an official diagnosisOfficial clinical diagnosis
    Support needsUsually lower support needsVaries from minimal to substantial
    CommunicationUsually verbal and fluentMay range from non-verbal to highly verbal
    IndependenceOften able to live independentlySome individuals require lifelong support

    Even though someone is labelled as having high-functioning autism, they may still face significant daily challenges.

    Want to know more? Get in touch with us.

    Characteristics of High-Functioning Autism

    Characteristics of High-Functioning Autism

    The characteristics of high-functioning autism can vary widely because autism exists on a spectrum. However, many individuals share certain behavioural, social, and cognitive traits. These characteristics may appear mild compared to other forms of autism, but they can still affect everyday life, relationships, and learning.

    Understanding these traits can help parents, educators, and caregivers provide better support.

    1. Social communication challenges

    People with high-functioning autism often find social interaction confusing. They may struggle to interpret facial expressions, tone of voice, gestures, or other non-verbal cues. As a result, they might unintentionally say something that sounds blunt or inappropriate in a social setting.

    2. Difficulty forming and maintaining friendships

    Many individuals want friendships but may not always know how to start conversations or maintain social connections. They might prefer spending time alone or with a small number of trusted people because social situations can feel overwhelming.

    3. Literal interpretation of language

    A common characteristic of high-functioning autism is interpreting language very literally. Idioms, sarcasm, humour, or metaphors can be confusing. For example, phrases like “break a leg” or “spill the beans” may be taken at face value.

    4. Intense focus on specific interests

    Many individuals develop strong interests in particular subjects such as technology, animals, astronomy, mathematics, trains, or history. They may spend a lot of time learning about these topics and can become extremely knowledgeable in their area of interest.

    5. Preference for routines and predictability

    People with high-functioning and low-functioning autism often feel comfortable with structure and routine. Sudden changes in plans, schedules, or environments may cause anxiety or stress because they rely on predictability to feel secure.

    6. Sensory sensitivities

    Another important trait linked to high-functioning autism symptoms is sensory sensitivity. Some individuals may be overly sensitive to sounds, lights, textures, smells, or crowded environments. For example, loud noises, bright lights, or certain clothing fabrics can feel overwhelming.

    7. Strong attention to detail

    Many individuals with high-functioning autism notice patterns, details, or small changes that others might overlook. This ability can be particularly useful in fields such as science, technology, research, engineering, and data analysis.

    8. Emotional regulation difficulties

    Managing emotions can sometimes be challenging. Stress, sensory overload, or unexpected changes may lead to frustration, anxiety, or emotional shutdown. With the right coping strategies and support, individuals can learn ways to manage these feelings effectively.

    9. Advanced vocabulary but unusual communication style

    Some individuals have strong language skills and may use advanced vocabulary for their age. However, their communication style might seem formal, repetitive, or overly detailed, especially when discussing topics they are passionate about.

    10. Difficulty understanding social boundaries

    People with high-functioning autism may struggle with personal space, turn-taking in conversations, or recognising when someone is bored or uncomfortable in a discussion.

    It Is Not in DSM-5 or ICD-11

    High-functioning autism does not appear anywhere in the DSM-5, DSM-5-TR, or ICD-11. It is a colloquial shorthand, not a clinical category. When a clinician formally diagnoses someone, they use Autism Spectrum Disorder and specify a support level (1, 2, or 3) along with any relevant specifiers such as “with or without accompanying intellectual impairment” or “with or without accompanying language impairment.”

    In the DSM-5-TR (published 2022), what most people call high-functioning autism corresponds to ASD Level 1 – the level requiring the least support. The criteria for Level 1 specify noticeable difficulties in social communication that cause real impairment, alongside inflexible behaviour that interferes with functioning, even without an intellectual or language disability.

    High Functioning Autism Symptoms

    High Functioning Autism Symptoms

    Recognising high-functioning autism symptoms early can help parents seek support and interventions.

    Below are some commonly observed symptoms.

    Social symptoms

    • Limited eye contact during conversations
    • Difficulty understanding social rules
    • Preference for being alone rather than in large groups
    • Trouble starting or maintaining conversations

    Communication symptoms

    • Very formal or monotone speech
    • Literal understanding of language
    • Difficulty expressing emotions clearly

    Behavioural symptoms

    • Strong preference for routines
    • Repetitive behaviours or habits
    • Intense interest in a specific topic

    Sensory symptoms

    • Sensitivity to loud sounds or bright lights
    • Discomfort with certain clothing textures
    • Strong reactions to smells or tastes

    Even though symptoms may appear mild, they can still affect school, relationships, and work.

    High Functioning and Low Functioning Autism

    High Functioning and Low Functioning Autism

    The terms high-functioning and low-functioning autism are often used to explain differences in communication abilities, independence, and support needs among autistic individuals. However, these are informal labels, and professionals today prefer focusing on support levels within ASD.

    Still, comparing the two can help parents and caregivers understand the general differences in needs and abilities.

    AspectHigh Functioning AutismLow Functioning Autism
    Communication abilityIndividuals usually have strong verbal communication skills and can hold conversations. However, they may struggle with social cues, tone, or understanding sarcasm and humour.Communication may be limited or non-verbal. Some individuals rely on gestures, pictures, or assistive communication devices to express their needs.
    Intellectual abilityMany individuals have average or above-average intelligence and may perform well academically in structured environments.Some individuals may have intellectual disabilities or learning differences that affect academic progress.
    Social interactionSocial interaction may be challenging due to difficulty understanding body language, emotions, or unspoken social rules. Friendships may require extra support and guidance.Social interaction may be more limited. Individuals may prefer minimal interaction or may not respond to social cues in typical ways.
    Daily living skillsMany people can manage daily activities such as dressing, eating, studying, and working independently with minimal guidance.Individuals often require support with daily activities such as dressing, hygiene, eating, or managing routines.
    Behavioural patternsRepetitive behaviours and strong interests may be present but are usually less disruptive to daily functioning.Repetitive behaviours may be more frequent and visible, such as rocking, hand-flapping, or repeating sounds or words.
    Sensory sensitivitiesSensory sensitivities may exist but can often be managed with coping strategies or environmental adjustments.Sensory sensitivities may be stronger and can cause significant distress in loud, crowded, or highly stimulating environments.
    Education and career opportunitiesMany individuals attend mainstream schools, pursue higher education, and develop careers when provided with appropriate support.Education may involve specialised learning environments, and long-term support may be required for independent living or employment.
    Support needsUsually requires lower levels of support, often associated with Level 1 autism.Usually requires moderate to high levels of support, often associated with Level 2 or Level 3 autism.

    Important Note

    Although the comparison between high-functioning and low-functioning autism can help explain general differences, these labels do not fully capture the complexity of autism. A person described as having high-functioning autism may still face significant challenges in daily life, while someone labelled low-functioning may have strengths and abilities that are often overlooked.

    Therefore, experts now focus more on individual strengths, challenges, and support needs rather than simple functioning labels. This approach helps ensure that every autistic individual receives the support required to live a meaningful and fulfilling life.

    Want to know more? Get in touch with us.

    Is High-Functioning Autism a Disability?

    Is High Functioning Autism a Disability

    Many parents, caregivers, and adults on the spectrum often ask: “Is high-functioning autism a disability?” The answer can sometimes feel complex because it depends on medical definitions, legal frameworks, and individual experiences.

    In general, autism spectrum disorder is classified as a developmental disability. This means it affects how a person communicates, interacts socially, processes information, and adapts to their environment. Even when someone is described as having high-functioning autism, they may still face challenges that affect everyday life.

    However, the level of difficulty can vary widely from one person to another.

    Medical and Clinical Perspective

    From a medical perspective, high-functioning autism still falls under Autism Spectrum Disorder. Autism is considered a neurodevelopmental condition that affects brain development and behaviour.

    Even if an individual has strong language skills or high intelligence, they may still experience:

    • Social communication difficulties: They may struggle to interpret facial expressions, tone of voice, or body language. This can make social interactions confusing or stressful.
    • Sensory sensitivities: Everyday environments such as noisy classrooms, crowded offices, or bright lights may feel overwhelming.
    • Challenges with flexibility and change: Unexpected changes in routines or plans can cause anxiety or emotional stress.
    • Executive functioning difficulties: Tasks such as planning, organising, managing time, or multitasking may require extra effort.

    Legal and Educational Perspective

    In many countries, autism is legally recognised as a disability. This recognition allows individuals to receive support services, accommodations, and protections.

    For example, people with autism may qualify for:

    • Educational accommodations in school or university
    • Workplace adjustments such as flexible schedules or quieter environments
    • Access to specialised therapies and support programmes
    • Disability benefits or social services, where applicable

    Even individuals with high-functioning autism may benefit from these supports, especially in environments that are socially demanding or sensory-heavy.

    Everyday Functioning and Independence

    One reason the question “Is high-functioning autism a disability?” can be confusing is that many individuals with this profile are able to function independently.

    Many people with high-functioning autism:

    • Attend mainstream schools or universities
    • Develop specialised skills or professional expertise
    • Build careers in fields such as technology, science, research, design, or engineering
    • Live independently and manage their daily routines

    However, independence does not mean the absence of challenges. Social expectations, sensory environments, and communication differences may still require effort to navigate.

    Strengths and Abilities

    It is also important to recognise that individuals with high-functioning autism often possess unique strengths. These abilities can be valuable in academic, professional, and creative settings.

    Some commonly observed strengths include:

    • Strong attention to detail
    • Deep focus on specific interests
    • Logical and analytical thinking
    • Excellent memory for facts and patterns
    • Honest and direct communication

    These qualities highlight that autism is not only about limitations but also about different ways of thinking and processing the world. Read our blog on Special Talents and Unique Abilities of autistic individuals.

    A Balanced Perspective

    A Balanced Perspective

    Instead of focusing only on whether high-functioning autism is a disability, it is more helpful to view autism through a strengths-and-support lens.

    Every autistic individual has:

    • Areas where they excel
    • Areas where they need support
    • Unique ways of learning and communicating

    Recognising both the challenges and the strengths allows families, educators, and communities to provide meaningful support while encouraging independence and personal growth.

    In this way, understanding high-functioning autism becomes less about labels and more about creating environments where autistic individuals can thrive, contribute, and live fulfilling lives.

    Legal and Educational Perspective

    In many countries, autism is legally recognised as a disability. This recognition allows individuals to receive support services, accommodations, and protections.

    For example, people with autism may qualify for:

    • Educational accommodations in school or university
    • Workplace adjustments such as flexible schedules or quieter environments
    • Access to specialised therapies and support programmes
    • Disability benefits or social services, where applicable

    Even individuals with high-functioning autism may benefit from these supports, especially in environments that are socially demanding or sensory-heavy.

    Everyday Functioning and Independence

    One reason the question “Is high-functioning autism a disability?” can be confusing is that many individuals with this profile are able to function independently.

    Many people with high-functioning autism:

    • Attend mainstream schools or universities
    • Develop specialised skills or professional expertise
    • Build careers in fields such as technology, science, research, design, or engineering
    • Live independently and manage their daily routines

    However, independence does not mean the absence of challenges. Social expectations, sensory environments, and communication differences may still require considerable effort to navigate.

    Strengths and Abilities

    It is also important to recognise that individuals with high-functioning autism often possess unique strengths:

    • Strong attention to detail
    • Deep focus on specific interests
    • Logical and analytical thinking
    • Excellent memory for facts and patterns
    • Honest and direct communication

    A Balanced Perspective

    Instead of focusing only on whether high-functioning autism is a disability, it is more helpful to view autism through a strengths-and-support lens. Every autistic individual has areas where they excel, areas where they need support, and unique ways of learning and communicating.

    Is Level 2 Autism High Functioning?

    Is Level 2 Autism High Functioning

    Many parents and caregivers often ask: “Is Level 2 autism high functioning?” The short answer is no; Level 2 autism is generally considered high functioning. However, understanding why requires looking at how ASD is classified today.

    Modern diagnostic systems categorise autism into three levels based on the amount of support an individual requires in daily life. These levels do not measure intelligence alone. Instead, they focus on social communication challenges, behaviour patterns, and independence in everyday activities.

    Autism LevelDescriptionSupport Needs
    Level 1 AutismIndividuals show noticeable difficulties in social communication but can usually speak, learn, and live relatively independently. This level is often associated with high-functioning autism.Requires support in social interaction, organisation, and adapting to change.
    Level 2 AutismIndividuals experience more pronounced challenges in communication, behaviour, and flexibility. Social difficulties are clearly noticeable even with support.Requires substantial support for communication, social interaction, and daily routines.
    Level 3 AutismIndividuals show severe challenges in verbal and non-verbal communication and may have significant behavioural differences.Requires very substantial support in most areas of life.

    Why Level 2 Autism Is Not Considered High Functioning

    People with Level 2 autism usually require more structured support than individuals described as having high-functioning autism. Their challenges may be more visible and can affect everyday activities such as school participation, communication, and social relationships.

    Some common characteristics of Level 2 autism include:

    • Significant social communication difficulties: Individuals may struggle to start or maintain conversations. Even when they speak, their communication may appear limited or unusual in social settings.
    • Noticeable behavioural differences: Repetitive behaviours, intense interests, or strict routines may interfere with daily functioning if changes occur.
    • Difficulty adapting to change: Unexpected transitions, schedule changes, or new environments may cause distress or anxiety.
    • Greater need for structured support: Individuals may benefit from specialised educational programmes, therapy, and guided routines to manage everyday tasks.

    Important Things to Remember

    Although Level 2 autism is not typically considered high functioning, it is important to remember that autism is a spectrum. Every individual has a unique set of strengths and challenges.

    For example, someone with Level 2 autism may still have:

    • Strong visual thinking abilities
    • Deep knowledge in specific subjects
    • Creative talents in art, music, or design
    • Strong memory and attention to detail

    At the same time, they may require consistent support to navigate social situations, communication, and daily responsibilities.

    Want to know more? Get in touch with us.

    How to Diagnose High-Functioning Autism

    How to Diagnose High-Functioning Autism

    Parents often ask how to diagnose high-functioning autism. Because it is not an official diagnosis, clinicians diagnose ASD instead.

    The diagnostic process usually includes:

    Developmental screening

    Doctors check whether the child is reaching developmental milestones such as speech, social interaction, and motor skills.

    Behavioural observations

    Specialists observe how the child communicates, interacts, and responds to social situations.

    Parent and teacher interviews

    Parents and teachers provide insights into behaviour patterns and developmental history.

    Standardised diagnostic tools

    Clinicians may use structured assessments to evaluate autism traits.

    Multidisciplinary evaluation

    A team including psychologists, speech therapists, and developmental specialists may conduct a detailed evaluation.

    Early diagnosis allows children to receive therapies that improve communication, independence, and quality of life.

    Benefits of High-Functioning Autism

    Benefits of High-Functioning Autism

    Although autism comes with challenges, there are also several benefits of high-functioning autism. Many individuals possess unique strengths that can help them succeed academically and professionally.

    Exceptional focus

    Many people can concentrate deeply on topics that interest them.

    Strong memory

    They may remember facts, numbers, and details extremely well.

    Analytical thinking

    Logical reasoning and pattern recognition are often strong abilities.

    Creativity and innovation

    Some individuals show remarkable creativity in art, music, or technology.

    Honesty and direct communication

    They often communicate honestly and value clarity.

    Passion for learning

    Strong curiosity about specific subjects can lead to expertise.

    High-Functioning Autism in Adults

    High-Functioning Autism in Adults

    High-functioning autism in adults is far more common than most people realise – and far more frequently missed. Many adults living with autism spectrum disorder today grew up without a diagnosis, simply because awareness was lower and diagnostic criteria were narrower.

    Why Adults Are Often Diagnosed Late

    The single biggest reason is masking, also called camouflaging. From a young age, many autistic people – particularly women and girls – learn to observe and imitate neurotypical social behaviour. They make eye contact because they have learnt it is expected, not because it feels natural, and script conversations in advance. They suppress stimming in public. From the outside, they appear to be managing perfectly well.

    This performance is exhausting. And it hides the underlying profile so effectively that even experienced clinicians can miss it. Research consistently shows that autistic women and girls are diagnosed significantly later than men and boys, often not until their 20s, 30s, or even 40s – sometimes only after a child of theirs receives a diagnosis.

    How Adult High-Functioning Autism Presents Differently

    In adults, the presentation of high-functioning autism often looks less like the childhood picture and more like a cluster of secondary effects:

    • Autistic burnout – a state of chronic exhaustion, reduced functioning, and withdrawal that results from sustained masking and sensory overload. It is distinct from depression, though it can trigger it.
    • Anxiety disorders – social anxiety in particular is extremely common, often the presenting complaint that first brings an adult to a mental health professional.
    • Depression – frequently a downstream effect of years of feeling different, misunderstood, or socially excluded without knowing why.
    • Relationship difficulties – patterns of miscommunication, difficulty reading partner cues, or intense relationships that become overwhelming.

    Many adults reach a diagnosis only after years of being told they have anxiety, depression, borderline personality disorder, or ADHD – all of which can co-occur with autism but do not explain the full picture.

    The Employment Challenge

    Employment is one of the starkest markers of the gap between potential and outcome for autistic adults. Studies consistently show that autistic adults – including those with strong cognitive abilities – face significant barriers in the workplace. Figures on unemployment among autistic adults vary widely across studies, but the pattern is consistent: autistic people are substantially underemployed relative to their skills and qualifications. Social demands of interviews, open-plan offices, unwritten workplace rules, and sensory environments all create barriers that have nothing to do with job competence.

    The challenges are real and well-documented. With the right workplace adjustments – remote working options, clear written communication, structured roles, and sensory accommodations – many highly functional autistic adults thrive professionally.

    Support and Interventions for High-Functioning Autism

    Support and Interventions for High-Functioning Autism

    Although individuals with high-functioning autism may appear independent, many still benefit from structured support and targeted interventions. These supports help them develop stronger communication skills, manage sensory sensitivities, build relationships, and navigate daily life more confidently.

    Early intervention and the right strategies can significantly improve long-term outcomes. Support does not aim to “change” the individual but to help them build skills, manage challenges, and use their strengths effectively.

    Below are some of the most helpful interventions for people with high-functioning autism symptoms.

    Behavioural Therapy

    Behavioural therapies focus on helping individuals understand and manage their behaviours, emotions, and social interactions.

    These therapies often teach practical skills such as:

    • Understanding social rules and expectations
    • Managing frustration or anxiety
    • Improving attention and focus
    • Learning positive coping strategies

    Structured behavioural programmes can help individuals gradually develop confidence in social situations and daily activities.

    Speech and Communication Therapy

    Even when individuals have strong vocabulary and language skills, high-functioning autism symptoms can include difficulties with social communication.

    Speech and communication therapy helps individuals learn:

    • How to start and maintain conversations
    • How to interpret tone of voice and facial expressions
    • How to understand humour, sarcasm, and figurative language
    • How to express emotions and thoughts more clearly

    This type of therapy improves everyday communication, which can strengthen friendships, school participation, and workplace interactions.

    Occupational Therapy

    Occupational therapy focuses on building practical life skills and sensory regulation.

    Many individuals with high-functioning autism experience sensory sensitivities or challenges with everyday routines. Occupational therapists help individuals:

    • Manage sensory sensitivities to sound, light, textures, or movement
    • Improve motor coordination and handwriting
    • Develop independence in daily activities such as dressing, eating, or organising tasks
    • Learn calming techniques to reduce sensory overload

    These skills help individuals function more comfortably at home, school, or work.

    Social Skills Training

    One of the most common characteristics of high-functioning autism is difficulty navigating social situations. Social skills training provides structured guidance to help individuals understand social behaviour.

    These programmes may teach:

    • How to greet people and start conversations
    • How to maintain eye contact appropriately
    • How to recognise emotions in others
    • How to take turns during conversations
    • How to resolve conflicts with peers

    Many programmes use role-playing, group activities, and real-life scenarios to help individuals practise these skills.

    Educational Support

    Students with high-functioning autism often attend mainstream schools but may still benefit from certain learning supports.

    Educational adjustments may include:

    • Structured classroom routines
    • Clear instructions and visual aids
    • Extra time for assignments or exams
    • Quiet spaces to manage sensory overload
    • Support from special educators or counsellors

    These adjustments help create a learning environment where students can focus on their strengths and academic development.

    Psychological Support and Counselling

    Some individuals with high-functioning autism experience anxiety, stress, or social frustration. Counselling or psychological therapy can help them develop emotional awareness and coping strategies.

    Therapy may focus on:

    • Managing anxiety and stress
    • Building self-confidence
    • Developing emotional regulation skills
    • Understanding social expectations

    Mental health support can be especially helpful during adolescence and adulthood when social and academic pressures increase.

    Family Education and Parent Training

    Parents and caregivers play a crucial role in supporting individuals with high-functioning autism. Parent education programmes provide guidance on how to support development at home.

    These programmes may help parents:

    • Understand high-functioning autism symptoms more clearly
    • Respond effectively to behavioural challenges
    • Create supportive routines and environments
    • Encourage independence and social development

    When families are actively involved, interventions become more effective and consistent.

    Skill Development and Vocational Training

    As individuals grow older, life skills and vocational training become increasingly important.

    These programmes help individuals develop skills such as:

    • Time management and organisation
    • Workplace communication and teamwork
    • Problem-solving and decision-making
    • Job-specific technical skills

    Many adults with high-functioning autism thrive in careers that value attention to detail, logical thinking, and specialised expertise.

    📥 Free download: Printable daily routine chart for autistic children

    Common Comorbidities in High-Functioning Autism

    Common Comorbidities in High-Functioning Autism

    High-functioning autism rarely travels alone. Most autistic individuals – particularly those with lower support needs – live with one or more co-occurring conditions. In fact, it is often a comorbidity, not autism itself, that first brings an adult to a clinician’s attention.

    Anxiety Disorders

    Anxiety is the most common comorbidity in high-functioning autism, affecting an estimated 40–50% of autistic individuals. Social anxiety disorder is particularly prevalent – not surprising given the daily effort of navigating social situations that do not come naturally. Generalised anxiety, specific phobias, and panic disorder also occur at elevated rates. Anxiety in autistic people can present atypically, making it harder to identify and treat.

    ADHD

    Attention Deficit Hyperactivity Disorder (ADHD) co-occurs with autism in a significant proportion of individuals – estimates range from 30% to 80% depending on the study population. The two conditions share some surface features (difficulty with sustained attention, impulsivity, sensory sensitivity) but are neurobiologically distinct. When both are present, the combined profile can make daily functioning considerably more demanding. Until 2013, the DSM-IV actually prohibited a dual diagnosis of autism and ADHD; the DSM-5 removed this restriction, allowing clinicians to diagnose both when warranted.

    OCD

    Obsessive-Compulsive Disorder (OCD) is another frequent companion. The repetitive behaviours seen in autism (routines, rituals, restricted interests) can superficially resemble OCD compulsions, but they are functionally different – autistic repetitive behaviours are often calming and pleasurable, whereas OCD compulsions are driven by distress. That said, true OCD does occur at higher rates in autistic populations. Research has pointed to a shared neurobiological pathway involving serotonin dysregulation, which may partly explain the overlap. This distinction matters clinically because the treatments differ.

    Tourette Syndrome

    Tourette syndrome and other tic disorders occur more frequently in autistic individuals than in the general population. The co-occurrence is well-established in the literature, though the mechanisms are not fully understood. Tics can add to the social complexity already faced by a highly functional autistic person, particularly in school and workplace settings.

    Depression

    Depression is both a comorbidity and a consequence. Years of social rejection, masking, burnout, and feeling misunderstood take a toll. Depression in autistic adults is often under-recognised because it may present differently – as increased rigidity, withdrawal from special interests, or heightened sensory sensitivity rather than the classic low mood and tearfulness that clinicians look for.

    Sensory Processing Disorder

    Many autistic individuals experience sensory processing difficulties that go beyond what is captured in the standard autism diagnostic criteria. Hypersensitivity (over-responsiveness) or hyposensitivity (under-responsiveness) to sound, light, touch, taste, smell, or proprioception can significantly affect daily life. Occupational therapists who specialise in sensory integration can help develop practical strategies.

    A note for parents and caregivers: if your child or family member has received diagnoses of anxiety, ADHD, or OCD but the picture still does not feel complete, it is worth asking whether an autism assessment has been considered. Comorbidities are frequently the presenting door through which autism is eventually recognised.

    High-Functioning Autism and Asperger’s Syndrome

    High-Functioning Autism and Asperger's Syndrome

    If you have been reading about high-functioning autism for any length of time, you will have come across the term Asperger’s Syndrome. The two are closely related – but they are not identical, and the history behind the label is more complicated than most people realise.

    Historical Background

    Asperger’s Syndrome was first described by Austrian paediatrician Hans Asperger in 1944, based on his observations of a group of children in Vienna who showed social difficulties, intense specific interests, and strong language abilities. His work remained largely unknown outside German-speaking countries until Lorna Wing brought it to international attention in 1981.

    By 1994, Asperger’s Syndrome had been formally included in the DSM-IV as a separate diagnosis – distinct from autistic disorder and from what was then called high-functioning autism.

    The Key Clinical Difference

    The primary distinction between Asperger’s Syndrome and high-functioning autism under the old DSM-IV criteria was early language development.

    • Asperger’s Syndrome: No clinically significant delay in spoken language. Children typically spoke on time or early.
    • High-Functioning Autism: A history of language delay in early childhood, even if language later developed to a strong level.

    Both groups shared the core features of social communication difficulties, restricted interests, and repetitive behaviours. The language history was the diagnostic dividing line.

    The 2013 DSM-5 Merger

    In 2013, the DSM-5 collapsed Asperger’s Syndrome, high-functioning autism, and several other previously separate diagnoses (including PDD-NOS and childhood disintegrative disorder) into a single umbrella: Autism Spectrum Disorder. The rationale was that the boundaries between these categories were clinically unreliable – different clinicians in different settings were applying them inconsistently.

    Under the current system, someone who would previously have been diagnosed with Asperger’s Syndrome would now receive a diagnosis of ASD Level 1 – the same category as high-functioning autism.

    Why Some People Still Identify with the Asperger’s Label

    The merger was clinically sensible, but it was not universally welcomed. Many people who had built their identity around an Asperger’s diagnosis – who had found community, self-understanding, and belonging through that label – felt it had been taken away from them.

    This is not a trivial concern. Identity matters. Many adults continue to self-identify as having Asperger’s, and many advocacy and peer-support communities still use the term. Clinicians generally respect this, even while using ASD Level 1 in formal documentation.

    The Hans Asperger Controversy

    The legacy of the Asperger’s label has been further complicated by historical scholarship published from 2010 onwards – and most prominently in a 2018 paper by Czech-Austrian historian Herwig Czech in the journal Molecular Autism.

    Czech’s research, drawing on previously unexamined archival records from Vienna, found that Hans Asperger was not the principled protector of vulnerable children that his earlier reputation suggested. The evidence indicates that Asperger joined Nazi-affiliated organisations, publicly endorsed race-hygiene ideas consistent with the regime’s ideology, and referred at least some children to the Am Spiegelgrund clinic – a facility in Vienna where children deemed “uneducable” were killed as part of the Nazi child euthanasia programme.

    It is important to be precise: Asperger was not a member of the Nazi Party, and historians disagree about how much he knew about the killing programme at the time of specific referrals. The picture that emerges is of a careerist who accommodated the regime and benefited from it – not a straightforward hero, but not necessarily a knowing participant in mass murder either.

    This history does not change the clinical validity of the traits Asperger described, or the value of the community that formed around his name. But it does raise legitimate ethical questions about whether a diagnosis should carry his name. Some autistic advocates have called for the term to be retired for this reason. Others feel that the community built around it is too important to discard.

    We present this history factually, without taking a position. Families and individuals deserve to know it.

    Read Asperger’s vs. Autism – What’s the difference?

    Conclusion

    Understanding high-functioning autism helps parents, educators, and society support autistic individuals more effectively.

    While the term is widely used, it is important to remember that autism is a spectrum. Some individuals may need minimal support, while others require more structured assistance.

    By recognising high-functioning autism symptoms, understanding how to diagnose high-functioning autism, and focusing on strengths and support, we can help autistic individuals lead meaningful and fulfilling lives.

    Frequently Asked Questions (FAQs)

    What is high-functioning autism?

    High-functioning autism is an informal term used to describe autistic individuals who have strong language skills and can manage daily life with minimal support.

    Is high-functioning autism a disability?

    Yes, autism is considered a developmental disability, but many individuals with high-functioning autism live independently and pursue successful careers.

    Is level 2 autism high functioning?

    No. Level 2 autism usually requires substantial support, while high-functioning autism is typically associated with Level 1 autism.

    How to diagnose high-functioning autism?

    Doctors diagnose Autism Spectrum Disorder through developmental screening, behavioural observation, and comprehensive clinical assessments.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

    Useful Sources

    American Psychiatric Association. Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR). 2022

    Baron-Cohen, S. et al. “The Autism-Spectrum Quotient (AQ): Evidence from Asperger Syndrome/High-Functioning Autism, Males and Females, Scientists and Mathematicians.” Journal of Autism and Developmental Disorders, 2001

    Czech, H. “Hans Asperger, National Socialism, and ‘race hygiene’ in Nazi-era Vienna.” Molecular Autism, 2018.

    National Trust for the Welfare of Persons with Autism, Cerebral Palsy, Mental Retardation and Multiple Disabilities

    Rehabilitation Council of India. Central Rehabilitation Register and norms

    Cambridge Autism Research Centre. Autism-Spectrum Quotient (AQ) – Adult version

  • Autism Challenges Explained: What to Know in 2026

    Autism Challenges Explained: What to Know in 2026

    As someone who cares about autism, whether you are a caregiver, family member, educator, or someone on the autism spectrum, you’ve probably been worried about the challenges in autism:

    • What are the real challenges in autism?
    • How do these challenges affect daily life?
    • What can we do to support autistic individuals better?

    In this article, I’ll take you through a detailed, compassionate, and educational journey into the challenges of autism in everyday life. I’ll break down the key areas where autistic people often struggle, what these struggles look like day to day, and how you can understand them better.

    What Is Autism Spectrum Disorder?

    What Is Autism Spectrum Disorder?

    Autism Spectrum Disorder (ASD) is a neurodevelopmental condition that affects the way a person thinks, communicates, and experiences the world. It is called a “spectrum” because no two autistic individuals are the same. Each person has unique strengths, needs, and challenges.

    At the core of autism, people may face differences in social communication, sensory processing, behaviour, and learning, but how these show up can vary widely from person to person.

    Social Communication Challenges

    Social Communication Challenges

    One of the most discussed challenges autistic people face involves communication and social interaction.

    Autistic individuals often find it hard to:

    • Understand social cues like facial expressions or tone of voice.

    • Maintain eye contact comfortably.

    • Take part in back-and-forth conversations.
    • Interpret sarcasm or indirect speech.

    Sometimes, a person may not speak at all. Others may have advanced speech but still struggle with the social rules of communication.

    Why is it a challenge in everyday life

    You might feel misunderstood or unable to express your own thoughts clearly. This can lead to frustration, social isolation, or anxiety, especially in group settings.

    That doesn’t mean autistic people don’t want connection. It means the way they connect is different. Many communicate through alternative methods, gestures, pictures, technology, or Augmentative and Alternative Communication (AAC).

    Want to know more? Get in touch with us.

    Sensory Processing: A Hidden Everyday Challenge

    Hidden Everyday Challenge of Sensory Processing

    Another major set of challenges in autism involves sensory sensitivities. Many autistic individuals process sensory information differently from others.

    This can include:

    • Hypersensitivity — extreme sensitivity to lights, sounds, textures, or smells.
    • Hyposensitivity — needing more intense sensory input to feel comfortable.

    These sensory reactions are more than just preferences — they can deeply affect everyday life.

    Imagine trying to concentrate when fluorescent lights make your head throb, or eating dinner when food textures feel unbearable. These are real struggles for many autistic people.

    Challenges of autism in everyday life include:

    • Overwhelm in crowded or noisy places.
    • Avoiding certain foods because of how they feel.
    • Difficulty wearing certain clothes due to texture sensitivity.

    Sensory overload can also lead to shutdowns or meltdowns — intense reactions that are often misunderstood by others. These reactions are not “bad behaviour”; they are nervous system responses to overwhelming stimuli.

    Routine, Change, and Predictability

    Routine, Change, and Predictability

    Many autistic people prefer structure and routine. Predictability creates safety. Change can feel threatening or disorienting.

    Imagine if your daily schedule suddenly changed — like missing your usual bus, or plans shifting at the last minute. For someone with autism, this can be far more stressful than it sounds.

    Some common everyday challenges include:

    • Anxiety when routines are interrupted.
    • Stress about new environments or unfamiliar tasks.
    • Resistance to change, even when the change is positive.

    Routines help reduce anxiety and offer a sense of control. Without routine, the brain has to work harder to predict what will happen next — and that extra effort can be exhausting.

    Executive Functioning and Daily Tasks

    Executive Functioning and Daily Tasks

    Executive functioning is a set of mental skills — like planning, organising, initiating tasks, and following through.

    Many autistic individuals struggle with one or more of these skills. That can make everyday tasks feel overwhelming:

    • Planning a schedule
    • Organizing belongings
    • Starting a task (even when you want to)
    • Switching between tasks

    This is another challenge in autism that often goes unnoticed because it affects thinking processes rather than outward behaviours.

    For example, something as simple as cooking dinner can become stressful if planning, timing, and multi-step thinking are hard.

    Behaviour Challenges in Autism

    Behaviour Challenges in Autism

    When we talk about behaviour challenges in autism, we’re not talking about “bad” behaviour. Rather, we’re talking about behaviours that arise from unmet needs or communication differences.

    Behaviour challenges may include:

    • Aggression or self-injury
    • Repetitive behaviours (like rocking or hand-flapping)
    • Difficulty regulating emotions
    • Shutdowns or meltdowns when overwhelmed

    These behaviours often occur because something else is triggering stress — sensory overload, anxiety, or difficulty expressing a need.

    For example, a child may hit when they are overstimulated and unable to communicate that they need a quiet space.

    Helpful strategies usually involve:

    • Understanding the cause of the behaviour
    • Building communication tools
    • Creating predictable routines
    • Teaching self-regulation skills

    Behaviour challenges in autism are often a form of communication — a way of showing distress when words aren’t enough.

    Want to know more? Get in touch with us.

    Sleep and Biological Challenges

    Sleep and Biological Challenges

    Sleep problems are very common among autistic individuals. Research indicates that up to 80% of autistic children experience sleep disturbances, compared to 25-40% in the general population.

    These challenges can include:

    • Trouble falling asleep
    • Frequent nighttime waking
    • Irregular sleep cycles

    Poor sleep affects energy, emotion regulation, concentration, and behaviour the next day.

    Sleep issues might occur due to sensory sensitivities, anxiety, or neurological differences. Addressing them often involves creating calming bedtime routines and sensory-friendly sleep environments.

    Gastrointestinal and Eating Challenges

    Gastrointestinal and Eating Challenges

    Many autistic people experience gastrointestinal (GI) problems such as constipation, stomach pain, or diarrhoea. Research suggests that GI symptoms can occur in nearly half to most autistic children.

    Additionally, food refusal is common and is often linked to sensory sensitivities — certain textures, smells, or combinations may be intolerable.

    In everyday life, this can make mealtime stressful or limited, affecting nutrition, family routines, and social eating situations.

    Social Isolation and Misunderstanding

    When you struggle with social communication and sensory processing, everyday environments — classrooms, workplaces, public places can feel intimidating.

    Autistic people often experience:

    • Misunderstandings in conversations
    • Difficulty making or keeping friends
    • Feeling left out or unseen

    Many adults with autism report stress when navigating social cues that others take for granted.

    Social differences are one of the hardest challenges autistic people face because they affect connection, something we all need.

    Autism and Food Refusal

    Autism and Food Refusal

    Food refusal, a significant concern for many families with autistic individuals, is often linked to sensory sensitivities, rigid eating habits, or gastrointestinal discomfort. In the Indian context, where traditional diets may differ significantly from the Western norm, addressing food-related challenges about autism and food refusal requires a culturally sensitive approach.

    We work closely with nutritionists and behavioural therapists to develop personalised plans that accommodate sensory preferences while ensuring balanced nutrition. By promoting a nuanced understanding of food-related challenges, we aim to empower families to create nourishing environments for their autistic loved ones.

    In India, where cultural nuances play a significant role in shaping behavioural expectations, we emphasise culturally competent approaches to autism and behaviour problems. By working with psychologists and behaviour analysts, we equip families and caregivers with tools to navigate and address challenging behaviours, fostering a more inclusive and understanding society.

    Here is our guide on Autism Therapies at Home, which might help you address some of these challenges.

    Autism Challenges in the Classroom

    Autism Challenges in the Classroom

    School can be one of the most demanding environments an autistic child faces – and one of the least adapted for how their brain works. If your child comes home exhausted, dysregulated, or refusing to go back, the classroom environment itself may be the source.

    Sensory Overload in School

    A typical Indian classroom is a sensory minefield: fluorescent lights that flicker, 30 children talking at once, the smell of chalk and tiffin boxes, a uniform that scratches. For an autistic child with sensory sensitivities, this isn’t background noise – it’s a constant physiological assault.

    Sensory overload reduces attention, increases anxiety, and makes learning nearly impossible. It also frequently triggers meltdowns that teachers misread as behavioural problems.

    What helps:

    • Seating away from high-traffic, noisy areas
    • Permission to use noise-cancelling headphones during independent work
    • Access to a calm-down space – even a quiet corner
    • Reduced visual clutter around the child’s desk

    Social Interaction Difficulties with Peers

    Playground and lunch break can be the hardest parts of the school day. Unstructured social time, implicit social rules, rapidly shifting group dynamics – these are exactly the situations autistic children find most confusing and exhausting.

    Peer rejection and bullying are real risks. Autistic children are significantly more likely to be bullied, and the social isolation compounds the mental health challenges they already face.

    What helps:

    • Structured social activities with clear rules (board games, shared projects) rather than open-ended play
    • A trusted peer buddy system
    • Teacher awareness of social dynamics – not just academic performance

    Executive Function Challenges

    Transitions, task-switching, starting a new activity, organising materials, remembering what homework was set – these are all executive function tasks, and they’re consistently difficult for autistic students.

    This is not defiance. A child who can’t start their essay isn’t being lazy. Their brain is genuinely struggling with task initiation.

    What helps:

    • Visual schedules showing the day’s sequence
    • First/then boards for transitions (“First maths, then break”)
    • Chunking large tasks into small, numbered steps
    • Extra time – not as a special favour, but as a reasonable accommodation
    • Advance notice of any change to routine

    Communication Barriers with Teachers

    Many autistic children struggle to ask for help, especially in a busy classroom. They may not be able to formulate the question quickly enough, may fear the social exposure of speaking up, or may genuinely not know what they don’t understand.

    What helps:

    • A private signal system (a card on the desk) the child can use to indicate they need help without speaking
    • Written instructions alongside verbal ones
    • Regular, low-key check-ins from the teacher rather than waiting for the child to initiate

    Special Interests: Challenge and Strength

    A child who can talk for 45 minutes about dinosaurs but won’t engage with the maths worksheet is not being difficult. Special interests are a genuine neurological feature – and a powerful teaching tool.

    The challenge is when rigidity around interests disrupts learning. The strength is that interest-based learning dramatically increases engagement and retention. A maths problem about dinosaur weights is the same maths problem. Use what works.

    For Parents Advocating in Indian Schools

    • Request a written Individual Education Plan (IEP) or support plan – you are entitled to ask for this
    • Document specific challenges with concrete examples, not just general descriptions
    • Bring information to teachers rather than assuming they know – most haven’t had autism-specific training
    • Build a relationship with one key teacher or counsellor who becomes your child’s advocate within the school

    Masking and Camouflaging in Autism

    Masking and Camouflaging in Autism

    If your child seems “fine” at school but falls apart the moment they get home, you may already be witnessing masking – even if you didn’t have a word for it.

    Masking (also called camouflaging) is the conscious or unconscious suppression of autistic traits to appear neurotypical. It looks like forcing eye contact, scripting conversations in advance, copying peers’ gestures, or laughing at jokes you don’t understand – all to avoid standing out.

    Why It Happens

    The drive to mask is rarely a free choice. It’s a survival response.

    Autistic individuals learn early that their natural way of being – stimming, speaking bluntly, needing quiet – draws negative attention. Social pressure, fear of rejection, bullying, and the relentless message that “normal” is better all push people toward hiding who they are. In India, where social conformity is deeply valued and autism awareness is still growing, that pressure can be especially intense.

    Who Is Most Affected

    Masking is more common – and more damaging – in certain groups:

    • Girls and women are diagnosed with autism far later than boys, partly because they tend to mask more effectively. Many aren’t identified until their 20s, 30s, or beyond.
    • Late-diagnosed adults who spent decades masking without understanding why they were exhausted.
    • Autistic people in high-demand social environments – competitive schools, workplaces, joint families.

    The Mental Health Cost

    This is where it gets serious. A 2024 systematic review found a significant correlation between camouflaging and higher anxiety, depression, and poorer psychological wellbeing. A separate 2024 meta-ethnography described masking as cognitively exhausting – leaving people “burnt out” and unable to manage basic daily activities.

    Autistic burnout is real. It’s not laziness or a bad attitude. It’s the accumulated cost of performing neurotypicality for months or years without a break.

    The mental health toll includes:

    • Chronic anxiety and social anxiety
    • Depression
    • Identity confusion (“I don’t know who I really am”)
    • Suicidal ideation in severe cases
    • Complete withdrawal from activities that once felt manageable

    Why Unmasking Matters

    When an autistic person feels safe enough to unmask – to stim, to be direct, to say “I need a break” – their wellbeing improves measurably. Creating that safety isn’t weakness. It’s the most protective thing a family, school, or therapist can do.

    The goal isn’t to make autistic people perform neurotypicality better. It’s to build environments where they don’t have to.

    Alexithymia: When Emotions Are Hard to Name

    Alexithymia: When Emotions Are Hard to Name

    Imagine not knowing whether you’re hungry, sad, or overwhelmed – just feeling a vague, uncomfortable pressure inside with no label attached. For many autistic individuals, this isn’t a metaphor. It’s Tuesday.

    Alexithymia is the difficulty identifying and describing one’s own emotional states. The word comes from the Greek: a (no) + lexis (word) + thymos (emotion). It’s not that the person doesn’t feel – it’s that the internal signal and the language for it are disconnected.

    How Common Is It?

    Very. A systematic review and meta-analysis found a weighted prevalence of ~50% in autistic individuals, compared to roughly 5% in the general population. Some clinical studies of autistic adults report rates as high as 55–66%. It’s not a fringe experience – it’s something half the autistic community navigates every day.

    Crucially, alexithymia is a separate condition that co-occurs with autism. Not every autistic person has it, and not everyone with alexithymia is autistic. But the overlap is substantial.

    How It Shows Up in Daily Life

    Alexithymia isn’t always obvious from the outside. Look for patterns like:

    • Not recognising hunger or thirst until it becomes urgent or physical (headache, shaking)
    • Describing emotions in physical terms – “my chest feels tight” instead of “I’m anxious”
    • Appearing flat or unresponsive in emotionally charged situations – not because they don’t care, but because they can’t access the feeling in real time
    • Delayed emotional processing – realising they were upset about something hours or days after it happened
    • Difficulty understanding why they’re having a meltdown – the body is in crisis but the mind can’t name the cause

    This creates real problems with self-care. If you can’t identify that you’re exhausted, you won’t rest. If you can’t name grief, you can’t seek comfort.

    Impact on Relationships

    Partners, parents, and friends often misread alexithymia as coldness, indifference, or emotional unavailability. It isn’t. The autistic person may care deeply but simply lack the internal map to navigate their own emotional landscape – let alone communicate it to someone else.

    This misreading causes enormous relational damage. Families benefit enormously from understanding that “I don’t know how I feel” is a genuine, neurological reality – not an excuse.

    Practical Ways to Support Someone with Alexithymia

    • Use body-based check-ins: “What does your body feel like right now?” is often more accessible than “How are you feeling?”
    • Offer emotion vocabulary without pressure: emotion wheels, feeling charts, or simple lists give a starting point without demanding introspection
    • Don’t push for immediate emotional responses – give processing time, sometimes hours
    • Name emotions you observe gently: “It looks like that was frustrating – is that right?” lets them confirm rather than generate
    • Work with an occupational therapist or psychologist trained in interoception – the sense of the body’s internal states – which is often the root of alexithymia in autistic individuals

    Co-occurring Conditions in Autism

    Co-occurring Conditions in Autism

    Autism rarely arrives alone. For most autistic individuals, the challenges in autism are compounded by one or more co-occurring conditions – and understanding this is essential to getting the right support.

    This isn’t about making autism seem worse than it is. It’s about being honest so families stop chasing one diagnosis while missing three others.

    Anxiety Disorders

    Anxiety is the most common co-occurring condition in autism. Estimates vary widely – from 20% to as high as 84% depending on the study and population – but the clinical reality is consistent: most autistic people experience significant anxiety.

    In autism, anxiety doesn’t always look like worry. It can appear as rigidity, meltdowns, refusal, physical complaints (stomach aches, headaches), or increased stimming. Standard anxiety treatments often need modification to work for autistic individuals – cognitive approaches that rely on abstract self-reflection can fall flat when alexithymia is also present.

    ADHD

    ADHD and autism overlap more than most people realise. A meta-analysis found ADHD in approximately 38–40% of autistic individuals. The two conditions share some features – distractibility, impulsivity, difficulty with transitions – but they’re neurologically distinct and require different support strategies.

    When both are present, executive function challenges are amplified. Organisation, task initiation, and emotional regulation all become significantly harder. Missing an ADHD diagnosis in an autistic child means missing a major piece of the support puzzle.

    Depression

    Depression affects autistic individuals at far higher rates than the general population, particularly in adolescence and adulthood. The causes are multiple: chronic social exclusion, the exhaustion of masking, repeated failure in environments not built for them, and the grief of late diagnosis.

    Depression in autism can be harder to identify because it may not present as sadness. Look for increased withdrawal, loss of interest in special interests (a significant red flag), changes in eating or sleep, and increased irritability.

    Epilepsy

    Epilepsy affects approximately 12–35% of autistic individuals – a rate dramatically higher than in the general population. Seizures can be subtle (absence seizures, staring episodes) and are sometimes mistaken for inattention or dissociation. Any unexplained episodes of unresponsiveness in an autistic child warrant neurological evaluation.

    OCD

    Obsessive-compulsive disorder co-occurs with autism and is frequently misdiagnosed – or missed entirely, because repetitive behaviours are already expected in autism. The key clinical distinction: OCD-driven repetition is ego-dystonic (the person doesn’t want to do it and finds it distressing), while autistic repetition is often ego-syntonic (it feels regulating and comforting). Getting this distinction right matters enormously for treatment.

    Eating Disorders and Feeding Difficulties

    Sensory sensitivities, rigidity around food textures and presentation, and difficulties with interoception all make autistic individuals – particularly girls and women – vulnerable to eating disorders. ARFID (Avoidant/Restrictive Food Intake Disorder) is especially common and is frequently unrecognised in autistic children.

    Why Co-occurring Conditions Are Missed

    Diagnostic overshadowing is real: clinicians attribute everything to autism and stop looking. Families are told “that’s just the autism” when a child is actually in the grip of a treatable anxiety disorder or a depressive episode.

    Holistic, multi-disciplinary care – involving psychiatry, psychology, occupational therapy, speech-language pathology, and neurology working together – is not a luxury. For most autistic individuals, it’s a necessity.

    How to Support Someone Facing These Challenges

    How to Support Someone Facing These Challenges

    You love this person. You’re doing everything you can. And some days it still feels like you’re failing. You’re not – but you may need a different toolkit.

    Supporting an autistic family member well isn’t about fixing them. It’s about building a world they can function in.

    Environmental Adaptations

    The environment is often the problem, not the person. Start there.

    • Reduce sensory load: lower lighting where possible, use noise-cancelling headphones, create a designated quiet space at home – even a corner with a tent or curtain counts
    • Build predictable routines: autistic individuals regulate better when they know what’s coming. A consistent daily structure – same wake time, same meal sequence, same bedtime routine – reduces baseline anxiety significantly
    • Give advance warning of changes: “In 10 minutes we’re leaving” is more respectful and more effective than a sudden transition
    • Designate a safe retreat space: somewhere the person can go when overwhelmed, without judgment

    Communication Adaptations

    How you communicate matters as much as what you say.

    • AAC (Augmentative and Alternative Communication): for non-speaking or minimally verbal individuals, tools like picture exchange systems, communication boards, or apps like Avaz (developed in India) can transform daily life. AAC doesn’t replace speech – it builds it
    • Visual schedules: picture or symbol-based daily schedules reduce the cognitive load of transitions and help with task initiation
    • Low-demand approaches: reduce the number of direct questions and commands. Offer choices. Narrate rather than interrogate (“I’m going to get your shoes now” rather than “Why aren’t your shoes on?”)
    • Written communication: for many autistic individuals, text or written notes are easier to process than spoken language, especially when stressed

    Emotional Support: Validate, Don’t Fix

    When your child or family member is in distress, the instinct is to solve it. Resist that instinct first.

    Validation comes before problem-solving. “That sounds really hard” lands before “Here’s what you should do.” Feeling heard is regulating. Being immediately redirected is not.

    • Avoid dismissing sensory experiences (“It’s not that loud”)
    • Don’t force eye contact or physical affection during distress
    • Sit with them in the difficulty before moving toward solutions

    When to Seek Professional Help

    Seek evaluation promptly if you notice:

    • Persistent self-harm or talk of not wanting to be alive
    • Complete withdrawal from previously enjoyed activities
    • Significant regression in skills
    • Suspected seizure activity
    • Eating that is severely restricted or causing physical health concerns
    • A caregiver who is burning out – your wellbeing is part of the support system

    Conclusion

    The challenges in autism — from behaviour challenges in autism to sensory sensitivities and communication differences — are real and impactful. But they are also understandable once we learn to see the world differently.

    To improve everyday life for autistic individuals, we need:

    • Awareness
    • Patience
    • Empathy
    • Adapted support systems

    Every person with autism has a story, a set of challenges, and enormous potential. With understanding and action, we can make life more inclusive — not just for autistic individuals, but for all of us who share this world.

    Frequently Asked Questions (FAQs)

    What are the most common challenges in autism?

    The most common challenges in autism include difficulties with social communication, sensory sensitivities, emotional regulation, and adapting to change. Many autistic individuals also experience behaviour challenges in autism, such as meltdowns or repetitive behaviours, especially when they feel overwhelmed or unable to communicate their needs.

    How do the challenges of autism affect everyday life?

    The challenges of autism in everyday life can impact daily routines, school, work, and social interactions. Simple tasks like going to a crowded place, following an unpredictable schedule, or participating in conversations may feel stressful due to sensory overload, anxiety, or communication differences.

    What behaviour challenges do autistic people commonly face?

    Behaviour challenges in autism may include meltdowns, shutdowns, self-stimulating behaviours, aggression, or difficulty managing emotions. These behaviours are not intentional or negative; they are often a response to stress, sensory discomfort, or unmet communication needs.

    Are the challenges autistic people face the same for everyone?

    No, the challenges autistic people face vary widely because autism is a spectrum. Each person experiences different strengths and challenges depending on factors like age, environment, level of support, and individual sensory and communication needs.

    Disclaimer: This article is intended for educational and informational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. If you are pregnant or have concerns about medication use during pregnancy, please consult a qualified healthcare provider. If your child has received an autism diagnosis and you have questions about causes or support, please reach out to a trained specialist or an autism-focused organisation for guidance.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

    Useful Sources

    Camouflaging and mental health – 2024 systematic review: pmc.ncbi.nlm.nih.gov/articles/PMC8992925

    Alexithymia prevalence in autism – meta-analysis: pmc.ncbi.nlm.nih.gov/articles/PMC6331035

    Alexithymia and autism – Autistica explainer: autistica.org.uk/what-is-autism/anxiety-and-autism-hub/alexithymia

    ADHD and autism co-occurrence – CHOP research: chop.edu/news/rates-adhd-remain-high-adulthood-among-patients-autism

    Co-occurring conditions overview – Autism Australia: autismaustralia.org.au/navigating-autism/autism-and-co-occurring-conditions

    AAC in India – Avaz app: play.google.com/store/apps/details?id=com.avazapp.autism.en_in.avaz

    Executive function and autism in the classroom: autismspeaks.org/executive-functioning

    Autistic strengths – Autistica: autistica.org.uk/what-is-autism/autistic-strengths

    Strengths-based approach research – Molecular Autism 2021: pmc.ncbi.nlm.nih.gov/articles/PMC7907419

  • 10 Best Exercises for Autistic Kids: Sensory, Motor & Social Benefits

    10 Best Exercises for Autistic Kids: Sensory, Motor & Social Benefits

    Movement is medicine – and for autistic children, it is one of the most accessible and powerful tools we have. The right exercises for kids with autism do far more than build physical fitness.

    They support sensory regulation, strengthen motor planning, ease anxiety, and open doors to social connection. Done consistently, they can shift the entire texture of a child’s day.

    This guide brings together 10 of the most effective and evidence-informed exercises for autistic children, drawn from clinical practice, peer-reviewed research, and the lived experience of families and therapists who work with children on the spectrum every day.

    Whether you are a parent, a special educator, or a therapist, you will find both the “why” and the “how to start” for each activity – along with honest notes on which sensory profiles each exercise suits best.

    Why Exercise Matters for Autistic Children

    Why Exercise Matters for Autistic Children

    Before we get to the list, it is worth understanding what the research actually says – because the case for physical activity in autism is stronger than many caregivers realise.

    The evidence is clear.

    A meta-analysis published in Medicine (2019), drawing on data from multiple controlled studies, found that physical exercise produced a significant reduction in stereotypic and repetitive behaviours in children with ASD, with an effect size of Hedges’ g = 1.16 in primary analyses. That is a large effect by any standard. Separately, a 2026 meta-analysis published in Frontiers in Psychiatry found that aerobic exercise showed the strongest anxiolytic effect among all exercise types studied in children with autism – more than yoga or resistance training alone.

    Research consistently links regular physical activity in autistic children to:

    • Improved attention and on-task behaviour in classroom and therapy settings
    • Reduced anxiety and emotional dysregulation
    • Better sleep quality
    • Gains in social engagement when exercise is done in group or partner formats
    • Decreased frequency and intensity of repetitive behaviours

    Autistic children move less – and that gap matters

    Studies show that autistic children spend significantly more time in sedentary behaviour than their neurotypical peers – on average, roughly one additional hour of sedentary time per day, with much of that driven by screen time. Given that physical activity is already hard to sustain for many children on the spectrum due to sensory sensitivities, motor coordination challenges, and difficulties with transitions, this gap compounds over time.

    Exercise as sensory regulation – not just fitness

    This is the framing shift that matters most. For many autistic children, movement is not primarily about cardiovascular health or muscle tone. It is a sensory regulation tool. Proprioceptive input (the feedback your joints and muscles send to your brain) is deeply calming for many children who are sensory-seeking. Vestibular input (movement through space) helps organise the nervous system. When we think of exercise this way – as a form of sensory diet rather than a workout – it becomes far easier to build into daily life.

    Yoga for Sensory Integration

    Yoga for Sensory Integration

    Yoga is one of the most well-researched and practically accessible exercises for autistic children. Its structured, predictable sequence of poses gives children a sense of safety and control – two things that matter enormously on the spectrum.

    What the research says: A 12-week yoga programme studied in children with ASD showed significant improvement in overall autism severity scores compared with controls, based on parent ratings (published in Journal of Alternative and Complementary Medicine, 2017). A systematic review of nine studies found positive outcomes in seven, including gains in sensory response, sociability, and attention.

    Sensory note: Yoga suits both sensory-seeking and sensory-avoidant children. For sensory seekers, poses like downward dog and warrior provide deep proprioceptive input. For sensory-avoidant children, the quiet, low-stimulation environment of a home yoga session is far less overwhelming than a gym or playground.

    How to start:

    • Begin with just three or four simple poses – cat-cow, child’s pose, and tree pose are good starting points.
    • Use visual cards showing each pose so the child can follow along without relying on verbal instruction.
    • Keep sessions to 10–15 minutes and use the same sequence each time. Predictability is the point.

    You might also enjoy our guide to 10 Fun Sensory Activities for an Autistic Child for more ideas that pair well with yoga.

    If you want to know 10 Fun Sensory Activities for an Autistic Child, you would love to have a look at this article.

    📥 Free download: Printable daily routine chart for autistic children

    Swimming for Sensory Input

    Swimming for Sensory Input

    Water is one of the most naturally therapeutic environments for many autistic children. The buoyancy reduces gravitational demand on the body, the resistance provides full-body proprioceptive feedback, and the consistent pressure of water can have a genuinely calming effect on the nervous system.

    What the research says: A 2022 study published in PLOS ONE found that aquatic therapy programmes for children with ASD led to significant improvements in social interaction, emotional regulation, and stereotyped behaviour. The consistent sensory input of water appears to support sensory modulation in ways that are difficult to replicate on land.

    Sensory note: Swimming is particularly well-suited to sensory-seeking children who crave deep pressure and movement input. For sensory-avoidant children, the initial experience of water on the face or unexpected splashing can be distressing – so a slow, child-led introduction is essential. Start with feet-in-water play before progressing to full immersion.

    How to start:

    • Look for adaptive swim programmes in your city – many run in smaller pools with quieter environments specifically for children with additional needs.
    • Begin with free water play rather than structured strokes. Let the child lead.
    • A consistent instructor who understands autism makes an enormous difference to how quickly a child builds trust and confidence in the water.

    📥 Free download: Printable daily routine chart for autistic children

    Balancing and Coordination Exercises

    Balancing and Coordination Exercises

    Many autistic children experience differences in proprioception and vestibular processing that make balance and coordination genuinely challenging. This is not a matter of effort or attention – it reflects real neurological differences in how the body maps itself in space. Targeted balance work addresses this directly.

    What the research says: A 2022 rehabilitation study published in PMC found that structured balance training – including single-leg standing, beam walking, and jumping between marked circles – produced measurable improvements in postural control and coordination in children with ASD over an eight-week period.

    Sensory note: Balance activities provide strong proprioceptive and vestibular input, making them excellent for sensory-seeking children. For sensory-avoidant children, avoid unpredictable movement challenges (like wobble boards without support) early on – build confidence with predictable, supported tasks first.

    How to start:

    • Tape a straight line on the floor and practise heel-to-toe walking along it. It costs nothing and works immediately.
    • Progress to walking along a low balance beam, then to single-leg standing while holding a wall for support.
    • Add a fun element – pretend the line is a tightrope over a jungle, or count how many seconds the child can balance on one foot.

    Therapeutic Horseback Riding

    Therapeutic Horseback Riding

    Therapeutic horseback riding – also called hippotherapy when delivered by a licensed therapist – is one of the most distinctive and effective interventions available for autistic children. The rhythmic, three-dimensional motion of the horse closely mimics the movement of human walking, providing rich vestibular and proprioceptive input with every step.

    What the research says: A systematic review published in PMC (2018) found that equine-assisted interventions were associated with improvements in adaptive behaviour, social interaction, and communication in children with ASD. A 2020 study in Frontiers in Psychology specifically noted that therapeutic horseback riding combined with cognitive exercises improved attention and reduced hyperactivity in children with ASD and comorbid ADHD.

    Sensory note: The gentle, rhythmic motion of a horse is deeply regulating for sensory-seeking children who need vestibular input. For children with tactile sensitivities, the texture of the saddle, the smell of the stable, and the unpredictability of an animal can be challenging – a careful, gradual introduction with a skilled equine therapist is essential.

    How to start:

    Sessions are typically 30–45 minutes and work best when scheduled consistently – weekly is ideal.

    Search for PATH International-certified equine therapy centres, or ask your child’s occupational therapist for a referral.

    The first session should be purely about meeting the horse – no riding required. Let the child groom the horse, offer a treat, and simply stand nearby.

    Want to know more? Get in touch with us.

    Breathing Exercises for Calming

    Breathing Exercises for Calming

    Breathing exercises are not glamorous. They do not require equipment, a gym, or a therapist. But they may be the single most transferable self-regulation skill an autistic child can learn – because they work anywhere, at any time, and in any situation.

    What the research says: Diaphragmatic breathing activates the parasympathetic nervous system, directly countering the fight-or-flight response. Research on mindfulness-based interventions in children with ASD – including a 2021 pilot randomised trial – found that breath-focused practices improved self-regulation and executive control, with parent-reported gains in emotional communication.

    Sensory note: Breathing exercises are ideal for sensory-avoidant children who find physical movement overwhelming. They are low-stimulation, predictable, and can be done in a quiet corner. For sensory-seeking children, pair breathing with movement – for example, “snake breath” (hissing out slowly while sliding arms down) adds a tactile and auditory dimension.

    How to start:

    Practise during calm moments, not just during distress. The goal is to build the habit before it is needed.

    Teach “belly breathing” first: place a small stuffed animal on the child’s tummy and ask them to make it rise and fall with each breath.

    Use a visual aid – a pinwheel, a bubble wand, or a simple drawing of a flower (sniff) and a candle (blow) – to make the technique concrete and memorable.

    Obstacle Courses for Motor Planning

    Obstacle Courses for Motor Planning

    Motor planning – the ability to conceive, organise, and execute a sequence of movements – is an area of genuine challenge for many autistic children. Obstacle courses are one of the most effective and enjoyable ways to build this skill, because they demand sequencing, spatial awareness, and problem-solving all at once.

    What the research says: Research on motor planning deficits in autism consistently shows that structured, repetitive movement sequences improve praxis (the ability to plan and perform novel movements). Obstacle courses are specifically recommended in adaptive physical education literature as a tool for developing this capacity in a playful, low-pressure context.

    Sensory note: Obstacle courses can be calibrated for any sensory profile. For sensory seekers, add tunnels to crawl through, crash pads to jump onto, and textured surfaces to walk across. For sensory-avoidant children, keep the environment quiet, use familiar household items, and introduce one new element at a time.

    How to start:

    Use picture cards showing each obstacle in sequence – this gives the child a visual map of the course and reduces transition anxiety between elements.

    Build a simple course at home using cushions to jump between, a table to crawl under, a line of tape to walk along, and a hoop to step through.

    Walk through the course with the child the first time, narrating each step: “First we jump, then we crawl, then we walk the line.”

    Sensory Play with Textures

    Sensory Play with Textures

    Sensory play with textures sits at the intersection of exercise and therapy. It is not vigorous physical activity in the traditional sense, but it is deeply important for sensory integration – the process by which the brain learns to organise and respond appropriately to sensory input from the environment.

    What the research says: Occupational therapy literature consistently supports texture-based sensory play as a component of sensory integration therapy for children with ASD. Tactile exploration helps the brain build more accurate sensory maps, reducing over- or under-responsiveness to touch over time.

    Sensory note: This activity is designed specifically for sensory-avoidant children who struggle with tactile input, but it must be introduced gradually and always on the child’s terms. For sensory-seeking children, it provides satisfying tactile stimulation and can be used as a calming activity before transitions.

    How to start:

    Gradually expand the range: wet sand, water beads, shaving foam, kinetic sand, and textured fabrics all offer different tactile experiences.

    Begin with textures the child already tolerates – perhaps dry rice, smooth playdough, or a soft fabric – before introducing anything new.

    Never force contact. Offer the material and let the child approach it at their own pace. Even watching another person play with a texture is a valid first step.

    Interactive Games for Social Skills

    Interactive Games for Social Skills

    Physical play and social development are deeply intertwined. Interactive games – from simple turn-taking activities to cooperative movement challenges – create structured, low-pressure opportunities for autistic children to practise the social skills that can feel elusive in unstructured settings.

    What the research says: A 2022 meta-analysis in Autism Research found that long-term, regular exercise in group formats was especially beneficial for social skills in children and adolescents with autism, with gains in communication, turn-taking, and cooperative behaviour.

    Sensory note: Group games suit sensory-seeking children who enjoy proximity and shared energy. For sensory-avoidant children, start with one-on-one games in a quiet space before gradually introducing peers. Keep group sizes small – two or three children is often more productive than a full class.

    How to start:

    • Start with simple turn-taking games: rolling a ball back and forth, taking turns stacking blocks, or passing a beanbag in a circle.
    • Use clear, consistent rules and visual supports (e.g., a “my turn / your turn” card) to reduce ambiguity.
    • Gradually introduce cooperative games where children must work together toward a shared goal – building a tower, completing a puzzle relay, or navigating an obstacle course as a team.

    Fine Motor Skill Development with Arts and Crafts

    Fine Motor Skill Development with Arts and Crafts

    Fine motor development – the precise coordination of small muscle groups in the hands and fingers – underpins writing, self-care, and many daily living skills. Arts and crafts activities build these skills in a context that feels creative and rewarding rather than therapeutic and effortful.

    What the research says: Occupational therapy research consistently identifies arts and crafts as an effective medium for fine motor skill development in children with ASD, with benefits in hand-eye coordination, grip strength, and bilateral coordination. The tactile dimension of art materials also supports sensory processing alongside motor development.

    Sensory note: Arts and crafts can be adapted for both sensory profiles. For sensory-seeking children, use materials with strong tactile properties – clay, finger paint, textured collage materials. For sensory-avoidant children, offer tools (brushes, stamps, rollers) that allow creative engagement without direct hand contact with messy materials.

    How to start:

    Gradually introduce activities that require more precision: cutting along a line, threading beads, or drawing within a shape.

    Begin with activities that have a clear, achievable end product – a stamped card, a simple collage, a clay pinch pot – so the child experiences a sense of completion and pride.

    Offer a range of tools and let the child choose. Autonomy matters enormously for engagement.

    Want to know more? Get in touch with us.

    Aerobic Activities for Overall Fitness

    Aerobic Activities for Overall Fitness

    Aerobic exercise – sustained, rhythmic movement that raises the heart rate – has some of the strongest evidence of any physical intervention for autistic children. It improves mood, reduces anxiety, supports attention, and builds the cardiovascular fitness that underpins long-term health.

    What the research says: A 2026 meta-analysis published in Frontiers in Psychiatry found that aerobic exercise produced the strongest reduction in anxiety among all exercise types studied in children with ASD. Autism Speaks’ research summary notes that 20–30 minutes of aerobic activity can improve attention and on-task behaviour for several hours afterwards – a finding with direct implications for learning and therapy sessions.

    Sensory note: Aerobic activities vary enormously in their sensory demands. Dancing suits sensory-seeking children who enjoy music and movement. Cycling is excellent for children who need predictable, repetitive input. For sensory-avoidant children, avoid crowded or noisy environments – a home dance session or a quiet bike ride is far more accessible than a gym class.

    How to start:

    Build aerobic activity into the daily routine at a consistent time – before school, after lunch, or as a transition between therapy and homework – so it becomes a predictable anchor in the child’s day.

    Choose an activity the child already shows interest in – if they love a particular song, dancing to it counts. If they enjoy being outdoors, a brisk walk or scooter ride works perfectly.

    Aim for 20–30 minutes, but start with 10 if that is what is achievable. Consistency matters more than duration.

    Common Barriers to Exercise – and How to Overcome Them

    Common Barriers to Exercise - and How to Overcome Them

    Knowing which exercises work is only half the challenge. The harder question is: how do you actually get started when the child resists, the environment is overwhelming, or the caregiver is exhausted? Here are the most common barriers we encounter, and what actually helps.

    Sensory sensitivities to the exercise environment

    Gyms are loud. Pools smell of chlorine. Sports equipment has unexpected textures. For many autistic children, the sensory demands of a typical exercise environment are the first obstacle – before the activity itself even begins.

    What helps: Start in the lowest-stimulation environment available, usually home. Introduce new environments gradually, with preview visits before the first active session. Noise-cancelling headphones can make a significant difference in pools, sports halls, and outdoor spaces. Let the child bring a preferred comfort item to new environments.

    Difficulty with transitions and new routines

    Introducing a new activity means changing an existing routine – and that is genuinely hard for many autistic children, regardless of how enjoyable the activity might eventually become.

    What helps: Use visual schedules to show the child exactly what will happen and when. Social stories (short, illustrated narratives describing the new activity step by step) are particularly effective for preparing children for unfamiliar experiences. Keep the timing consistent – same day, same time, same sequence – until the activity becomes part of the expected routine.

    Motor coordination challenges

    Some children avoid physical activity not because they dislike movement, but because movement is genuinely harder for them and past experiences have involved frustration or failure.

    What helps: Break every activity into the smallest possible steps and teach each step separately before combining them. Hand-over-hand guidance – where the adult physically guides the child’s movement – is appropriate for introducing new motor patterns, then gradually faded as the child builds confidence. Celebrate every small gain explicitly.

    Motivation and engagement

    An activity that does not connect to the child’s interests will not last – regardless of how good the evidence for it is.

    What helps: Follow the child’s lead. If they love dinosaurs, build a dinosaur-themed obstacle course. If they are fascinated by a particular TV character, find yoga poses named after that character. Preferred themes and characters are not a distraction from the exercise – they are the engine that makes it work.

    Caregiver fatigue and access

    Many families of autistic children are already stretched thin. The idea of adding a structured exercise programme to an already demanding day can feel impossible.

    What helps: Ten to fifteen minutes counts. A short walk, a dance to two songs, or a quick obstacle course in the living room is genuinely beneficial – especially when done consistently. Free and low-cost options are abundant: YouTube channels offer yoga and movement sessions designed specifically for children with additional needs, and home obstacle courses require nothing more than cushions and tape.

    Tips for Caregivers: Making Exercise a Daily Habit

    Tips for Caregivers: Making Exercise a Daily Habit

    Building a sustainable movement routine takes time. Here is what we have found works in practice.

    Start small and stay consistent. Ten to fifteen minutes a day, done five days a week, will produce more benefit than an hour-long session once a week. Consistency is the variable that matters most.

    Use visual timers and schedules. A visual timer (a Time Timer, for example, or a simple sand timer) makes the duration of an activity concrete and predictable. Knowing that exercise ends when the sand runs out reduces resistance to starting.

    Celebrate effort, not performance. Autistic children – like all children – thrive on acknowledgement. But the reinforcer should be for trying, not for achieving a particular standard. Use the child’s preferred reinforcers: verbal praise, a sticker chart, a preferred activity afterwards, or simply a high-five.

    Involve siblings or peers where possible. Exercise done alongside a sibling or a trusted peer adds a social dimension that builds communication and cooperation skills naturally. It also makes the activity more fun – which is, ultimately, the most important factor in whether it continues.

    Track progress simply. A basic chart on the fridge – one sticker per day of movement – gives the child a visual record of their own consistency and builds intrinsic motivation over time. Download our free printable daily routine chart to get started.

    Know when to involve a professional. If a child’s motor challenges, sensory sensitivities, or behavioural responses to exercise are significant, a referral to an occupational therapist, physiotherapist, or certified adaptive physical education specialist is the right next step. These professionals can design individualised programmes, identify underlying sensory or motor issues, and support both the child and the caregiver with evidence-based strategies.

    Conclusion

    Tailoring exercises for autistic kids goes beyond physical health – it nurtures sensory processing, emotional regulation, and cognitive development. These 10 important exercises offer a diverse range of activities that can be adapted to meet the unique needs of each child on the autism spectrum. By incorporating these exercises into daily routines, we empower autistic children to thrive physically, emotionally, and socially, unlocking their full potential for a healthier and more fulfilling life.

    Useful Sources

    Ferreira, J.P. et al. (2019). Effects of physical exercise on stereotyped behaviour in ASD. Medicine. pmc.ncbi.nlm.nih.gov/articles/PMC6843401

    Frontiers in Psychiatry (2026). Exercise and anxiety in children with ASD: meta-analysis. frontiersin.org/journals/psychiatry/articles/10.3389/fpsyt.2026.1761833/full

    Autism Speaks. Can exercise improve behaviour in autism? autismspeaks.org/expert-opinion/can-exercise-improve-behavior

    PMC (2018). Equine-assisted interventions and ASD: systematic review. pmc.ncbi.nlm.nih.gov/articles/PMC6178825

    PMC (2022). Aquatic therapy and ASD outcomes. pmc.ncbi.nlm.nih.gov/articles/PMC9138228

    PMC (2022). Balance training in children with ASD. pmc.ncbi.nlm.nih.gov/articles/PMC9406473

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

    Disclaimer: This article is intended for educational and informational purposes only. It does not constitute medical advice, a clinical diagnosis, or a substitute for professional consultation. If you have concerns about your child’s development, please consult a qualified healthcare professional or developmental specialist. India Autism Center encourages all families to seek personalised guidance from trained clinicians. The research cited reflects findings available at the time of publication and is subject to ongoing scientific review.

  • Cognitive Behavioural Therapy: Detailed Guide for Parents & Caregivers

    Cognitive Behavioural Therapy: Detailed Guide for Parents & Caregivers

    If you’ve ever found yourself thinking, “Why do I keep reacting this way?” or “How can I help my child manage emotions better?” — you’re not alone. I hear this often from parents, caregivers, and individuals navigating emotional or behavioural challenges. That’s where cognitive behavioural therapy (CBT) becomes a powerful, practical solution.

    In this comprehensive guide, I’ll walk you through what cognitive behavioural therapy is, how it works, and how it connects with neurodevelopmental disorders like autism, Attention-deficit/hyperactivity disorder (ADHD), and learning difficulties.

    What Is Cognitive Behavioural Therapy and Why Does It Work for Children?

    What Is Cognitive Behavioural Therapy

    Before we talk about techniques, let’s get clear on the cognitive behavioural therapy definition.

    Cognitive behavioural therapy is a short-term, goal-oriented form of therapy that examines the relationship between thoughts, feelings, and behaviours. The core idea is simple but powerful: Your thoughts shape your feelings, and your feelings shape your actions. Change the thought, and you can change the entire chain reaction.

    The CBT Triangle Explained (Thoughts → Feelings → Actions)

    Imagine a triangle with three corners:

    • Thoughts (what you say to yourself internally)
    • Feelings (emotions like fear, anger, sadness, or excitement)
    • Actions (what you actually do, like hiding, yelling, or asking for help)

    Here’s how it plays out for a child who’s scared of the dark:

    • Thought: “There’s something under my bed.”
    • Feeling: Terror, racing heart, sweaty palms.
    • Action: Screaming for mom, refusing to sleep alone, lying rigid in bed.

    Now watch what happens when we change the thought:

    • New Thought: “I checked under the bed with Dad. There’s nothing there. I am safe.”
    • New Feeling: Calm, relaxed, sleepy.
    • New Action: Closing eyes, falling asleep, staying in bed all night.

    That’s cognitive behavioural therapy in a nutshell. And when you teach this framework to children, you give them a superpower: the ability to become their own thought detectives.

    How Children’s Brains Process CBT Differently Than Adults

    How Children’s Brains Process CBT Differently Than Adults

    Might you be wondering: Can my 7-year-old really understand this?

    The answer is yes—but with one important caveat. Children’s prefrontal cortexes (the “logic center” of the brain) are still developing. That means they struggle with abstract reasoning. So you can’t just hand them a textbook on cognitive behavioural therapy.

    Instead, you adapt, use stories, drawings, puppets, and games. You call negative thoughts “thought monsters” or “brain bugs.” You make it concrete, visual, and playful.

    For teenagers, you can be more direct. Teens have better abstract thinking skills, so you can introduce worksheets, journals, and digital apps. But the principle remains the same: meet the child where they are developmentally.

    Evidence-Based Success Rates for Childhood Anxiety, OCD, and Anger

    See, cognitive behavioural therapy isn’t a fad. It’s one of the most researched psychological treatments in existence.

    Here’s what the data shows:

    • Anxiety disorders: Up to 60% of children show significant improvement after 8–12 sessions of CBT.
    • OCD: CBT with Exposure and Response Prevention (ERP) works for 70 – 80% of pediatric patients.
    • Anger and aggression: CBT reduces disruptive behaviors by 40 – 50% compared to no treatment.

    These aren’t guesses. These are numbers from peer-reviewed studies. So when someone asks, “Does cognitive behavioural therapy work?”—you can answer with confidence: Yes!

    Want to know more? Get in touch with us.

    5 Core CBT Techniques Every Parent Can Use at Home

    5 Core CBT Techniques Every Parent Can Use at Home

    Now let’s get practical. You don’t need a therapist in the room to start using cognitive behavioral therapy techniques. Here are five strategies you can implement tonight.

    1. Thought Detective: Helping Your Child Catch Negative Thoughts

    This is the foundation of everything.

    What to do: Teach your child that thoughts are not facts. Just because they think something terrible will happen doesn’t mean it will.

    How to explain it: Say, “Your brain has a detective agency. Sometimes the detective makes mistakes. Let’s catch those mistakes together.”

    Questions to ask your child:

    • What’s the evidence that this scary thing will happen?
    • What’s the evidence that it won’t happen?
    • What would you tell a friend who had this same thought?

    Example: Your daughter thinks, “Nobody likes me at school.” You ask for evidence. She says, “Lily didn’t sit next to me at lunch.” Then you ask for evidence against: “But Emma saved you a seat yesterday, right? And you played tag with three kids at recess.”

    Suddenly, the original thought doesn’t hold up.

    2. The Feelings Thermometer: Scaling Emotional Intensity

    Young children struggle to describe emotions. They only know “fine” or “terrible.” The Feelings Thermometer gives them a scale from 1 to 10.

    How to make one: Draw a large thermometer on paper. Color the bottom green (1–2: calm/happy). Move to yellow (3–5: worried/frustrated). Then orange (6–8: very upset). Finally, red (9–10: explosive panic).

    How to use it: Use when your child is calm; practice rating different situations. “How many points would you give a small spider? Then, when they’re upset, ask: “Where are you on the thermometer right now?”

    This does two things. First, it gives you objective data. Second, it forces the child to pause and self-reflect, which alone lowers the intensity.

    3. Behavioural Activation: Breaking the Avoidance Cycle

    Anxiety and depression feed on avoidance. The more your child avoids the scary thing (school, social events, homework), the bigger that thing becomes in their mind.

    Behavioural activation is the opposite: you deliberately engage in positive or neutral activities even when you don’t feel like it.

    How to do it at home: Create a “brave choices” chart. Every time your child does something they were afraid of (asking a question in class, going to a birthday party), they earn a sticker. After five stickers, they get a small reward.

    Real-world example: One parent I worked with had a son who refused to order his own food at restaurants. They started small: first, he just made eye contact with the waiter. Next, he whispered his order to mom, who repeated it. Finally, he ordered a single drink by himself. Each step earned points. Within three weeks, he was ordering full meals.

    4. The Worry Journal: Tracking Triggers and Patterns

    You cannot fix what you do not measure.

    What to do: Buy a simple notebook. Label it “My Worry Journal.” Every evening, ask your child to write (or draw) three things:

    • What made me worried today?
    • What did I think would happen?
    • What actually happened?

    Why this works: Over time, patterns emerge. Your child will see, with their own eyes, that 90% of their predicted disasters never come true. That’s not you telling them—that’s data telling them. And data is hard to argue with.

    5. Brave Ladder (Exposure Hierarchy): Facing Fears Step-by-Step

    This is the gold standard for treating phobias and severe anxiety. But you have to do it carefully.

    How to build a Brave Ladder:

    1. List everything your child is afraid of related to one specific trigger (e.g., dogs).
    2. Rank each item from least scary (1) to most scary (10).
    3. Start at #1 and don’t move up until your child feels comfortable.

    A common example is the Brave Ladder for fear of dogs. This is just for understanding. You can pick anything for this:

    StepTaskScary Rating
    1Look at a cartoon picture of a dog2
    2Look at a real photo of a small dog3
    3Watch a 10-second video of a calm dog4
    4Stand 10 feet away from a real dog on a leash6
    5Stand 3 feet away from the same dog7
    6Pet the dog for 2 seconds with your hand9
    7Pet the dog for 10 seconds10

    Golden rule: Never force the next step. Let your child control the pace. Celebrate every small victory.

    Want to know more? Get in touch with us.

    Age-by-Age Guide: Adapting CBT for Preschoolers, School-Age Kids, and Teens

    Age-by-Age Guide: Adapting CBT for Preschoolers, School-Age Kids, and Teens

    One size does not fit all. Here’s how to adjust cognitive behavioural therapy for different developmental stages.

    CBT for Preschoolers (Ages 3–6): Play-Based Techniques

    At this age, abstract thinking is almost nonexistent. So you don’t lecture. You play.

    What works:

    • Puppet shows: Have a brave puppet and a scared puppet talk through problems.
    • Drawing feelings: “Draw a picture of your anger. What colour is it? Does it have teeth?”
    • Monster spray: Fill a spray bottle with water and lavender. Call it “worry spray.” Let your child “spray away” fears before bed.

    What doesn’t work: Worksheets, logic debates, or asking “Why do you feel that way?” (They don’t know why. They’re just 4 years old.)

    CBT for School-Age Children (Ages 7–12): Worksheets and Role-Play

    This is the sweet spot. Kids this age love structure, games, and earning rewards.

    What works:

    • Printable cognitive behavioural therapy worksheets (free online)
    • Role-playing difficult conversations with stuffed animals
    • The “Worry Box”: Decorate a shoebox. Write worries on slips of paper. “Lock” them inside at bedtime.

    Pro tip: Use their interests. If they love superheroes, frame CBT as “training your brain to defeat the worry villain.”

    CBT for Teenagers (Ages 13–18): Self-Monitoring and Digital Tools

    Teens value autonomy. They also live on their phones. Use that to your advantage.

    What works:

    • CBT apps like MindShift, Woebot, or Sanvello
    • Digital mood trackers (Daylio, Moodnotes)
    • Letting them lead their own therapy sessions (with your support)

    What to avoid: Nagging, checking their journal without permission, or forcing them to talk “on your schedule.” Teens will shut down fast.

    Common Childhood Conditions CBT Treats Most Effectively

    Common Childhood Conditions CBT Treats Most Effectively

    Let me be clear: cognitive behavioural therapy isn’t a magic wand. But for the following conditions, it’s often the first-line treatment recommended by pediatric psychologists.

    Generalized Anxiety Disorder (GAD) in Children

    Symptoms: Constant worrying about school, family health, natural disasters, or performance. Physical symptoms like headaches and fatigue.

    How CBT helps: Thought challenging reduces catastrophic predictions. Relaxation techniques (deep breathing, progressive muscle relaxation) lower physical arousal.

    Social Anxiety and Selective Mutism

    Symptoms: Extreme fear of embarrassment or judgment. Some children speak normally at home but go completely silent at school (selective mutism).

    How CBT helps: Brave Ladders slowly expose the child to social situations. Role-play builds conversational confidence.

    You can read our blog on Social Skills Development in Autism | 5 Proven Approaches (2026).

    Anger, Oppositional Defiant Disorder (ODD), and Impulse Control

    Symptoms: Frequent tantrums, arguing, blaming others, deliberately annoying people.

    How CBT helps: Teaches “stop and think” skills. Replaces aggressive actions with verbal expression (“I’m angry because…”).

    CBT for Pediatric OCD and Tic Disorders

    Symptoms: Repeated unwanted thoughts (obsessions) and rituals (compulsions). Tics are sudden, repetitive movements or sounds.

    How CBT helps: A specialized form called Exposure and Response Prevention (ERP) teaches the child to feel the urge to perform a ritual—but not do it. Over time, the urge fades.

    Sleep Disorders and Nightmares in Kids

    Symptoms: Difficulty falling asleep, frequent night waking, terrifying dreams.

    How CBT helps: Stimulus control (only using bed for sleep), bedtime routine adjustments, and “dream rescripting” (rewriting the nightmare’s ending with a positive twist).

    Want to know more? Get in touch with us.

    How to Find a Qualified Child CBT Therapist

    How to Find a Qualified Child CBT Therapist

    At some point, you might decide: I need professional help. That’s wise. Here’s exactly how to search for “cognitive behavioural therapy near me” and find someone great.

    10 Questions to Ask a Potential Therapist

    Before you book a session, call or email these questions:

    1. Do you have specific training in cognitive behavioural therapy for children?
    2. How many children with my child’s condition have you treated?
    3. Do you involve parents in the sessions?
    4. Will you give us “homework” to practice between sessions?
    5. How do you measure progress?
    6. What happens if my child refuses to talk?
    7. Do you offer teletherapy (video sessions)?
    8. What’s your cancellation policy?
    9. How much does each session cost?
    10. Do you accept our insurance?

    Red Flags: When CBT Isn’t Being Done Properly

    Be cautious if the therapist:

    • Never gives you a clear treatment plan or timeline
    • Tells you parents should “stay out of it”
    • Only talks to your child about “how that makes you feel” without teaching skills
    • Promises a “cure” in 3 sessions

    Real cognitive behavioural therapy is structured, goal-oriented, and transparent. If something feels off, trust your gut.

    Parent-Led CBT vs. Professional Therapy: What’s Best for Your Family?

    Parent-Led CBT vs. Professional Therapy

    You might be wondering: Can I just do this myself?

    The answer: Sometimes yes, sometimes no.

    When You Can Successfully Use DIY CBT Techniques

    Try home-based CBT first if:

    • Your child has mild anxiety (worries less than 1 hour/day)
    • The problem is recent (started within the last few months)
    • Your child is cooperative and willing to try
    • You have the time and patience to practice daily

    Signs Your Child Needs a Professional

    Get professional help immediately if your child:

    • Refuses to go to school for more than 2 weeks
    • Talks about wanting to hurt themselves or others
    • Has panic attacks (can’t breathe, chest pain, dizziness)
    • Is losing weight or not sleeping for days
    • Has stopped bathing, changing clothes, or seeing friends

    Combining Home Practices with Weekly Therapy for Faster Results

    Here’s the secret: The best outcomes happen when parents and therapists work together.

    In weekly therapy, the child learns skills. At home, you reinforce those skills. You become the coach, not the therapist. You practice the Brave Ladder, the Feelings Thermometer, and celebrate the small wins.

    When you search for “where can I get cognitive behavioural therapy,” ask the provider: “Do you offer parent training sessions?” If yes, jump on it.

    7 Common Mistakes Parents Make with CBT (And How to Avoid Them)

    7 Common Mistakes Parents Make with CBT

    I’ve seen hundreds of families try cognitive behavioural therapy. Here are the mistakes that derail progress—and how to sidestep them.

    Mistake #1: Lecturing Instead of Collaborating

    Wrong: “You’re being irrational. There’s nothing to be afraid of. Stop it.”

    Right: “I see you’re scared. Let’s figure this out together. What’s your brain telling you right now?”

    Mistake #2: Skipping the “Feeling” Step

    Wrong: “Just go to the party. You’ll be fine.”

    Right: “First, let’s name what you’re feeling. Scared? Nervous? Okay, now let’s rate it on the thermometer.”

    Mistake #3: Inconsistency with Rewards

    Wrong: Praising bravery one day, ignoring it the next.

    Right: Same reward system. Same expectations. Every. Single. Day.

    Mistake #4: Doing the Brave Ladder Backward

    Wrong: Starting with the scariest task (step 10) and being shocked when your child melts down.

    Right: Step 1 only. Master it. Then step 2.

    Mistake #5: Forgetting to Model CBT Yourself

    Wrong: “Do as I say, not as I do.”

    Right: Narrate your own thought process. “Mommy is worried about her presentation tomorrow. Let me check the evidence…”

    Mistake #6: Quitting Too Early

    Wrong: Stopping after two good days.

    Right: CBT takes 8–12 weeks minimum. Old habits die hard. Stick with it.

    Mistake #7: Not Celebrating Effort

    Wrong: Only praising the final outcome.

    Right: “I’m so proud of you for trying step 4, even though you were scared. That took real courage.”

    Conclusion

    Cognitive behavioural therapy isn’t a mystery. It’s a practical, evidence-based framework that shows your child how thoughts create feelings, and feelings create actions. You now know the cognitive behavioral therapy definition, the core techniques, and exactly how to do cognitive behavioral therapy at home.

    You’ve seen the age-by-age adaptations. You’ve learned when to search for “cognitive behavioral therapy near me” and when to trust your own parenting skills. And you have a list of common mistakes to avoid.

    So here’s my challenge to you.

    Pick just one technique from this guide. The Feelings Thermometer. The Thought Detective questions. A single rung on a Brave Ladder. Try it tonight. Not tomorrow. Not “when things calm down.” Tonight.

    Because here’s the truth I’ve learned from working with hundreds of families: The parents who see the biggest changes aren’t the smartest or the wealthiest. They’re the ones who start.

    Frequently Asked Questions (FAQs)

    Can I do CBT with my child without a therapist?

    Yes, for mild to moderate issues. The techniques I shared above (Thought Detective, Feelings Thermometer, Brave Ladder) are safe and effective for home use. However, if your child has a diagnosed mental health condition or is in crisis, please consult a professional.

    What’s the difference between CBT and play therapy?

    Play therapy uses toys, art, and sand trays to help young children express emotions indirectly. CBT is more structured and skills-based. For children under 6, play therapy is often preferred. For children 7 and older, CBT is typically more effective for specific problems like anxiety or anger.

    Does my child have to talk about trauma for CBT to work?

    No. While some forms of CBT address traumatic memories (Trauma-Focused CBT), standard CBT focuses on current thoughts, feelings, and behaviours. Your child never has to relive painful memories unless you and the therapist agree that the approach is necessary.

    What age is appropriate for cognitive behavioral therapy?

    Cognitive behavioural therapy can be used for children as young as 5–6 years old, with techniques adapted to their developmental level. It is effective for teenagers and even adults, making it a versatile, lifelong skill.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

  • Virtual Autism Symptoms in Children: Signs, Causes & Recovery

    Virtual Autism Symptoms in Children: Signs, Causes & Recovery

    In recent years, several parents have noticed subtle changes in their kids. A few years earlier, toddlers were curious and responsive, but today many show a preference for screens, avoid eye contact, and are often found lost in their own worlds. 

    A new term has been coined to describe these concerns: virtual autism. However, having a term is not enough; several questions arise for a parent today. Is it the same as autism? Is it real? Can it be cured? How do I know if my child has virtual autism symptoms or classic autism? 

    So here we are with answers. In this article, we are going to explore what virtual autism is, the common symptoms, and the steps parents can take to help their child. 

    What is Virtual Autism?

    Illustration explaining what virtual autism is and how excessive screen exposure affects child development

    In some children, there are a few autism-like developmental symptoms. There is a non-clinical term to describe these symptoms: Virtual Autism. It is common in young children, particularly toddlers. 

    These conditions are associated with excessive and early exposure to digital screens, such as smartphones, tablets, televisions, or other electronic devices. If you want to understand what virtual autism is, it is necessary to be clear that the symptoms are real, and the cause is environmental.

    Virtual autism means a child’s development is influenced more by a virtual (screen-based) environment than by real-world human interaction during the critical early years of brain growth.

    There are certain symptoms, such as delayed or absent speech, poor eye contact, reduced social engagement, limited attention span, and repetitive behaviour, which can closely resemble the symptoms of Autism Spectrum Disorder (ASD). However, there are still distinctions between the two. 

    In virtual autism, the primary concern is that passive screen exposure has replaced essential developmental experiences, such as:

    • Back-and-forth conversation
    • Emotional responsiveness
    • Joint attention (sharing focus with another person)
    • Interactive play

    Why the Term Virtual Autism Has Emerged Now?

    Reasons behind the rise of virtual autism including early screen exposure and reduced face-to-face interaction

    Virtual Autism is now recognised as a condition. However, it has not always been prevalent because earlier kids got little to no exposure to screens. In fact, it is only over the last decade that:

    • Screens have become primary soothing tools
    • Children have exposure to digital content earlier than ever
    • Face-to-face interaction time has reduced
    • Background media has become constant

    Proper brain development in a child depends on social interactions, not on passive stimulation. Human speech, facial expressions, turn-taking, and shared attention are essential for language and emotional growth. 

    However, as screens are now replacing these interactions, developmental delays are bound to happen. This is also common when screen exposure is prominent during the first three years of childhood. It does not mean screen exposure causes autism. 

    The effects of screen exposure can influence how the symptoms appear, worsen, or even mimic autism-like behaviour. 

    📥 Free download: Printable daily routine chart for autistic children

    Is Virtual Autism Real? 

    Visual explanation showing whether virtual autism is real and how it relates to developmental challenges in children

    A large population study asks: Is virtual autism real? The answer is not so simple and depends upon how you interpret the term, since the term is not an official medical virtual autism diagnosis. 

    This distinction is crucial, especially for parents who are worried, confused, or overwhelmed by what they’re seeing in their child. It is important to understand that children described as having virtual autism often show very real developmental challenges, just like in ASD.

    The behaviours are not imagination, exaggeration, or “just bad habits”; they are measurable, observable, and sometimes quite concerning. 

    What are the Most Common Virtual Autism Symptoms?

    List of the most common virtual autism symptoms such as speech delay, reduced eye contact, and emotional dysregulation

    Virtual autism symptoms refer to autism-like behaviours that are frequently observed in young children who have early and excessive screen exposure. Here are some of the most common virtual autism symptoms observed:

    1. Speech and Language Delays

    One of the earliest and most noticeable virtual autism symptoms is a delay in speech development. Some of the prominent symptoms that parents observe include:

    • No babbling or very limited babbling.
    • No meaningful word, even when the child turns 18 months.
    • Absence of two-word phrases even by the age of 2.
    • Loss of words the child previously used

    Language develops through back-and-forth human interaction. When screens replace conversation, children hear language but do not learn how to use it socially.

    2. Reduced Eye Contact and Social Engagement

    Another hallmark of virtual autism symptoms is poor or inconsistent eye contact. Some parents have noticed the following behaviour in their child:

    • The child rarely looks at faces.
    • Their child seems to avoid eye contact during play or in conversation.
    • The child does not seem to follow pointing.
    • Appears more engaged with screens than people

    Screens do not respond to a child’s facial expression, tone, or emotional cues, which limits their social learning. This reduces social engagement and connection. 

    3. No or Limited Responsiveness

    Since a child with virtual autism has reduced social attention, parents may observe other behaviours in terms of responsiveness, s such as

    • Not responding when called by name.
    • Often, they cannot react to familiar voices.
    • The child has zero to verify.
    • The child shows no interest when a person enters or leaves the room.

    4. Poor Joint Attention

    Joint attention is the ability of a child to look at an object, then look back at the caregiver, and respond with excitement or interest. However, when a child has virtual autism symptoms, they may not point or show interest.

    • Do not bring toys to show parents
    • Play alone without seeking shared interaction

    Poor joint attention can be a significant concern that requires timely evaluation.

    5. Absence of Pretend Play

    When a child is 18-24 months old, they achieve a major developmental milestone: pretend play. This milestone is often absent or limited to children with virtual autism symptoms. 

    Such a child may:

    • Use toys repetitively rather than imaginatively
    • Spin wheels, line up objects, or tap items repeatedly
    • Show little interest in pretend scenarios (feeding dolls, role-play games)

    6. Repetitive Behaviours and Movements

    When you observe your child displaying repetitive actions, you may feel they have autism. However, it doesn’t need to be autism. To distinguish, look for repetitive actions, such as.

    • Hand flapping
    • Rocking
    • Spinning
    • Repetitive vocal sounds

    These behaviours may also increase drastically when the child is overstimulated, bored, or disengaged, or when the child does not get screen time. 

    While repetitive behaviours can occur in autism, in virtual autism, they are often linked to sensory dysregulation and a lack of interactive stimulation.

    7. Prefer Screens Over People

    One of the major symptoms of virtual autism is that the child feels an intense attachment to the screens. There are certain scenarios that you may observe as a parent, such as

    • When the screens are absent, there is extreme distress.
    • When a distressed child gets a screen or device, they calm down.
    • Children with virtual autism syndrome are not very interested in toys, books, or even in interacting with people.
    • Such children also find it difficult to engage in non-screen activities. 

    8. Short Attention Span 

    Since children with virtual autism prefer screens, they focus intently on them for longer periods. They also lose interest in any non-screen activities. They also seem to struggle with turn-taking or even structured play. 

    Screens provide rapid visual rewards, making real-world activities feel slow or less engaging by comparison.

    9. Emotional Dysregulation and Behavioural Outbursts

    As soon as the screen is taken away, parents report that their child throws tantrums, becomes highly irritated or frustrated, and it becomes quite difficult to calm them down. More often than not, these reactions are due to:

    • Overstimulation
    • Poor self-regulation skills
    • Dependence on external (screen-based) soothing

    10. Regression After Normal Early Development

    A particularly concerning virtual autism symptom is developmental regression. It is more common than people expect. Parents report that their child was developing normally, and then things changed suddenly. 

    Some signs of developmental regression include:

    • Loss of words
    • Reduced social interaction
    • Increased screen fixation

    When parents report regression, it is necessary to take it seriously and to evaluate.

    Autism vs Virtual Autism: Key Conceptual Differences

    Comparison between autism and virtual autism highlighting key conceptual and developmental differences

    Awareness of developmental concerns in childhood is growing. However, because of similar symptoms, a parent can confuse two conditions, like ASD and virtual autism. The confusion is understandable. The behaviours can appear strikingly alike: delayed speech, reduced eye contact, limited social interaction, and repetitive actions.

    However, the underlying cause for these behaviours may vary widely, which is why distinguishing between the two concepts matters. Here is a comparison table for autism vs virtual autism explaining the key conceptual difference between the two:

    AspectAutism Spectrum Disorder (ASD)Virtual Autism
    DefinitionA recognised neurodevelopmental condition characterised by differences in social communication, behaviour, and sensory processing.An informal term describing autism-like symptoms believed to arise primarily from environmental factors, especially excessive early screen exposure.
    Medical RecognitionOfficially recognised and diagnosable using standard clinical criteria (DSM-5 / ICD-11).Not a recognised medical virtual autism diagnosis; used descriptively in clinical and therapeutic discussions.
    Primary CauseLargely neurobiological, with strong genetic and neurological components.Considered mainly environmental, with screen overuse and reduced human interaction playing a significant role.
    Age of OnsetSigns are usually present from infancy, even if they become more noticeable as the child grows.Symptoms often emerge after a period of heavy screen exposure, sometimes following an initially typical development.
    Role of Screen TimeScreen exposure does not cause autism, though excessive use may worsen existing symptoms.Screen exposure is believed to be a central contributing factor to the development or amplification of symptoms.
    Speech and Language DevelopmentDelays or atypical language patterns are common and persist without targeted therapy.Speech delays are common but may improve significantly once screen time is reduced and interaction increases.
    Social InteractionOngoing challenges with social communication, eye contact, and social reciprocity.Reduced social engagement is often linked to screen preference and may improve with increased real-world interaction.
    Joint AttentionFrequently limited or absent due to underlying neurodevelopmental differences.Often underdeveloped because of reduced interactive experiences, not necessarily a neurological impairment.
    Pretend and Imaginative PlayMay be limited, unusual, or develop differently compared to neurotypical peers.Often delayed due to a lack of modelling and interaction, with potential to develop once exposure increases.
    Repetitive BehavioursCore diagnostic feature; may persist long-term.May appear but cannot always be fixed, and can reduce as engagement and stimulation diversify.
    Response to Environmental ChangesIt can improve over time with consistent therapy and proper support, but there is a chance that the traits will remain.Noticeable improvement is quite possible with screen reduction and improved interaction.
    Long-Term OutlookA lifelong condition with varying levels of independence and support needs.Not considered lifelong; symptoms may reduce or resolve if environmental factors are addressed early.
    Approach to InterventionRequires structured, long-term interventions such as speech therapy, behavioural therapy, and educational support.Focuses on reducing exposure to screens, increasing social interaction, and monitoring progress, along with consistent therapy if needed.
    Risk of MisinterpretationDelayed diagnosis can delay access to essential support services.Mislabeling may lead to false reassurance or delayed autism assessment if professional evaluation is absent.
    Key Takeaway for ParentsEarly diagnosis enables access to appropriate lifelong supports.Early action can lead to significant improvement, but professional assessment remains essential.

    Can Virtual Autism Be Reversed?

    This is the question every parent asks first. And the honest answer is: for many children, yes – especially when action is taken early.

    Here is why. The first five years of a child’s life are the most neurologically active period in human development. The brain is not a fixed organ at this age; it is extraordinarily malleable. This capacity for change is called neuroplasticity – the brain’s ability to reorganise itself by forming new neural connections in response to experience, learning, and environment.

    Research from the Harvard Center on the Developing Child shows that the brain builds its architecture in the early years at a pace that will never be repeated – with more than 1 million new neural connections forming every second in infancy. When the right experiences are introduced, the brain responds. When harmful patterns (like passive screen dependency) are removed and replaced with rich human interaction, the developing brain can course-correct.

    This is the key distinction between virtual autism and ASD. Because virtual autism symptoms arise from an environmental cause – not a neurological one – the brain has not been wired differently from birth. The developmental gaps have formed because the right inputs were missing. Restore those inputs, and the brain can begin to fill those gaps.

    Clinical observations support this. Children who show virtual autism symptoms and receive early intervention – structured speech therapy, increased caregiver interaction, sensory play, and screen time reduction – frequently show significant improvement within 3 to 6 months. Some children recover fully; others show partial but meaningful gains.

    That said, outcomes are not uniform. A few honest caveats:

    • Age matters. The earlier the intervention, the greater the neuroplastic response. Children under 3 tend to show the fastest and most complete recovery. Between ages 3 and 5, improvement is still very achievable but may require more structured support.
    • Severity of exposure matters. A child who has had 6 hours of daily unsupervised screen time from 12 months of age will likely need more intensive support than one who had moderate exposure from age 2.
    • Individual variation is real. No two children respond identically. Some will bounce back quickly; others will need sustained therapy over a year or more.
    • Professional evaluation is non-negotiable. If symptoms do not improve meaningfully after 3 months of consistent screen reduction and enriched interaction, a formal developmental assessment is essential – because what looks like virtual autism may, in some cases, be ASD or another developmental condition that needs its own pathway of support.

    The bottom line for parents: you have not missed a window that cannot be reopened. If your child is under 5 and you are acting now, the brain is still very much on your side.

    Signs of Virtual Autism Recovery – What to Look For

    Recovery does not happen overnight, and it rarely announces itself dramatically. It shows up in small, quiet moments – a glance held a second longer, a new word said unprompted, a giggle during a game. These are the milestones worth celebrating.

    Here are the encouraging signs that your child is moving in the right direction:

    1. Increased Eye Contact

    One of the earliest and most reliable signs of recovery is a child who begins to hold your gaze more naturally. You might notice it during feeding, during a song, or when you call their name. It may last only a second at first. That second matters enormously – it signals that the child’s social brain is beginning to re-engage.

    2. Spontaneous Speech or New Words

    When a child starts producing new words – especially without being prompted – it is a strong indicator that language pathways are activating. Watch for words that emerge in context: “ball” when they want to play, “mama” when they want comfort. Spontaneous, functional speech is a very different thing from repeating sounds heard on a screen.

    3. Interest in Toys and Imaginative Play

    A child who was previously fixating on a screen or lining up objects repetitively begins to pick up a toy and use it with intent – pretending a spoon is a phone, feeding a stuffed animal, building something and showing it to you. This shift from repetitive to imaginative play is a significant developmental leap and a clear sign of recovery.

    4. Seeking Interaction with Parents and Siblings

    Watch for the child who starts coming to you – tugging at your sleeve, bringing you a book, pulling you toward something they want to show you. This social initiation is one of the most meaningful recovery signs. It means the child is beginning to prefer human connection over passive screen stimulation.

    5. Reduced Tantrums When Screens Are Removed

    In the early stages of screen reduction, meltdowns are common and expected. They are a sign of withdrawal, not failure. As recovery progresses, you will notice these tantrums becoming shorter, less intense, and less frequent. A child who can be redirected to another activity within a few minutes – rather than screaming for 40 – is making real progress.

    6. Improved Attention During Non-Screen Activities

    Screens are engineered to hold attention through rapid cuts, bright colours, and constant novelty. The real world cannot compete – at first. But as the brain recalibrates, children begin to sustain attention during slower, richer activities: a picture book, a puzzle, a conversation. Even 5 minutes of focused engagement with a non-screen activity, where there was none before, is worth noting.

    7. Emotional Responsiveness – Smiling Back, Reacting to Names

    A child who begins to smile when you smile, laugh when you laugh, or look up when their name is called is demonstrating that their social-emotional circuits are coming back online. These responses – so automatic in typically developing children – are genuinely hard-won milestones for a child recovering from virtual autism, and they deserve to be recognised as such.

    How to Help a Child with Virtual Autism – Treatment and Recovery Steps

    There is no single prescription for virtual autism recovery. But there is a clear direction. The steps below are evidence-informed, practical, and designed to work within the reality of Indian family life.

    Step 1: Reduce Screen Time – Gradually and Deliberately

    Cold turkey rarely works for young children. A sudden, total removal of screens often triggers intense distress that makes everything harder. Instead, reduce screen time in stages over 2–4 weeks.

    The American Academy of Pediatrics (AAP) guidelines are a useful benchmark:

    • Under 18 months: no screen media at all, except video calls with family members.
    • 18–24 months: if introduced, only high-quality content, always co-viewed with a parent.
    • Ages 2–5: maximum 1 hour per day of age-appropriate, high-quality programming – co-viewed, not solo.

    Use these as your target, not your starting point. If your child is currently watching 4 hours a day, reduce to 3, then 2, then 1 – week by week. Replace each removed hour with something from the steps below.

    Step 2: Replace Screen Time with Face-to-Face Interaction Rituals

    The brain learns language, emotion, and social connection through live human interaction – not through watching it on a screen. Build daily rituals that create these interactions:

    • Reading aloud together – even 10 minutes a day of shared picture-book reading builds vocabulary, joint attention, and emotional bonding. Point to pictures, name things, pause and wait for the child to respond.
    • Singing and nursery rhymes – songs with repetition, gesture, and eye contact (think Johny Johny, Twinkle Twinkle, Machli Jal Ki Rani) are powerful language tools.
    • Turn-taking games – rolling a ball back and forth, stacking blocks and knocking them down together, simple peek-a-boo. These teach reciprocity, the foundation of all communication.
    • Narrate your day – talk to your child constantly. “Now we’re washing hands. Cold water! Now we’re drying. Good job.” This running commentary builds language comprehension even before the child can respond.

    Step 3: Prioritise Outdoor and Sensory Play

    Many children with virtual autism symptoms show signs of sensory dysregulation – they are either over-sensitive or under-sensitive to touch, sound, and movement, partly because passive screen time does not provide the varied sensory input the developing brain needs.

    Outdoor play addresses this directly:

    • Sand play, water play, and mud play provide rich tactile input.
    • Running, climbing, and swinging develop vestibular and proprioceptive systems.
    • Interaction with other children in a park or playground builds social skills organically.

    Even 30–45 minutes of outdoor play daily can make a measurable difference within weeks.

    Step 4: Seek Speech Therapy If Delays Persist

    If your child’s speech has not shown meaningful improvement after 3 months of consistent screen reduction and enriched interaction, do not wait further. Refer to a qualified speech-language pathologist.

    Speech therapy for virtual autism typically focuses on:

    • Building functional vocabulary (words the child uses to communicate needs and wants)
    • Developing joint attention and turn-taking in conversation
    • Encouraging spontaneous communication rather than scripted or prompted responses

    The earlier speech therapy begins, the better the outcomes. A child who starts at 2 years will generally progress faster than one who starts at 4.

    Step 5: Consider Occupational Therapy for Sensory and Motor Development

    If your child shows significant sensory sensitivities, poor motor coordination, or difficulty with daily activities like self-feeding, dressing, or sitting still for play, occupational therapy (OT) is worth exploring.

    OT for young children addresses:

    • Sensory processing and regulation
    • Fine and gross motor skill development
    • Play skills and social participation
    • Self-care routines

    An occupational therapist can also guide parents on setting up a sensory-friendly home environment that supports the child’s recovery.

    Step 6: Know When to Seek a Formal ASD Evaluation

    This is the most important step many parents delay – and the one that matters most.

    Seek a formal developmental evaluation if:

    • Symptoms do not improve, or worsen, after 3 months of consistent screen reduction and intervention
    • Your child shows no meaningful speech by 18 months, or no two-word phrases by 24 months
    • You notice regression – loss of skills the child previously had
    • Repetitive behaviours are intensifying rather than reducing
    • Your gut, as a parent, tells you something more is going on

    A formal evaluation by a developmental paediatrician, child psychologist, or multidisciplinary team will clarify whether your child has ASD, a speech or language disorder, a sensory processing difference, or a combination – and will open the door to the right support.

    Getting a diagnosis is not a failure. It is the fastest route to the right help.

    Conclusion

    Conclusion illustration emphasizing early professional assessment for autism and virtual autism symptoms in children

    It is quite natural for a parent to feel confused between autism and virtual autism based on the symptoms. Several autism symptoms are similar to those that are visible in children with autism. However, there is a slight distinction between the two. Even if you notice a few of the symptoms listed above, it is best to seek professional help to manage the condition effectively. 

    Frequently Asked Questions

    What is virtual autism in simple terms?

    Virtual autism is an informal term which describes autism-like developmental symptoms in young children that are believed to be strongly influenced by excessive early screen exposure, rather than an underlying neurodevelopmental condition. It is not a medical diagnosis but a descriptive concept used in developmental discussions.

    Is virtual autism real or just an internet myth?

    The behaviours associated with virtual autism are real and clinically observed. However, the term itself is not an official diagnosis. It is used to explain autism-like symptoms linked to environmental factors, particularly heavy screen use.

    Can screen time really cause virtual autism symptoms?

    Screens do not “cause” autism. However, excessive passive screen exposure during early childhood can interfere with speech, attention, and social development, leading to virtual autism symptoms that resemble autism.

    Can virtual autism be cured completely?

    Parents often ask whether virtual autism can be cured. If symptoms are primarily environmental, many children show significant improvement or resolution with early intervention, reduced screen time, and increased social interaction. Outcomes vary by child.

    Can a child have both autism and virtual autism traits?

    Yes. A child with autism may also experience worsening symptoms because of excessive screen exposure. Reducing screen time benefits children regardless of diagnosis.

    What should parents do if virtual autism symptoms worsen after screen removal?

    Temporary behavioural challenges can occur during screen withdrawal. In case the symptoms persist or worsen over time, consult a healthcare professional to rule out autism or other developmental conditions.

    Disclaimer: This article is intended for educational and informational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. If you are pregnant or have concerns about medication use during pregnancy, please consult a qualified healthcare provider. If your child has received an autism diagnosis and you have questions about causes or support, please reach out to a trained specialist or an autism-focused organisation for guidance.

    Useful Sources

    American Academy of Pediatrics – Media and Young Minds

    Harvard Center on the Developing Child – Brain Architecture

    PMC – Neuroplasticity and Early Intervention in Children

    DSM-5 / ICD-11 – ASD Diagnostic Criteria

    PMC – Long-Term Outcomes in Autism Spectrum Disorder

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

  • What Is Nonverbal Autism? Signs, Causes & Communication Strategies

    What Is Nonverbal Autism? Signs, Causes & Communication Strategies

    Autism is a spectrum, and every individual experiences it differently. One of the most misunderstood aspects of autism is nonverbal autism. It is a condition where individuals have limited or no spoken language but still communicate in other meaningful ways.

    In fact, out of the total number of individuals on the autism spectrum disorder, about 30% of the children are minimally verbal. However, there can still be considerable improvement in speech and language if intervention is provided early.

    While the absence of speech can feel overwhelming, understanding the nuances of autism and nonverbal communication is the first step toward unlocking your child’s potential.

    Today, we are looking deeply into the meaning, symptoms, causes, and supportive methods that can help a nonverbal individual lead a fulfilling life.

    What is Nonverbal Autism?

    What is Nonverbal Autism?

    Nonverbal autism is not a separate diagnosis. It is a specific presentation within Autism Spectrum Disorder (ASD) where an individual uses little or no spoken language to communicate. Some children produce no speech at all. Others have a handful of words they use without meaningful context – they might say “biscuit” every day but never use it to actually ask for one.

    The clinical term you’ll see in research is “minimally verbal” – defined as fewer than 20 functional words used consistently. According to a landmark study published in PNAS (Tager-Flusberg & Kasari, 2013), approximately 25–40% of individuals on the autism spectrum are minimally verbal or nonspeaking. That is a significant portion of the ASD community, and yet it remains dramatically underrepresented in research and public conversation.

    Three outcome pathways – what the research actually shows:

    1. Full or near-typical speech development. Some children who are minimally verbal at age three develop functional spoken language by age five or six, particularly with early, intensive intervention. A 2023 study in the Journal of Autism and Developmental Disorders found that roughly 20% of minimally verbal children made substantial gains in speech with targeted therapy before age five.

    2. Partial speech alongside AAC. Many individuals develop some functional spoken words – enough to express basic needs – but rely on Augmentative and Alternative Communication (AAC) for more complex communication. This is the most common outcome pathway.

    3. Permanently nonspeaking. Some individuals remain nonspeaking throughout life. This does not mean they cannot communicate. It means they communicate differently – through AAC devices, sign language, picture boards, writing, or typing. Many nonspeaking autistic adults have written books, given talks, and led full, meaningful lives.

    Actionable takeaway: Do not let anyone tell you there is a “window” that closes. Research consistently shows that communication development can occur at any age with the right support.

    “Nonverbal” vs. “Nonspeaking” vs. “Preverbal” – Why the Words We Use Matter

    "Nonverbal" vs. "Nonspeaking" vs. "Preverbal" - Why the Words We Use Matter

    Language shapes how we think about people. This is not a small debate.

    “Nonverbal” is the most commonly used clinical term, and it’s what most parents search for. But many autistic self-advocates and researchers argue it is misleading – because it implies the person has no language at all, when in fact they may have rich inner language, strong reading comprehension, and the ability to communicate through text or AAC.

    “Nonspeaking” is the term increasingly preferred by the autistic community and by progressive clinicians. It is precise: it describes the absence of spoken output, not the absence of language or thought. Nonspeaking autism acknowledges that the person has a voice – it just doesn’t come through the mouth.

    “Preverbal” is sometimes used for very young children (typically under age three) who haven’t yet developed speech, but for whom speech is still a realistic possibility. It is a developmental stage descriptor, not a permanent label.

    At India Autism Center, we use both “nonverbal” and “nonspeaking” alongside each other – because parents searching for help use “nonverbal autism,” and we want to meet them where they are. But in our clinical practice and in how we speak about the individuals we support, we increasingly prefer “nonspeaking” because it centres the person’s humanity and potential, not their deficit.

    Actionable takeaway: When talking to your child’s school, therapists, or extended family, try shifting to “nonspeaking” – it opens a different conversation about capability rather than limitation.

    How Common Is Nonverbal Autism?

    How Common Is Nonverbal Autism?

    More common than most people realise.

    The most widely cited figure is 25–40% of people with ASD are minimally verbal or nonspeaking (Tager-Flusberg & Kasari, 2013, PNAS). The CDC’s Autism and Developmental Disabilities Monitoring (ADDM) Network 2022 data adds important nuance: among autistic individuals, 39.6% had co-occurring intellectual disability, 24% had borderline intellectual functioning, and – critically – 36% scored average or above on nonverbal IQ tests. That last number matters enormously. More on that in the causes section.

    The Autism Science Foundation’s analysis of CDC data found that 26.7% of autistic children fall into the “profound autism” category, which includes most nonspeaking individuals.

    India context: India does not yet have a national autism prevalence registry equivalent to the CDC ADDM. Estimates from studies published in the Indian Journal of Pediatrics suggest ASD prevalence in India is approximately 1 in 68–100 children, broadly consistent with global figures. Given that 25–40% of those may be minimally verbal, we are potentially talking about hundreds of thousands of nonspeaking autistic individuals in India – the vast majority without access to specialist AAC support or trained SLPs.

    Actionable takeaway: If your child has been diagnosed with ASD and is not yet speaking, know that you are part of a large community – and that community has produced powerful advocates, communicators, and change-makers.

    Autism vs Nonverbal Learning Disorder: How Do They Differ?

    Autism vs Nonverbal Learning Disorder: How Do They Differ?

    The two concepts of autism and nonverbal learning disorder can be quite confusing. While the names are strikingly similar, the profiles of these two conditions are nearly opposites.

    Nonverbal Learning Disorder (NVLD) is characterised by:

    • Strong verbal skills and early speech development.
    • Excellent rote memory.
    • Significant struggles with non-linguistic information, such as visual-spatial patterns, mathematics, and reading social cues (facial expressions and body language).

    In contrast, nonverbal autism involves:

    • Significant delays or a total absence of spoken language.
    • Social communication challenges.
    • Repetitive behaviours and restricted interests.

    While both require specialised educational support, the methods for teaching a student with nonverbal autism focus heavily on building a communication system from the ground up. In contrast, NVLD support focuses on helping a verbal student navigate physical space and social nuances.

    What Are the Most Common Signs and Symptoms of Nonverbal Autism?

    What Are the Most Common Signs and Symptoms of Nonverbal Autism?

    Early intervention is the “gold standard” for improving outcomes. Knowing the signs of nonverbal autism allows parents to seek support during the critical years of brain plasticity.

    Here are some of the common nonverbal autism symptoms:

    • No speech or very limited vocabulary: A child may not speak at all or may repeat a few words without meaningful use. For example, they might echo phrases but not use them to communicate needs.
    • Difficulty understanding spoken language: Difficulty understanding spoken language.
    • Limited use of gestures: They may not point at objects, wave goodbye, or answer yes or no with a nod. This reduces their ability to communicate basic needs.
    • Avoidance of eye contact: Eye contact may feel uncomfortable or overwhelming, making social interaction harder.
    • Repetitive behaviours: Actions such as hand-flapping, rocking, or spinning objects may help them regulate their emotions or sensory input.
    • Difficulty expressing needs verbally: Instead of directly asking for water, a child might cry, pull a caregiver, or become agitated.
    • Strong preference for routines: When there is a change in routine, there is distress because predictability provides comfort.
    • Sensory sensitivities: Sounds, lights, textures, or smells may feel overwhelming or painful.

    Early Signs of Nonverbal Autism in Toddlers

    Early Signs of Nonverbal Autism in Toddlers

    The signs of nonverbal autism in toddlers can appear before age two. About 40–70% of children with ASD show delayed speech and language development. The earlier you notice and act, the better.

    Watch for:

    • No babbling by 12 months – babies typically start making consonant-vowel sounds (“ba,” “da,” “ma”) well before their first birthday
    • Not responding to their name by 12 months, even when called consistently and from close range
    • No pointing or showing objects by 14 months – joint attention (sharing interest in something with another person) is a key pre-language milestone
    • No single words by 16 months
    • No two-word phrases by 24 months (e.g., “more milk,” “Daddy go”)
    • Regression – losing words or skills they previously had, which can occur between 18 and 24 months
    • Difficulty imitating sounds or actions

    If you notice three or more of these signs, speak to your paediatrician immediately and ask for a referral to a developmental paediatrician or speech-language pathologist. Don’t wait for the “wait and see” approach – early intervention is the single most evidence-backed strategy we have.

    What Causes Nonverbal Autism?

    What Causes Nonverbal Autism?

    The question of what causes nonverbal autism is one that researchers are working tirelessly to answer. In 2026, the consensus is that there is no single “autism gene.” Instead, it is a combination of environmental and genetic factors that can influence brain development during pregnancy as well as early infancy.

    1. Neurological Factors

    Studies using functional MRI (fMRI) are known to show that in nonverbal autistic individuals, Broca’s area, the part of the brain that is primarily responsible for speech production, may function differently. 

    There may be “under-connectivity” between the brain areas that perceive sound and those that control the muscles of the mouth.

    2. Motor Planning and Apraxia

    Sometimes, the cause isn’t a lack of language understanding but a “motor planning” issue. Conditions like Childhood Apraxia of Speech often overlap with autism. 

    In these cases, the child’s brain knows the word “Mama,” but the message gets scrambled on the way to the lips and tongue. This is why nonverbal speech therapy programs for autism often include physical exercises for the mouth.

    3. Genetic Predispositions

    Although not every child with autism necessarily has a family history, genetics can play a massive role. Certain rare genetic mutations are more common in nonverbal individuals. Understanding the biological roots helps remove the stigma and the guilt that parents often feel. This helps to reinforce that autism is a natural neurological variation.

    The Three Communication Pathways – What to Expect

    The Three Communication Pathways - What to Expect

    Let’s be direct about what the research shows – and frame it with hope.

    Pathway 1: Speech emerges. With early, intensive, evidence-based intervention, some minimally verbal children develop functional spoken language. A 2023 meta-analysis in Autism Research found that children who began intensive speech and AAC intervention before age four had significantly better language outcomes than those who started later. This is not a guarantee – but it is a real possibility worth pursuing urgently.

    Pathway 2: Multimodal communication. This is the most common outcome. The individual develops some spoken words alongside AAC tools – a tablet, a picture board, sign language. They communicate across multiple channels depending on context, energy, and environment. Many adults in this pathway lead deeply connected, productive lives.

    Pathway 3: Primarily AAC-based communication. Some individuals remain primarily nonspeaking throughout life. This is not a failure. It is a different way of being in the world. Nonspeaking autistic author Naoki Higashida wrote The Reason I Jump using a letter board. Carly Fleischmann hosts a talk show using AAC. Amy Sequenzia writes poetry and advocacy essays. The absence of speech is not the absence of a story.

    Actionable takeaway: Whichever pathway your child is on, AAC should begin now – not after speech fails, not as a last resort. AAC does not prevent speech development. Research consistently shows it supports it.

    Nonverbal Autism Life: What to Expect in Adulthood?

    Nonverbal Autism Life

    One of the deepest anxieties for parents is the nonverbal autism life as an adult. Parents often wonder, “What happens when I am no longer here to advocate for them?”

    It is important to emphasise that being nonverbal does not inherently reduce a person’s life expectancy. However, the life of a nonverbal person with autism can be affected by secondary factors. 

    For example, if an individual cannot communicate that they are in pain, a medical condition such as a tooth infection or appendicitis might go untreated longer than it would in a verbal person. This is why teaching functional communication is literally a matter of safety.

    Nonverbal Autism in Adults

    As we look at nonverbal autism in adults, the definition of success shifts. For an adult, success might mean:

    • Using a tablet to order food at a restaurant.
    • Working in a supported employment environment.
    • Living in a group home or a community-integrated apartment with the help of a caregiver.

    AAC for Nonverbal Autism – A Complete Guide for Indian Families

    AAC for Nonverbal Autism

    AAC for autism – Augmentative and Alternative Communication – is the umbrella term for any method of communication that supplements or replaces spoken speech. It is not a consolation prize. It is a communication right.

    And for Indian families, there are specific considerations that most Western guides simply don’t address.

    No-Tech and Low-Tech AAC

    You don’t need a device to start. Low-tech AAC is powerful, portable, and free.

    • PECS (Picture Exchange Communication System): The child hands a picture card to a communication partner to request something. Phase 1 is simply: “I want this.” Over six phases, PECS builds to full sentence construction. It is one of the most researched AAC systems for autism, with strong evidence from randomised controlled trials.
    • Picture boards/communication books: A laminated book or folder of photographs and symbols organised by category (food, feelings, activities, people). Incredibly effective when consistently used across all environments.
    • Core vocabulary boards: Rather than pictures of specific items, core boards use high-frequency words (“want,” “more,” “stop,” “go,” “help,” “like”) that appear in almost every conversation. These are more generalisable than item-specific pictures.
    • Sign language: Covered in detail below. Even 5–10 functional signs can transform daily life.

    A note on Indian Sign Language (ISL): ISL is a complete, independent language – not a signed version of Hindi or English. It has its own grammar and regional variations. For families in India, ISL is the most accessible sign system. The Ali Yavar Jung National Institute of Speech and Hearing Disabilities (AYJNISHD) in Mumbai offers ISL resources and training. The Indian Sign Language Research and Training Centre (ISLRTC) in New Delhi has developed a national ISL dictionary available online.

    High-Tech AAC

    Speech-generating devices (SGDs) and AAC apps produce spoken output – either synthesised or recorded voice – when the user selects symbols, words, or phrases.

    • Proloquo2Go: The gold standard AAC app, available on iPad. Highly customisable, research-backed, used globally. Expensive (around ₹8,000–10,000 per year), but widely used in IAC therapy sessions.
    • Avaz AAC: Developed in India by Invention Labs, Chennai. Specifically designed for autism, with support for multiple Indian languages including Hindi, Tamil, Telugu, Kannada, and Bengali. This is our top recommendation for Indian families – it understands the cultural and linguistic context.
    • Snap Core First: Another robust AAC app with strong symbol libraries and customisation options.
    • Dedicated SGDs: Devices like the Tobii Dynavox are used for individuals with significant motor difficulties alongside communication needs. These are available in India through specialised suppliers, though cost remains a barrier.

    AAC in Multilingual Indian Homes – Hindi, Regional Languages, and Code-Switching

    This is where most AAC guides fail Indian families entirely. Let’s fix that.

    The average middle-class Indian household operates in at least two languages – often a regional language at home and Hindi or English at school. Many families use all three fluidly, switching mid-sentence. This is called code-switching, and it is completely normal, cognitively healthy, and linguistically rich.

    Does bilingualism delay communication in nonspeaking autistic children? No. The research is detailed on this. A 2016 study in the Journal of Child Language (Hambly & Fombonne) found no evidence that bilingual exposure delays language development in autistic children. A 2019 study in Autism & Developmental Language Impairments confirmed that bilingual autistic children do not show worse language outcomes than monolingual peers. Bilingualism does not cause or worsen nonverbal autism.

    Practical strategies for multilingual AAC:

    • Programme your AAC device in both languages. Avaz AAC allows multilingual symbol sets. If your child hears “paani” at home and “water” at school, both words should be available on the device.
    • Use the home language first. Research on bilingual AAC (Kohnert, 2010) suggests that building communication in the child’s strongest language first creates a foundation that transfers to the second language.
    • Don’t force English-only AAC. Many families feel pressure to use only English AAC because “that’s what the therapist uses.” Push back on this. Your child’s right to communicate in their mother tongue is fundamental.
    • Consistent vocabulary across languages. Core words like “more,” “stop,” “help,” and “want” should be programmed in all languages the child hears regularly.
    • Talk to your SLP about code-switching. A good SLP will programme the AAC device to reflect how your family actually communicates – not an idealised monolingual version of it.

    Apps with Indian language support:

    • Avaz AAC – Hindi, Tamil, Telugu, Kannada, Bengali, Marathi, Malayalam
    • Cboard – open-source, community-translated into several Indian languages
    • LetMeTalk – supports custom symbol sets; families can add regional language labels

    Actionable takeaway: Contact Avaz AAC’s India support team directly – they offer free trials and have worked with Indian SLPs to develop culturally relevant symbol sets. Don’t let language be a barrier to starting AAC.

    Can Nonverbal Autism Be Cured?

    Can Nonverbal Autism Be Cured?

    It has been found in a study that 26.7% of autistic children fall under the profound autism category, which includes nonverbal autism as well. Hence, the question “Can nonverbal autism be cured?” is controversial. In the medical sense, there is no cure because autism is not a disease or an infection; it is a different way the brain is wired. You cannot “un-wire” a brain.

    However, if by “cure,” a parent means “Can my child learn to communicate and live a happy life?”, the answer is a resounding yes. Through intensive speech therapy, autism nonverbal and behavioural interventions, many children who were nonverbal at age four gain significant speech by age eight. 

    For those who remain nonverbal, the goal is not to “fix” them but to provide them with the tools to interact with a primarily verbal world.

    Speech Therapy for Nonverbal Autism: More Than Just Talking

    Speech Therapy for Nonverbal Autism

    When people hear “speech therapy,” they picture a child repeating words in front of a mirror. Speech therapy for nonverbal autism is far more sophisticated than that.

    A skilled Speech-Language Pathologist (SLP) working with a nonspeaking child focuses first on the foundations of communication – the pre-linguistic skills that must be in place before speech or AAC can be used meaningfully.

    The foundational triad:

    • Imitation: Can the child copy a movement? A sound? A facial expression? Imitation is the engine of learning. Without it, no communication system can take hold.
    • Turn-taking: Communication is a back-and-forth exchange. Rolling a ball, taking turns with a toy, pausing and waiting – these are the social-cognitive roots of conversation.
    • Cause and effect: “If I press this button, music plays.” “If I hand this picture to Amma, I get a biscuit.” Understanding that my action produces a result is the foundation of intentional communication.

    What an IAC speech therapy session looks like:

    At India Autism Center, our SLPs don’t work in isolation. A session for a nonspeaking child might include:

    1. Sensory warm-up – regulating the child’s nervous system before communication work begins (often in coordination with our occupational therapy team)
    2. Joint attention activities – following the child’s lead, building shared focus on an object or activity
    3. AAC modelling – the therapist uses the AAC device alongside the child, modelling how to communicate without demanding the child use it (“aided language stimulation”)
    4. PECS or core board practice – structured, motivating exchanges
    5. Oral motor exercises – for children with suspected CAS, specific exercises to improve motor planning for speech
    6. Parent coaching – every session includes time to teach the family what was done and how to replicate it at home

    The last point is non-negotiable. Therapy happens for one or two hours a week. Communication happens all day. Parents are the most important communication partners a child has.

    To learn more about our speech and language therapy approach, visit our comprehensive guide.

    Actionable takeaway: Ask your SLP to teach you “aided language stimulation” – it is the single most powerful thing a parent can do at home to support AAC use.

    What Are the Effective Methods For Teaching A Child With Nonverbal Autism?

    What Are the Effective Methods For Teaching A Child With Nonverbal Autism?

    Teaching a nonspeaking child requires a structured, visual, and consistent approach. Here are the methods with the strongest evidence base:

    1. Picture Exchange Communication System (PECS): The child hands a picture to a communication partner to receive a desired item. It teaches the fundamental power of initiation – I can make things happen by communicating. PECS has six phases, from simple requesting to commenting and answering questions.

    2. Treatment and Education of Autistic and Communication-related Handicapped Children (TEACCH): Developed at the University of North Carolina, TEACCH emphasises structured physical environments with clear visual boundaries. For a nonspeaking child, knowing exactly where the “work zone” ends and the “play zone” begins dramatically reduces anxiety and increases engagement.

    3. Discrete Trial Training (DTT): Breaking complex skills into tiny, manageable steps and using systematic positive reinforcement to build each step. DTT is particularly effective for teaching new vocabulary and AAC use. Learn more about ABA therapy, which incorporates DTT.

    4. Video Modelling: Showing the child a video of a peer or adult performing a task (washing hands, requesting a snack, greeting someone) can be more effective than verbal instruction for visual learners. The child’s brain processes the visual demonstration more readily than spoken directions.

    5. Functional Communication Training (FCT): FCT replaces challenging behaviours (hitting, biting, screaming) with functional communication. The premise: if a child is hitting to escape a task, teach them to hand over a “break” card instead. FCT is one of the most powerful tools for reducing behavioural challenges in nonspeaking children, because it addresses the communicative function of the behaviour.

    Actionable takeaway: Ask your child’s school whether they are using FCT. If a child has a behaviour support plan that doesn’t include a communication replacement behaviour, it is incomplete.

    How Does Sign Language For Nonverbal Autism Help?

    How Does Sign Language For Nonverbal Autism Help?

    Sign language for nonverbal autism is one of the most accessible, low-cost, and immediately effective communication tools available.

    Why it works:

    • Portability: Your hands are always with you. No device to charge, no app to open.
    • Kinesthetic learning: The physical movement of signing reinforces meaning in the brain – the body remembers what the mouth cannot yet say.
    • Immediate feedback: A parent can gently guide a child’s hands to form the sign, providing physical prompts impossible with vocal speech.
    • Reduces meltdowns: Even five basic signs – Eat, Drink, More, Help, All Done – can dramatically reduce the frustration-driven behaviours that come from an inability to express basic needs.

    Indian Sign Language (ISL) context:

    ISL is not a regional dialect of British or American Sign Language. It is an independent language, recognised by the Government of India under the Rights of Persons with Disabilities (RPWD) Act 2016. ISL has its own grammar, syntax, and regional variations (signs may differ between Mumbai, Delhi, and Chennai communities).

    For families in India, learning even basic ISL signs is more culturally integrated and community-relevant than learning ASL. Resources:

    • ISLRTC (Indian Sign Language Research and Training Centre) – New Delhi – offers online courses and a national dictionary
    • AYJNISHD – Mumbai – training programmes for families and educators
    • YouTube ISL channels – several ISL educators post free tutorials in Hindi and English

    Actionable takeaway: Start with five signs this week. Eat, drink, more, help, all done. Use them consistently every time you say the word. Repetition across contexts is what builds the connection.

    What Are the Best Free Apps for Nonverbal Autism?

    What Are the Best Free Apps for Nonverbal Autism?

    Free and low-cost options:

    • Cboard (free, web-based and app) – open-source AAC with community-translated symbol sets; works offline; supports multiple languages including Hindi
    • LetMeTalk (free, Android) – picture-based communication, works offline, fully customisable; families can add photos of real objects from their home
    • JABtalk (free, Android) – highly customisable, supports recorded voice output (record Amma’s or Baba’s voice for the buttons)
    • Snap Express (free version available) – quick-access core vocabulary board

    India-specific and Indian language-supported apps:

    • Avaz AAC (paid, iOS and Android) – our top recommendation for Indian families; developed in Chennai; supports Hindi, Tamil, Telugu, Kannada, Bengali, Marathi, Malayalam; used in IAC therapy sessions; free trial available
    • Kidsense Communication – developed with Indian SLPs; culturally relevant symbol sets including Indian foods, festivals, and family terms
    • Vidya Sagar’s AAC resources – Chennai-based disability organisation with free downloadable picture boards in Tamil and English

    For older children and adults:

    • Proloquo2Go (paid, iOS) – the most research-backed AAC app globally; highly customisable; used widely in IAC’s adult programmes
    • TouchChat HD (paid, iOS/Android) – robust vocabulary with good customisation for Indian language labels

    Actionable takeaway: Download LetMeTalk or Cboard today – right now, before you finish reading this article. Start with 10 pictures of things your child loves. That is your first AAC board.

    By introducing these free apps alongside early speech and language therapy for nonverbal autism, parents can give their child a sense of agency and control over their environment.

    What Therapies Help Individuals With Nonverbal Autism?

    What Therapies Help Individuals With Nonverbal Autism?

    Different therapies support communication, behaviour, and daily living skills. A combination of therapies is often the most effective approach. Here are the autism therapies that can be of great help:

    1. Speech Therapy: It primarily focuses on communication methods

    2. Occupational Therapy: This helps to improve daily skills as well as sensory processing

    3. Behavioural Therapy (ABA): This is very important as it helps to encourage positive behaviours

    4. Sensory Integration Therapy: It helps manage sensory sensitivities

    How Can Parents Successfully Create a Supportive Environment at Home?

    How Can Parents Successfully Create a Supportive Environment at Home?

    The home is where communication either flourishes or stagnates. Here are six concrete strategies:

    1. Label everything with pictures and words. Put a picture card on the toy bin, the pantry, the bathroom door, the bedroom. Use real photographs of your child’s actual objects – not clip art. This builds receptive vocabulary and makes the environment “readable.”

    2. Narrate your day – constantly. Even when your child doesn’t respond, describe what you are doing. “I am cutting the sabzi. The knife is sharp.” “We are going to the market. First market, then home.” This builds receptive language and gives your child the words they will eventually use – or programme into their AAC device.

    3. Wait. Then wait longer. After asking a question or making a request, count to ten silently. Nonspeaking brains often need significantly more processing time than neurotypical brains. The reflex to fill the silence is strong – resist it. The response may come.

    4. Follow their lead. If your child is fixated on spinning a bottle cap, sit with them and spin one too. Join their world before trying to bring them into yours. This is the foundation of relationship-based therapy approaches like Floortime/DIR.

    5. Create communication opportunities – don’t just meet needs. If your child wants biscuits, don’t just give them. Pause. Look expectant. Hold the packet and wait. Create the communicative need. Then respond enthusiastically to whatever communication attempt they make – a gesture, a look, a reach, a sound.

    6. Use visual schedules. A visual schedule – photographs or symbols showing the sequence of the day – reduces anxiety and creates predictable communication opportunities. “First bath, then breakfast, then school.” Predictability is not rigidity; it is safety.

    Actionable takeaway: Start with one strategy this week. The visual schedule is the highest-impact, lowest-effort place to begin.

    Conclusion

    If you are beginning to explore what nonverbal autism is, remember that a lack of speech is not a lack of soul. Your child has thoughts, preferences, and a unique personality. 

    They may communicate through the way they lean into your hug, the way they light up when they see their favourite toy, or the way they use a tablet to tell you they love you. The nonverbal autism lifespan is a journey of constant discovery. 

    With the right combination of awareness, intervention, therapy, assistive technology, and unconditional love, the “wall” of silence can become a window and can help to create a beautiful, different way of experiencing the world. 

    Stay patient, stay curious, and never stop listening to what your child is telling you, even when they aren’t using words.

    Frequently Asked Questions

    What is nonverbal autism in simple terms?

    Nonverbal autism essentially refers to individuals on the autism spectrum who do not generally use spoken language or have very limited speech. However, they still communicate using gestures, facial expressions, sounds, or tools like communication apps and picture boards to express their needs and emotions.

    What causes nonverbal autism?

    A combination of genetic, neurological, and developmental factors is the main cause of nonverbal autism. Differences in brain development, especially in language areas, also play a big role. There is no single cause, and it is not linked to vaccines or parenting styles.

    What are the early signs of nonverbal autism?

    Early signs include a lack of babbling, failing to respond when their name is called, limited eye contact, no pointing or gestures, and reduced or no interest in social interaction. Such signs tend to appear before age three; a child should be evaluated early for better outcomes.

    Are there free apps for nonverbal communication in autism?

    Yes, there are several free apps, such as Cboard, LetMeTalk, and JABtalk, that can considerably help individuals communicate using pictures and voice output. These apps are useful at home and school and can improve independence and reduce communication-related frustration.

    How is autism different from nonverbal learning disorder?

    Autism affects different aspects of life, such as communication, behaviour, and social interaction, often including varying levels of speech challenges. Nonverbal learning disorder mainly affects spatial and social skills, but individuals usually have strong verbal abilities. Proper diagnosis is necessary as it helps support strategies that differ between the two conditions.

    Disclaimer: This article is intended for educational and informational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. If you are pregnant or have concerns about medication use during pregnancy, please consult a qualified healthcare provider. If your child has received an autism diagnosis and you have questions about causes or support, please reach out to a trained specialist or an autism-focused organisation for guidance.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

    Useful Sources

    CDC ADDM Network (2022). Prevalence and Characteristics of Autism Spectrum Disorder Among Children.

    Autism Science Foundation / CDC Profound Autism Statistics

  • Level 3 Autism: What It Means for Your Child and What to Do Next

    Level 3 Autism: What It Means for Your Child and What to Do Next

    Receiving a Level 3 autism diagnosis can feel like the ground shifting beneath your feet – and it’s okay to need a moment before you can think clearly about next steps. Autism is not a one-size-fits-all condition. It exists on a spectrum, meaning every individual experiences it differently. Among the three levels defined under Autism Spectrum Disorder (ASD), level 3 autism is considered the most intensive in terms of support needs.

    Level 3 autism spectrum disorder is defined by the DSM-5 as “requiring very substantial support.” It sits at the highest end of the three-level classification system introduced when the DSM-5 replaced earlier labels like “severe autism” and “classic autism” in 2013.

    Here is how the three levels compare at a glance:

    • Level 1 ASD – Requiring support
    • Level 2 ASD – Requiring substantial support
    • Level 3 ASD – Requiring very substantial support

    The DSM-5 assigns Level 3 when a person shows severe deficits in verbal and nonverbal social communication and highly inflexible behaviour that markedly interferes with functioning across multiple settings – at home, at school, and in the community.

    What does “very substantial support” actually look like in daily life? It means your child may have very limited or no functional spoken language. A change in the morning routine – a different brand of biscuit, a different route to school – can trigger extreme distress. They need consistent, structured, one-to-one support for most of their waking hours.

    But here is what the diagnosis does not mean: it does not mean your child cannot learn, cannot communicate, or cannot live a life full of connection and purpose. A Level 3 diagnosis is a starting point, not a sentence. It tells you how much support your child needs right now – not what they are capable of becoming.

    You may also hear the term “stage 3 autism” used in conversation. It’s worth clarifying: autism is not a progressive disease with stages that worsen over time. It is a neurodevelopmental condition with levels of support needed. Using the correct term matters – it affects how services are accessed and how insurance or government benefits are applied.

    What is Level 3 Autism?

    What is Level 3 Autism

    Level 3 autism spectrum disorder refers to the most severe classification within ASD. Individuals diagnosed at this level need very substantial support in their daily lives. To understand what level 3 autism is, it helps to know how autism levels are defined:

    Level 1 Autism: Requires support

    Level 2 Autism: Requires substantial support

    Level 3 Autism: Requires complete support

    People with autism level 3 often have significant challenges in communication, social interaction, and behavior. These challenges can affect nearly every part of daily functioning.

    Individuals who have level 3 autism have very limited use of functional speech, experience extreme distress when routines change, and may have significant sensory sensitivities. For parents, this often means your child lives in a world that feels much louder, brighter, and more chaotic than it does for others.

    You might occasionally hear people use the term stage 3 autism. It is important to clarify that autism is not a progressive disease with “stages.” Instead, it is a developmental condition with “levels” of support. Using the correct terminology helps in accessing the right therapeutic resources and insurance coverage.

    Recognising Autism Level 3 Symptoms

    Recognising Autism Level 3 Symptoms

    In the world of ASD level 3, the sensory input of daily life, the texture of a shirt, or the flickering of a fluorescent light, can be as overwhelming as a thunderclap.

    When we discuss autism level 3 symptoms, we are referring to a set of behaviors that indicate a person needs substantial support to navigate daily life. These symptoms are categorised into two main categories: social communication and restrictive, repetitive behaviors.

    1. Social Communication Challenges

    In Level 3, communication is often the most significant hurdle. While a child with Level 1 might struggle with sarcasm or social cues, a child with Level 3 autism may struggle to convey basic physical needs like hunger or pain.

    Limited or Absent Verbal Speech

    • Many individuals use “functional language” only, meaning they might use single words to get what they need, but cannot engage in a back-and-forth conversation.
    • Some may use echolalia, which is the repetition of phrases they have heard in movies or from parents, but they may not use these phrases to communicate a specific thought.

    Difficulty with Social Initiation and Response

    • They may not respond when their name is called, even if their hearing is perfect.
    • They might not use gestures, such as pointing at an aeroplane in the sky or waving goodbye.
    • Social reciprocity (the natural give-and-take of human interaction) is often absent. They may seem to be in their own world, not out of a desire to be alone, but because the “social coding” others use is not processed by their brain the same way.

    2. Restrictive and Repetitive Behaviours

    The second pillar of what is level 3 autism involves behaviors that provide the individual with a sense of order and safety in a chaotic world.

    Inflexible Adherence to Routines

    • A change as minor as the brand of milk in the fridge or the sequence of putting on shoes can cause extreme distress.
    • This distress often manifests as a “meltdown,” a total neurological overload distinct from a typical toddler tantrum.

    Intense Repetitive Movements (Stimming)

    • Motor Stims: This includes vigorous hand-flapping, rocking back and forth, or spinning in circles for long periods.
    • Visual Stims: A child might stare at the spinning blades of a fan or line up toys in a perfectly straight line for hours, becoming highly distressed if one toy is moved.

    Sensory Processing Issues

    • Hypersensitivity: They may be hyper-aware of sounds, smells, or lights that others don’t notice. The sound of a hair dryer might feel physically painful.
    • Hyposensitivity: Conversely, they may have a high pain threshold or a “sensory seeking” behavior, such as crashing into walls or furniture to feel the physical pressure against their body.

    Identifying Level 3 Autism in a Toddler

    Identifying Level 3 Autism in a Toddler

    The earlier a child is identified, the earlier support can begin – and the evidence on early intervention is clear: it makes a difference.

    Most parents of children with Level 3 autism look back and say they noticed something was different in the first year of life. Here is what to watch for at each stage:

    12–18 Months

    • No pointing to share interest in objects or events
    • No waving goodbye or hello
    • No babbling or very limited vocalisation
    • Not responding to their name consistently
    • Limited or no eye contact during feeding or play
    • No imitation – not copying simple actions like clapping or banging a spoon

    18–24 Months

    • No meaningful two-word phrases (not counting echolalia)
    • Loss of previously acquired language – a child who said “mama” or “ball” and then stopped
    • No pretend play – not feeding a doll, not using a banana as a phone
    • Intense fixation on parts of objects – spinning the wheels of a toy car rather than rolling it
    • Extreme distress at transitions – moving from one activity to another causes prolonged crying or self-injurious behaviour

    2–3 Years

    • Very limited or no functional communication – cannot reliably request food, drink, or comfort
    • Repetitive movements that are intense and prolonged
    • No interest in other children – does not watch, approach, or imitate peers
    • Severe sensory reactions – refuses certain foods, fabrics, environments
    • Meltdowns that are frequent, intense, and difficult to de-escalate

    If you are seeing several of these signs, do not wait for your child to “grow out of it.” Ask your paediatrician for a referral to a developmental specialist. Early intervention before age 3 is when the brain is most plastic – most able to form new connections in response to structured learning.

    Steps in the Diagnostic Process

    Steps in the Diagnostic Process

    A diagnosis can take months – and for many Indian families, navigating the process without a clear roadmap is exhausting. Here is how it works.

    Developmental Screening

    The first step is usually a developmental screening at your paediatrician’s clinic. The most widely used tool is the M-CHAT-R/F (Modified Checklist for Autism in Toddlers, Revised with Follow-Up), recommended at the 18-month and 24-month well-child visits.

    If your child scores in the high-risk range, your paediatrician should refer you for a formal diagnostic evaluation. In India, this referral often goes to a developmental paediatrician, child psychiatrist, or a specialised autism assessment centre.

    The Formal Evaluation Team

    No single clinician diagnoses Level 3 autism alone. A thorough evaluation typically involves:

    • Developmental Paediatrician – rules out other neurological or medical conditions
    • Child Psychologist or Psychiatrist – assesses cognitive functioning, adaptive behaviour, and emotional profile
    • Speech-Language Pathologist (SLP) – evaluates the severity of communication delays and functional language
    • Occupational Therapist (OT) – assesses sensory processing, fine motor skills, and daily living abilities

    Expect the full evaluation to take multiple sessions across several weeks. This is normal – and it is worth doing thoroughly.

    Diagnostic Tools (ADOS-2, ADI-R, DSM-5 Criteria)

    The gold standard diagnostic tools used internationally – and increasingly in India’s leading centres – are:

    ISAA (Indian Scale for Assessment of Autism): Developed specifically for the Indian context, the ISAA is used by many government medical boards for disability certification purposes.

    ADOS-2 (Autism Diagnostic Observation Schedule, Second Edition): A structured observation where the clinician engages the child in specific play and social tasks. For Level 3, the child typically shows minimal response to the examiner, very limited communication, and intense repetitive behaviours.

    ADI-R (Autism Diagnostic Interview – Revised): A detailed parent interview covering developmental history, communication, social behaviour, and repetitive behaviours from early childhood onward.

    DSM-5 Criteria: The formal diagnostic framework. A Level 3 classification requires meeting all three social communication criteria and at least two of four restricted/repetitive behaviour criteria, with symptoms present from early development and causing significant functional impairment.

    Differentiating Level 3 from Other Levels

    Differentiating Level 3 from Other Levels

    A key part of the diagnosis is distinguishing Level 3 autism from Levels 1 or 2. Let us look at how Level 3 autism differs from levels 1 and 2:

    FeatureLevel 1 (Requiring Support)Level 2 (Substantial Support)Level 3 (Very Substantial Support)
    Social CommunicationCan speak in full sentences and engage in talk, but struggles with the “back-and-forth” flow of conversation.Speaks in simple sentences. Their interaction is limited to narrow special interests, and they have marked oddities in nonverbal communication.Very limited or no functional speech. They rarely initiate interaction and may only respond to very direct social approaches.
    Response to ChangeBecomes anxious when plans change, but can eventually adapt with some verbal coaching.Clear distress or difficulty changing focus. It is obvious to a casual observer that the person is struggling to switch tasks.Extreme distress or meltdowns when routines are altered. They have great difficulty redirecting their focus from a repetitive task.
    Social SkillsMay appear “awkward” or have trouble making friends, but desires social connection.Has marked gaps in social and nonverbal communication skills; may not seek out others unless they need something.Appears to be in their own world. They may not respond to their name or acknowledge the presence of others in the room.
    Daily Living SkillsCan often manage self-care and independent living with occasional guidance or organizational tools.Needs significant help with daily transitions and may require a structured environment or a part-time caregiver.Requires 24/7 supervision. They usually need full assistance with basic needs like dressing, hygiene, and safety.

    Communication in Level 3 Autism – AAC and Alternative Methods

    Communication in Level 3 Autism

    One of the most common fears parents carry into our conversations is this: “My child may never speak.” It is a real fear, and it deserves a real answer – not platitudes.

    For many children with Level 3 autism, spoken language is genuinely difficult to develop. But communication is not the same as speech. And that distinction is life-changing.

    What Is AAC?

    AAC – Augmentative and Alternative Communication – is an umbrella term for all the ways people communicate besides spoken words. It ranges from simple, low-tech tools to sophisticated electronic devices.

    AAC is not a last resort. It is not something you try when speech therapy has “failed.” It is a communication right – and the evidence is clear that introducing AAC early does not stop speech from developing. In fact, a systematic review published in Augmentative and Alternative Communication found that AAC interventions improved speech production in most participants, and no studies in the review reported a decrease in spoken language when AAC was used (Millar et al., 2006, via ASHA).

    Types of AAC

    Unaided AAC (no device needed):

    • Sign language – simplified sign systems like Makaton are used widely in autism support settings; they give the child a physical, embodied way to communicate
    • PECS (Picture Exchange Communication System) – the child hands a picture card to a communication partner to request an item or action; it is one of the most researched AAC approaches in autism and is highly practical for Indian home settings

    Aided AAC (uses a tool or device):

    • Low-tech communication boards – laminated picture boards or books organised by category (food, feelings, activities)
    • Speech-Generating Devices (SGDs) – dedicated electronic devices that produce spoken output when the child selects symbols or words
    • Tablet-based AAC apps – apps like Proloquo2Go, TouchChat, and LetMeTalk (free, open-source) turn an iPad or Android tablet into a communication device; these are increasingly accessible in India and can be customised to include the child’s home language

    How AAC Is Introduced

    AAC is introduced by a trained Speech-Language Pathologist, ideally one with specific AAC experience. The process typically involves:

    1. Assessment – understanding the child’s current communication abilities, motor skills, and sensory profile
    2. System selection – choosing the right AAC type and vocabulary based on the child’s needs
    3. Modelling – the therapist and parents use the AAC system themselves, showing the child how it works before expecting the child to use it
    4. Generalisation – practising AAC across settings: at home, at school, in the community

    Parents are central to AAC success. The more consistently the system is used at home, the faster the child learns.

    “Will AAC Stop My Child from Speaking?”

    This is the question we hear most often. The answer, backed by research, is no.

    ASHA’s evidence summary states clearly that AAC does not hinder speech development in the early stages of language acquisition (ASHA, 2023). A review of speech-generating device studies in autism found that 87% of participants showed improved vocal utterances, with no studies reporting decreased spoken language when devices were used.

    AAC gives your child a voice now – while speech therapy continues to work on spoken language alongside it. These are not competing approaches. They work together.

    Autism Therapies That Help

    Autism Therapies That Help

    There is no single therapy that “fixes” Level 3 autism – and anyone who tells you otherwise is not being straight with you. What works is a coordinated, intensive, individualised programme that addresses communication, behaviour, sensory processing, and daily living skills together.

    Applied Behaviour Analysis (ABA)

    ABA therapy is one of the most extensively researched interventions for autism. For Level 3, it typically involves intensive one-to-one sessions – often 20–40 hours per week in early intervention – focused on building foundational skills: making requests, following simple instructions, tolerating transitions, and reducing behaviours that cause harm or prevent learning.

    Modern ABA is naturalistic and play-based, not the rigid, drill-based approach of earlier decades. The goal is to make learning feel meaningful and motivating for the child.

    Speech and Language Therapy

    Speech therapy for Level 3 autism goes far beyond “practising words.” It addresses the full communication profile: functional requesting, joint attention, understanding language, and – critically – AAC implementation.

    A good SLP working with a Level 3 child will spend as much time coaching parents as they do working directly with the child. The hours between therapy sessions are where the real learning happens.

    Occupational Therapy

    Occupational therapy builds the functional independence skills that make daily life more manageable – for the child and for the family. This includes dressing, eating, toileting, fine motor skills, and the ability to tolerate and navigate different environments.

    OT also addresses the sensory processing differences that underlie so much of the behavioural picture in Level 3 autism.

    Sensory Integration Therapy

    Sensory integration therapy uses structured, playful activities – swings, weighted blankets, tactile play, proprioceptive input – to help the nervous system process sensory information more efficiently. For a child whose sensory world is overwhelming, this is not a luxury. It is foundational.

    Techniques like deep pressure, brushing protocols, and vestibular activities can significantly reduce the frequency and intensity of meltdowns by addressing their root cause: a nervous system that is not regulating sensory input effectively.

    Can Level 3 Autism Improve?

    Can Level 3 Autism Improve?

    It is vital to note that these levels are not permanent “labels” that never change. When we ask whether level 3 autism can improve, we are looking at the spectrum’s fluidity.

    With intensive early intervention, especially when identifying level 3 autism in toddler years, a child can gain communication skills that move them into a lower support category over time.

    What Improvement Means

    • Better communication skills
    • Reduced behavioral challenges
    • Increased ability to perform daily tasks

    However, level 3 autism is a lifelong condition. The goal is not to “cure” it but to help the individual reach their full potential.

    Therapies That Help

    • Applied Behavior Analysis (ABA): This highly structured therapy focuses on reinforcing positive behaviours and teaching essential life skills. For level 3 autism, intensive one-on-one sessions help reduce severe challenges—like self-injury—while building foundational communication.
    • Speech Therapy: Speech therapy addresses profound communication barriers, helping individuals safely express their needs and emotions. When spoken language isn’t possible, therapists introduce Alternative and Augmentative Communication (AAC) tools like speech-generating tablets.
    • Occupational Therapy: Occupational therapy builds functional independence by teaching daily living skills like dressing, eating, and personal hygiene. Strategies are customised to the individual’s physical abilities to improve motor skills and overall quality of life.
    • Sensory Integration Therapy: Because level 3 autism often involves severe sensory sensitivities that trigger distress, this therapy uses structured activities to regulate the nervous system. Techniques like deep pressure help individuals process sensory input safely and reduce anxiety.

    Can Level 3 Autism Live Independently?

    Supported living models and community frameworks empower individuals with level 3 autism

    This is the fear that keeps parents awake at 2 a.m. – “What happens to my child when I am no longer here?”

    The honest answer: most individuals with Level 3 autism will need some level of support throughout their lives. Full independent living – managing finances, cooking, navigating public transport, holding a job – is not a realistic goal for the majority. But that framing misses something important.

    Independence is not binary. There is a vast spectrum between “completely dependent” and “fully independent” – and most adults with Level 3 autism live somewhere in that middle ground, with the right support structures in place.

    Some individuals, with years of intensive therapy and strong family involvement, develop enough skills to manage semi-structured supported living – where they have their own space, their own routines, and their own choices, with staff support available when needed. This is not a lesser life. It is a dignified, self-determined life.

    In India, residential care options for adults with high-support autism have historically been limited. Most families have relied entirely on home-based care, often at enormous personal cost to parents and siblings. That is changing.

    India Autism Center’s residential ecosystem was built specifically to address this gap. It is a first-of-its-kind holistic residential community in India – designed not as an institution, but as a living environment where adults with autism can have structured routines, therapeutic support, meaningful activities, and genuine community. For families who are beginning to think about long-term planning, it is worth knowing that this option exists in India – because for a long time, it simply did not.

    The most important thing you can do right now is not to solve the independence question – it is to invest in the therapies and skills that give your child the best possible foundation. The rest builds from there.

    Level 3 Autism Life Expectancy

    Level 3 Autism Life Expectancy

    Parents sometimes search this question in the middle of the night, terrified of what they might find. Let’s address it directly and honestly.

    People with autism, including autism Level 3, do not have a fundamentally different biological lifespan from the general population. Autism itself is not a life-shortening condition.

    However, research does show that autistic individuals – particularly those with higher support needs – face elevated risks from co-occurring conditions and safety factors that can affect lifespan:

    • Co-occurring medical conditions – epilepsy affects approximately 20–30% of people with autism, and the rate is higher in those with intellectual disability; gastrointestinal conditions, sleep disorders, and metabolic issues are also more common
    • Accidental injury and safety risks – individuals with Level 3 autism may have limited awareness of danger (traffic, water, heights), and wandering (elopement) is a significant safety concern
    • Limited access to healthcare – communication difficulties can make it hard to report pain or illness, leading to delayed diagnosis and treatment of medical conditions

    The most important factors for quality of life and longevity are: consistent medical care, a safe living environment, and a support team that knows the individual well enough to notice when something is wrong.

    Quality of life – not statistics – is the right frame for this question. With the right support, people with Level 3 autism live lives that are meaningful, connected, and full of moments that matter.

    Myths About Level 3 Autism

    Myths About Level 3 Autism

    There are several myths that people believe when it comes to Level 3 autism, which can create confusion and unnecessary fear for families.

    Myth 1: People with level 3 autism cannot learn

    Reality: Individuals with asd level 3 can learn with structured support, therapies, and consistent routines.

    Myth 2: They cannot communicate

    Reality: Communication may not necessarily be verbal; however, tools like gestures, pictures, or devices can be quite helpful to express needs.

    Myth 3: They do not feel emotions

    Reality: People with autism level 3 are known to experience emotions on a deeper level, but may express them differently.

    Myth 4: Level 3 autism cannot improve

    Reality: While lifelong, skills can improve with therapy. Progress may be slow but meaningful.

    Myth 5: They cannot live a meaningful life

    Reality: With the right kind of support, individuals with level 3 autism spectrum disorder can enjoy routines, relationships, and fulfilling experiences.

    Understanding the true meaning of level 3 autism helps replace fear with informed support and acceptance.

    Conclusion

    Understanding what level 3 autism is goes beyond labels. It is about recognising the level of support an individual needs and responding with patience, structure, and informed care.

    While level 3 autism spectrum disorder presents significant challenges in communication, behavior, and daily functioning, it does not define a person’s potential or worth.

    With early diagnosis, consistent therapies, and a robust support system, people with autism level 3 can make steady progress and lead fulfilling lives in their own way. The journey requires long-term commitment from families and caregivers, but the right interventions can be life-changing.

    The key is awareness and acceptance. When we truly understand the meaning of level 3 autism, we move closer to creating an environment where individuals are supported, respected, and given every opportunity to thrive.

    Frequently Asked Questions

    What is level 3 autism?

    Level 3 autism is a severe form of autism spectrum disorder, where individuals need very substantial support in communication, behavior, and daily living activities. It affects how a person interacts and functions every day.

    How is level 3 autism different from other levels?

    Unlike levels 1 and 2, level 3 autism spectrum disorder involves more severe challenges, including minimal communication and a greater need for supervision and structured support.

    Can a person with level 3 autism live independently?

    The answer to whether a person with level 3 autism can live independently varies. Most individuals need lifelong support, but some may gain partial independence with proper training and structured environments.

    How is level 3 autism diagnosed?

    Diagnosis of level 3 autism spectrum disorder is done through developmental screenings, behavioral assessments, and guidelines from DSM-5. It helps to understand the severity and support needs.

    Can children with level 3 autism go to school?

    Yes, children with level 3 autism can attend school through special education programs that mainly focus on communication, behavior, and life skills development.

    Disclaimer: This article is intended for educational and informational purposes only. It is not a substitute for professional medical advice, diagnosis, or treatment. If you are pregnant or have concerns about medication use during pregnancy, please consult a qualified healthcare provider. If your child has received an autism diagnosis and you have questions about causes or support, please reach out to a trained specialist or an autism-focused organisation for guidance.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.

    Useful Sources

    DSM-5 Autism Diagnostic Criteria - Autism Speaks

    National Trust Act - National Trust India

    NIEPID - National Institute for Empowerment of Persons with Intellectual Disabilities

    Dawson et al. (2010) - Early Start Denver Model RCT, Pediatrics

    Millar et al. - AAC and Speech Production Systematic Review, via PMC

  • Short-Term Stay for Autism: What It Means

    Short-Term Stay for Autism: What It Means

    When you care for an autistic individual, you do it with love—but also with constant responsibility. I understand how overwhelming it can feel at times. That’s where a short-term stay for autism can truly help.

    In this guide, I will walk you through everything you need to know about a short-term stay, how it connects with assisted living, and why it can be a powerful support system for both you and your loved one.

    What is a Short-Term Stay in Autism Care?

    What is a Short Term Stay in Autism Care

    Ashort-term stay is a temporary residential care option designed specifically to support autistic individuals in a structured and safe environment—for a limited period of time.

    Let me explain this more practically.

    Think of it as a planned, short break from home, where your child or loved one stays at a specialised centre that understands autism deeply. This stay could last:

    • A few days
    • A weekend
    • A couple of weeks

    Now, this is not just about “staying away from home.”

    Instead, during a short-term stay, your loved one:

    • Follows a structured daily routine
    • Receives professional care and supervision
    • Participates in therapies and skill-building activities
    • Learns to adapt to a new environment gradually

    At the same time, you get the space to:

    • Rest and recharge
    • Focus on other responsibilities
    • Plan long-term care, including assisted living options

    Read: Is a Residential Autism Program Worth the Cost?

    Why You Should Consider a Short-Term Stay

    Why You Should Consider a Short Term Stay

    Let’s slow this down and understand it a bit more deeply—because this decision is often emotional, not just practical.

    A short-term stay is not about “sending your child away.” Instead, it is about sharing the responsibility of care in a healthy and sustainable way.

    Here’s what that really means for you and your loved one:

    1. You Get Respite Without Guilt

    Caregiving is a full-time role. Over time, it can affect your:

    • Energy
    • Mental health
    • Patience

    Now, you may feel guilty even thinking about taking a break. That’s natural. But here’s the truth—you cannot pour from an empty cup.

    A short-term stay gives you:

    • Time to rest
    • Space to focus on other family needs
    • A chance to reset emotionally

    And when you come back, you are more present, calm, and effective as a caregiver.

    2. Your Loved One Builds Independence

    This is one of the most powerful benefits.

    When your child or adult steps into a short-term stay, they are gently encouraged to do things on their own:

    • Follow routines without constant prompts
    • Make small choices
    • Interact with new people

    At home, we often (understandably) do a lot for them. But in a structured setting, they get the chance to try, learn, and grow.

    Over time, this builds:

    • Confidence
    • Adaptability
    • Self-reliance

    These are essential life skills, especially if you are considering assisted living in the future.

    3. It Prepares for Assisted Living Gradually

    Let’s be honest—thinking about assisted living can feel overwhelming.

    Questions like:

    • Will my child adjust?
    • Will they feel safe?
    • Will they accept the change?

    A short-term stay helps answer these questions—step by step.

    It acts as a trial experience, where:

    • Your loved one gets familiar with a residential setting
    • You observe how they respond
    • The care team understands their needs better

    Want to know more? Get in touch with us.

    How Does Short-Term Stay Support Autism Development?

    How Short Term Stay Supports Autism

    A short-term stay is not just about temporary care. It actively contributes to your loved one’s growth and development in a structured, supportive way. Let me explain each aspect briefly so you can clearly understand its value.

    Structured Routine

    Autistic individuals often feel more comfortable when their day follows a predictable pattern. During a short-term stay, routines are carefully planned and consistently followed.

    For example, there are fixed times for:

    • Waking up
    • Meals
    • Activities
    • Rest

    Because of this structure, your loved one feels more secure and less anxious. Over time, this consistency helps improve focus, behaviour, and overall emotional stability.

    Skill Building

    A key goal of any short-term stay is to build everyday life skills.

    In a supportive setting, individuals are gently encouraged to:

    • Take care of personal hygiene
    • Eat independently
    • Organise their belongings
    • Communicate their needs

    These may seem like small steps. However, they play a big role in developing independence. This becomes especially important if you are considering assisted living in the future.

    Social Interaction

    Many autistic individuals find social situations challenging. A short-term stay creates safe opportunities to interact with others.

    Through guided group activities, your loved one learns to:

    • Share space with peers
    • Participate in simple group tasks
    • Understand social cues gradually

    Because this happens in a controlled environment, it reduces pressure and builds confidence step by step.

    Behavioural Support

    During a short-term stay, trained professionals observe and support behaviour using structured approaches.

    They help your loved one to:

    • Manage anxiety or frustration
    • Reduce challenging behaviours
    • Develop coping strategies

    This is done with patience and consistency. As a result, your loved one becomes better at handling changes and expressing emotions.

    Sensory-Friendly Environment

    Many autistic individuals are sensitive to noise, light, or crowded spaces. Good short-term stay facilities for autism are designed to be sensory-friendly.

    This includes:

    • Calm, clutter-free spaces
    • Controlled noise levels
    • Soothing colours and lighting

    Such an environment helps your loved one feel comfortable and reduces sensory overload.

    📥 Free download: Printable daily routine chart for autistic children

    Short-Term Stay vs Assisted Living: Key Differences

    AspectShort Term StayAssisted Living
    DurationTemporary (few days to a few weeks)Long-term or ongoing stay
    PurposeRespite, trial experience, and exposure to structured careStable living with continuous support and development
    Commitment LevelNo long-term commitmentRequires long-term planning and decision-making
    Care StructureStructured but flexibleHighly structured and consistent
    Focus AreaAdjustment, routine-building, and short-term skill developmentIndependence, daily living support, and long-term growth
    Family InvolvementVery high; you stay closely involvedTemporary (a few days to a few weeks)
    Emotional AdjustmentModerate; you remain involved, but not daily caregivingTakes time; involves deeper lifestyle adjustment
    Environment ExposureHelps individuals get used to residential settingsBecomes the individual’s primary living environment
    Use CaseWhen you need a break, during emergencies, or to test readinessWhen long-term support and supervised living are needed
    Role in TransitionActs as a bridge to assisted livingFinal or ongoing stage of supported independent living

    Want to know more? Get in touch with us.

    When Should You Choose a Short-Term Stay for Autism?

    When Should You Choose a Short Term Stay for Autism?

    This is a very practical question—and honestly, there is no “perfect time.” Instead, there are certain situations where a short-term stay becomes especially helpful for both you and your loved one.

    Let me explain each situation clearly so you can relate it to your own circumstances.

    When You Feel Caregiver Burnout

    Caring for an autistic individual is a full-time responsibility. Over time, it can become physically and emotionally exhausting.

    You might notice:

    • Constant fatigue
    • Irritability or stress
    • Lack of personal time

    At this point, a short-term stay gives you the chance to rest and recharge. And this is important—because when you feel better, you provide better care.

    When You Need to Travel or Handle Emergencies

    Life can be unpredictable. There may be times when you:

    • Need to travel for work or family
    • Face a medical emergency
    • Have urgent responsibilities

    In such situations, a short-term stay ensures your loved one continues to receive structured and professional care, without disruption in routine.

    When Your Loved One is Transitioning to Adulthood

    As autistic individuals grow older, their needs change. The focus slowly shifts from dependence to building independence.

    A short-term stay helps during this phase by:

    • Introducing structured living outside the home
    • Teaching daily life skills
    • Encouraging responsibility

    This makes the transition smoother and more natural over time.

    When You Want to Explore Assisted Living

    Thinking about assisted living can feel overwhelming. You may not be sure how your loved one will respond.

    A short-term stay works as a safe starting point. It allows you to:

    • Observe how they adjust to a residential setup
    • Understand their comfort level
    • Identify support needs

    So instead of making a big decision suddenly, you take a step-by-step approach.

    When Social Exposure is Limited

    If your loved one mostly stays at home, they may have fewer opportunities to interact with others.

    During a short-term stay, they get:

    • Exposure to peers
    • Opportunities for group activities
    • Guided social interaction

    This helps improve confidence and reduce social anxiety gradually.

    When Routine Needs Reinforcement

    Sometimes, maintaining structure at home becomes difficult due to daily demands.

    A short-term stay reinforces:

    • Consistent routines
    • Behavioural expectations
    • Daily living habits

    This structure often carries forward even after your loved one returns home.

    Want to know more? Get in touch with us.

    What Happens During a Short-Term Stay?

    What Happens During a Short Term Stay?

    A short-term stay is carefully designed to provide a balance of care, structure, and development. It is not just about accommodation—it is a planned, supportive experience that helps your loved one feel secure while learning new skills. Let’s understand each part in a bit more detail.

    Daily Life

    • Structured routine: Each day follows a consistent schedule, including wake-up time, meals, activities, and rest, which helps reduce uncertainty and anxiety.
    • Balanced activities: The day is thoughtfully divided between therapy, leisure, and relaxation so your loved one stays engaged without feeling overwhelmed.
    • Gradual independence: Individuals are encouraged to complete simple daily tasks on their own, helping them build confidence step by step.

    Therapies and Activities

    • Skill-based therapies: Professional sessions like occupational or speech therapy focus on improving communication, motor skills, and everyday functioning.
    • Sensory-friendly activities: Activities are designed to suit sensory needs, helping individuals stay calm, focused, and comfortable.
    • Group interaction: Guided group tasks encourage social engagement, helping your loved one slowly build interaction and cooperation skills.

    Supervision and Safety

    • Trained caregivers: Experienced staff are present round the clock to guide, support, and respond to individual needs with care and understanding.
    • Personalised attention: Care plans are often tailored, ensuring your loved one receives support based on their specific strengths and challenges.
    • Safe environment: The facility is designed with safety measures, including secure spaces and emergency protocols, so you can feel reassured at all times.

    Choosing the Right Short-Term Stay Facility

    Choosing the Right Short Term Stay Facility

    Selecting the right short-term stay facility is one of the most important decisions you will make. The quality of the environment, staff, and approach can directly impact your loved one’s comfort and development. So, let me guide you through what you should look for—clearly and practically.

    Autism-Specific Expertise

    • Specialised understanding: Choose a facility that focuses on autism, so they understand sensory needs, communication styles, and behavioural patterns.
    • Tailored interventions: Such centres design programs specifically for autistic individuals rather than using a general care approach.

    Structured Yet Flexible Programs

    • Consistent routine: A well-planned daily schedule helps your loved one feel secure and reduces anxiety.
    • Individual flexibility: At the same time, the program should adapt to your loved one’s pace, preferences, and comfort levels.

    Qualified and Trained Staff

    • Professional expertise: Look for trained therapists, special educators, and caregivers who have experience in autism care.
    • Compassionate approach: Beyond qualifications, the staff should be patient, empathetic, and responsive to individual needs.

    Transition to Assisted Living Options

    • Continuity of care: Facilities that also offer assisted living can provide a smoother transition if you consider long-term support later.
    • Familiar environment: Your loved one already knows the space and people, which reduces stress during future transitions.

    Family Communication and Involvement

    • Regular updates: You should receive consistent feedback about routines, behaviour, and progress during theshort-termm stay.
    • Open communication: A good facility encourages your involvement and listens to your concerns and input.

    Safety and Infrastructure

    • Secure environment: The space should be designed to prevent risks, with proper supervision and safety measures in place.
    • Sensory-friendly design: Calm lighting, minimal noise, and clutter-free spaces help your loved one feel comfortable and regulated.

    Trial and Observation Option

    • Short trial stays: A good facility allows you to start with a brief short-term stay to assess comfort and suitability.
    • Observation opportunity: This helps you evaluate how your loved one adapts before making longer commitments.

    Want to know more? Get in touch with us.

    How to Prepare Your Loved One for a Short-Term Stay

    How to Prepare Your Loved One for a Short Term Stay

    Preparing your loved one for a short-term stay is just as important as choosing the right facility. A thoughtful and gradual approach can reduce anxiety, build trust, and make the experience smoother for both of you. Let me walk you through how you can do this effectively.

    Visit the Facility Beforehand

    • Familiarisation: Take your loved one to visit the centre so they can see the space, meet staff, and feel more comfortable with the environment.
    • Reduce anxiety: When the place is no longer “new,” it lowers fear and resistance during the actual stay.

    Share Routines and Preferences

    • Consistency in care: Inform the staff about daily habits, food preferences, triggers, and calming techniques to maintain familiarity.
    • Personalised support: This helps caregivers adjust their approach according to your loved one’s unique needs.

    Pack Familiar Items

    • Emotional comfort: Carry favourite items like toys, blankets, or books to create a sense of home in the new environment.
    • Easier adjustment: Familiar objects can soothe anxiety and help your loved one settle in faster.

    Talk Positively About the Experience

    • Build trust: Explain the short-term stay in a calm and encouraging way so your loved one feels safe and supported.
    • Set expectations: Let them know what to expect, using simple and reassuring language to avoid confusion.

    Start with Short Durations

    • Gradual exposure: Begin with a short stay, like a day or weekend, before moving to longer durations.
    • Build confidence: This step-by-step approach helps your loved one adjust without feeling overwhelmed.

    Stay Calm and Reassuring

    • Emotional transfer: Your feelings influence your loved one—if you stay calm, they are more likely to feel secure.
    • Consistent reassurance: Let them know you will return and that they are safe, which builds trust in the process.

    Coordinate with the Care Team

    • Clear communication: Stay in touch with caregivers to understand how your loved one is adjusting during the stay.
    • Ongoing support: This collaboration ensures any concerns are addressed quickly and effectively.

     Why Choose IAC’s Short Stay Program

    We provide a safe and supportive residential for autism for assisted living and residential environment, where your child can learn, practice, and grow every day.  Our focus is on your child’s overall development across key areas:

    • Cognitive and Learning Skills: We help your child build attention, memory, and early learning abilities through structured activities.
    • Behavioural and Emotional Regulation: We support your child in managing emotions, reducing challenging behaviours, and developing calm responses.
    • Communication and Social Skills: We work on helping your child express needs, understand language, and interact confidently with others.
    • Daily Living and Independence: We teach essential life skills such as eating, dressing, hygiene, and following routines.

    Customised Short Stay Program for Your Child

    Ages 3–6: Early Intervention

    We focus on communication, play, and early developmental skills, while also guiding parents on how to support learning at home.

    Ages 7–12: Skill Development

    We work on independence, behaviour management, social interaction, and functional academics.

    Ages 13–15: Emotional and Social Understanding

    We help children navigate emotional changes, build social awareness, and strengthen academic skills.

    Ages 16–19: Preparing for Adulthood

    We focus on vocational training, independence, and understanding relationships and responsibilities.

    Want to know more? Get in touch with us.

    Conclusion

    At the end of the day, you want one thing—a safe, fulfilling life for your loved one.

    A short term stay is not just a service. It is:

    • A support system
    • A learning environment
    • A stepping stone to independence

    And when combined with the right assisted living approach, it can truly transform lives.

    Frequently Asked Questions

    How long can a short term stay last?

    A short-term stay can range from a few days to a few weeks, depending on your needs and the facility’s program. You can start small and gradually increase the duration as your loved one becomes comfortable.

    Will my loved one feel anxious during a short term stay?

    It is natural for some individuals to feel anxious initially. However, with proper preparation, familiar items, and supportive staff, most individuals gradually adjust and feel more comfortable within a structured environment.

    Is a short term stay safe for autistic individuals?

    Yes, a well-designed short-term stay facility provides 24/7 supervision, trained caregivers, and a sensory-friendly environment to ensure safety, comfort, and proper care at all times.

    How is short term stay different from assisted living?

    A short term stay is temporary and mainly used for respite, trial, or transition purposes. In contrast, assisted living is a long-term residential arrangement focused on continuous support and independent living.

    Can a short term stay help prepare for assisted living?

    Absolutely. A short-term stay acts as a stepping stone by helping your loved one adjust to new environments, routines, and caregivers—making the transition to assisted living smoother and less stressful.

    For expert insights, support services, and inclusive learning initiatives, visit the India Autism Center.